Top Physician Skill -Listening

One physician I’ve worked with recalls a mother of a patient telling him, ‘I really wish my husband would listen the way you do.’  This particular physician replied, ‘Well, just pay him $100 every time you say something.’

While this mother had a good experience with her physician (despite the cost), not all physicians are listening enough.  Here’s a link to a NY Times article that discusses this problem: Doctor, Shut Up and Listen

Here’s an excerpt:

A doctor’s ability to explain, listen and empathize has a profound impact on a patient’s care. Yet, as one survey found, two out of every three patients are discharged from the hospital without even knowing their diagnosis. Another study discovered that in over 60 percent of cases, patients misunderstood directions after a visit to their doctor’s office. And on average, physicians wait just 18 seconds before interrupting patients’ narratives of their symptoms. Evidently, we have a long way to go….

Observation soon revealed that physicians introduced themselves on only about one in four occasions…

Brief, rushed physician encounters were common, with limited opportunity for questions. A lack of empathy was often apparent…

We developed a physician-training program, which involved mock patient interviews and assessment from the actor role-playing the patient. Over 250 physicians were trained using this technique. We also arranged for a “physician coach” to sit in on real patient interviews and provide feedback.

Over the next two years, patient satisfaction with doctors, as measured by a standard questionnaire, moved the hospital’s predicted score up in national rankings by a remarkable 40 percentile points.

My take: I wonder about the accuracy of the information presented in this article.  Despite this, the message is clear that patients want to make sure that physicians are listening to them.

Another NY Times article worth a glance: The Drugs That Companies Promote to Doctors Are Rarely Breakthroughs  One quote: If a drug is either the first to treat a disease or is much better than existing drugs, said Dr. Sidney Wolfe, the founder and now senior adviser to Public Citizen’s Health Research Group, “they ‘sell themselves’ on the merits of their unique benefits.”

Dr. Oz Gives Out Wrong/Baseless Advice More Often Than Right

Dr. Oz, “America’s doctor,” while wildly popular, continues to receive bad press regarding the accuracy of his advice.  Recent Washington Post link: “Half of Dr. Oz’s Medical Advice is Baseless or Wrong” (Thanks to Eric Benchimol’s twitter feed for this link)

An excerpt:

The British Medical Journal, which on Wednesday published a study analyzing Oz’s claims along with those made on another medical talk show. What they found wasn’t reassuring. The researchers, led by Christina Korownyk of the University of Alberta, charged medical research either didn’t substantiate — or flat out contradicted — more than half of Oz’s recommendations. “Recommendations made on medical talk shows often lack adequate information on specific benefits or the magnitude of the effects of these benefits,” the article said. “… The public should be skeptical about recommendations made on medical talk shows.”

Related blogs:

Mobile Health Apps

Last month I posted some notes from Brennan Spiegel who gave the keynote address at NASPGHAN (“The future of gastrointestinal disease and symptom …).  This past month, he reviewed mobile health apps.  Here’s the link: AGA Perspectives on mHealth Apps

Here’s an excerpt:

The IMS Institute for Healthcare Informatics evaluated each of the apps on the market and concluded that well over 90 percent were of low quality…

IMS points to iTriage as a model for evaluation. iTriage collects signs and symptoms, crunches the input through algorithms, yields a differential diagnosis, and suggests an action plan and list of appropriate local providers. “Virtual visit” apps like HealthTap, Teladoc, American Well and MDLive go a step further by offering patients direct and immediate access to a physician through their smartphone or tablet device. For $49 on average, physicians can conduct a virtual face-to-face interview, make a diagnosis and even send prescriptions. The app “Pager” goes yet a step further. Founded by the team that developed Uber — the wildly successful car service app — Pager allows patients to select among a panel of doctors and obtain rapid house calls for $199. Insurance is now starting to cover some of the virtual visits and app-generated house calls.

What Better Care Looks Like -Five Examples

From Harvard Business Review and the New England Journal of Medicine: Five examples of Better Care

  1. Increased transparency with patient feedback at University of Utah
  2. Shared responsibility to coordinate care experience at Mayo Clinic
  3. Teamwork with all members of health care team at Northwestern
  4. Addressing socioeconomic barriers at Contra Costa
  5. Consolidating care in London to specialized centers to improve outcomes and costs (with stroke)

What sets your institution apart from others?

Microcytic Anemia Review

A useful review of microcytic anemia (NEJM 2014; 371: 1324-31) discusses the most common causes, mechanisms and treatment of microcytic anemia.

Common causes discussed include thalassemia, iron deficiency anemia, and anemia of inflammation.  With the latter, the authors review the pathophysiology: “the cause of this anemia is twofold. First, renal production of erythropoietin is suppressed by inflammatory cytokines, resulting in decreased red-cell production. Second, lack of iron availability for developing red cells can lead to microcytosis.  The lack of iron is largely due to the protein hepcidin, an acute-phase reactant that leads to both reduced iron absorption and reduced release of iron from body stores.”

Treatment of iron deficiency anemia –pointers:

  • Ferrous sulfate (325 mg [65 mg of elemental iron] orally three times a day -considered first line for adults.  Ferrous gluconate at a daily dose of 325 mg [35 mg elemental] is an alternative.
  • “Several trials suggest that lower doses of iron, such as 15 to 20 mg of elemental iron daily can be as effective as higher doses and have fewer side effects.”
  • “There are many oral iron preparations, but no one compound appears to be superior to another.”
  • In those with an inadequate response to oral iron therapy, parenteral iron can be helpful.  The authors note that low-molecular-weight iron dextran (INFeD) is “associated with an incidence of reactions that is similar to that with the newer products but allows for higher doses of iron replacement.”  Typical dosing for adults: 25 mg test dose, and if tolerated for 1 hr, can give 975 mg (1000 mg total) over 4-6 hours.  The low-molecular-weight iron dextran should not be used in patients with previous iron dextran hypersensitivity reactions.
  • Alternative IV iron products: Ferric gluconate [Ferrlecit] 125 mg adult dose over 1 hour -given weekly (8 doses = 1000 mg) or Iron Sucrose [Venofer] 200 mg adult dose over 15-60 min, 300 mg over 1.5 hr, or 500 mg over 4 hr; can repeat in subsequent sessions until total dose of 1000 mg.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

More Measles Cases -Here’s the Data

This past month a recent perspective article (NEJM 2014; 371: 1661-3) provides an update on measles and the problems with vaccination rates.

Key points:

  • More measles cases in 2014 (592 thru Aug 29) than in any year in the past 20.  Already, the number of cases this year is >3-fold the number in 2013 and ~10-fold more than in 2012
  • Most cases are due to infections acquired during travel or due to cases being brought into U.S. by foreign travelers
  • Problem has expanded due to increasing number of unvaccinated children.  Vaccines “that remain in the vial are completely ineffective.”
  • Measles remains one of the most contagious illnesses and typically one person can infect up to 18 susceptible persons.  Due to its contagiousness, a high level of herd immunity (>92-94% immune) is needed to prevent sustained spread of virus.
  • Measles can be deadly with case fatality rate of 0.2% to 0.3% in the developed world and much higher in the developing world (2-15%).
  • Even a few cases are very expensive to control. A 2004 Iowa outbreak of only three patients cost more than $140,000 to contain/investigate.  An outbreak in Arizona with only 7 patients cost more than $800,000.

Related blog posts:

“The future of gastrointestinal disease and symptom monitoring: biosensor, E-portal, and social media”

At this year’s NASPGHAN meeting, the keynote lecture was given by Brennan Spiegel.  (Brennan Spiegel, MD (@BrennanSpiegel) | Twitter) This was a great talk!

This blog entry has abbreviated/summarized the presentation. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.

Challenges in healthcare:

  • Time with patient is limited/poorly-timed in comparison to health care needs.
  • Care is reactive rather than proactive.
  • Care is expensive.

We spend all our time within walls of our clinic/hospital, but patients spend 99% time outside


How do we tailor care to the individual and make it more cost-effective? How do we get there?  Potential/Emerging Tools:

    • Patient provider portals (including mobile)
    • Social media
    • Wireless biosensors


Key question for patients: What is the most important goal for you/your family today?

How to improve communication with family? Electronic medical records often designed for billing rather than educating

MyGiHealth website/soon-to-be-app.  Here’s a link to YouTube video introduction.

  • HISTORY: Trained computer to interview patient re: abdominal pain –where, timing, risk factors for H pylori, etc.
  • Symptoms and severity: constipation, abdominal pain, gas/bloating, heartburn, diarrhea, dysphagia, incontinence, nausea/vomiting (Promise scales –percentiles).
  • Computer history looked better than history by physician (example below with fictional patient). If history obtained prior to physician coming into room, this would allow physician more time to communicate with patient rather than documenting (Related post: Aptly titled “The Cost of Technology” | gutsandgrowth)
  • Man vs Machine (Spiegel in press Am J Gastro 2014). History performed well with regard to billing complexity and completeness.
  • THIS IS COOL!
  • Physician still needed to analyze information and make diagnosis/treatment plan.
  • Also website/app with EDUCATION applicable to patient.
History by computer outperformed physicians

History by computer outperformed physicians

Obtaining information outside the confines of the office can help overcome Hawthorne effect. (Related blog post: Checklists -Helpful? Overhyped? Hawthorne Effect …). Passive vs Active monitoring.

Twitter: “What you say on twitter may be seen by everyone all over the word instantly”

  • Tool for epidemiologic data.
  • Marketing/advertising
  • Recruiting for clinical studies
  • Measure consumer sentiment
  • Educate patients/providers
  • Forge patient affinity groups
  • Monitor patients for clinical practice
  • Help to manage and direct care

Mayo clinic is studying the impact of social media.

Example of patients initiating research. “Spontaneous Coronary Artery Dissection: A Disease-Specific Social Networking Community-Initiated Study” Lead author: Marysia Tweet

Biosensors:

  • “91% of people keep their phone within 3 feet of themselves 24 hours a day.”
  • Can be used to track intake of food, air quality, movements etc
  • Current sensors: Fit bit, amigo (?sp), shine (?sp), Zeo (for sleep) others.
  • Fitbit: Calories, distance, active time, sleep time
  • More advanced sensors for athletes. Stride dynamics can predict marathon winner at mile 16!
  • Wireless sleep (eg. Zeo) monitor equivalent to formal sleep study
  • Q Sensor –can measure stress: physical ,cognitive, emotional (watching horror movie)
  • Hapi fork –can tell if you are eating too fast (correlated with BMI)
  • Proteus –monitors intake
  • Propeller –monitors MDI use for asthma (FDA approved)
  • AbStats Digestion Sensor –adheres to abdomen and can provide neurogastroenterology data. Green light –will tolerate feeds, Yellow light –will tolerate clears

75,000 health apps available at this time.

Recommended Reading by Dr. Spiegel: The Creative Destruction of Medicine by Eric Topol.  The Creative Destruction of Medicine: How the Digital …


“Decision Fatigue” & 1000 Posts

This post is number 1000!  I don’t think this fact is related to “decision fatigue.”

From NY Times –here’s the link: Decision Fatigue for Physicians

Here’s an excerpt:

The phenomenon of “decision fatigue” has been found in judges, who are more likely to deny bail at the end of the day than at the beginning. Now researchers have found…As the day wears on, doctors become increasingly more likely to prescribe antibiotics even when they are not indicated.

For the study, published in JAMA Internal Medicine, scientists analyzed diagnoses of acute respiratory infections in 21,867 cases over 18 months in primary care practices in and near Boston.

In two-thirds of the cases, antibiotics were prescribed even though they were not indicated… Over all, compared to the first hour, the probability of a prescription for antibiotics increased by 1 percent in the second hour, 14 percent in the third hour and 26 percent in the fourth.

For pediatric gastroenterologists, what do you think happens more often (or less often) due to decision fatigue?  excessive/less testing? excessive/less use of medications (like proton pump inhibitors)?

For Halloween yesterday –some people had some great outfits.

That's Dinesh under that mask

That’s Dinesh under that mask

Wrongful Conviction: HCV Acquitted of Causing Diabetes & a Word on Ebola

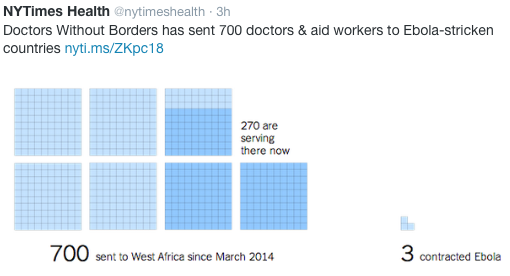
First about Ebola –here’s the Ebola recommendation from the NEJM editors regarding quarantine:

An excerpt:

The governors of a number of states, including New York and New Jersey, recently imposed 21-day quarantines on health care workers returning to the United States from regions of the world where they may have cared for patients with Ebola virus disease. We understand their motivation for this policy — to protect the citizens of their states from contracting this often-fatal illness. This approach, however, is not scientifically based, is unfair and unwise, and will impede essential efforts to stop these awful outbreaks of Ebola disease at their source, which is the only satisfactory goal…We should be honoring, not quarantining, health care workers who put their lives at risk not only to save people suffering from Ebola virus disease in West Africa but also to help achieve source control, bringing the world closer to stopping the spread of this killer epidemic.

Take-home message: Read the entire editorial why quarantine is not the right approach for asymptomatic returning health care workers.

Direct Ebola Risk to Health Care Workers

Direct Ebola Risk to Health Care Workers

Now in followup to yesterday’s post about HCV and diabetes:

Even Perry Mason would have had a difficult time proving hepatitis C virus (HCV) did not cause diabetes until a recent publication (Hepatology 2014; 60: 1139-49, editorial 1121-23).

In this study using population-based data from the U.S. National Health and Nutrition Examination Survey (NHANES) with 15,128 adult participants, the authors show that the prevalence of diabetes and prediabetes did not differ by HCV status.  The authors used standardized definitions for diabetes and prediabetes and adjusted for major confounders.  The authors did note a relationship between elevated alanine aminotransferase (ALT) with diabetes regardless of HCV status.  In their cohort, 56.7% had normal glucose, 32.8% had prediabetes, 3.2% had undiagnosed diabetes, and 7.3% had diagnosed diabetes.  The mean age progressively increased in these groups: 40.8 years, 51.9 years, 58.9 years, and 59.2 years respectively.

Among those with diabetes, 10.5% were HCV RNA-negative and 12.0% were HCV RNA-positive –unadjusted for ALT values; the unadjusted HCV antibody status was nearly identical at 10.5% and 10.2% respectively. After adjustment, the OR for being HCV RNA-positive was 1.06 (P=0.53) with confidence limits of 0.59-1.90.

In examining the evidence, the editorial and the discussion review previous evidence of a significant association between HCV infection, insulin resistance, and diabetes.  The odds ratio for this association (HCV and diabetes) was estimated to be about 1.7.  The problems with this association were the following:

  • Much of the work was reported from tertiary care centers
  • Advanced liver disease (of any type) is a well-established risk factor for type 2 diabetes (T2DM)
  • Many studies may have included patients with nonalcoholic fatty liver disease which is another risk factor for diabetes
  • These studies did not control for ALT values

Bottomline (from editorial): This study “calls one to reconsider the dogma on the role of IR [insulin resistance] in the pathogenesis of HCV infection and its association with T2DM.” If there is an association, it is much smaller than previous estimates.

Related blog post: Treating HCV Helps Diabetics | gutsandgrowth

Social Media -Why It is Useful for Physicians

Just now, I participated in a 5K run to support The NASPGHAN Foundation.  My suggestion is to move this to a Saturday or Sunday next year to allow more support from the community at large.  That being said, I was pleased to be able to participate in this inaugural race.

Later today, I am giving a talk at our national pediatric gastroenterology meeting on social media.  On one of my first slides, I disclose that I have no financial conflicts and that I am not an expert on social media. The truth is that most teenagers are much more knowledgeable about social media than I am.  Perhaps the perspective that I lend to this area is that I have some experience on how social media can be helpful for physicians.

Here’s a link to my talk: StayingInformed WhyDoctorsNeedTwitter

If you have some suggestions, let me know soon.