
Alan Alda (aka Hawkeye Pierce) on Communicating Science

Link from Dr. Chris Simpson: http://t.co/f4etUVUiQr

Here’s an excerpt:

While Alda is best known for his role on  M.A.S.H  , the 78-year-old is also a science enthusiast who has spent more screentime hosting a PBS show called Scientific American Frontiers  than portraying Hawkeye Pierce. On that fateful day ten years ago, he was at a mountain observatory in Chile for Scientific American Frontiers, preparing to interview some astronomers, when he felt a sudden pain in his gut….

Alda recounted this [near-death] story…in Chicago, where hundreds of scientists from around the world crowded into a packed conference hall to hear him talk about science communication. Alda was one of       four plenary speakers     at the       2014 AAAS meeting     , the world’s largest annual general science conference.

His plenary speech was about communicating science, a subject Alda has become intensely passionate about over the years. He has described his stint at Scientific American Frontiers as “the best thing I ever did in front of a camera” — but it also showed him that many scientists have incredible stories but lack the tools to describe their work in a way that most people can understand.

This is a very real problem, one that journalists often struggle with when interviewing scientists. But for scientists, learning how to describe their work is not only a necessity, it is also a responsibility.

“Communication is essential to science,” Alda said. “It’s essential to the funding of science and even in the doing of it.”

So nowadays, Alda devotes himself to helping scientists discover their inner storytellers. He is a visiting professor at the Alan Alda Center for Communicating Science at Stony Brook University and has also created an improv class for scientists. A few years ago, he also started an annual competition challenging scientists to explain a scientific concept — for example, “what is a flame?” — in terms that would make sense to 11-year-olds, who actually judge the entries. This year’s challenge: “What is colour?”

(Last year’s winner, by the way, was a       PhD student from the University of Ottawa     who made this       video     to entertainingly answer the question “what is time?”).

On Saturday, Alda said he is often asked for tips on how to communicate science better. But there are no shortcuts, he said— becoming a storyteller is something that takes training, practice and commitment to improve.

But his speech left the audience with one general rule of thumb: storytelling is a powerful tool for helping people understand science.

“If you don’t begin with a story, or some kind of introduction to the hard words, we’re suffering from something awful that a couple of people have called the curse of knowledge,” Alda said. “It’s a curse when you know something in such depth, and with such a level of complexity, that you forget what it’s like not to know it at that depth. That’s a curse.”

Related blog post:
Why I have always liked Arthur Caplan… | gutsandgrowth

How often do you wipe down your stethoscope?

From NY Times, http://t.co/RoyhpjtPTQ; an except:

Doctors’ stethoscopes are contaminated with bacteria that can easily be transferred from one patient to another, a new study has found.

Researchers cultured bacteria from the fingertips, palms and stethoscopes of three doctors who had done standard physical examinations on 83 patients at a Swiss hospital. They tested for the presence of viable bacterial cells, looking specifically for the potentially deadly methicillin-resistant Staphylococcus aureus, or MRSA. The study appears in the March issue of the Mayo Clinic Proceedings.

Fingertips on the doctors’ dominant hands were the most contaminated, but the part of the stethoscope that touches the patients’ skin held more than twice as much bacteria as the physicians’ palms…

The authors acknowledge that the study was small and may not be applicable to other health care sites. Except for MRSA, they did not distinguish harmful from harmless bacteria.

That bacteria are found on stethoscopes is “not a surprise,” said the senior author, Dr. Didier Pittet, a professor of medicine at the University of Geneva Hospitals. He cleans his own stethoscope with alcohol swabs after each examination, but “most physicians do not.”


Facts, “Misfearing” and Women’s Health

A terrific short perspective article shows how “misfearing” affects health care (NEJM 2014; 370: 595-597).

The author quotes one of her patients who when asked what is the number-one killer of women, replies “I know the right answer is heart disease…but I’m still going to say ‘breast cancer.'”

Key points:

  • “Tornadoes. Terrorist attacks. Homicides.  The big, the dramatic, and the memorable occupy far more of our worry budget than the things that kill with far greater frequency.”
  • “Misfearing” is a term coined by Cass Sunstein “to describe the human tendency to fear instinctively rather than factually”  274. Cass R. Sunstein, “Misfearing: A Reply” – University of Chicago 
  • “When I read Angelina Jolie’s New York Times editorial…She’s beautiful and brave, I thought, and I want to be like her.  The cardiologist in me, however, said, ‘Oh no –will this make it even harder for us to help women believe they’re at risk for cardiovascular disease?'” My Medical Choice by Angelina Jolie – NYTimes.com

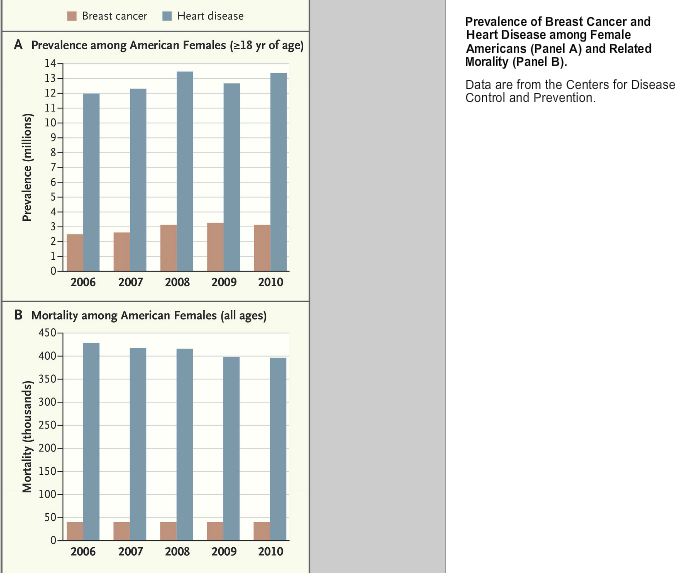
A graphic from this perspective article shows that mortality from cardiovascular disease is approximately ten times greater than mortality from breast cancer (if difficult to see, the graphic is available online http://www.nejm.org/doi/full/10.1056/NEJMp1314638?query=featured_home):

Cardiovascular vs. Breast Cancer Mortality in Women

Cardiovascular vs. Breast Cancer Mortality in Women

In pediatric GI, families are often more worried about the treatment than the disease (e.g.. inflammatory bowel disease), despite the fact that the disease is often far more dangerous.

Take home message: (quote from author) “If we want our facts to translate into better health, we may need to start talking more about our feelings.” This is true not just in cardiovascular disease, but in all aspects of medicine.

Related blog posts:

Crisis or Not -Tough to Change Bad Habits

For those of you with new resolutions, a sobering study from JAMA shows how difficult it is to change bad habits, even after a heart attack or a stroke.

From Sanjay Gupta’s twitter feed, link and excerpt: Video (1:48) http://ow.ly/sdS7R 

Even a brush with death is often not enough to get us to make better choices. Researchers studied more than 150,000 people from all around the world, rich and poor, urban and rural. Participants answered questions about exercise, diet, and smoking.

Because the group was so large, there were almost 8,000 participants who had survived either a heart attack or a stroke. The health habits of this group were startling. Only 39 percent reported improving their diet, and just 35 percent increased their physical activity. Of those who were smokers, only 52 percent quit. Just 4 percent of those 8,000 people improved their habits in all three areas: smoking, diet, and exercise.

Buyer Beware: Online Pharmacy Problems

“It always seems impossible until it’s done.”  –Nelson Mandela

From NY Times:

http://well.blogs.nytimes.com

Though technically illegal, millions of Americans buy prescription drugs from overseas pharmacies to save money.  But the practice can be a huge gamble.

The National Association of Boards of Pharmacy, a professional group, reviewed over 10,000 Internet drug outlets and found that many sold fake or unapproved drugs. Some that claimed to be Canadian pharmacies actually sold medicines from developing countries where regulations are weak and counterfeit drugs are common.

Roger Bate, a pharmaceutical expert at the American Enterprise Institute, estimates that 2 to 3 percent of online pharmacies are legitimate. When buying Canadian, he said, look for outlets certified by the Canadian International Pharmacy Association, a trade group of Canadian pharmacies, or those certified by PharmacyChecker.com, a free website that verifies that the foreign sites it approves protect consumer information and meet quality standards.

Last year, Mr. Bate and his colleagues published a study analyzing 372 orders of five popular prescription drugs – Lipitor, Celebrex, Viagra, Nexium and Zoloft – that they purchased from 79 domestic and foreign online drug outlets. Products bought from Canadian or other foreign sites certified by C.I.P.A. or PharmacyChecker.com were of high quality. So were products ordered from American sites verified by either the N.A.B.P. or LegitScript.com, a certification agency founded by a former White House aide on drug policy issues.

But that was not the case for sites that were not certified by any of these four groups. Many of the drugs they sold were fakes, including about a quarter of the Viagra samples, which largely appeared to have originated in China.

“You can’t be 100 percent certain with any sites, frankly,” Mr. Bate said. “But you are running a much lower risk if you buy from a credentialed site.”

Understanding PEWs & Online Reputation

Most pediatric gastroenterologists would think that the acronym PEWS referred to “Pediatric Early Warning Score” which is used to identify patient deterioration (Sensitivity of the Pediatric Early Warning Score to Identify Patient …).  This PEWS has been an important  achievement in patient safety contributing to lower mortality, reduced codes, and shortened intensive care unit stays (Simple Scoring System and Action Algorithm Identifies Children at …).

PEWs acronym also refers to “physician evaluation websites.”  These type of scores are growing in importance and may also reflect quality care.  As such, a recent article highlights this emerging phenomenon (Am J Gastroenterol 2013; 108: 1676-85 -thanks to Ben Gold for this reference).  While physicians are concerned about their reputations, these websites have not been widely embraced.  This article makes several points about why physicians may need to reconsider.

Key points:

  • 35 websites met criteria to be included in this study: 18 were dedicated physician evaluation websites, 5 were health information websites, and 12 were general information websites (eg. Angieslist.com, kudzu.com, yelp.com).
  • Frequent analysis/questions besides demographics/affiliations: punctuality, quality of staff (office/nursing), bedside manner, ability to make correct diagnosis, spent sufficient time, costs
  • Five sites allow physician feedback and chance to respond to dissatisfied patients: docspot.com, doctorscorecard.com, healthgrades.com, ratemds.com, and your city.md
  • Multiple charts indicate the huge traffic on these websites.  For dedicated PEWs, healthgrades.com has the highest volume at over 5 million unique visitors per month (2011-2012).
  • Most online evaluations are completed by females (with at least some college education) with a peak age between 45-65 years.  Some smaller PEWs attract a younger crowd (eg. Zocdoc.com -4th most visited dedicated PEW).
  • Most evaluations are positive.  “Site administrators…self-reported figures…ranged from 60-75% positive, 4-22% neutral, and 9-21% negative.”

Unique Aspects:

  • ucomparehealthcare.com (3rd most visited dedicated PEW) allows multiple physician profiles to be analyzed side-by-side.
  • docspot.com compiles existing reviews from over 15 other websites.
  • healthgrades.com (most visited dedicated PEW) allows users to rate physicians with a star scale but does not allow free response (avoids libelous comments).
  • vitals.com -2nd most visited dedicated PEW.
  • yourcity.md considered most “doctor friendly.” Prior to publicizing negative comments, this site allow doctors the option to respond publicly or privately; afterwards, the negative review can be revised.  In addition, per user agreement, a negative claim which cannot be substantiated could result in the anonymous reviewer’s name being revealed to the physician or be removed.

One of my mentors told me that the key to patient care was the the 3 A’s: availability, affability, and ability.  PEWs likely can help evaluate the first two A’s.  PEWs allow for constructive criticisms but need to evolve to include other measures of physician performance.  Ignoring PEWs would be a mistake for physicians –they are here to stay.

Related blog posts:

45,000 Unnecessary Deaths Per Year

According to a recent editorial (NEJM 2013; 369: 1180-81), 45,000 American adults die each year because they have no medical coverage (Am J Public Health 2009; 99: 2289-95).

The editorial which describes a late diagnosis of colon cancer in an adult who had been chronically uninsured despite working full-time makes a couple of key points:

  • Lack of insurance can be lethal
  • Underinsured also have higher mortality rates  One example: insurance status, not race, was associated with mortality after an acute cardiovascular event in Maryland (J Gen Intern Med 2012; 27: 1368)

While the rollout for the Affordable Care Act (ACA) has been bad, the underlying reason for it remains sound.  In addition, though the ACA expands coverage, I am skeptical that it will control problems with skyrocketing costs.  As such, many other difficult changes in medical care delivery will ultimately be needed.

Related blog post:

Life in the balance (book) | gutsandgrowth

Quality care = Work Satisfaction for Physicians

From Atul Gawande’s twitter feed:

RAND study:

“Factors Affecting Physician Professional Satisfaction and Their Implications for Patient Care, Health Systems, and Health Policy” Full article: http://bit.ly/19vVAnK 

1) Best predictor of MD work satisfaction: how we rate system’s care quality.  Physicians who felt that they were working in an environment with high quality care had higher work satisfaction.

2) Bad EHRs are killing us.  (Related blog entry: Aptly titled “The Cost of Technology” | gutsandgrowth)


Challenging assumptions

While this topic is not directly related to pediatrics or pediatric gastroenterology, I found a recent article regarding the treatment of back pain with steroids interesting.  This study challenges a treatment algorithm of using steroids to relieve inflammation triggering back pain.  The investigators showed that steroids per se are not more beneficial then saline in improving back pain.  Here is an excerpt from the NY Times, http://t.co/RF5O78odWe:

Questioning Steroid Shots for Back Pain

By NICHOLAS BAKALAR

Injecting steroids into the area around the spinal cord, known as an epidural, is the most commonly used treatment for back pain, but a new review of studies suggests that injecting any liquid, even plain saline solution, works just as well.

Researchers pooled the results of 43 studies involving more than 3,600 patients who got various kinds of injections for back pain. As they expected, they found some evidence that epidural steroid injections provided more relief than steroid injections into the muscles.

But the study, published online in Anesthesiology, also found that there was little difference between the amount of relief provided by steroidal and nonsteroidal epidural injections.

The researchers suggest that any liquid injected epidurally can help reduce inflammation, enhance blood flow to the nerves and clean out scar tissue.

Comment: There are inherently many limitations in pooling 43 studies and trying to reach a definitive conclusion.  Nevertheless, this study challenges some long-term treatment approaches.

Breakfast: a marker for heart-healthy habits

Summary of study (Circulation 2013; 128: 337-343) from Epocrates (emphasis in blue by blog):

Study Question:
Is eating breakfast or not associated with risk for coronary heart disease (CHD) among men residing in the United States?
Methods:
Data for this analysis were from the Health Professionals Follow-up Study, an ongoing prospective study of male health professionals. Approximately 97% of participants were of white European descent. Eating habits, including breakfast eating, were assessed in 1992 in 26,902 American men, ages 45-82 years, who were free of cardiovascular disease and cancer. Participants were followed through mailed biennial questionnaires that ascertained medical history, lifestyle, and health-related behaviors. Cox proportional hazards models were used to estimate relative risks and 95% confidence intervals for CHD, adjusted for demographic, diet, lifestyle, and other CHD risk factors.
Results:
Participants who did not report eating breakfast were younger than those who did, and were more likely to be smokers, to work full-time, to be unmarried, to be less physically active, and to drink more alcohol. Men who reported that they ate late at night were more likely to smoke, to sleep <7 hours a night, or to have baseline hypertension compared with men who did not eat late at night. The late-night eating abstainers were more likely to be married and to work full-time, and ate on average one time less per day than the late-night eaters. The mean diet quality of the participants was high among participants, regardless of their breakfast or late-night eating status. During 16 years of follow-up, 1,527 incident CHD cases were diagnosed. Men who skipped breakfast had a 27% higher risk of CHD compared with men who did not (relative risk, 1.27; 95% confidence interval, 1.06-1.53). Compared with men who did not eat late at night, those who ate late at night had a 55% higher CHD risk (relative risk, 1.55; 95% confidence interval, 1.05-2.29). These associations were mediated by body mass index, hypertension, hypercholesterolemia, and diabetes mellitus. No association was observed between eating frequency (times per day) and risk of CHD.
Conclusions:
The investigators concluded that eating breakfast was associated with significantly lower CHD risk in this cohort of male health professionals.
Perspective:
These data suggest that time of meals is associated with other lifestyle behaviors. Adjustment for body mass index, hypercholesterolemia, hypertension, and diabetes [resulted in the relationship between breakfast (and late-night meals) and CHD no longer being significant.] Physicians may use this information to assist in the identification of those who may be at risk and need to improve lifestyle habits. However, it is unlikely that eating breakfast by itself would confer significant protection against heart disease.

Full text available at http://circ.ahajournals.org/content/128/4/337

Related blog post:

Skipping breakfast –boomerang effect for obesity | gutsandgrowth