21 Year Data for Cancer Survivors

Most pediatric gastroenterologists see many children with pediatric cancers, so it is gratifying to see data showing improving long-term outcomes (GT Armstrong et al. NEJM 2016; 374: 833-42).  In addition, pediatric oncology serves as a model for improving therapy by enrolling virtually all of its patients in research protocols.

The authors evaluated late mortality among 34,033 patients in the Childhood Cancer Survivor Study.  All of these patients had survived at least 5 years after childhood cancer. During the study which had a median followup of 21 years, there were 3958 deaths and 1618 (41%) of these were attributable to health-related causes, including subsequent neoplasms (n=746), cardiac (n=241), and pulmonary (n=137).

The improvement in treatment regimens have included reductions in radiotherapy and anthracycline exposure.  The graph below shows survival rates 20 years after being cancer-free (15 years after being cancer-free for 5 years).

My take: This study confirms that these improved regimens have long-lasting effects on mortality.  Through cooperative research, we can do better in oncology and in all of pediatrics.

Incidence of death from any cause from patients treated between 1970-1999.

Incidence of death from any cause from patients treated between 1970-1999.

CDC Guideline for Prescribing Opioids for Chronic Pain

Full Text: CDC Guideline for Prescribing Opioids for Chronic Pain—United States, 2016

D Dowell et al. JAMA. Published online March 15, 2016. doi:10.1001/jama.2016.1464 .

Excerpts:

  • No evidence shows a long-term benefit of opioids in pain and function vs no opioids for chronic pain with outcomes examined at least 1 year later (with most placebo-controlled randomized clinical trials ≤6 weeks in duration).

  • Extensive evidence shows the possible harms of opioids (including opioid use disorder, overdose, and motor vehicle injury).

  • Extensive evidence suggests some benefits of nonpharmacologic and nonopioid pharmacologic therapy, with less harm.

CDC: “We know of no other medication routinely used for a nonfatal condition that kills patients so frequently,”

1st Six Recommendations (12 total)

1. Nonpharmacologic therapy and nonopioid pharmacologic therapy are preferred for chronic pain. Clinicians should consider opioid therapy only if expected benefits for both pain and function are anticipated to outweigh risks to the patient. If opioids are used, they should be combined with nonpharmacologic therapy and nonopioid pharmacologic therapy, as appropriate. (Recommendation category: A; evidence type: 3)

2. Before starting opioid therapy for chronic pain, clinicians should establish treatment goals with all patients, including realistic goals for pain and function, and consider how opioid therapy will be discontinued if benefits do not outweigh risks. Clinicians should continue opioid therapy only if there is clinically meaningful improvement in pain and function that outweighs risks to patient safety. (Recommendation category: A; evidence type: 4)

3. Before starting and periodically during opioid therapy, clinicians should discuss with patients known risks and realistic benefits of opioid therapy and patient and clinician responsibilities for managing therapy. (Recommendation category: A; evidence type: 3)

4. When starting opioid therapy for chronic pain, clinicians should prescribe immediate-release opioids instead of extended-release/long-acting (ER/LA) opioids. (Recommendation category: A; evidence type: 4)

5. When opioids are started, clinicians should prescribe the lowest effective dosage.  (Recommendation category: A; evidence type: 3)

6. Long-term opioid use often begins with treatment of acute pain. When opioids are used for acute pain, clinicians should prescribe the lowest effective dose of immediate-release opioids and should prescribe no greater quantity than needed for the expected duration of pain severe enough to require opioids. Three days or less will often be sufficient; more than 7 days will rarely be needed. (Recommendation category: A; evidence type: 4)

Other points:

  • Avoid concurrent benzodiazepines
  • Review state prescription drug monitoring program to look for dangerous combination therapies and prior opiod dosing
  • Consider risk mitigation strategies (eg. naloxone)
  • Suggests urine screening at start to screen for illicit substance abuse which increases risk

USAToday’s review of these guidelines: CDC issues new guideline on opiods

Bottomline: This report is very important for those who prescribe opiods for chronic pain.

Law Library, Univ of Michigan

Law Library, Univ of Michigan

Drug Waste Costing Billions. Who benefits? Pharmaceutical Companies

From NY Times: Waste in Cancer Drugs Costs $3 Billion a Year

Here’s an excerpt:

The federal Medicare program and private health insurers waste nearly $3 billion every year buying cancer medicines that are thrown out because many drug makers distribute the drugs only in vials that hold too much for most patients, a group of cancer researchers has found…

If drug makers distributed vials containing smaller quantities, nurses could pick the right volume for a patient and minimize waste…according to researchers at Memorial Sloan Kettering Cancer Center, whopublished a study on Tuesday in BMJ…

“Drug companies are quietly making billions forcing little old ladies to buy enough medicine to treat football players, and regulators have completely missed it,” said Dr. Peter B. Bach, director of the Center for Health Policy and Outcomes at Memorial Sloan Kettering and a co-author of the study…

Some non-cancer drugs also generate considerable waste, includingRemicade, an arthritis drug sold by Johnson & Johnson for which an estimated $500 million of the drug’s $4.3 billion in annual sales comes from quantities that are thrown away, researchers found.

My take: this is another indictment of our pharmaceutical companies willful neglect of medication costs or cynical manipulation of our healthcare system.

Related blog posts:

Why Georgia Cannot Provide More Healthcare

RE: Georgia Senate Resolution 756.

From Jay Bookman: Ga. can’t afford health care for its people, but tax cuts? Sure!..

Here is an excerpt:

Medicaid cannot be expanded in Georgia, extending much-needed health insurance to some 400,000 of our fellow citizens, because the state budget is under too much strain.

Sure, expanding Medicaid would save lives and improve the quality of life for many others, many of them lower-income working people whose jobs don’t include health coverage. Sure, it would bring billions of new federal dollars into the state and help rescue a health-care delivery system that is now collapsing in much of rural Georgia. Sure, it would create thousands of jobs, and sure, federal tax money would no longer be flowing out of Georgia to subsidize Medicaid coverage for people in other states…

Yet on Monday, a supermajority of the state Senate voted to slash the state income tax by an amount roughly equivalent to that needed to fund Medicaid expansion.

Related blog posts:

My day on the beach is about to get worse

My day on the beach is about to get worse. Flamenco beach.

NPR: Understanding “Sleep Munchies”

From NPR: Sleep Munchies: Why It’s Harder to Resist Snacks When We’re Tired

An excerpt:

There’s lots of evidence that getting too little sleep is associated with overeating and an increased body weight.

The question is, why? Part of the answer seems to be that skimping on sleep can disrupt our circadian rhythms. Lack of sleep can also alter hunger and satiety hormones.

Now, a new study finds evidence that sleep deprivation (getting less than five hours of sleep per night) produces higher peaks of a lipid in our bloodstream known as an endocannabinoid that may make eating more pleasurable.

So, what’s an endocannabinoid? If you look at the word closely, you may already have a clue. The prefix endo means inner, or within. And cannabinoid looks like … you got it: cannabis.

My take: Another good reason to avoid being on call -it could lead to sleep deprivation/weight gain.

Old San Juan

Old San Juan

Worried About the Zika Virus

While Zika virus infections may not be seen frequently by pediatric gastroenterologists, this infection will be a common concern for the families we treat and we may end up taking care of children with feeding problems/neurologic impairment due to congenital infection.

I attended a recent Georgia American Academy of Pediatrics board meeting.  One of the topics discussed was the Zika virus.  An update was given by Dr. Harry Keyserling, chair of the infectious disease committee (who has given permission for me to share some of his slides).  Some of the important points from his talk:

  • The Zika virus shares some similarities with the Dengue virus. The Zika virus is a single-stranded RNA flavivirus. Incubation period is 3 days to a few weeks.  It can be acquired from mosquito bites, spread sexually, transplacentally or intrapartum.  It may be transmissible via blood, organ donation or possibly breastmilk.


History of Zika Virus

History of Zika Virus

Most are asymptomatic. The clinical spectrum in those with symptoms are noted above.

Most are asymptomatic. The clinical spectrum in those with symptoms are noted above.

  • 80% of infected individuals are asymptomatic.
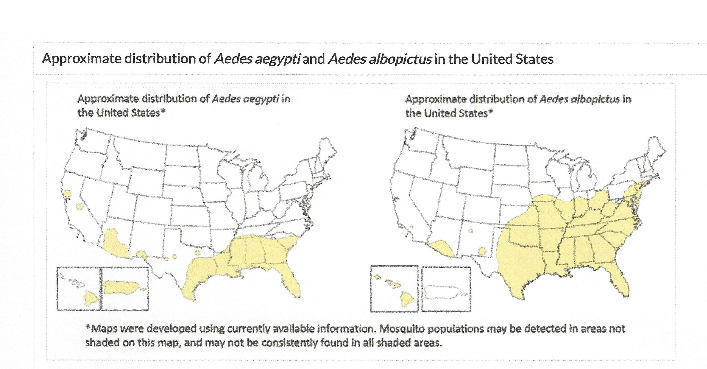
Approximate distribution of mosquito vector

Approximate distribution of mosquito vector

  • Due to the geographic distribution of the vector, it is likely that there will be many more cases in Georgia.

Screen Shot 2016-03-02 at 6.57.28 PM

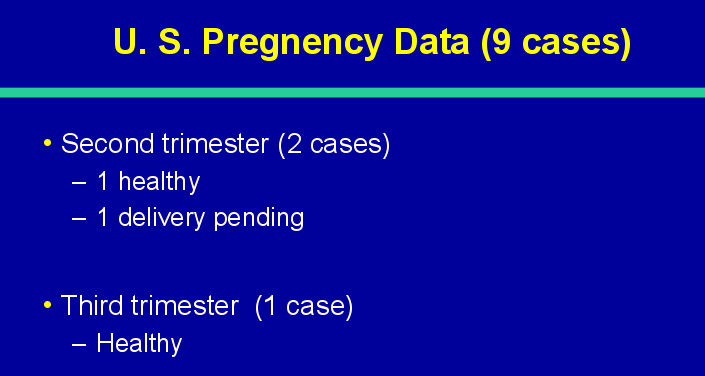
US DATA 1

US DATA 2

  • The most alarming association has been with microcephaly.  In some locations, there have been recommendations to avoid pregnancy until 2018.  After natural infection has spread, it is likely to lead to immunity and then should be safe to become pregnant.

Prevention

  • Zika can be acquired through sexual-transmission which indicates that pregnant women in endemic areas could need to avoid sex.

More resources:

My take: Because the Zika virus is going to continue to spread and the methods for prevention are not entirely effective, the next few years are going to present a lot of challenges.  This will continue until some population immunity develops (following infection or perhaps after development of an effective vaccine).

Surgery Resident Sleep & Flexibility in Training

A recent study (KY Bilimoria et al. NEJM 2016; DOI: 10.1056/NEJMoa1515724) indicates that some flexibility in training hours did not result in increased adverse outcomes and improved continuity of care. This study examined the care of nearly 140,000 patients.

For a 2 minute quick take -video available at this link along with full-text and abstract: National Cluster-Randomized Trial of Duty-Hour Flexibility in Surgical Training

Related blog posts:

Emergency Medical Information -Easy Access on Your iPhone

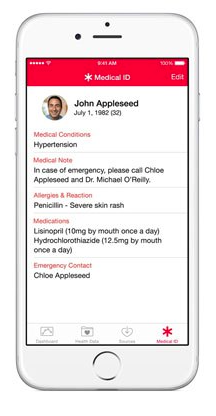
When I purchased a new iPhone, one of my sons was eager to show me all of the cool features.  If you do not have a teenager (i.e. house IT specialist) in the house, you may not have taken advantage of the health app built into the iPhone 6.  This can be very useful for you and your patients.

Screen Shot 2016-01-31 at 12.14.08 PM

One feature of the health app is that it allows you to store emergency contact information and health information that’s accessible from your device’s Lock screen. First responders or good Samaritans will be able to call the emergency contacts listed in Medical ID.  This health app also can function as an activity tracker.

Screen Shot 2016-01-31 at 12.12.38 PM

Here’s a link with additional information: How to set up your emergency medical ID

Piling on PPIs -Now Concerns about Dementia

A recent study (see abstract below -from Mike Hart) indicates the possibility that proton pump inhibitors (PPIs) could increase the risk of dementia to a small degree.  Despite the big numbers, this study cannot adequately control for numerous factors that could influence these results.  As is often said, association does not prove causation.  Nevertheless, this study is another reminder to use PPIs when indicated and to use them for the appropriate length of therapy.

Here’s NBC News Narrative: Popular Heartburn Drugs Linked to Dementia

ONLINE FIRST

Association of Proton Pump Inhibitors With Risk of Dementia: A Pharmacoepidemiological Claims Data Analysis

Willy Gomm, PhD1; Klaus von Holt, MD, PhD1; Friederike Thomé, MSc1; Karl Broich, MD2; Wolfgang Maier, MD1,3; Anne Fink, MSc1,4; Gabriele Doblhammer, PhD1,4,5,6; Britta Haenisch, PhD1

JAMA Neurol
. Published online February 15, 2016. doi:10.1001/jamaneurol.2015.4791
 
ABSTRACT

Importance  Medications that influence the risk of dementia in the elderly can be relevant for dementia prevention. Proton pump inhibitors (PPIs) are widely used for the treatment of gastrointestinal diseases but have also been shown to be potentially involved in cognitive decline.

Objective  To examine the association between the use of PPIs and the risk of incident dementia in the elderly.

Design, Setting, and Participants  We conducted a prospective cohort study using observational data from 2004 to 2011, derived from the largest German statutory health insurer, Allgemeine Ortskrankenkassen (AOK). Data on inpatient and outpatient diagnoses (coded by the German modification of the International Statistical Classification of Diseases and Related Health Problems, Tenth Revision) and drug prescriptions (categorized according to the Anatomical Therapeutic Chemical Classification System) were available on a quarterly basis. Data analysis was performed from August to November 2015.

Exposures  Prescription of omeprazole, pantoprazole, lansoprazole, esomeprazole, or rabeprazole.

Main Outcomes and Measures  The main outcome was a diagnosis of incident dementia coded by the German modification of the International Statistical Classification of Diseases and Related Health Problems, Tenth Revision. The association between PPI use and dementia was analyzed using time-dependent Cox regression. The model was adjusted for potential confounding factors, including age, sex, comorbidities, and polypharmacy.

Results  A total of 73 679 participants 75 years of age or older and free of dementia at baseline were analyzed. The patients receiving regular PPI medication (n = 2950; mean [SD] age, 83.8 [5.4] years; 77.9% female) had a significantly increased risk of incident dementia compared with the patients not receiving PPI medication (n = 70 729; mean [SD] age, 83.0 [5.6] years; 73.6% female) (hazard ratio, 1.44 [95% CI, 1.36-1.52]; P < .001).

Conclusions and Relevance  The avoidance of PPI medication may prevent the development of dementia. This finding is supported by recent pharmacoepidemiological analyses on primary data and is in line with mouse models in which the use of PPIs increased the levels of β-amyloid in the brains of mice. Randomized, prospective clinical trials are needed to examine this connection in more detail.

Related blog post: Proton Pump Inhibitors Webinar

Unrelated article (from Ben Gold): J Molina-Infante et al. Am J Gastroenterol 2015; 110: 1567-1575.  This study examined 75 patients (mean age 38 years) with proton-pump inhibitor responsive esophageal eosinophilia (PPI-REE).  55 (73%) had long-term sustained histologic remission with low-dose PPI therapy (20 mg once or twice daily). In addition, the article noted that 9 of 10 relapsers with distal eosinophilia were noted to have a CYP2C19 rapid metabolizer genotype and regained histologic remission with dose intensification.

Briefly noted: AI Sharara et al. Clin Gastroenterol Hepatol 2016; 14: 317-21.  Among 414 who met inclusion criteria (at least 6 months of PPI usage and at least 1 serum magnesium level), 57 (13.8%) had at least 1 low serum magnesium –44 of these patients had recognizable causes (eg. diuretics, chronic diarrhea).  Of the remainder who continued with PPI therapy, the level was normal at final measurement and only mildly low levels were noted previously.  Thus, in patients without other reasons for low magnesium, the authors found that use of a PPI does not appear to be associated with hypomagnesemia.


Trends in Non-medical Opiod Use and Heroin Addiction

Almost all physicians use opiods in their practice and need to keep up with the challenges of pain management and addiction.  An update on the problem of non-medical opiod use and heroin addiction from NEJM:

Full article link: Relationship between Nonmedical Prescription-Opiod Use and Heroin Use

An excerpt:

The transition from nonmedical use of prescription opioids to heroin use appears to be part of the progression of addiction in a subgroup of nonmedical users of prescription opioids, primarily among persons with frequent nonmedical use and those with prescription opioid abuse or dependence. Although some authors suggest that there is an association between policy-driven reductions in the availability of prescription opioids and increases in the rates of heroin use,16,18 the timing of these shifts, many of which began before policies were robustly implemented, makes a causal link unlikely…

In the majority of studies, the increase in the rates of heroin use preceded changes in prescription-opioid policies, and there is no consistent evidence of an association between the implementation of policies related to prescription opioids and increases in the rates of heroin use or deaths, although the data are relatively sparse. Alternatively, heroin market forces, including increased accessibility, reduced price, and high purity of heroin appear to be major drivers of the recent increases in rates of heroin use…

Fundamentally, prescription opioids and heroin are each elements of a larger epidemic of opioid-related disorders and death. Viewing them from a unified perspective is essential to improving public health. The perniciousness of this epidemic requires a multipronged interventional approach that engages all sectors of society.

Related blog posts:


Screen Shot 2016-01-14 at 8.01.08 PM