

Category Archives: General Health
Image Only -Mortality from Cancer and Heart Attacks
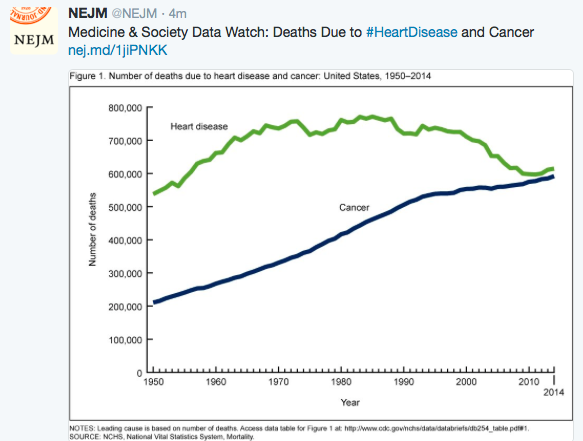
Image Only -Change in Teen Pregnancy Rates

Related blog post:
Is a Gluten-Free Diet a Healthy Diet for Those without Celiac Disease?
A helpful commentary (NR Reilly. J Pediatr 2016; 175: 206-10) on the gluten-free diet (GFD) tries to separate fact from fiction. A few key points:
- There are some health problems that can occur with a GFD, particularly when the diet is started without the support of an experienced dietician. GFD foods frequently contain a greater density of fat and sugar and can contribute to obesity and metabolic syndrome. A GFD may lead to nutrient deficiencies in B vitamins, folate, and iron. GFD without sufficient dietary diversity may contain increase in toxin exposures (eg. arsenic, and mercury).
- Gluten is not toxic. “There are no data to support the theory of an intrinsically toxic property of gluten for otherwise-healthy and asymptomatic adults and children, and certain studies have specifically demonstrated a lack of toxic effects.“
- Most individuals with NonCeliac Gluten Sensitivity (NCGS) do not have NCGS! First of all, many receive a GFD without proper testing to exclude celiac disease. Secondly, most will tolerate gluten reintroduction. In an Italian study, “only 6.6% of consecutive patients with presumed gluten sensitivity…actually had NCGS. 86% did not experience symptoms when gluten was reintroduced.”
- Timing of gluten introduction: “The most current understanding…in at-risk infants is that neither delaying gluten introduction from the recommended 6 months of age to 1 year, nor introducing at 4 months of age alters long-term CD risk estimates.”
My take: This is an excellent commentary. While many people (without celiac disease) perceive benefit from a GFD, only a minority are likely to derive better health or improved quality of life. Those who stick with a GFD should seek the help of a well-qualified dietician.
Related blog posts:
- An Unexpected Twist for “Gluten Sensitivity” | gutsandgrowth
- The Science Behind IBS Dietary Interventions | gutsandgrowth
- Gluten sensitivity without celiac disease | gutsandgrowth
- Food choices, FODMAPs, and gluten haters | gutsandgrowth

Glacier Nat’l Park
Medical Error -Overestimated as Cause of Death
A recent NY Times article provides some context to previous studies claiming that medical error could cause 100,000-250,000 deaths per year: Aaron Carroll Death by Medical Error
Here’s some excerpts:
When I started out as a doctor in 1999, the Institute of Medicine published a blockbuster report that declared that up to 98,000 people were dying in United States hospitals each year as a result of preventable medical errors. Just a few months ago, a study in the BMJ declared that number has now risen to more than 250,000, making preventable medical errors in hospitals the third-largest cause of death in the country in 2013…
There are about 2.5 million deaths each year in the United States, about 700,000 of which are hospitalized patients. This means that medical errors — in hospitals — would have to account for up to 10 percent of all deaths, or up to more than a third of hospitalized patients. That’s hard to fathom….
It’s somewhat sensationalistic to keep coming up with increasing numbers. I’m not sure it’s doing much good. After the publication of the initial report, defenders of the 98,000 number argued that even if the numbers were wrong, bringing attention to this problem would be good in itself.
Unfortunately, research doesn’t necessarily back that up. A 2010 study in The New England Journal of Medicine followed 10 North Carolina hospitals in the 10 years after the Institute of Medicine report. They found that the overall rate of harms, and the rate of preventable harms, did not significantly improve over that period.
My take: The article, in full, makes some compelling arguments that medical errors are overly-attributed as causes of death. At the same time, the article does not dismiss the importance of medical errors. Many of the harms from medical errors do not result in death.

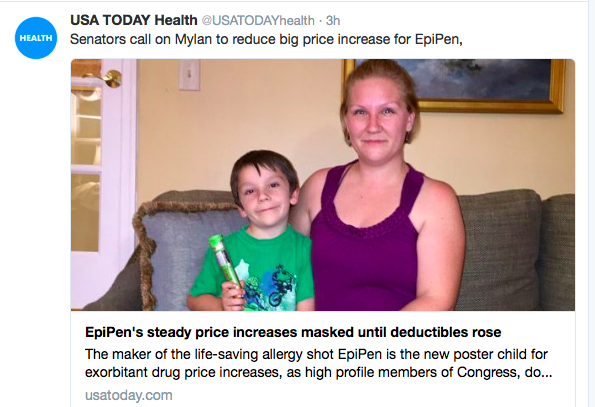
Another Day, Another Exorbitant Drug Increase for a Vital Drug: Epipen
From NBC News: EpiPen Prices Rocket Along With Drugmaker Executive’s Pay




Also, this story has been discussed in NY Times (Epipen & Health Care System Dysfucntion) and USA Today (see below)
Also, from KT Park’s twitter feed:

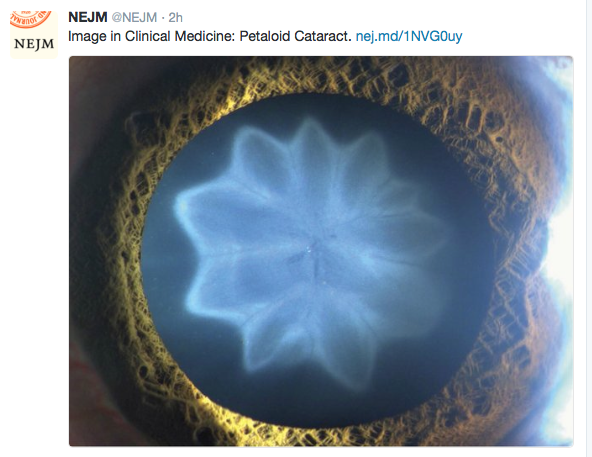
Petaloid Cataract
“The petaloid cataract is classically seen in patients who have had blunt trauma to the eye.” NEJM: Petaloid Cataract
Raynaud’s Phenomenon
IN 1862, Maurice Raynaud described a 26-year-old female patient: “Under the influence of a very moderate cold…she sees her fingers become ex-sanguine, completely insensible, and of a whitish-yellow color. This phenomenon …lasts a variable time, and terminates by a period of very painful reaction, during which the circulation is re-established…and recurs to the normal state.”
An updated review on Raynaud’s: FM Wigley, NA Flavahan. NEJM 2016; 375: 556-65.
This review highlights treatments and the differential diagnosis of primary Raynaud’s phenomenon form secondary causes (eg scleroderma, SLE, dermatomyositis, Sjogren’s and others).

A) Pallor phase B) Cyanotic phase C) Normal nailfold capillaries (primary phenomenon) D) Abnormal nailfold capillaries typical of microvascular disease
Addressing Medical Issues Before International Travel
Briefly noted: An highly detailed but concise review of “Medical Considerations before International Travel” DO Freedman et al. NEJM 2016; 375: 247-60.
Figure 1:
- Risk assessment: medical history, prior travel experience, specific itinerary (region, season), type of accommodations, risk tolerance, financial challenges
- Standard Interventions: Immunizations, Malaria prophylaxis (if risk), Traveler’s diarrhea strategy
- Focused education: vectorborne diseases, altitude illness, thrombosis risk, STDs/bloodborne infections, transportation risks (eg no car seats), respiratory infections, medical kit, medical insurance
Tables:
- Table 1: Practices for reducing disease risk (too many to summarize)
- Table 2: Vaccine Recommendations
- Table 3: Malaria Prophylaxis
- Table 4: Recommendations based on location
Short Take Video Link (2 min): Travel Health and Safety
CDC: Traveler’s Health Website
Travel Resource: GeoSentinel Website
My take: This is a handy updated reference for international medical travel
Related blog posts:
- Guidelines for Traveler’s Diarrhea in Adults | gutsandgrowth
- Apple Juice for Gastroenteritis | gutsandgrowth


What a Natural Death Now Looks Like
N Gray. Ann Intern Med. 2016;165(3):W5. doi:10.7326/G16-0002
From Annals of Intern Med Twitter Feed:

My take: Heroic (and often futile) medical therapy is NOT limited to the elderly. Physicians are much more likely to choose a no code status if faced with a terminal illness. See related post:

