Eric Topol to Stephen Hahn/FDA: “Tell the Truth or Resign”

An open letter from Eric Topol to Dr.Stephen Hahn details a number of glaring mistakes at the FDA which threaten its credibility and its mission.

Here’s the link: Dear Commissioner Hahn: Tell the Truth or Resign

The letter points to three high profile, politically-fraught decisions at the FDA:

  1. Authorization of hydroxychloroquine
    • “Immediately after President Trump widely and aggressively promoted hydroxychloroquine as a “miracle drug,” on March 30, 2020, you granted an Emergency Use Authorization (EUA) for this drug without any sufficient or meaningful supportive evidence”
  2. Authorization of convalescent plasma
    • “This is a major advance…[A]nd a 35% improvement in survival is a pretty substantial clinical benefit. What that means is — and if the data continue to pan out — [of] 100 people who are sick with COVID-19, 35 would have been saved because of the admission of plasma.” Every part of that statement is incorrect and a blatant misrepresentation of the data. “
  3. Authorizaton of remdesevir
    • The third breach of evidence-based data was your EUA issued August 28, 2020 broadening the remdesivir approval to include any patient hospitalized with moderate COVID-19. There are insufficient data to support this approval, as it is based on small, open-label studies with subjective endpoints.

Dr. Topol worries that Dr. Hahn will further erode confidence in the FDA by approval of a SARS-CoV-2 vaccine prematurely.  “Any shortcuts will not only jeopardize the vaccine programs but betray the public trust, which is already fragile about vaccines, and has been made more so by your lack of autonomy from the Trump administration and its overt politicization of the FDA.”

For SARS-CoV-2–Is 2 Meters Enough?

NR Jones et al. BMJ 2020;370:m3223. Full Text: Two metres or one: what is the evidence for physical distancing in covid-19?

Key messages from article:

  • Current rules on safe physical distancing are based on outdated science
  • Distribution of viral particles is affected by numerous factors, including air flow
  • Evidence suggests SARS-CoV-2 may travel more than 2 m through activities such as coughing and shouting
  • Rules on distancing should reflect the multiple factors that affect risk, including ventilation, occupancy, and exposure time

Highlighted article from Eric Topol’s Twitter Feed

A more nuanced approach is recommended by authors -color-coded Figure 3 above –caption: “Risk of SARS-CoV-2 transmission from asymptomatic people in different settings and for different occupation times, venting, and crowding levels (ignoring variation in susceptibility and viral shedding rates). Face covering refers to those for the general population and not high grade respirators. The grades are indicative of qualitative relative risk and do not represent a quantitative measure. Other factors not presented in these tables may also need to be taken into account when considering transmission risk, including viral load of an infected person and people’s susceptibility to infection. Coughing or sneezing, even if these are due to irritation or allergies while asymptomatic, would exacerbate risk of exposure across an indoor space, regardless of ventilation.”

MIT Technology Review: How to Talk to Conspiracy Theorists

From Bryan Vartabedian’s 33email –this link: MIT Technology Review: How to Talk to Conspiracy Theorists

An excerpt:

  • Always, always speak respectfully. Every single person I spoke to said that without respect, compassion, and empathy, no one will open their mind or heart to you. No one will listen.
  • Go private…
  • Test the waters first. That way you save yourself time and energy. “You can ask what it would take to change their mind, and if they say they will never change their mind, then you should take them at their word and not bother engaging,”
  • Agree…[with some parts] Conspiracy theories often feature elements that everyone can agree on
  • Try the “truth sandwich. Use the fact-fallacy-fact approach…
  • Or use the Socratic method. In other words, use questions to help others probe their own argument and see if it stands up. ..The best way to change someone’s view is to make them feel like they’ve uncovered it themselves,” he says. That means engaging in back-and-forth questions and answers until you hit a dead end, gently pointing out inconsistencies.
  • Be very careful with loved ones.
  • Realize that some people don’t want to change, no matter the facts.
  • If it gets bad, stop. … “If I am not enjoying the discussion and getting angry, then I simply stop.”
  • Every little bit helps. One conversation will probably not change a person’s mind, and that’s okay

Related blog posts:

COVID-19: At-Risk Populations, Moral Distress, and Related News

Before today’s post –more on voting this year:

Democracy Docket Four Ways to Safely Cast Your Ballot without USPS

  • This article also has very helpful links to all of the states’ resources, regulations, and contacts

Several recent commentaries have shown scenarios impacted by this pandemic.  Thanks to Ben Gold for sharing these references.

CA Wong et al. Pediatrics, : Mitigating the Impacts of the COVID-19 Pandemic Response on At-Risk Children

Here, we (1) highlight the health risks of the pandemic response measures to vulnerable pediatric subpopulations and (2) propose risk mitigation strategies that can be enacted by policy makers, health care providers and systems, and communities.

  • Children With Behavioral Health Needs
  • Children in Foster Care or at Risk for Maltreatment
  • Children With Medical Complexity

R Cholera et al. Pediatrics. Full link: Sheltering in Place in a Xenophobic Climate: COVID-19 and Children in Immigrant Families

One in 4 children (>18 million) in the United States lives in an immigrant family, in which the child or ≥1 parent was born outside the United States.1 Among children in immigrant families (CIF), >7 million live in “mixed-status” families, meaning ≥1 parent is not a US citizen.2… The COVID-19 pandemic amplifies existing inequities and introduces new ones as immigrant families navigate school closures, lack of health insurance and paid leave, and decisions to seek medical care or public services amid ongoing immigration enforcement. Additionally, immigrant families are more likely to live in multigenerational households,4 heightening the risk of COVID-19 for multiple family members…For CIF in US communities coping with persistent fears of immigration enforcement and family separation, economic devastation during a pandemic may threaten the stability of place. In this article, we apply a health equity framework5 to evaluate the impact of COVID-19 on CIF and highlight opportunities for advocacy and action for pediatricians, hospitals and health care systems, and policymakers to mitigate the unique risks faced by CIF

AM Evans et al. Pediatrics:  Pediatric Palliative Care in a Pandemic: Role Obligations, Moral Distress, and the Care You Can Give

Moral distress refers to the experience of being unable to take the action that one believes to be morally right or required.1… the inability to provide care because of resource constraints, involvement in care that one deems to be against a patient’s interests, and disputes about care planning with families and within teams…

We cannot have an obligation to save a life that cannot be saved: we can only be obliged to do what we can… It is only your role to act well within your scope of responsibility and to be the best clinician that you can be under the circumstances. Recognizing the limits of one’s powers can relieve a burden of guilt that is unconnected with one’s own choices and actions.


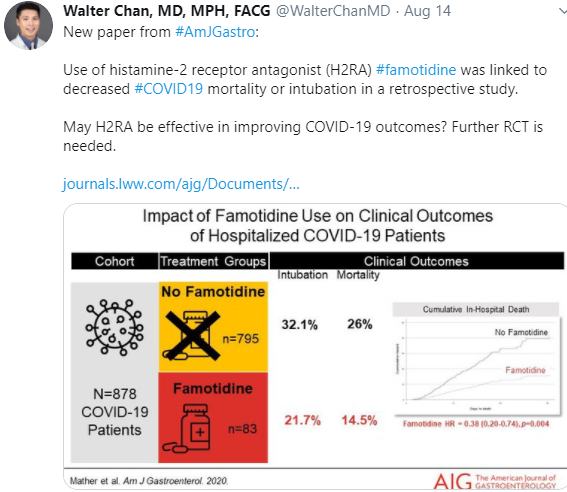
Famotidine may be helpful based on a retrospective study:


This long piece from Slate details the myriad public health mistakes in the U.S. approach to COVID-19: The Trump Pandemic

Screenshots and Tweets; MCAT Exposures, Uninsured in Texas, Health Inequalities, a Joke, Other News

Good Reads:

  1. Wired: Bill Gates on Covid: Most US Tests Are ‘Completely Garbage’
  2. MMWR: Hospitalization Rates and Characteristics of Children Aged <18 Years Hospitalized with Laboratory-Confirmed COVID-19 — COVID-NET, 14 States, March 1–July 25, 2020 “Analysis of pediatric COVID-19 hospitalization data from 14 states found that although the cumulative rate of COVID-19–associated hospitalization among children (8.0 per 100,000 population) is low compared with that in adults (164.5), one in three hospitalized children was admitted to an intensive care unit…Among 222 (38.5%) of 576 children with information on underlying medical conditions, 94 (42.3%) had one or more underlying conditions . The most prevalent conditions included obesity (37.8%), chronic lung disease (18.0%), and prematurity (gestational age <37 weeks at birth, collected only for children aged <2 years) (15.4%)end highlight.”  Key finding: Using a multisite, geographically diverse network, this report found that children with SARS-CoV-2 infection can have severe illness requiring hospitalization and intensive care.

COVID-19 Physician’s Personal Experience

Link: MY COVID-19 Excerpts:


Reopening Primary Schools -What’s At Stake

R Levinson et al. NEJM 2020; DOI: 10.1056/NEJMms2024920. Full Link: Reopening Primary Schools during the Pandemic

An excerpt:

Children miss out on essential academic and social–emotional learning, formative relationships with peers and adults, opportunities for play, and other developmental necessities when they are kept at home. Children living in poverty, children of color, English language learners, children with diagnosed disabilities, and young children face especially severe losses.

School-provided social welfare services support the health of U.S. communities made  vulnerable by systemic racism, inadequate insurance, family instability, environmental toxicity, and poorly paid jobs.1 More than 50% of all U.S. school-age children rely on their schools for free or reduced-price daily meals. Despite efforts by school districts to maintain these services even when school was conducted remotely, a majority of children have been unable to access the full nutritional benefits to which they’re entitled.5 Schools also provide physical, mental health, and therapeutic services to millions of students per year. Many of these services have proved inaccessible to children — particularly low-income children of color and children with noncitizen family members — when schools are physically closed.1 Finally, safe and consistently open schools are essential for many parents and guardians (particularly women) to be able to reenter the workforce — including the health care sector…

Most locations (except Israel) whose schools are open had already achieved low community transmission rates (<1 new case per day per 100,000 people) and have remained focused on maintaining population-level infection control…

The safest way to open schools fully is to reduce or eliminate community transmission while ramping up testing and surveillance…These precautions are especially important insofar as 17.5% of teachers are 55 or older…

The fundamental argument that children, families, educators, and society deserve to have safe and reliable primary schools should not be controversial. If we all agree on that principle, then it is inexcusable to open nonessential services for adults this summer if it forces students to remain at home even part-time this fall.

My take: This commentary makes strong arguments for reopening schools; however, in countries where this is succeeding, community transmission of SARS-CoV-2 is low and we are nowhere close to low.

Related blog posts:

NY Times: Opening Schools Safely

NY Times: Opening Schools Won’t Be Easy, but Here’s How to Do It Safely

An excerpt:

  • First, schools cannot reopen safely when community transmission is high and climbing. In our view, schools should open only in places that have fewer than 75 confirmed cases per 100,000 people cumulatively over the previous seven days, and that have a test positivity rate below 5 percent…
  • Second, schools should avoid high-risk activities. ..
  • Third, focus on the basics where risks are tolerable — that is at the medium level or lower on our chart. ..
  • [Fourth] Schools must adhere to public health measures and reduce density in classrooms and elsewhere on campus.

Related blog posts: