Increasing Rates of Professional Burnout

A recent study (T Shanafelt et al. Mayo Clin Proc. 2015;90(12):1600-1613) indicates that there may be increasing rates of physicians with “Professional Burnout.”  The study is limited by suboptimal response rates but provides some useful information on this topic.

Full text article: Changes in Burnout and Satisfaction With Work-Life Balance in Physicians and the General US Working Population Between 2011 and 2014

Results: Of the 35,922 physicians who received an invitation to participate, 6880 (19.2%) completed surveys. When assessed using the Maslach Burnout Inventory, 54.4% (n=3680) of the physicians reported at least 1 symptom of burnout in 2014 compared with 45.5% (n=3310) in 2011 (P<.001). Satisfaction with work-life balance also declined in physicians between 2011 and 2014 (48.5% vs 40.9%; P<.001). Substantial differences in rates of burnout and satisfaction with work-life balance were observed by specialty.  In contrast to the trends in physicians, minimal changes in burnout or satisfaction with work-life balance were observed between 2011 and 2014 in probability-based samples of working US adults, resulting in an increasing disparity in burnout and satisfaction with work-life balance in physicians relative to the general US working population.  After pooled multivariate analysis adjusting for age, sex, relationship status, and hours worked per week, physicians remained at an increased risk of burnout (odds ratio, 1.97; 95% CI, 1.80-2.16; P<.001) and were less likely to be satisfied with work-life balance (odds ratio, 0.68; 95% CI, 0.62-0.75; P<.001).

The indices that the authors studied included measures of the following (Table 2):

  • Emotional exhaustion
  • Depersonalization
  • Personal Accomplishment
  • Depression: 38% (2011) –>39% (2014)
  • Suicidal ideation: 6.4% (2011) and 6.4% (2014)
  • Burned out rate: 45.5% (2011) –>54.4% (2014)
  • Career satisfaction (would become a doctor again): 70% (2011) –>67% (2014)

Satisfaction with work life balance (Figure 1):

  • Pediatrics generally better than other fields, but close to 50% in 2014 were not satisfied compared with about 40% in 2011 (P <.05).

Take-home message from authors:

Burnout and satisfaction with WLB among US physicians are getting worse. American medicine appears to be at a tipping point with more than half of US physicians experiencing professional burnout. Given the extensive evidence that burnout among physicians has effects on quality of care, patient satisfaction, turnover, and patient safety, these findings have important implications for society at large. 11-20.  There is an urgent need for systematic application of evidence-based interventions addressing the drivers of burnout among physicians. These interventions must address contributing factors in the practice environment rather than focusing exclusively on helping physicians care for themselves and training them to be more resilient.

Related blog posts:

Zion National Park

Zion National Park


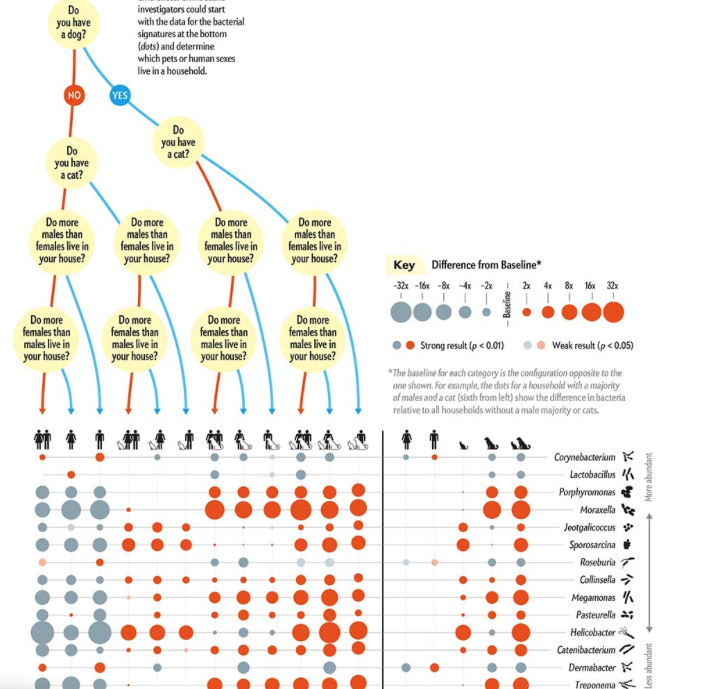
The Ecology of Microscopic Life in Household Dust

An interesting article about the fungi and bacterial in our households –has implications for our microbiome and for our predilection for allergies: full text: The Ecology of Microscopic Life in Household Dust

Barbera ́n A et al. The ecology of microscopic life in household dust. Proc. R. Soc. B 282: 20151139. http://dx.doi.org/10.1098/rspb.2015.1139 (reference from KT Park’s twitter feed)

Screen Shot 2015-11-22 at 9.07.00 AM

This article was summarized in by Mark Fischetti in Scientific American: full text: Men and Women Alter a Home’s Bacteria Differently

Screen Shot 2015-11-22 at 9.15.14 AM

NY Times: End the Gun Epidemic in America

Full link: End the Gun Epidemic in America.  This editorial published on A1 in the Dec. 5 edition of The New York Times. It is the first time an editorial has appeared on the front page since 1920.

An excerpt:

It is a moral outrage and a national disgrace that civilians can legally purchase weapons designed specifically to kill people with brutal speed and efficiency. These are weapons of war, barely modified and deliberately marketed as tools of macho vigilantism and even insurrection. America’s elected leaders offer prayers for gun victims and then, callously and without fear of consequence, reject the most basic restrictions on weapons of mass killing, as they did on Thursday. They distract us with arguments about the word terrorism. Let’s be clear: These spree killings are all, in their own ways, acts of terrorism.

Related blog posts:

“New Math on Drug Cost-Effectiveness”

Competing commentaries on rising drug prices:

  • Bach PB. “New Math on Drug Cost-Effectiveness” NEJM 2015; 373: 1797-99
  • Chin WW. “A Delicate Balance –Pharmaceutical Innovation and Access” NEJM 2015; 373: 199-1801)

Dr. Bach’s commentary focuses on the exorbitant costs of many medications.  His key points:

  • “The rate of introduction of new and expensive drugs has accelerated; the pace of conversion to generics is slowing; the prices of many generics are rising; and expensive drugs are now being introduced for conditions that affect millions of people rather than thousands.”
  • “Drug prices are increasing more rapidly than their benefits.”

Dr. Chin counters that there have been more than 500 new medications that have been approved in the United States since 2000.

  • “The United States relies on competitive markets to set prices and encourage innovation —a system that, as I see it, is working well.”
  • “The…hepatitis C medications, with cure rates above 90% are a good case study: within a year, competing medications entered the market, driving down prices by about half.”
  • “Any centralized government-purchasing model would probably result in drastically limited choices for physicians and patients.”

Another “must-read” on this topic comes from Ezekiel Emmanuel & the NY Times: I Am Paying for Your Expensive Medicine  Here’s an excerpt:

In July, the Food and Drug Administration approved the first of two new PCSK9 inhibitors that lower the bad type of cholesterol, LDL. Studiessuggest that they can reduce it by up to 60 percent, … and reduce it up to 36 percent more than statins… However, there are no definitive data on how much these drugs actually reduce heart attacks, strokes and deaths from heart disease…the retail price for a prescription would be more than $14,000 per patient per year. The price is particularly steep given that these drugs may need to be taken for the rest of the patients’ lives. How much patients pay directly would depend on their insurance plan….even if the price came down to about $11,000 per patient per year, and only 1.1 million of the roughly 23 million middle-age Americans with high cholesterol actually took these drugs, the bill would be so high that for a typical insurance plan, “annual insurance premiums would increase by $124 for every person” in the insurance plan…

As the PCSK9 story is making clear, the drug cost debate is now beginning to focus on two questions that are currently unresolved: First, how do we determine value so the perspectives of all Americans are considered? Second, how do we implement and enforce that determination of value?…

Many people hope that the drug industry will self-regulate, using value-based pricing of its new drugs. But if past experience is any indication of future behavior, self-regulation may be a pipe dream. 

My take: I don’t agree with Dr. Chin that our system has the right balance at this time, though he is right that too much interference could slow innovation.  In my view, recent high-profile excesses by pharmaceutical companies have strengthened the argument for more government intervention.

Morning in Sandy Springs

Morning in Sandy Springs


“I’ve Got the Best Doctor”

In numerous conversations, I have had heard from friends and family that “I’ve Got the Best Doctor.”  For everyone who thinks that, here’s a good read by Ezekiel Emanuel in NY Times:

“Are Good Doctors Bad for Your Health?”

Here’s an excerpt:

One of the more surprising — and genuinely scary — research papers published recently appeared in JAMA Internal Medicine. It examined 10 years of data involving tens of thousands of hospital admissions. It found that patients with acute, life-threatening cardiac conditions didbetter when the senior cardiologists were out of town. And this was at the best hospitals in the United States, our academic teaching hospitals. As the article concludes, high-risk patients with heart failure and cardiac arrest, hospitalized in teaching hospitals, had lower 30-day mortality when cardiologists were away from the hospital attending national cardiology meetings. And the differences were not trivial — mortality decreased by about a third for some patients when those top doctors were away…

One possible explanation is that while senior cardiologists are great researchers, the junior physicians — recently out of training — may actually be more adept clinically. Another potential explanation suggested by the data is that senior cardiologists try more interventions…

One thing patients can do is ask four simple questions when doctors are proposing an intervention, whether an X-ray, genetic test or surgery. First, what difference will it make? Will the test results change our approach to treatment? Second, how much improvement in terms of prolongation of life, reduction in risk of a heart attack or other problem is the treatment actually going to make? Third, how likely and severe are the side effects? And fourth, is the hospital a teaching hospital?

My take: Perhaps some of the differences in outcome are related to severity of illness that more experienced physicians may manage.  Nevertheless, it is clear that the reputation of the physician does not correlate well with clinical outcomes.

Related blog posts:


Clearing Out My Desk

These articles have been sitting on my desk or my email and worth a quick mention:

“Proton Pump Inhibitors Alter Specific Taxa in the Human Gastrointestinal Microbiome: A Crossover Trial” DE Freedberg et al. Gastroenterol 2015; 149: 883-85. In this study of 12 healthy volunteers over 12 weeks, the study’s major finding (according to associated commentary) “is the absence of any significant changes in microbial diversity with proton pump inhibitors.” However, there was “an increase in bacterial taxa associated with C difficile infection.”

“Quality of Life and Its Determinants in a Multicenter Cohort of Children with Alagille Syndrome” BM Kamath et al. J Pediatr 2015; 167: 390-6.  Quality of life is impaired in Alagille compared to healthy children and children with alpha-one antitrypsin; it is associated with growth failure which may be modifiable.

“Baseline Ultrasound and Clinical Correlates in Children with Cystic Fibrosis” DH Leung et al. J Pediatr 2015; 167: 862-68.  In this prospective study of children (n=719) from age 3-12 years, unsuspected cirrhosis was seen in 3.3% of patients and a heterogeneous liver echotexture was identified in 8.9%.

Case report of phlegmonous gastritis associated with ulcerative colitis (with good pictures): J Cordova, R Gokhale, B Kirschner. Gastroenterol 2015; 149: 867-69.

“High Prevalence of Idiopathic Bile Acid Diarrhea Among Patients with Diarrhea-Predominant Irritable Bowel Syndrome Based on Rome III Criteria” I Aziz et al. Clin Gastroenterol Hepatol 2015; 13: 1650-55.

“Emergence of plasmid-mediated colistin resistance mechanism MCR-1 in animals and human beings in China: a microbiological and molecular biological study” The Lancet. DOI: http://dx.doi.org/10.1016/S1473-3099(15)00424-7 (Reference from Sana Syed)

Gratitude and Eye Sight

For this day, I wanted to share a NY Times Story by Nicholas Kristof (In 5 Minutes, He Lets the Blind See) which highlights the successes of Dr. Sanduk Ruit (a Nepali ophthalmologist) along with Dr. Geoffrey Tabin (from University of Utah).  They can restore eyesight for $25!

An excerpt:

Some 39 million people worldwide are blind — about half because of cataracts — and another 246 million have impaired vision, according to the World Health Organization…He has restored eyesight to more than 100,000 people, perhaps more than any doctor in history, and still his patients come…

At first, skeptics denounced or mocked his innovations. But then the American Journal of Ophthalmology published a study of a randomized trial finding that Dr. Ruit’s technique had exactly the same outcome (98 percent success at a six-month follow-up) as the Western machines. One difference was that Dr. Ruit’s method was much faster and cheaper.

Related story on CNBC from 2013: Curing the blind

Bottomline: If you want to help save someone’s eyesight for $25: http://www.cureblindness.org/get-involved/support (Himalayan Cataract Project).

Sandy Springs

Sandy Springs

The Problem with Black Box Warnings

A short article (T Elraiyah, et al. Ann Intern Med. Published online 29 September 2015 doi:10.7326/M15-1097) explains the problem with current black box warnings and what can be done to improve them. “A black box warning (BBW) is the highest level of warning issued by the U.S. Food and Drug Administration (FDA)…These warnings are required when there is reasonable evidence of association between the drug and a significant safety concern.” Key points:

  • BBWs “have been the subject of controversy, due in part to their opaque connection to the underlying body of evidence.”
  • The authors reviewed 70 BBWs from the top 200 drugs.  “We found only 19 (27%) provided an estimate of the likelihood of harm, and only 8 (11%) reported a CI for that estimate.”
  • “Fewer than half (43%) presented the source of evidence. None described the quality (certainty of the evidence).”
  • “None provided guidance on how to communicate or act on the evidence.”

The authors state that “BBWs infrequently contain 3 elements required for evidence-based practice (estimate of effect, source and trustworthiness of evidence, and guidance on implementation).” There are some medicines that already have a well-presented BBW, including Advair-diskus.

My take: Black box warnings can generate a lot of anxiety and may adversely affect the calculation of benefit versus harm.  Improving them could be helpful for patients and doctors alike.

Related blog posts:

Atlanta Botanical Gardens

Atlanta Botanical Gardens


Understanding Your Food and Biotechnology (Part 3)

This is the last of my blog posts on the topic of biotechnology and foods from Ronald Kleinman’s lecture: Biotechnology, Nutrition, and Agriculture: A Perspective and Implications for Child Health. The posts over the past 4 days describe in detail why the hysteria over genetically modified foods/genetically modified organisms (GMOs) is detrimental.  Unfortunately, the lack of understanding has led to widespread adoption of “GMO-free” labeling by food manufacturers which perpetuates the misplaced idea that these foods may not be safe.  The slides and lecture will be available at the Nutrition4Kids website.

Screen Shot 2015-11-11 at 5.47.17 PM


This mother’s blog: “I don’t feed them organic food and I’m not a bad Mom.” It is a sad commentary that someone needs to write this.

Screen Shot 2015-11-11 at 5.46.45 PM

Humans, unlike plants, do not have the enzyme that Roundup (glyposate) targets –so it is safe. By targeting this enzyme, genetic engineering can allow the crop to be herbicide resistant, making it fairly easy to kill off weeds without hurting crop.  With biotechnology, we can kill weeds without killing plants. Thus, no till farming is needed. Current herbicides are much safer than prior agents.  Roundup (glyphosate) is water-soluble; it is not stored in fat. There is a 30 yr hx/o safe use.  There is no data indicating cancer risk in humans or fertility risk.

Screen Shot 2015-11-11 at 5.48.35 PM

Screen Shot 2015-11-11 at 5.48.03 PM

In the past, testing breastmilk for roundup used a flawed methodology. F/u study by McGuire M (sponsored by US govt) showed no Roundup (glyphosate) in breastmilk.

Drought-resistant crops are becoming increasingly important. Meeting global food production will require more ‘crop per drop’ due to increasing population and less lands available for farming. Not just 3rd World –look at California. There are low crop yields in areas without biotech (Subsaharan Africa) and higher mortality.

Key points:

  1. Genetically Modified Foods/Genetically modified organisms (GMO). These foods are safer and better than foods that are not genetically modified.
  2. Roundup is not dangerous for humans.
  3. Attacks on GMOs are part of a larger “War on Science.” As with vaccinations, there is a great deal of misleading and exaggerated information.
  4. Biotechnology can help solve food crisis, improve the lives of small farmers, and reduce malnutrition.  Genetically modified food reduces the needs for chemicals and can improve health.

Understanding Your Food and Biotechnology (Part 2)

This blog continues on the issue of genetic engineering and how it affects your food.  The information was presented in a lecture by Ronald Kleinman (see the posts from the last two days):  Biotechnology, Nutrition, and Agriculture: A Perspective and Implications for Child Health.  The slides and lecture will be posted on Nutrition4Kids website.

Biotechnology/genetic engineering is more precise in selecting desirable crop traits

Biotechnology/genetic engineering is more precise in selecting desirable crop traits

Why Newer Techniques (Genetic Engineering) Are Safer

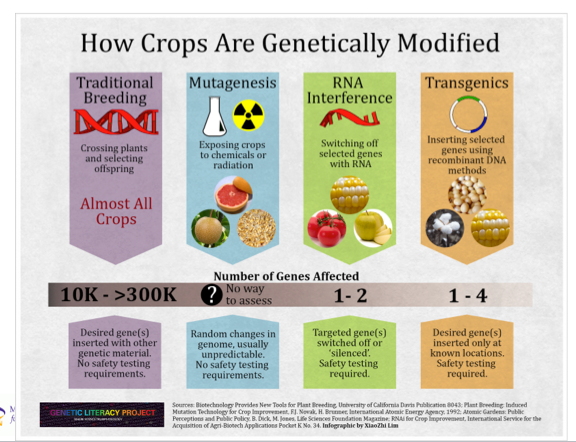
Why Newer Techniques (Genetic Engineering) Are Safer: Fewer Genes Affected Than Traditional Breeding and Mutagenesis along with Required Safety Testing

In the slide above, the first column shows traditional breeding of crops and how this can introduce thousands of changes into the crop.  The second column illustrates the use of chemicals and radiation (mutagenesis) to change crops; this type of crop engineering preceded genetic engineering and has not required the rigorous testing of the final two columns which depict modern biotechnology with either RNA interference of transgenetics.  Both of the later two methods are precise and undergo ~6-10 years of testing before introduction.

3

The above slide is one example of the safety of genetically modified tomatoes.

BT Corn (insect resistant) is Safer with Less Liver Cancer and Fewer Birth Defects

BT Corn (insect resistant) is Safer with Less Liver Cancer and Fewer Birth Defects

Key points:

  1. Genetic change in foods is as old as agriculture. Lots of vegetables/crops were not found in nature, including corn and wheat.
  2. Why is it false to talk about genetic modification as a special category? It’s all DNA which is undergoing constant change. Traditional breeding allows selection of random multiple genes and then selecting plant we like. Biotechnology is more precise and safer (eg. only the gene for sweetness for corn is transferred).
  3. 240 Agencies from across the globe have confirmed that biotechnology is safe because of the extensive testing that show these agents are at least as safe as ‘natural’ products. 2500 studies of GMO products from across the globe (not just Monsanto!) have proven the safety of these products.
  4. Other examples of beneficial biotechnology: a) BT Corn — safer, less liver cancer, less birth defects (myelomeningocele) b) Golden Rice –can solve iron & vitamin A deficiency.  Vitamin A deficiency contributes >1 million deaths/yr due to increased susceptibility to infections. Golden Rice in normal quantities provides RDA of Vit A. This is a lot more effective and less expensive than a supplement.

More tomorrow…