Eosinophilic Esophagitis Review -NEJM

Good review:  Glenn T. Furuta, M.D., and David A. Katzka, M.D. N Engl J Med 2015; 373:1640-1648

A couple pointers from this review:

  • Estimated prevalence of eosinophilic esophagitis (EoE) 0.4% in Western countries.  Symptoms are often underestimated due to patient ‘accommodation’ which includes eating slowly/carefully, drinking a lot of liquids and avoiding items more prone to become lodged (meats, pills, breads)
  • Pathogenesis: “Birth by cesarean section, premature delivery, antibiotic exposure during infancy, food allergy, lack of breast-feeding, and living in an area of lower population density have all been associated with eosinophilic esophagitis.”
  • Impaired barrier function and enhanced the activity play a role in pathogenesis
  • Food allergy is a non-IgE-mediated process.  Omalizumab, an anti-IgE biologic, is ineffective in EoE and EoE can develop in IgE-null mice
  • Male predominance (3:1) suggests that there is a genetic component.
Esophagus with ringed appearance, furrowing, and loss of vascular markings

Esophagus with ringed appearance, furrowing, and loss of vascular markings

Another useful reference on Eosinophilic Gastritis in Children: Am J Gastroenterol 2014; 109; 1277-85.  This article provides data on clinical and histologic remission with eosinophilic gastritis (>70 eos/hpf), n=30 children.  “Response to dietary restriction was high” (82% clinical, 78% histologic response) Thanks to Seth Marcus for this reference.

Related blog posts:

Antibiotics and Growth in India

A recent study (Rogawski ET, et al. J Pediatr 2015; 167: 1096-102) examined a prospective observational cohort of 497 children in India (from “semi-urban slums”).  The authors found that early exposure to antibiotics were not associated with increased or decreased growth.

“There are several potential explanations for the lack of a growth-promoting effect.  Most of the previous studies showing increased weight gain or risk of obesity associated with antibiotics were conducted in high-income countries with Western diets.”

My take: This was a negative study on antibiotics and obesity.  This suggests that the effects of antibiotics with regard to weight gain may be limited and/or modified by diet.

Also noted: Wakamoto H, et al. J Pediatr 2015; 167: 1136-42.  This study showed that Krebs von den Lungen-6 (KL-6) which is abundant on type II alveolar pneumoctyes and respiratory epithelial cells is a fairly good serum biomarker for chronic aspiration in this study of children with severe motor and intellectual disabilities.  Figure 1 shows the distribution of KL-6 among the 37 with aspiration and the 29 without aspiration.  The median in the former was 344 vs 207 in the later, though there was overlapping results.

Related blog posts:

Sandy Springs

Sandy Springs

Henoch-Schonlein Purpura and Neurologic Manifestations

Briefly noted:

Stefek B, et al. J Pediatr 2015; 167: 1152-4.  This study reports on an 8-year-old with Henoch-Schonlein purpura (HSP) who developed posterior reversible encephalopathy syndrome (PRES).  The authors state that neurologic manifestations develop in 2-8% of patients with HSP; of these patients, 20% suffer long-term effects.

Also, in commentary to my post on Thursday, one blog follower pointed out that the Fred Hollows Foundation is another charitable organization dedicated to restoring eyesight and has been doing this for a long time.

Atlanta Botanical Gardens

Atlanta Botanical Gardens

Milder Celiac Disease Being Diagnosed Now

A study (Kivela L et al. J Pediatr 2015; 167: 1109-15) over a period of 48 years from Finland provides some hard data regarding the changing presentation of celiac disease.

Here are the key points;

  • Age at diagnosis has increased from a median of 4.3 years before 1980 to 7.6 years and 9.0 years in later periods.
  • Poor growth has decreased.  Among the 46 children diagnosed prior to 1980, poor growth occurred in 66% whereas 2010-2013: 23% had poor growth (had 14% were overweight or obese)
  • Severity of small-bowel mucosal damage was milder (Figure 1 D).  Among those with gastrointestinal presentation, total villous atrophy also declined from “61-62% to 18-22% (P=.001).”

Why is the presentation changing? There are increased “proportions of screen-detected and asymptomatic children…[this has] increased over 6-fold and simultaneously gastrointestinal symptoms …decreased.”  While there are improved diagnostic methods and increased knowledge, there has also been a “well-defined increase in the true prevalence of celiac disease.”

Related blog posts:

More Training Needed for Wireless Capsule Endoscopy

A recent study (NM Hijaz et al. JPGN 2015; 61: 421-23) shows that there is little formal training in wireless capsule endoscopy.  Though this study was merely a 5-item questionnaire sent to program directors (adult and pediatric), it showed that only 4% of pediatric program respondents had a formal training module and only 27% have a hands-on course.  These results were based on a 39% pediatric program response (25/64).

My take: Despite the low response rate to the questionnaire, given the increasing use of WCE as an evaluation tool, better training is needed.

Related blog posts:

sunf

IBD ‘Pearls’

A clinical pearl is “a short, straightforward piece of clinical advice.” Here are a few:

2015 DDW abstract –#536 DR Hoekman et al “Non-trough IFX concentrations reliably predict trough levels and accelerate dose-adjustment in Crohn’s disease.”  This abstract examined data from 20 CD patients.  The authors noted that infliximab concentrations of 15 mcg/mL or higher at week 4 and 7.5 mcg/mL or higher at week 6 appeared to predict trough concentrations of 3 mcg/mL or higher at week 8.

U Kopylov et al. Inflamm Bowel Dis 2015; 21: 1847-53.  This nested case control study identified 19,582 eligible patients.  Key findings:

  • Treatment with thiopurines for more than 5 years did not increase the risk of lymphoma, melanoma or colorectal cancer.
  • There was an association between thiopurine use and nonmelanoma skin cancer (OR 1.78).
  • No association was found between the risk of the evaluated malignancies and anti-TNFα medications

K Huth et al. Inflamm Bowel Dis 2015; 21: 1761-68. This prospective cohort study completed over 2 successive influenza seasons showed that offering education and access to vaccination improved rates of vaccination from 47% (2011-12) to 75% (2013-14).  The education module is available: www.cheo.on.ca/en/IBDflu

KH Katsanos et al. “Review article: non-malignant oral manifestations in inflammatory bowel disease” Aliment Pharmacol There 2015; 42: 40-60. (Thanks to Ben Gold for this reference). This review article provides extensive information about oral lesions in IBD, differential diagnosis, numerous pictures, and management recommendations.  Some oral lesions are directly related to IBD, others can be induced by vitamin deficiencies or by medications.

One of my pet peeves -I avoid using straws

One of my pet peeves -I avoid using straws.  I heard this statistic several years ago and also see too many littered straws.

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Rectal Suction Biopsies Less Accurate in Infants <40 days

Briefly noted:

RJ Meinds et al Clin Gastroenterol Hepatol 2015; 13: 1801-07. In this retrospective analysis (1975-2011) of 529 rectal suction biopsies (RSBs) from 441 patients, the authors note lower sensitivity for RSB in infants <40 days.

From Table 3:

  • Hirschsprung’s disease patients <40 days: true-positive RSB 56/111 (50%), inconclusive RSB 32/111 (29%) and false negative 23/111 (21%)
  • Hirschsprung’s disease patients >40 days: true-positive RSB 136/154 (88%), inconclusive RSB 14/154 (9%) and false negative 4/154 (3%)
  • Non-HD patients <40 days: inconclusive RSB 2/48 (4%), false-positive RSB 0/48 (0%)
  • Non-HD patients >40 days: inconclusive RSB 10/216 (5%), false-positive RSB 1/216 (<1%)

Bottomline: This study may need to be replicated due to improvements in biopsy analysis (eg. calretinin); however, in the first 40 days of life, RSBs are more often inconclusive and/or false-negatives.  The use of anorectal manometry may be helpful.

Related blog posts:

Coors Field

Nutrition Symposium Georgia AAP (Part 3)

Along with Kylia Crane, I presented the final lecture at this year’s Georgia AAP Nutrition Symposium: Optimizing Nutrition and Formula Selection in Toddler’s and Children.  Kylia is a nutritionist and dietician at the Georgia AAP who works on a multitude of projects to enhance nutrition for pediatric patients across the state.  This lecture was intended as a practical review of feeding problems and poor growth.

After a brief discussion of some basic feeding principles, the lecture focused on specific case presentations and then reviewed formula selection.  At the end, I quickly mentioned some of the big nutrition stories for 2015. The entire talk will be available at the Nutrition4Kids website.

Here are some of the slides:

Screen Shot 2015-11-08 at 1.22.52 PM

Screen Shot 2015-11-08 at 1.20.16 PM

Screen Shot 2015-11-08 at 1.20.38 PM

Screen Shot 2015-11-08 at 1.21.13 PM

Screen Shot 2015-11-08 at 1.21.31 PM

Screen Shot 2015-11-08 at 1.21.47 PM

Screen Shot 2015-11-08 at 1.22.17 PM

Additional resources that I discussed:

FeedingTubeAwareness.com

—Ellyn Satter:

  • —“Child of Mine”
  • —“The Secrets of Feeding a Healthy Family”

—Laura Jana/Jennifer Shu:

  • —“Food Fights”

In the lecture, I credited some of the material to Dr. Praveen Goday who shared his slides from a previous lecture.  In addition, I am grateful to Dr. Seth Marcus who provided input into the lecture content.

Related blog posts:


Nutrition Symposium Georgia AAP (Part 2)

Last week I summarized an excellent talk by Ronald Kleinman.  For me, I had never heard such a concise and definitive rebuttal of the claims of those fearful of food biotechnology.  There were three other lectures at the symposium.  These three lectures covered areas that are well-known to pediatric gastroenterologists but less familiar to general pediatricians.  The full set of slides are available at the Georgia AAP Symposium Website.

Jeff Lewis had an excellent lecture that tied together gluten and our microbiome: Gluten – Eat not, suffer not and Microbiome 101: Waste Not, Want Not

After reviewing celiac disease and other wheat-related disorders (eg. wheat intolerance syndrome, and wheat allergy), he summarized a great deal of information regarding the human microbiome and which factors influence this. In addition, he had the opportunity to briefly present data from his research on fecal microbiota transplantation (for C diff) and its influence on the microbiome over time. Here are a couple of slides from his talk:


Screen Shot 2015-11-13 at 5.51.40 PM

Screen Shot 2015-11-13 at 5.50.12 PM

Screen Shot 2015-11-13 at 5.49.18 PM

Key points:

  • “It is hard to communicate science to families. It is a huge challenge for us.”
  • Dermatitis herpetiformis (rare in kids), a rash associated with celiac disease, can be treated with Dapsone. This rash has caused such severe itching that there are cases of suicide that have been reported.
  • For celiac disease, Dr. Lewis recommends testing of 1st degree relatives but this needs to be after gluten exposure and before gluten-free diet.
  • Wheat allergy reviewed. Skin test positivity does not prove that you are allergic to food. IgG based testing is worthless –it means you have been exposed to a food, but is not an indication of food allergy.
  • Nonceliac gluten sensitivity (aka. wheat intolerance syndrome): need to test for celiac first. No tests/biomarker that can confirm this diagnostic. This appears to be a true disease; there is a small subset of patients who develop symptoms with a double-blind challenge.
  • Microbiome –more bacterial DNA in us than human DNA. New organisms –archaea kingdom.  Now a specimen of a person’s microbiome can be run for <$50.
  • Microbiome terms: Richness, Diversity, and Dysbiosis. Many diseases are associated with dysbiosis (obesity, IBD), but there is a ‘chicken and the egg’ problem. Is dysbiosis a causal factor or a secondary factor?
  • Xyloglucans (in lettuce) –not broken down by humans and affected by gut bacteria.
  • Mice given stool from fat mice or fat person become heavy.

Nutrition Symposium Georgia AAP (Part 1)

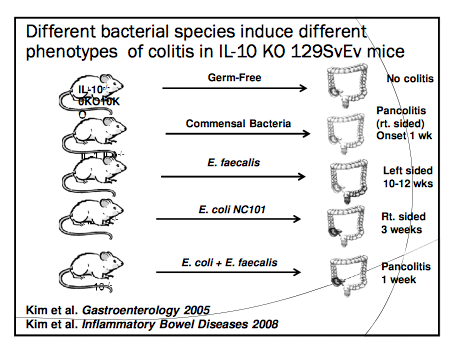
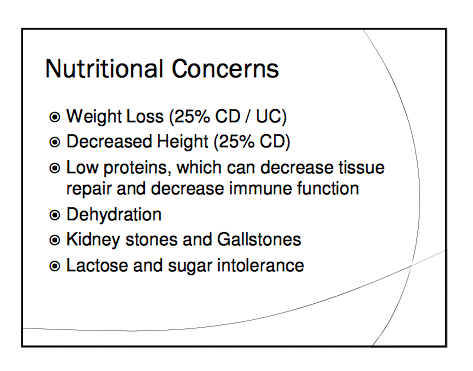
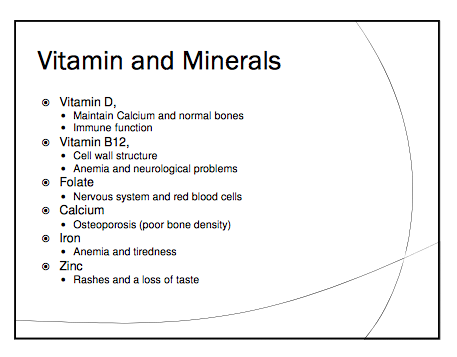
At this year’s nutrition symposium, Dr. Stan Cohen presented the latest information on nutrition and inflammatory bowel disease.  His entire presentation will be on the Nutrition4Kids website.  While I took a few pictures, my notes from his presentation were minimal, mainly because I had to give a talk afterwards.  He reviewed how the microbiome can be influenced by diet and that this in turn can result in phenotypic changes.  Specific complications from poor diet/nutrient deficiencies were discussed.  In addition, data from exclusive enteral nutrition and the specific carbohydrate diet were presented. Here are some slides from his lecture (also available at Georgia AAP Symposium Website):

Screen Shot 2015-11-13 at 5.55.55 PM

Screen Shot 2015-11-13 at 5.57.12 PM

Screen Shot 2015-11-13 at 5.57.27 PM

Screen Shot 2015-11-13 at 6.01.10 PM

Related blog posts: