




A recent study (S Nageswaran et al. J Pediatr 2018; 203; 354-60) examined parents’ perceptions about their decision to proceed with a tracheostomy. As a GI doctor, I am not directly involved in the discussions about tracheostomy; however, we interact closely with many complex patients whose families have reached this decision. Many times I have wondered whether families regret this decision and whether a more palliative approach may have been appropriate in some children.
In this study with interviews from 56 caregivers of 41 children, their was very high satisfaction with the decision to proceed with a tracheostomy. All children in this study had a tracheostomy for 5 years or less.
The parents reported the following reasons:
Key finding: Among 38 interviews, 38 out of 41 explicitly expressed satisfaction with their decision to pursue a tracheostomy. In none of the interviews did any caregiver express clear regrets about their decision.
At the same time, the parents acknowledged difficulties like mucus plugs, accidental decannulation, and difficulty of home care with a tracheostomy..

Briefly noted: A Meyer et al. Ann Intern Med. 2018. DOI: 10.7326/M18-1512
Abstract link: Effectiveness and Safety of Reference Infliximab and Biosimilar in Crohn Disease: A French Equivalence Study
In this study with 5050 patients, based on review of an administration database, the authors found the following:
The authors conclude that “real-world data indicates that the effectiveness of CT-P13 is equivalent to that of RP for infliximab-naive patients with CD.”
Related blog posts:
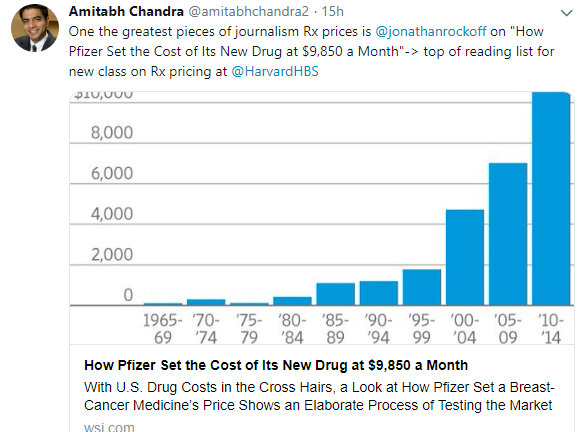
WSJ: How Pfizer Set the Cost of Its New Drug at $9,850 a Month
An excerpt:
The average cost of a branded cancer drug in the U.S. is around $10,000 a month, double the level a decade ago
Pfizer’s multistep pricing process shows drugmakers don’t just pick a lofty figure out of the air. At the same time, its process yielded a price that bore little relation to the drug industry’s oft-cited justification for its prices, the cost of research and development.
Instead, the price that emerged was largely based on a complex analysis of the need for a new drug with this one’s particular set of benefits and risks, potential competing drugs, the sentiments of cancer doctors and a shrewd assessment of how health plans were likely to treat the product…
In 2013, Pfizer hired outside firms to conduct hourlong interviews with more than 125 cancer doctors in six cities…
Pfizer hired firms that surveyed more than 80 health-plan officials such as medical directors and pharmacists…
Pfizer employees say the mock reviews supported a monthly price below $10,000. If it was higher, insurers could start requiring doctors to fill out paperwork justifying its use.
My take: This article makes clear that the driver of higher pharmaceutical prices is based on a shrewd assessment of what the market will bear.
Related blog posts:
Recently, I listed the posts that had the most views in the past year –some dating back to 2012. The following list includes less viewed but some of my favorite posts from 2018:
GI:
Nutrition:
LIVER:
Miscellaneous:

Flowers in Calgary
Since this blog’s inception, there are now more than 2500 posts; these are the most popular (most views):
Most of these posts are referenced in more recent posts on the same or similar subjects.

Near Banff
A recent randomized controlled, open-label study (S Wirth et al. Hepatology 2018; 68: 1681-94) examined the use of weekly peginterferon alfa-2a (PEG) in 161 children (3-18 yrs) with immune-active HBe-Ag-positive children. The two main groups were for those without advanced fibrosis: a PEG group (n=101) and a placebo group (n=50). A third group enrolled 10 patients with advanced fibrosis who all received PEG. The treatment period was 48 weeks with ongoing observation for an additional 24 weeks.
Key findings:
My take: This study does not answer the question about which treatment is optimal for hepatitis B in children–direct-acting antivirals (eg. entecavir, and tenofovir) or peginterferon. It does shows that weekly peginterferon alfa-2a was associated with HBeAg seroconversion in 26% of recipients at week 72. Although a high number of patients experienced adverse effects, there were no new safety signals identified.
Related blog posts:

View from Parker Ridge, near Banff

These five posts were the most popular (most views) in the past year:

This is a bike path from Canmore to Banff. I had a chance to ride an electric bike which was a lot of fun.
Briefly noted: M Izzy, J Oh, KD Watt. Hepatology 2018; 68: 2008-2015. This concise review discusses the outcome of cirrhotic cardiomyopathy after liver transplantation.
Key point: “Although it is often believed that cirrhotic cardiomyopathy resolves post-LT, the data, albeit limited, do not support this postulation…diastolic function may not improve post-transplant and may actually worsen. Improvement in systolic function was suggested by only two of six studies.”
Related blog post: Cholecardia

This figure from Hepatology November cover depicts a cirrhotic liver restricting the heart filling during diastole. (From Wiley Online Library -free access)
A recent randomized controlled trial (C Properzi et al. Hepatology 2018; 68: 1741-54) compare the Mediterranean diet (MD) and a low-fat (LF) diet for non-alcoholic fatty liver disease.
A total of 48 patients completed the 12-week study and were analyzed; subjects had a mean BMI of 31. Both groups consumed a 2400-2600 kcal diet.
Key findings:
The associated editorial (pg 1668-71) notes the following:
My take: If you have to make a dietary recommendation, this study indicates that MD is probably a better diet than LF in patients with NAFLD.
Related blog posts:


Town of Banff

