
pH Probe Testing: Rumors of My Death are Premature

Several years ago, an “obituary” was written for the pH probe (Putnam PE,J Pediatr.  2010; 157(6):878-80) due to the presumed superiority of pH-impedance (pH-MII) studies in detecting gastroesophageal reflux disease (GERD)  As noted in previous blogs (see below), there have remained a number of concerns with the assumption that pH-MII is an improvement over pH studies without impedance.  Several recent studies elaborate on those concerns:

  1. Cheng F-K F, et al. Clin Gastroenterol Hepatol 2015; 13: 867-73
  2. Patel A, et al. Clin Gastroenterol Hepatol 2015; 13: 884-91
  3. Vaezi MF. Clin Gastroenterol Hepatol 2015; 13: 892-94 (editorial)

In the first study, the authors identified 221 patients and retrospectively reviewed GERD testing from 2006-2011.  Prior to testing, 97% had received prescribed PPIs before testing; however, PPIs were discontinued for at least 1 week prior to evaluation which included upper endoscopy, esophageal manometry, and pH-MII.

  • 21 (10%) had erosive esophagitis
  • 61 (27%) had nonerosive reflux disease with increased pH
  • 18 (8%) had nonerosive reflux disease with abnormal impedance
  • 30 (14%) had hypersensitive esophagus
  • 18 (8%) had functional heartburn
  • 30 (14%) had other functional disorders
  • 43 (19%) were undetermined

Thus, this retrospective study showed that the majority (roughly 2/3rds) of patients with GERD symptoms on PPI therapy did not have GERD based on objective testing.  The authors chose to test off PPI therapy “because we postulated that the pretest probability of GERD diagnosis was low, primarily given their lack of response to PPI.”

In the second study, 187 subjects (≥18 years) underwent pH-MII testing in a prospective study from 2005-2010.  49.7% were tested off proton pump inhibitor therapy. Abnormal acid exposure time consistently predicted symptomatic outcome.  The authors note that performing pH-MII off PPI therapy best predicts response to antireflux therapy

In the third reference, the editorial which commented on the second, there are several useful points:

  • “There is little doubt that pH-impedance testing provides a more sensitive means of comprehensively identifying reflux events in a given patient. However, to date, studies have failed to demonstrate that it provides any significant additional clinical benefit.”
  • “Caution must be exercised when incorporating the added objective data from non-acidic or weakly acidic reflux events into treatment decision-making…Studies including Patel et al have not shown that knowledge regarding continued non-acid or weakly acid reflux events alter patient outcomes.”
  • “Wireless pH testing is generally better tolerated and provides longer measurement duration”
  • The use of symptom indices are too subjective.  “Recent data question the use of these indices especially in those with refractory symptoms and minimal reflux by pH or impedance testing.”  SI and SAP could be altered by chance occurrences….”A colleague expert in esophageal diseases …once said: “I know the tests are no good but I don’t know what else to use.'”
  • “Let us simplify our approach on the basis of available data and not use measures that we know are suboptimal at best.”

After looking at these studies and the previous pH probe obituary, I’m reminded of a story.  Several religious leaders were asked what they wanted someone to say at their funeral.  A few stated that they wanted their congregants/flock to comment on their values, like piety and charity.  However, one said, “I hope they say, ‘Look he’s moving!'”

Bottomline: There is no reliable evidence that pH-MII testing improves outcomes over conventional pH probe testing. In fact, the use of pH-MII, by lowering the specificity for GERD, could have a detrimental effect.  With either test, holding acid suppression for 1 week (with PPIs) is likely to be helpful in interpreting the results.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Zoo Atlanta
Zoo Atlanta

No Effect of Proton Pump Inhibitors and Irritability on Crying in Infants

While the title of this blog will come as no surprise to most pediatric gastroenterologists, many parents would be surprised that a systemic review of randomized controlled trials (RCTs) showed` that proton pump inhibitors (PPI) are ineffective for crying infants (J Pediatr 2015; 166: 767-70).

In this review, only five trials (with 430 infants) met the prespecified inclusion criteria.  While some trials showed a decrease in crying/irritability form baseline to the end of the intervention, a similar effect was evident in the control group.  The authors found that one trial reported a higher risk of lower respiratory tract infections in the PPI group and note that “administration of PPIs is not without risk.”

Take-home message: “the limited data available suggest that PPIs are not effective for the management of crying/irritability in infants.”

Another PPI citation: Rosen R et al. J Pediatr 2015; 166: 917-23.  In this study, the authors prospectively showed that PPI use was associated with differences in gastric, lung, and oropharyngeal microflora (n=116 children with 59 receiving PPIs)

Related blog posts:

Transoral Fundoplication for Refractory Gastroesophageal Reflux

A new endoscopic technique’s efficacy has recently been reported (Gastroenterol 2015; 148: 324-33).  Since this technique is not likely to be broadly applicable to the pediatric population for some time, I will not delve into all of the details.

In essence, a carefully selected group (n=129 from a screened group of 696) of adult patients with persistent regurgitation underwent transoral fundoplication; this eliminated troublesome regurgitation in 67% compared to 45% who were randomized to sham/PPI.  Severe complications were rare.

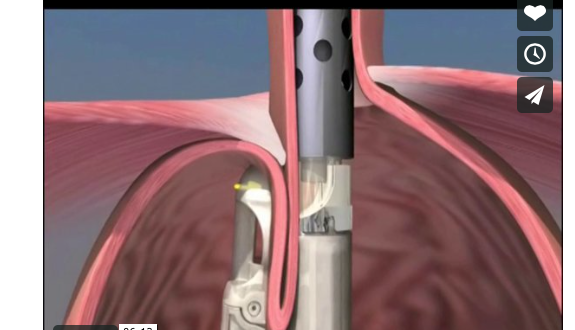
Here is a picture of the technique:

Transoral Fundoplication

Transoral Fundoplication

Link: Description and a video animation of the procedure

Bottomline: This endoscopic procedure along with the Stretta procedure and the LINX device (using magnets) offer alternatives to surgical fundoplication in carefully-selected patients with refractory gastroesophageal reflux symptoms.

New drugs approved by FDA:

Ceftolozane (Zerbaxa) -combines a cephalosporin with a beta-lactamase inhibitor (tazobactam).  Indications: complicated intra-abdominal infections (in combination with metronidazole), and complicated urinary tract infections. From FDA: FDA approves new antibacterial drug Zerbaxa

Viekira Pak -combination of 3 new drugs: ombitasvir, paritaprevir, and dasabuvir along with  older drug: ritonavir.  Indications: Hepatitis C genotype 1. From FDA: FDA approves Viekira Pak to treat hepatitis C

Related blog posts to fundoplication:

Which is Safer –Drip Feeds or Bolus Feeds in Healthy Preterm Infants?

A recent provocative study (J Pediatr 2014; 165: 1255-7) takes a look at the frequency of cardiorespiratory events in healthy neonates <33 weeks gestation who needed supplemental enteral tube feeds.

It is generally accepted that continuous or “drip” feedings are less likely to provoke reflux events (and reflux-induced cardiorespiratory events) by limiting the amount of formula in the stomach at any time point.  If there is less formula, presumably there would be less stomach distention and a lower likelihood of reflux.  In addition, a continuous amount of formula would serve to buffer stomach acid.

Despite the sound theoretical underpinnings, is this really true?  In this study, the authors detected fewer cardiorespiratory events with polysomnographic monitoring in healthy premature neonates who were fed with bolus feedings rather than with drip feedings.

Study design: Each of 33 infants served as its own control.  During a 6-hour monitoring period, noninvasive polysomnographic recordings were performed.  Each infant was fed twice via an orogastric tube.  The first meal was given as a 10-minute bolus (by gravity) and the second was delivered over 3 hours. It is noted that the tube was removed after the bolus feeding (this is not routinely done in clinical practice).

Demographics: Median gestational age was 31 weeks and median postnatal age was 16 days.  Fortified human milk was given in 12, premature formula in 7, and 14 had mixed feeding.

Results (Table 2): “continuous feeding was associated with a greater number of prolonged apneas and apnea-related hypoxic episodes.”

  • Median Apnea Frequency: 4 in continuous versus 2 in bolus group (no obstructive apneas were noted)
  • Median hypoxic episodes: 3 in continuous versus 2 in bolus group.

The authors speculate that leaving the tube in place for continuous feeds could increase GER-related apnea or trigger ‘protective upper airway reflexes in response to the irritating stimulus.’

Bottomline: The assumption that continuous feedings will reduce cardiorespiratory events is not supported by this study.  The findings warrant cautious interpretation; the small sample size and specific ages of the premature infants are significant limitations.   In addition, leaving an enteral tube in place after a bolus feeding would be a better design as this is a routine practice.

Related blog post:

Accuracy of ENT diagnosis of Reflux Changes

Many gastroenterologists suspiciously view a diagnosis of laryngopharyngeal reflux (LPR) as assessed by an Ear, Nose, and Throat (ENT or otorhinolaryngologist) physician.  This is due to a high degree of variability of these visible findings in a number of studies.  A recent pediatric study reaches the same conclusion (J Pediatr 2014; 165: 479-84).

In this study, the authors recruited 52 infants in an effort to establish a reflux finding score for infants (RFS-I).  This infant scale was modified based on a previous RFS developed in adults (Laryngoscope 2001; 111: 1313-7).  In these infants, scored videos were evaluated by 3 pediatric ENTs, 2 adult ENTs, and 2 gastroenterology fellows.

Specific finding:

  • “laryngeal erythema/edema showed the lowest observer agreement…it is often speculated that laryngeal edema is caused by LPR, but no convincing evidence is available to support this theory.”

Bottomline: “Only moderate interobserver agreement [of the RFS-I] was reached with a highly variable intraobserver agreement…the RFS-I and flexible laryngoscopy should not be used solely to clinically assess LPR related findings of the larynx, nor to guide treatment.”

Related blog post:

Clinical Features of 22q11.2 Deletion Syndrome

Since I participate in the 22q Specialty Clinic in Atlanta, I am interested in relevant clinical studies.  A recent study provides more information on clinical features and follow-up (J Pediatr 2014; 164: 1475-80).

This retrospective and prospective multicenter study involved 228 patients.  The median age at diagnosis was 4 months.  In 71% the diagnosis was made before age 2 years and predominantly related to congenital heart disease and neonatal hypocalcemia.

Key findings:

  • The survival probability was 0.92 at 15 years from diagnosis, most commonly from severe cardiovascular complications.  Two subjects died without cardiac defects, one with severe autoimmune anemia and the second with lymphoproliferative disease.
  • Congenital heart disease was confirmed in 79% of the entire cohort.
  • Neonatal hypocalcemia was noted in 43%
  • ENT manifestations were present in 59% and included most commonly velopharyngeal insufficiency
  • GI manifestations were noted in 41%, particularly feeding difficulties in infancy.  Anorectal malformations were identified in 5% and esophageal atresia was noted in 1%.  GI problems tended to improve during followup, particularly gastroesophageal reflux.  During followup, three children with abdominal pain (along with leg pain) had mild hypocalcemia.
  • Autoimmune manifestations developed in 11%, most commonly autoimmune thrombocytopenia.

Related blog posts:

Link: Practice guidelines for 22 q (from UC Davis Website and J Pediatr. 2011 Aug;159(2):332-9.e1. doi: 10.1016/j.jpeds.2011.02.039).

How Proton Pump Inhibitors Can Cause Infections

In yesterday’s blog, the editorial on “Acid-reducing agents in infants and children: friend or foe?” also commented on an additional study (JAMA Pediatr. 2014. doi: 10.1001/jamapediatrics.2014.696) which addresses the issue of how proton pump inhibitors (PPIs) may contribute to an increased risk of infections.  It is well-known that use of PPIs (and to a lesser extent histamine-2 receptor antagonists) contribute to a significant increased risk of community-acquired pneumonias and gastrointestinal infections (probably including necrotizing enterocolitis in infants).

In this study, (from the editorial) “acid suppression was associated with a positive gastric culture (P =.003) and increased median concentration of gastric bacteria (P<.001). Full-column nonacid reflux was associated with higher concentrations of bacteria in the lung.”

In this era of pioneering microbiome research, it is not surprising that chronic changes in gastric acid production could cause these results.  This is something to consider when calculating risks and benefits, particularly in situations where the benefits are quite minimal.

Here’s the abstract:

Importance  The use of acid suppression has been associated with an increased risk of upper and lower respiratory tract infections in the outpatient setting but the mechanism behind this increased risk is unknown. We hypothesize that this infection risk results from gastric bacterial overgrowth with subsequent seeding of the lungs.

Objectives  To determine if acid-suppression use results in gastric bacterial overgrowth, if there are changes in lung microflora associated with the use of acid suppression, and if changes in lung microflora are related to full-column nonacid gastroesophageal reflux.

Design, Setting, and Participants  A 5-year prospective cohort study at a tertiary care center where children ages 1 to 18 years were undergoing bronchoscopy and endoscopy for the evaluation of chronic cough. Acid-suppression use was assessed through questionnaires with confirmation using an electronic medical record review.

Main Outcomes and Measures  Our primary outcome was to compare differences in concentration and prevalence of gastric and lung bacteria between patients who were and were not receiving acid-suppression therapy. We compared medians using the Wilcoxon signed rank test and determined prevalence ratios using asymptotic standard errors and 95% confidence intervals. We determined correlations between continuous variables using Pearson correlation coefficients and compared categorical variables using the Fisher exact test.

Results  Forty-six percent of patients taking acid-suppression medication had gastric bacterial growth compared with 18% of untreated patients (P = .003). Staphylococcus (prevalence ratio, 12.75 [95% CI, 1.72-94.36]), Streptococcus (prevalence ratio, 6.91 [95% CI, 1.64-29.02]), Veillonella (prevalence ratio, 9.56 [95% CI, 1.26-72.67]), Dermabacter (prevalence ratio, 4.78 [95% CI, 1.09-21.02]), and Rothia (prevalence ratio, 6.38 [95% CI, 1.50-27.02]) were found more commonly in the gastric fluid of treated patients. The median bacterial concentration was higher in treated patients than in untreated patients (P = .001). There was no difference in the prevalence (P > .23) of different bacterial genera or the median concentration of total bacteria (P = .85) in the lungs between treated and untreated patients. There were significant positive correlations between proximal nonacid reflux burden and lung concentrations of Bacillus (r = 0.47, P = .005), Dermabacter (r = 0.37, P = .008), Lactobacillus (r = 0.45, P = .001), Peptostreptococcus (r = 0.37,P = .008), and Capnocytophagia (r = 0.37, P = .008).

Conclusions and Relevance  Acid-suppression use results in gastric bacterial overgrowth of genera including Staphylococcus and Streptococcus. Full-column nonacid reflux is associated with greater concentrations of bacteria in the lung. Additional studies are needed to determine if acid suppression–related microflora changes predict clinical infection risk; these results suggest that acid suppression use may need to be limited in patients at risk for infections.

Related blog posts:

GERD Treatment in Infants: “Friend or Foe”

From a recent JAMA Peds editorial: (JAMA Pediatr. Published online August 18, 2014. doi:10.1001/jamapediatrics.2014.1263)

An excerpt:

Gastroesophageal reflux disease (GERD) is common in infants and children and has been estimated to affect as much as 3.3% of the pediatric population.1 Despite this, we still struggle with the management of GERD. With a growing body of literature that illustrates a lack of efficacy and alarming adverse effects, there is increasing reason to limit the empirical use of acid suppression therapy in children.

Other points highlighted in this editorial:

  • 36% of pediatricians prescribe PPIs for infants with uncomplicated regurgitation -“despite evidence and recommendations against this approach.”
  • 39% of pediatricians prescribed proton pump inhibitors (PPIs) for infants with unexplained crying
  • Conditions predisposing a child for severe GERD include those with neurological impairment, repaired esophageal atresia, cystic fibrosis, hiatal hernia, repaired achalasia, and lung transplantation.
  • In the related article ((JAMA Pediatr. doi: 10.10001/jamapediatrics.2014.1273), the authors reviewed 8 studies of histamine-2 receptor antagonists (H2RAs) and noted no improvement in overall symptoms infants.  In older age groups, H2RAs were more effective than placebo in symptom reduction, and histological healing.

Take-home message: “It is becoming clearer that in many circumstances, prescribing acid-reducing medication to infants is doing no good and increasing the risk of harm.”

Related blog posts:


Will This Change ALTE-GERD Practice?

This blog has highlighted several publications which have shown the lack of benefit and potential harm of pharmaceutical agents for gastroesophageal reflux “disease” (GERD) in infancy (see links below). However, in current practice, proton pump inhibitors and histamine receptor antagonists are used frequently.  Now, another influential study (J Pediatr 2014; 165: 250-5) has shown the lack of GERD as a causal mechanism in acute life-threatening events (ALTEs) and demonstrated other pathophysiologic mechanisms. However, changing physicians’ practice in this regard may prove to be as difficult as avoiding overprescribing antibiotics, or convincing reluctant parents to vaccinate their children.

So what did this study show?

This study of 20 infants (10 with proven ALTE and 10 healthy controls) had pharyngoesophageal manometry.  Key findings:

  • Infants with ALTE (vs controls) had delays in restoring aerodigestive normalcy (P=.03).  This was indicated by more frequent and prolonged spontaneous respiratory events (SREs)
  • Infants with ALTE had a lower magnitude of protective upper esophageal sphincter contractile reflexes (P=.01)
  • Infants with ALTE had swallowing as the most frequent esophageal event associated with SREs (84%), a higher proportion of failed esophageal propagation (10% vs 0%, P=.02), an more frequent mixed apnea mechanisms (P=<.01) along with gasping breaths (P=.04)

The associated editorial (pg 225-26) explains some of the limitations of the study, including the fact that the patients had a mean gestational age of 28 weeks.

The authors conclusion: “In infants with ALTE, prolonged SREs are associated with ineffective esophageal motility ,,,suggestive of dysfunctional regulation of swallow-respiratory junction interactions.  Hence, treatment should not target gastroesophageal reflux, but rather the proximal aerodigestive tract.”

Take-home message: (from the editorial): “Far too many low birth weight (and term) infants are being unnecessarily treated with a variety of antireflux medications that have serious side effects and few, if any, demonstrable benefits.”

Related blog posts:

“If all you have is a hammer…”

In my training, one of my mentors would be critical of the mentality “scope first, think second.”  He was concerned that too many gastroenterologists/pediatric gastroenterologists used endoscopy as a tool simply “because if all you have is a hammer, the world looks like a nail.”

A recent publication (Clin Gastroenterol Hepatol 2014; 12: 963-69) on first glance, however, provides ammunition to the “scope first” gastroenterologists and undermines the concept that “functional” GI disorders vastly outnumber “organic” GI disorders.  The key finding was that esophagogastroduodenoscopy (EGD) provided an “accurate” diagnosis in 38%.  This included reflux esophagitis in 21%, eosinophilic esophagitis (EoE) in 5%, eosinophilic gastroenteritis (EGE) in 4%, H pylori in 2%, celiac disease 0.6%, and Crohn’s disease 0.4%. This finding is dramatically higher than previous studies.  In fact, in a recent published study (Understanding Idiopathic Nausea | gutsandgrowth) on idiopathic nausea, a control group of patients with chronic abdominal pain had a normal endoscopy in 100%!

In this prospective study of 290 children (ages 4-18 years with a mean age of 11.9 years), the primary indication for upper endoscopy was chronic abdominal pain.  Of this 290, 216 had at least 1 alarm feature and 125 had at least 2 alarm features.  Alarm features were considered to be the following:

  • Nighttime awakening 33.3%
  • Weight loss 15.6%
  • Family history of IBD 8.4%
  • Vomiting 7.8%
  • Dysphagia 6.9%
  • Nocturnal diarrhea 6.7%
  • Gastrointestinal bleed 5.8%
  • Chronic diarrhea 5.8%
  • Unexplained fever 4.4%
  • Arthralgia 4.0%
  • Growth failure 2.4%
  • Perirectal disease 0.7%
  • Delayed puberty 0.2%

There is little debate that abdominal pain in combination with true alarm symptoms (True red flags in recurrent abdominal pain | gutsandgrowth) merits further evaluation.  The aspect of this report that is worthy of close inspection is the diagnostic yield in the 74 patients without alarm symptoms.  The authors note that 25 (33.7%) had a diagnosis established with EGD including 16 with reflux esophagitis, 4 with EGE, 2 with EoE, 1 with erosive esophagitis, 1 with celiac and 1 with H pylori.  The diagnostic criteria for EGE included ≥10 eosinophils per hpf in the stomach and ≥20 eosinophils per hpf in the duodenum.

The authors note that the diagnostic yield was based on gross endoscopic findings in procedure notes or histologic changes in biopsy reports; “final pathology report on biopsies provided the data source for histologic diagnosis.”

In my opinion there are multiple flaws of this prospective study.

1. There is a very high rate of reflux esophagitis in both the alarm group and the non-alarm group patients with chronic abdominal pain.  Of the entire cohort (n=290), the authors identified reflux esophagitis in 21% and this was “primarily histologic esophagitis.”  Furthermore, the authors state that “the presence or response to PPI therapy was not predictive of esophagitis or GERD.”  So, the obvious problems:

  • Presence of histologic reflux esophagitis varies widely based on the interpreting pathologist.  In a prospective study, more than one pathologist interpreting the histology would be useful.
  • Presence of histologic reflux esophagitis does not exclude the likelihood of coexisting functional disorders (related blog post: Why didn’t patient with documented reflux get better with PPI …).  As a practical matter, “slight” or “focal” esophagitis on histology has questionable real-world relevance in pediatric gastroenterology.
  • The authors acknowledge, “current expert consensus indicates that histology has limited value in evaluating pediatric GERD.”  Yet this diagnostic finding is one of the reasons why the authors claim that EGD is so valuable.

2. In the entire cohort, the authors try to validate their findings by indicating that identification of a diagnosis led to medical therapy that was “effective in approximately 67%” of children with short-term followup. (Only 81% had short-term followup outcomes available).  Yet, there is no control group.  How many children with chronic abdominal pain will improve for a short period without an EGD-based diagnosis?  The answer: a lot of them.

3. Limitations include selection bias toward those with more severe symptoms or alarm symptoms.  In addition, this study included only a small number who were considered to have no alarm symptoms.  Finally, the short-term followup makes conclusions about the response to therapy questionable.

This study will be a useful reference for any pediatric gastroenterologist who wants to justify the need for an endoscopy.  The authors note “the majority of children in our study (93%) met criteria for functional gastrointestinal disorders, and a significant proportion (38%) still had significant histologic findings.  Therefore, we conclude the Rome III criteria alone are not sufficient to identify children who require upper endoscopy, and screening for alarm symptoms has limited utility.”

In my opinion, the reliance on histology as well as selection bias weaken the findings of this study.  If a patient with a histologic diagnosis of reflux (or several other entities) and a presentation of chronic abdominal pain does not improve, the pediatric gastroenterologist should remember that only “a poor carpenter blames his tools.”

Bottomline: EGD remains an important tool in evaluating abdominal pain.  However, I think this study substantially overestimates its utility.

Related blog posts: