
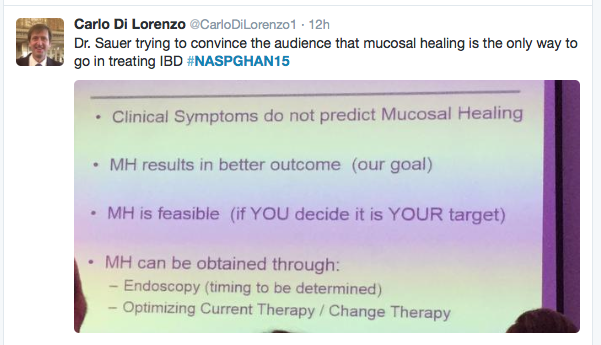
From debate regarding importance of mucosal healing:
Related blog posts:


From debate regarding importance of mucosal healing:
Related blog posts:
A short communication (C Pant et al. JPGN 2015; 61: 282-84, ed 267-8) provides some insight into what is happening in the ER when patient with inflammatory bowel disease are evaluated.
The authors analyzed a national database, the Healthcare Cost and Utilizationa Porject Nationwide Emergency Department Sample (NEDS), from 2006-2010.
Key findings:
The associated editorial by Jennifer Dotson and Michael Kappelman explain the limitations of relying on data that are derived mainly for billing rather than research and comment on the “alarming increase” in CT usage due to the risk of radiation exposure and the potential alternatives (eg. ultrasound, MRE). With regard to limitations, they likely included inaccurate and incomplete entries. In addition, the database included 950 hospitals, but may have under-sampled large freestanding children’s hospitals. This could skew the data. Finally, the data uses “visit-level” data rather than “patient-level” data; thus, one ‘cannot distinguish between a single patient who is seen on three separate visits or three unique patients.’
My take: There has been increasing use of ER visits and CT scanning for pediatric patients with IBD. One of my colleagues in town (Cary Sauer) has a humorous slide of a CT scanner as the entrance door to the ER. The message from this study indicates that we should be working on changing practice by working with our ER colleagues along with radiologists to minimize CT scans in favor of more gently imaging.
Related blog posts:

Atlanta Botanical Gardens, Bruce Munro exhibit
With the respiratory virus season fast approaching, a recent study and editorial (J Szymczak et al. JAMA Pediatr 2105; 169: 815-21, editorial 809-10 -thanks to Ben Gold) are worth a look; they focus attention on the practice of working while sick. In the study, the researchers use an anonymous survey of more than 900 physicians and advance practice clinicians working at a large children’s hospital. 83% reported working sick at least 1 time in the past year and 9% reported working while sick at least 5 times. The authors note “some ambiguity persists around what constitutes being too sick to work, and a perception exists that sick leave is impractical.” Most of the respondents understood that their illness could have an adverse effect on patients, but 97% did not want to let colleagues down and 94% did not want to create staffing shortages.
The editorial makes several more points:
My take: These articles suggest a need for a culture change that supports paid sick leave that is adequate and non-punitive. At the current time, adequate backup is often lacking. Also, these articles serve as a reminder: it is a good idea to get your flu shot!
A recent study (E Echocahrd-Dugelay et al. JPGN 2015; 61: 346-54, editorial 268-9) provides a little more data on the rare condition of portopulmonary hypertension (POPH). Untreated POPH can lead to right-sided heart failure and death; a prompt diagnosis improves the chance for responding to treatment.
In brief, the authors reviewed their experience with 14 patients that were diagnosed with POPH between 1983-2009. The authors also reviewed the literature for a total of 98 patients.
Findings:
Dr. Ronald Sokol’s commentary noted that guidelines for timing/frequency of pulse oximetry testing and formal echocardiographic screening are needed but “challenging given the present body of evidence.” He recommends screening all pediatric liver transplantation candidates who have cirrhosis and portal hypertension with pulse oximetry and echocardiography as well as those with clinical features of POPH (eg. syncope, shortness of breath, dyspnea). For other patient populations, it remains unclear.
Bottomline (from the authors): “Detection of POPH at an early stage requires systematic screening at regular intervals by echocardiography in children with all causes of portal hypertension.” Unanswered questions:
Related blog posts:

A provocative article poses the question: Should we bank our own stool?
Here’s an excerpt:
The scientific term for this is “autologous fecal transplant.” In theory, it could work like a system reboot disk works for your computer. You’d freeze your feces, which are roughly half microbes, and when your microbiome became corrupted or was depleted with antimicrobials, you could “reinstall” it from a backup copy.
That damage from antibiotics may not be trivial. Studies have linked antibiotic use early in life with a modestly increased risk of asthma,inflammatory bowel disease, obesity and rheumatoid arthritis. These are associations, of course; they don’t prove that antibiotics cause disease…
Almost 60 years later, the “fecal transplant” is a cutting-edge treatment for the pathogen Clostridium difficile, a bug that kills 29,000 yearly and infects nearly half a million…
Memorial Sloan Kettering Cancer Center in New York has also started a proactive stool-banking study. Most of the subjects are patients with leukemia. Before stem cell transplants, patients receive antibiotics andchemotherapy, often wiping out their microbiota…
OpenBiome…started a pilot self-banking program called “PersonalBiome.” One complication: If he stores your stool, you can generally withdraw it only to treat C. difficile, not for preventive “reconstitution.” That’s because stool is regulated as a drug and not, as with embryos or blood, a tissue, which makes its use more complex.
Related blog posts:

Atlanta Botanical Garden, Bruce Munro Exhibit
Opportunity Costs of Doctor Visits -YouTube Video
From the Boston Globe:
The study estimates that the typical visit to a doctor consumes 121 minutes of the patient’s time — 37 minutes in travel, 64 minutes waiting for care or filling out forms, and only 20 minutes face to face with the physician.
Based on the average sum a person could earn if working during that time, the researchers figure, it costs patients $43 in lost time for each medical visit — more than the average out-of-pocket cost for the care itself, which is about $32.
Mehrotra’s team drew their results from three national surveys, chiefly the 2003-2010 American Time Use Survey, administered by the Bureau of Labor Statistics. The survey asked randomly selected respondents to recall what they did from 4 a.m. on the previous day until 4 a.m. on the day of the survey. The researchers examined the experiences of the 3,927 respondents who had sought medical care during that 24-hour period.
The initial study: Opportunity Costs of Ambulatory Medical Care in the United States Kristin N. Ray, MD, MS; Amalavoyal V. Chari, PhD; John Engberg, PhD; Marnie Bertolet, PhD; and Ateev Mehrotra, MD, MPH. Published in American Journal of Managed Care (August 2015)
Progressive Familial Intrahepatic Cholestasis, type 2, (PFIC2) is due to decrease (or absent) function of the bile salt export pump (BSEP) encoded by ABCB11 has been treated mainly in a symptomatic manner with medicines like ursodeoxycholic acid and sometimes biliary diversion. PFIC2 has been associated with increased risk for hepatocellular carcinoma (HCC).
A recent study (E Gonzales, et al. Hepatology 2015; 62: 558-66) indicates that newer therapies targeting the specific mutation may be effective.
In this study, treatment with oral 4-phenylbutyrate (4-PB) in four patients improved pruritus, serum bile acid concentrations, and liver function tests. 4-PB is considered a chaperone drug and may partially correct mistrafficking.
The associated editorial (pg 349-50) notes that 4-PB has an unpleasant taste and requires ingestion of a large number of pills. In addition, patients with complete loss of BSEP, 4-PB will not be effective. Finally, even in patients with a clinical response, it is unclear if this will lower the risk of HCC.
A second study (S Varma et al. Hepatology 2015; 62: 198-206) retrospectively studied 22 children with PFIC2. “Children with late-onset presentation, lower ALT, and intracellular BSEP expression are likely to respond, at least transiently, to nontransplant treatment.” Nontransplant treatment in this cohort included ursodeoxycholic acid in 19 (10 mg/kg thrice daily) and partial biliary diversion in 3. Higher ALT values were considered to be >165 IU/L. Another point in this study: response to treatment can be slow and take many months.
My take: These studies provide useful information about which patients with PFIC2 respond medically and introduce a new therapy, 4-PB.
Related blog posts:

Perhaps next week the story will be: man with venomous snakes says they make great pets?

One clarification -I do not think that Dr. Narkewicz is calling Dr. Balistreri a panda:






Related blog posts:
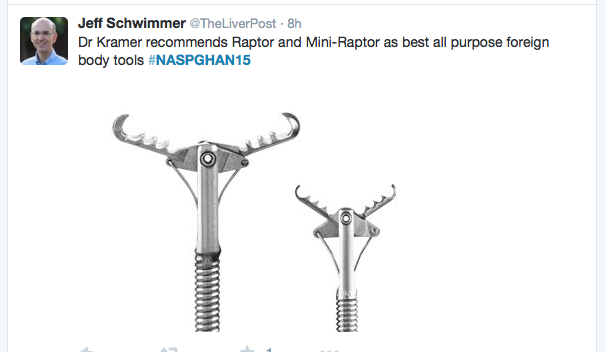
Since I am not at this year’s national meeting, I have followed some of the information on social media. Here are some of the best tweets:





Related blog posts:

