Using a post hoc analysis of 2 large Crohn’s disease (CD) trial with 420 biologic-naive adult patients, the authors found the following Key Findings:
At week 6, a comparable number of patients achieved clinical remission with infliximab compared with patients treated with ustekinumab (44.9% vs 37.9%; adjusted odds ratio [aOR], 1.22)
At week 6 the clinical response rates were not significantly different (58.4% infliximab vs 54.9% ustekinumab; aOR, 1.25)
At week 6, 42.3% infliximab vs 34.7% ustekinumab had fecal calprotectin level less than 250 mcg/L in those with increased values at baseline
My take: A true head-to-head trial, rather than a post-hoc analysis, would more definitively determine relative efficacy and relative time to response. This study indicates that both agents have similar efficacy by week 6.
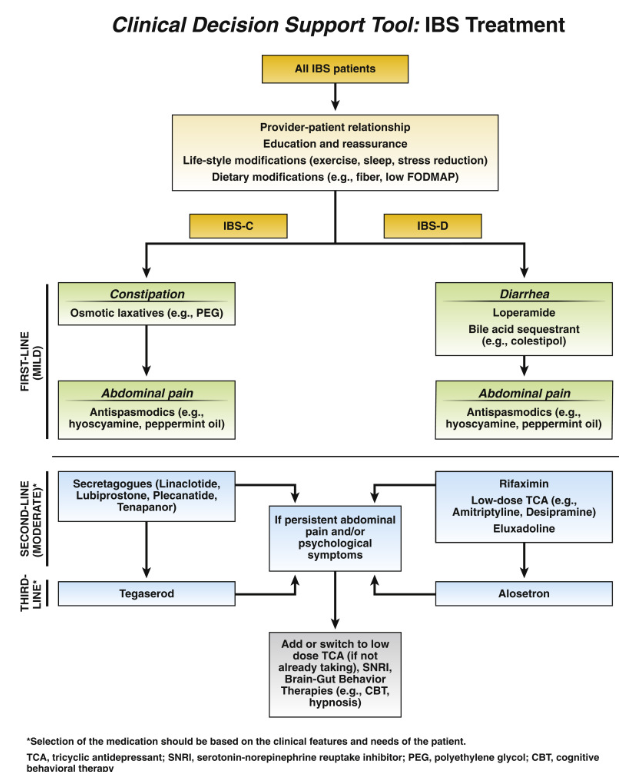
The associated 1-page summary (“Spotlight: IBS Treatment“) on pg 153 reviews society guidelines on testing in IBS. This includes for IBS-D celiac serology, calprotectin/lactoferrin, CRP, possilby Giardia antigen (if in endemic area) and possibly bile acid diarrhea testing. Not recommended include food allergy/sensitivity testing, colonoscopy if <45 years and lactulose or glucose hydrogen breath testing. This 1-page summary details therapeutic dosing and costs. Monthly costs of selected medications according to this report:
The main component of this double-blind, randomized (no placebo) study allocated 512 patients with ulcerative colitis to a higher induction regimen (HIR) of adalimumab and 340 patients to a standard induction regimen (SIR). A maintenance phase continued with 374 main patients who were clinical responders at week 8 (n=757 who completed induction). The study results are presented in a confusing manner, in part because of a subgroup from Japan as well as a great deal of data from both the induction phase and the maintenance phase.
Key findings:
In the main study, 13.3% vs 10.9% of patients receiving the higher induction regimen (HIR) vs standard induction regimen (SIR) achieved clinical remission (full Mayo score ≤2 with no subscore >1) at week 8 (induction primary end point; P = .265)
Among week-8 responders, 39.5% vs 29.0% receiving 40 mg ew vs 40 mg eow achieved clinical remission at week 52 (maintenance primary end point; P = .069).
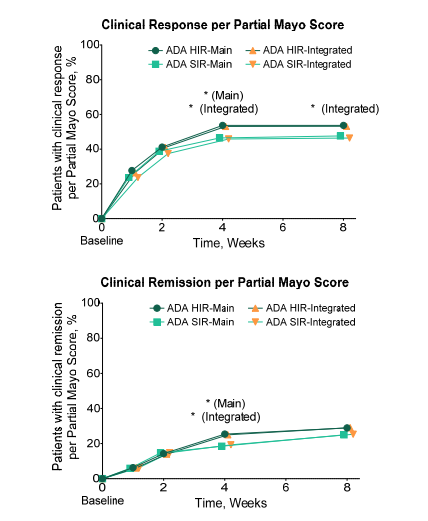
Figure S2 below shows that approximately 50% of patients treated with adalimumab had a clinical response at week 8
My takes on this study:
Fairly low response to adalimumab: the clinical remission rate for adalimumab is low at week 8 (10-13%) and the 8-week response rate is less than 50%
Higher doses during induction were not helpful & did not result in significantly better responses at week 8
Therapeutic drug monitoring was not beneficial in this study
Higher doses during maintenance were associated with improved responses: patients receiving weekly adalimumab during maintenance treatment had improved week 52 remission. The editorial (pages 1831-1832) note that this effect was demonstrated in those with “elevated C-reactive protein, low albumin, extensive UC or long disease burden”
Figure S2: Clinical response was defined as Partial Mayo Score decrease from baseline ≥ 2 and ≥ 30% plus ≥ 1-point decrease from baseline in rectal bleeding subscore or absolute rectal bleeding subscore of 0 or 1. Clinical remission was defined as Partial Mayo Score ≤ 2 with no subscore > 1. ADA, adalimumab; HIR, higher induction regimen; SD, standard deviation; SIR, standard induction regimen
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
This retrospective study reviewed 395 CD patients received ustekinumab therapy (79 CD-ASD (autoimmune skin disease), 316 CD-none). ASD included atopic dermatitis, eczema, psoriasis/psoriaform dermatitis and alopecia. The skin disease group also included those with cutaneous manifestations of Crohn’s disease: erythema nodosum, pyoderma gangrenosum, pyostomatitis vegetans, Sweet’s syndrome, granulomatous vasculitis, and leukocytoclastic vasculitis. 55 of the 79 with CD-ASD had psoriatic disease, 20 had eczema, 11 had erythema nodosum, 8 had pyoderma gangrenosum.
Key findings:
Ustekinumab had greater efficacy in CD-ASD when evaluated by fecal calprotectin (P = .0337) and CRP (P = .078). For calprotectin, the values decreased by 61% after at least 5 months of therapy (394 to 164) in the CD-ASD group compared to 11% in the group without skin disease (365 to 265)
The CD-ASD group also showed better outcomes in Likert scores of endoscopy (P = .016), histopathology (P = .074), and imaging (P = .094).
My take: Ustekinumab appears to be particularly effective in patients with concurrent skin disease.
Preoperative TNFi exposure was not associated with postoperative infectious complications in a large prospective multicenter cohort. Any infection (18.1% vs 20.2%, P = .469) and SSI (12.0% vs 12.6%, P = .889) rates were similar in patients currently exposed to TNFis and those unexposed.
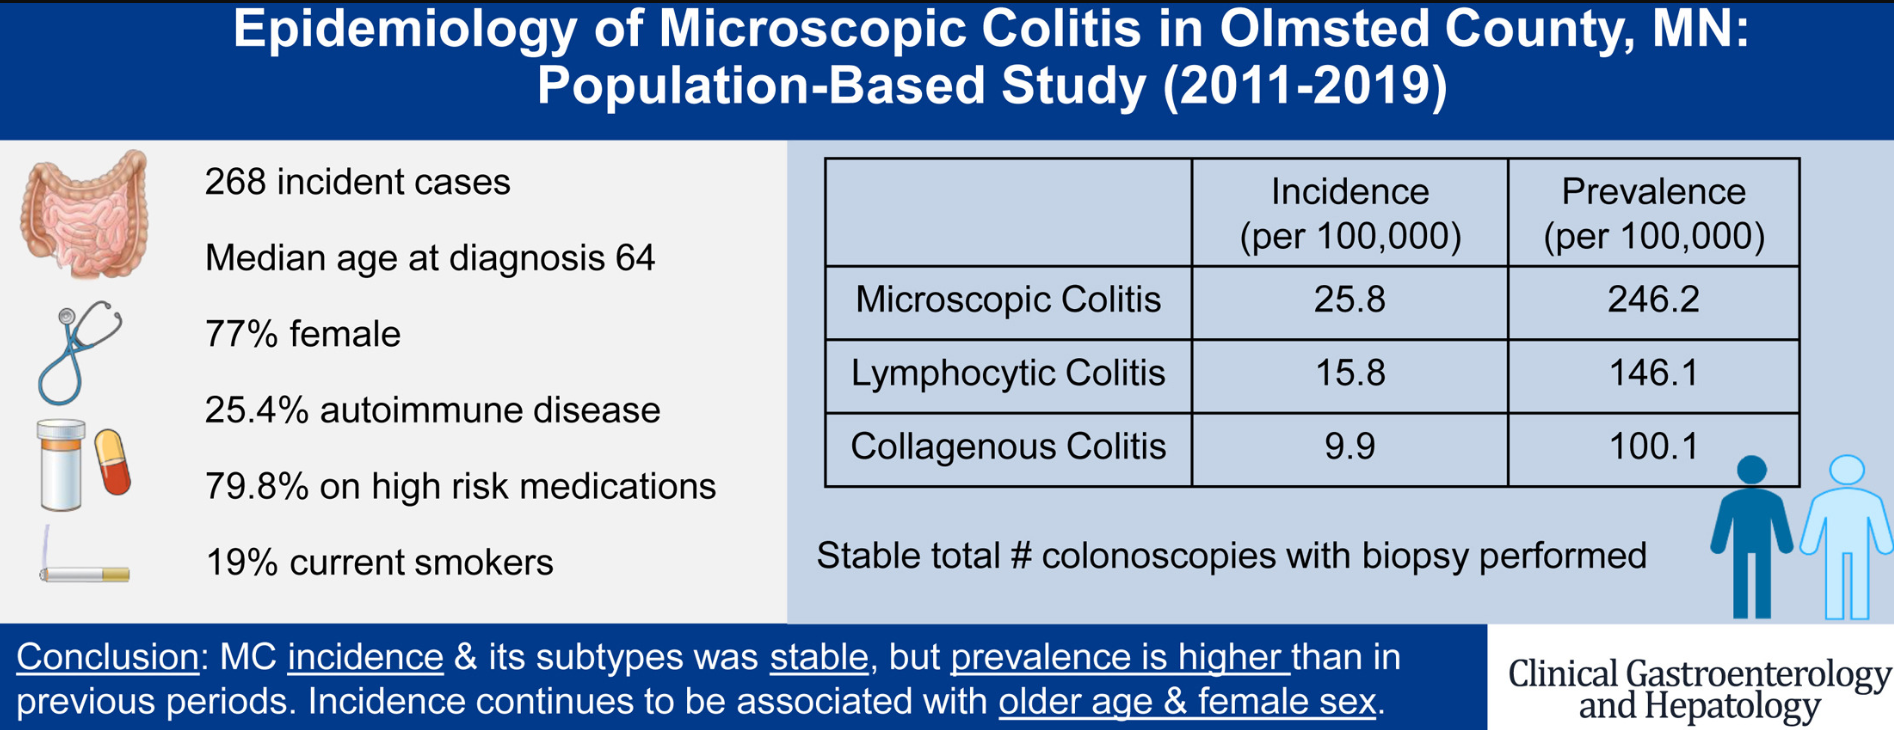
“The overall incidence of MC in Olmsted County, MN, increased from 1985 to 2001, stabilized between 2002 and 2010, and continues to show a plateau between 2011 and 2019.”
Medications associated with a risk of microscopic colitis (MC) include statins, SSRIs, PPIs, aspirin, other NSAIDs, and histamine H2-receptor antagonists within 3 months of diagnosis. “A recent US multicenter cohort study found an inverse association with PPIs and histamine H2-receptor antagonists when compared with controls with chronic diarrhea; only NSAID use was associated with MC. 31 It is plausible these medications do not cause MC, but instead aggravate diarrhea and bring the diagnosis to clinical attention.”
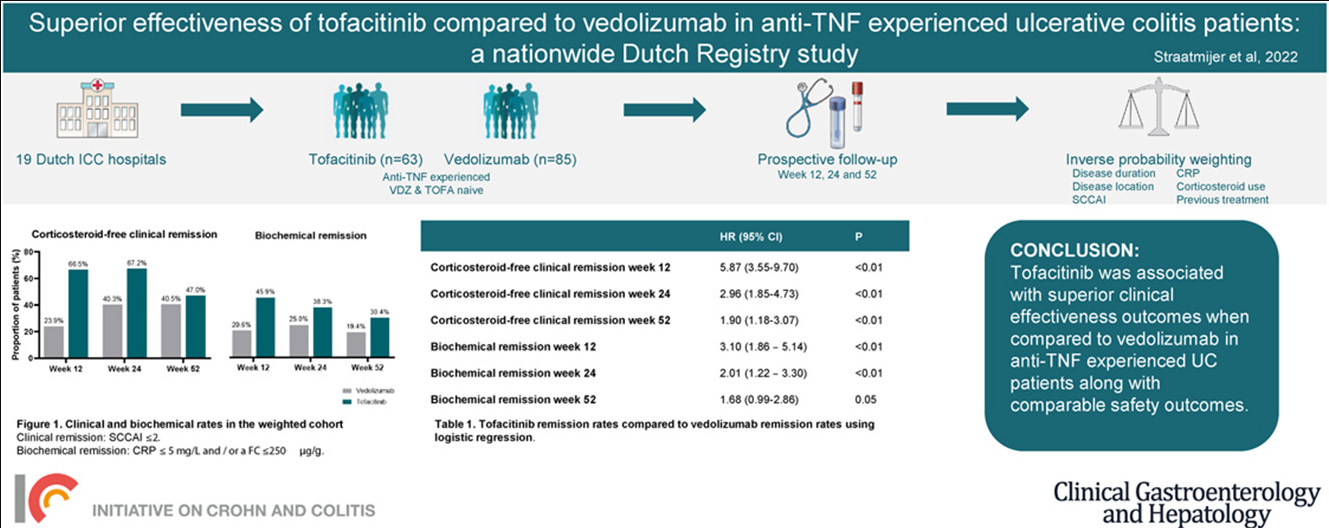
Methods: Ulcerative colitis patients who failed anti-TNF treatment and initiated vedolizumab (n=83) or tofacitinib (n=65) treatment, were identified in the ICC Registry in the Netherlands.
Key findings:
Tofacitinib treated patients were more likely to achieve corticosteroid-free clinical remission and biochemical remission at week 12, 24 and 52 compared to vedolizumab treated patients (OR: 6.33, OR: 3.02, and OR 1.86 and OR: 3.27, OR: 1.87, and OR:1.81, respectively).
There was no difference in infection rate or severe adverse events.
My take: The response rates with tofacitinib were significantly better than vedolizumab at all time points; however, by 52 weeks, the differences were less pronounced. Nevertheless, the safety profile of vedolizumab is much more favorable than tofacitinib and this is a very important consideration.
– Third approved indication for SKYRIZI (risankizumab-rzaa) is supported by safety and efficacy data from two induction and one maintenance clinical trials evaluating SKYRIZI in moderately to severely active Crohn’s disease, ADVANCE, MOTIVATE and FORTIFY1-4
– As early as week 4 in the induction studies, clinical response and clinical remission were achieved by significantly more subjects treated with SKYRIZI versus placebo, as were co-primary endpoints of endoscopic response and clinical remission at week 12 and week 521-4
About SKYRIZI® (risankizumab-rzaa) SKYRIZI is an interleukin-23 (IL-23) inhibitor that selectively blocks IL-23 by binding to its p19 subunit.9,10 IL-23, a cytokine involved in inflammatory processes, is thought to be linked to a number of chronic immune-mediated diseases, including Crohn’s disease.10 The approved dose to treat adults with moderately to severely active Crohn’s disease is 600 mg administered by intravenous infusion over at least one hour at week 0, week 4, and week 8, followed by 360 mg administered by subcutaneous injection at week 12, and every 8 weeks thereafter.4 SKYRIZI is also approved in the U.S. to treat moderate to severe plaque psoriasis in adults who are candidates for systemic therapy or phototherapy, as well as to treat active psoriatic arthritis in adults, and the recommended dosage is 150 mg administered by subcutaneous injection at week 0, week 4, and every 12 weeks thereafter.4 Phase 3 trials of SKYRIZI in psoriasis, Crohn’s disease, ulcerative colitis and psoriatic arthritis are ongoing
Many times, treatment decisions are like on “Let’s Make a Deal.” That is, should I stick with what I’ve got or should I try for something better & sometimes wind up with a goat. In this referenced article, patients were under maintenance therapy with adalimumab (ADA) monotherapy (40 mg every 14 days) and had experienced a secondary loss of response (LOR) despite trough levels > 4.9 μg/mL. In this nonrandomized prospective study, patients were either swapped to vedolizumab (VDZ) or optimized on adalimumab (ADA) treatment.
Key findings:
At 24 months, 11 out of 70 patients (16%) in the swap group discontinued treatment compared with 36 out of 61 (59%) patients in the optimization group (P < 0.001)
In the optimization group, treatment discontinuation was positively associated with baseline fecal calprotectin >500 μg/g (HR, 3.5)
In patients selected for optimization, 56% (34/61) remained on ADA at 1 year and 41% (25/61) at 2 years
In their discussion, the authors state “current guidelines recommend switching to another class of biologics in case of LOR to ADA with therapeutic drug levels.” However, the authors note that their therapeutic level cut-off of >4.9 mcg/mL is lower than the latest recommendations. In addition, in their conclusion, they note that due to limited biologic options, “ADA optimization strategy might be considered” in a subgroup.
My take: Despite better results in the patients that swapped to VDZ in this study, I think it is important to assure adequate drug levels before choosing a new drug class. For ADA, expert recommendations have suggested a level of 8-12 as therapeutic and to avoid discontinuation if ADA level is less than 10. In this study, more than 40% remained on ADA two years after LOR in those with dosing optimization.
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.