Protecting Animals in Medical Schools

An interesting development has been the abandonment of live animals to train surgical skills (DJ Simkin et al. NEJM 2017; 376: 713-15).  Last year, the last two medical schools, who used live (anesthetized) animals, dropped this part of a core curriculum for training in surgery.

While the use of animals for medical education had “been used in medical education for millennia, the practice has now been abolished from the standard curriculum of every U.S. medical school.”  While some alternative methods for training, like more sophisticated simulation, had been developed, clearly the change was driven by groups like “The Physicians Committee for Responsible Medicine” (8% of whose members are physicians).

While the goal of humane care for animals is laudable, it is worthwhile to contemplate that now “the brunt of the risks associated with learning tends to be borne by patients who are uninsured, undocumented, members of minority groups or otherwise marginalized.”

My take (borrowed from authors): “The underlying moral question –On whose bodies will clinical medicine first be practiced?–continues to require close attention.”

screenshot-157

Do antibiotics contribute to obesity? Not in recent study

There have been studies suggesting that antibiotics at a young age promote obesity and other studies that have NOT found an association. A recent study (JAMA Pediatr. 2017;171(2):150-156. doi:10.1001/jamapediatrics.2016.3349) could not find an effect of chronic prophylactic antibiotics.

Link: Weight Gain and Obesity in Infants and Young Children Exposed to Prolonged Antibiotic Prophylaxis

From Abstract:

Design, Setting, and Participants  Secondary analysis of data from the Randomized Intervention for Children With Vesicoureteral Reflux Study, a 2-year randomized clinical trial that enrolled participants from 2007 to 2011. All 607 children who were randomized to receive antibiotic (n = 302) or placebo (n = 305) were included. Children with urinary tract anomalies, premature birth, or major comorbidities were excluded from participation.

Interventions  Trimethoprim-sulfamethoxazole or placebo taken orally, once daily, for 2 years.

Results  Participants had a median age of 12 months (range, 2-71 months) and 558 of 607 (91.9%) were female. Anthropometric data were complete at the 24-month visit for 428 children (214 in the trimethoprim-sulfamethoxazole group and 214 in the placebo group). Weight gain in the trimethoprim-sulfamethoxazole group and the placebo group was similar (mean [SD] change in weight-for-age z score: +0.14 [0.83] and +0.18 [0.85], respectively; difference, −0.04 [95% CI, −0.19 to 0.12]; P = .65). There was no significant difference in weight gain at 6, 12, or 18 months or in the prevalence of overweight or obesity at 24 months (24.8% vs 25.7%; P = .82). Subgroup analyses showed no significant interaction between weight gain effect and age, sex, history of breastfeeding, prior antibiotic use, adherence to study medication, or development of urinary tract infection during the study.

My take: Whether antibiotics could contribute to obesity is not entirely clear –even the possibility could encourage better stewardship of antimicrobials.

Related blog posts:

screenshot-143

screenshot-144

“Addressing Physician Burnout”

In the last few years, there have been increasing reports of physician burnout.  A recent report (JAMA. Published online February 9, 2017. doi:10.1001/jama.2017.0076) (thanks to Ben Gold for this reference) provides a concise review of the reasons and potential mitigating strategies.

Full Text Link: “Addressing Physician Burnout”

An excerpt:

Physicians also have to navigate a rapidly expanding medical knowledge base, more onerous maintenance of certification requirements, increased clerical burden associated with the introduction of electronic health records (EHRs) and patient portals, new regulatory requirements (meaningful use, e-prescribing, medication reconciliation), and an unprecedented level of scrutiny (quality metrics, patient satisfaction scores, measures of cost).

These challenges have taken a toll on US physicians. Burnout is a syndrome of exhaustion, cynicism, and decreased effectiveness at work…The first large, national study of burnout among US physicians across all specialties did not occur until 2011. That study of 7288 participating physicians documented that approximately 45% reported at least 1 symptom of burnout and that burnout was more common among physicians than US workers in other fields…

The first large, national study of burnout among US physicians across all specialties did not occur until 2011. That study of 7288 participating physicians documented that approximately 45% reported at least 1 symptom of burnout and that burnout was more common among physicians than US workers in other fields…

Physician burnout has been linked to self-reported errors, turnover, and higher mortality ratios in hospitalized patients…

The current burden of documentation related to the clinical encounter required to meet billing requirements, quality reporting, and separate justification for each test ordered individually is unsustainable…

Individual physicians must also do their part…Individual physicians have a professional responsibility to take care of themselves. Adequate sleep, exercise, and attending to personal medical needs should be considered a minimal standard for self-care. Physicians must also proactively identify personal and professional priorities and take deliberate steps to integrate their personal and professional lives.

Related blog posts:

birthoutcomesaftertnt

Heartfelt Apologies

“Resentment is like drinking poison and then hoping it will kill your enemies.”

–Nelson Mandela

A recent NY Times article explains how the right type of apology can be good medicine: The Right Way to Say ‘I’m Sorry’

An excerpt:

I admit to a lifetime of challenges when it comes to apologizing, especially when I thought I was right or misunderstood or that the offended party was being overly sensitive. But I recently discovered that the need for an apology is less about me than the person who, for whatever reason, is offended by something I said or did or failed to do, regardless of my intentions…

Nor should a request for forgiveness be part of an apology. The offended party may accept a sincere apology but still be unready to forgive the transgression. Forgiveness, should it come, may depend on a demonstration going forward that the offense will not be repeated…

Offering an apology is an admission of guilt that admittedly leaves people vulnerable. There’s no guarantee as to how it will be received. It is the prerogative of the injured party to reject an apology, even when sincerely offered…

“Apology has the power to repair harm, mend relationships, soothe wounds and heal broken hearts. An apology actually affects the bodily functions of the person receiving it — blood pressure decreases, heart rate slows and breathing becomes steadier.”

Related blog posts:

screenshot-98

Deadly Market Forces in Narcotics

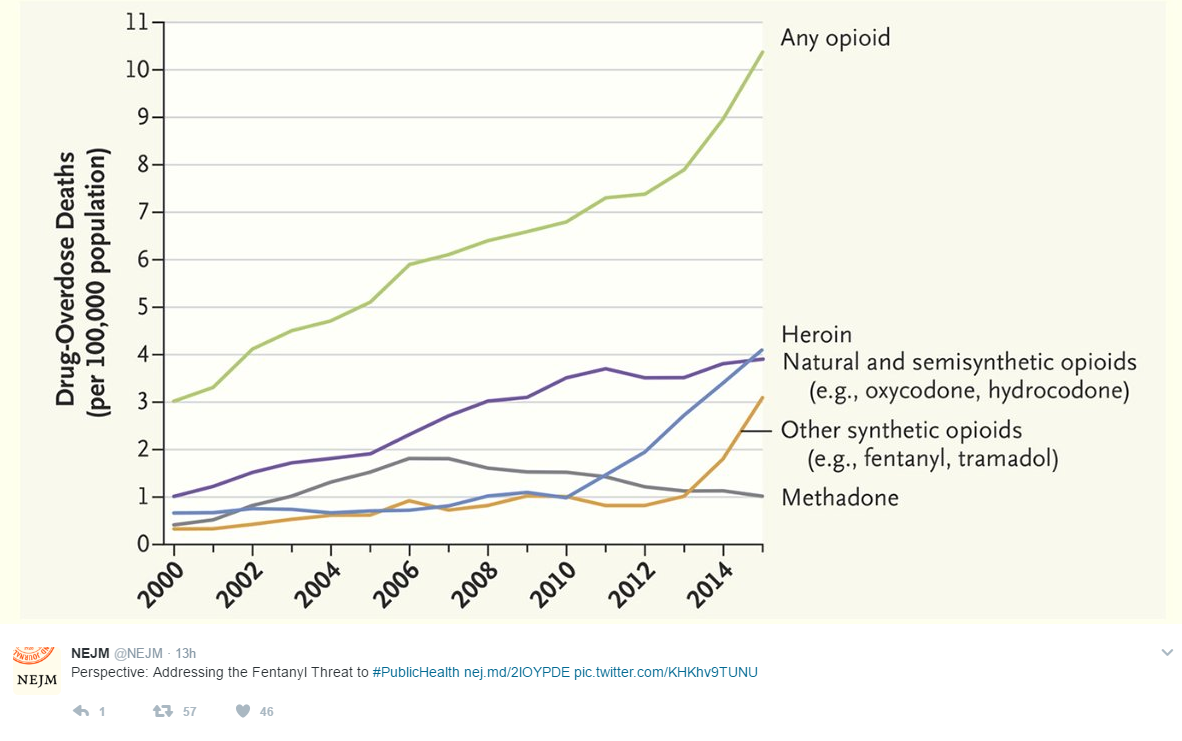
Lately, I’ve been shocked and dismayed by the frequent headlines about the number of overdoses and deaths due to narcotics throughout our country.  A timely article (RG Frank, HA Pollack. NEJM 2017; 376: 605-7) addresses one aspect of this threat to public health that I was not aware of previously.

  • Fentanyl, which is a powerful synthetic opioid, is much cheaper to produce than heroin.  In addition, fentanyl can result in death much more quickly as well.
  • Presumably due to its lower cost, suppliers ‘cut’ heroin with the drug.  As a consequence, fentanyl is increasingly responsible for opioid deaths. The authors estimate that from 2012 to 2014, the number of deaths due to fentanyl doubled to 5544 and that “41% of the roughly 7100 heroin-related deaths during this period involved fentanyl.”
  • Fentanyl has been found in multiple counterfeit illicit drugs.  For example, in a recent analysis from Canada, “89% of seized counterfeit OxyContin tablets” had fentanyl present.
  • Naloxone can reverse fentanyl overdoses but needs to be given more quickly and sometimes multiple doses are needed.

My take: The presence of fentanyl in illicit drugs means that even experimenting once could be fatal.

screenshot-135

Related blog posts:


Narcotic Slippery Slope

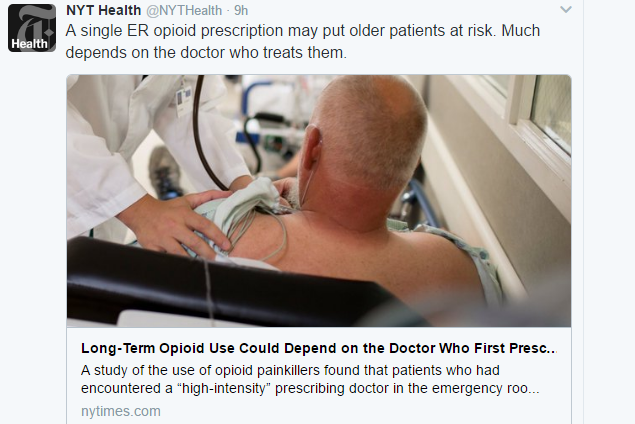
In a recent article (NEJM 2017; 376: 663-73), ML Barnett show that opioid-prescribing patterns of emergency physicians may increase the risk of long-term use. By focusing on variation of prescribing practices among physicians at the same hospitals and with a sample size of ~380,000 patients, the authors provide convincing data that starting opioids even for an intended brief period can have lasting consequences. This study focused on medicare beneficiaries (average age ~68 yrs) who received narcotics from either higher-frequency or lower-frequency physician prescribers.

In their discussion, the authors state “if our results represent a causal relationship, for every 49 patients prescribed a new opioid in the emergency department who might not otherwise use opioids, 1 will become a long-term user.”

My  take: Starting a narcotic may be the first step in a long treacherous road.

Related blog posts:

screenshot-134

Atul Gawande: “Tell Me Where It Hurts”

In a recent New Yorker article (Jan 23, 2017, pgs 36-45,LINK:  “Tell Me Where It Hurts” –thanks to Stan Cohen for this article), Atul Gawande provides a compelling narrative on the ‘heroism’ of incremental care.

He starts his narrative with the story of Bill Haynes who had had severe migraines for four decades, but eventually improved under the care of Elizabeth Loder (John Graham Headache Center).  Over the course of four years, her ‘systematic incrementalism had done what nothing else had.’

Dr. Gawande explains that chronic illness is commonplace but “we have been poorly prepared to deal with it.  Much of what ails us requires a more patient kind of skill.  I was drawn to medicine by the aura of heroism–by the chance to charge in and solve a dangerous problem.”

Despite the appeal of dramatic medical moments, bigger impacts are noted with more subtle care. “States with higher ratios of primary care physicians have lower rates of general mortality, infant mortality, and mortality from specific conditions such as heart disease and stroke.”  One of the ways mortality is reduced is getting seen sooner for medical problems. Having a relationship with a physician “has a powerful effect on your willingness to seek care for severe symptoms.”

A parallel narrative in this piece regards the Silver Bridge tragedy in 1967.  This bridge which connected Gallipolis, Ohio and Point Pleasant, West Virginia, over the Ohio River, keeled over and resulted in 46 deaths and dozens more who were injured. This tragedy sparked attention towards infrastructure and trying to address problems before a critical collapse occurs.  “We will all turn out to have –like the Silver Bridge and the growing crack in its critical steel link–a lurking heart condition or a tumor or a depression or some rare disease that needs to be managed. This is a problem for our healthcare system.  It doesn’t put great value on care that takes time to pay off.”

Other points:

  • Incremental medicine is “at odds with our system’s allocation of rewards…the lowest-paid specialties: pediatrics, endocrinology, family medicine, HIV/infectious disease, allergy/immunology, internal medicine, psychiatry, and rheumatology.”
  • “More than a quarter of Americans and Europeans who die before the age of seventy-five would not have died so soon if they’d received appropriate medical care for their conditions.”
  • “Data indicate that twenty-seven per cent of adults under sixty-five…[have] conditions that make them uninsurable without protections” form the Affordable Care Act.

My take: Fixing an aging bridge may not be as exciting as building a new one –unless you are the aging bridge or depend on that bridge.

screenshot-147


Making Doctors Yelp?

Yelp definition: “a short sharp cry, especially of pain or alarm.”

Apparently the online review site, Yelp, is now reviewing health care provider performance.  A recent commentary (V Lee. NEJM 2017; 376: 197-9) provides some insight into this development.

  • Yelp has had “102 million customer reviews to date, 6% of them in the health care arena;” thus, Yelp “dwarfs longer-standing commercial physician review sites such as Healthgrades and Vitals.”
  • “Physicians do not always respond positively to the sudden exposure of sometimes negative reviews.”  These reviews could contribute to drops in physician morale.
  • However, these reviews are here to stay and help patients make more informed choices, provide performance feedback, and may improve quality in health care.
  • The biggest problems with these reviews include the fact that anyone (even a disgruntled neighbor, ex-girlfriend) can post a review and due to clarity of the reviews.  In addition, patient reviews should not be viewed without other metrics like quality and cost.

My take (borrowed from author): “the question is not whether there should be public disclosure of information on patient satisfaction, outcomes, and costs — it’s how and by whom it should be done.”

Related blog posts:

screenshot-69

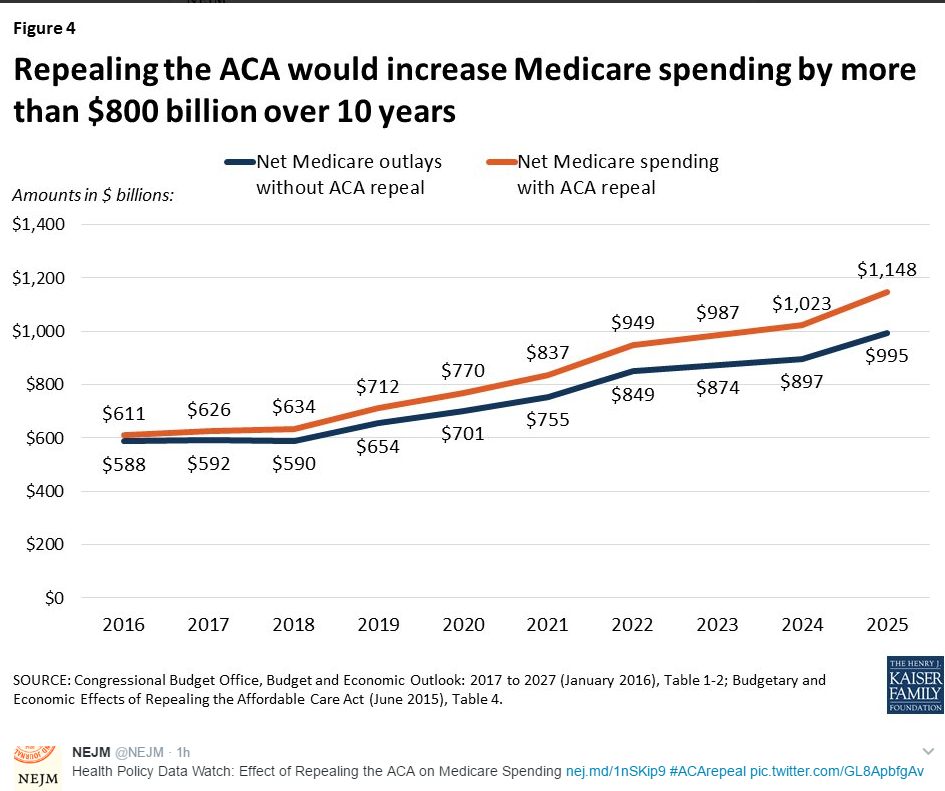
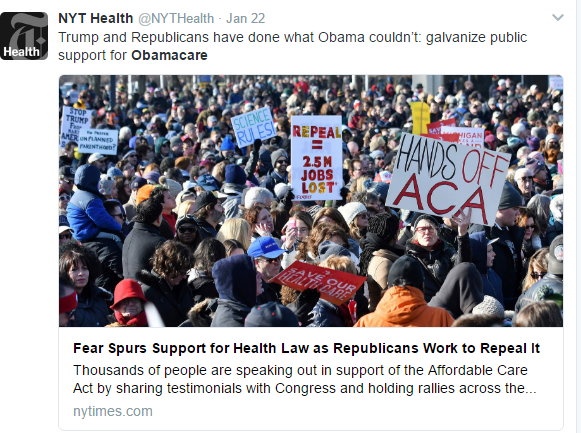
Repealing the Affordable Care Act Without a Replacement

Barack Obama, in a perspective article (BH Obama. NEJM January 6, 2017; DOI: 10.1056/NEJMp1616577), explains the hazards of “repeal and delay.”

Here’s a link to the full text: Repealing the ACA without a Replacement — The Risks to American Health Care

Here’s an excerpt:

Put simply, all our gains are at stake if Congress takes up repealing the health law without an alternative that covers more Americans, improves quality, and makes health care more affordable. That move takes away the opportunity to build on what works and fix what does not. It adds uncertainty to lives of patients, the work of their doctors, and the hospitals and health systems that care for them. And it jeopardizes the improvements in health care that millions of Americans now enjoy.

Congress can take a responsible, bipartisan approach to improving the health care system. This was how we overhauled Medicare’s flawed physician payment system less than 2 years ago. I will applaud legislation that improves Americans’ care, but Republicans should identify improvements and explain their plan from the start — they owe the American people nothing less.

Health care reform isn’t about a nameless, faceless “system.” It’s about the millions of lives at stake — from the cancer survivor who can now take a new job without fear of losing his insurance, to the young person who can stay on her parents’ insurance after college, to the countless Americans who now live healthier lives thanks to the law’s protections. Policymakers should therefore abide by the physician’s oath: “first, do no harm.”

A related article from the LA Times indicates that Aetna misled the public with regard to its reasons for pulling out of several exchanges: Link:U.S. judge finds that Aetna misled the public about its reasons for quitting Obamacare

An excerpt:

The judge’s conclusions about Aetna’s real reasons for pulling out of Obamacare — as opposed to the rationalization the company made in public — are crucial for the debate over the fate of the Affordable Care Act. That’s because the company’s withdrawal has been exploited by Republicans to justify repealing the act. Just last week, House Speaker Paul Ryan (R-Wisc.) cited Aetna’s action on the “Charlie Rose” show, saying that it proved how shaky the exchanges were. ..

Bates found that this rationalization was largely untrue. In fact, he noted, Aetna pulled out of some states and counties that were actually profitable to make a point in its lawsuit defense — and then misled the public about its motivations.

Related blog posts:

screenshot-77

How Rudeness Affects Performance in Medicine (and probably elsewhere)

From A Riskin et al. Pediatrics Jan 2017 (Thanks to Seth Marcus for pointing out this study), Link: Rudeness and Medical Team Performance

Abstract

OBJECTIVES: Rudeness is routinely experienced by medical teams. We sought to explore the impact of rudeness on medical teams’ performance and test interventions that might mitigate its negative consequences.

METHODS: Thirty-nine NICU teams participated in a training workshop including simulations of acute care of term and preterm newborns. In each workshop, 2 teams were randomly assigned to either an exposure to rudeness (in which the comments of the patient’s mother included rude statements completely unrelated to the teams’ performance) or control (neutral comments) condition, and 2 additional teams were assigned to rudeness with either a preventative (cognitive bias modification [CBM]) or therapeutic (narrative) intervention. Simulation sessions were evaluated by 2 independent judges, blind to team exposure, who used structured questionnaires to assess team performance.

RESULTS: Rudeness had adverse consequences not only on diagnostic and intervention parameters (mean therapeutic score 3.81 ± 0.36 vs 4.31 ± 0.35 in controls, P < .01), but also on team processes (such as information and workload sharing, helping and communication) central to patient care (mean teamwork score 4.04 ± 0.34 vs 4.43 ± 0.37, P < .05). CBM mitigated most of these adverse effects of rudeness, but the postexposure narrative intervention had no significant effect.

CONCLUSIONS: Rudeness has robust, deleterious effects on the performance of medical teams. Moreover, exposure to rudeness debilitated the very collaborative mechanisms recognized as essential for patient care and safety. Interventions focusing on teaching medical professionals to implicitly avoid cognitive distraction such as CBM may offer a means to mitigate the adverse consequences of behaviors that, unfortunately, cannot be prevented.

This same group had a related study in 2015:The Impact of Rudeness on Medical Team Performance: A Randomized Trial

My take:The saying “you catch more flies with honey than you do with vinegar” is probably accurate.

Costa Maya, Mexico

Costa Maya, Mexico