Iron Metabolism Improves after Anti-TNF Therapy for Crohn’s Disease

A previous study has shown that low vitamin D levels improved with anti-TNF therapy for Crohn’s disease in the absence of supplemental vitamin D.  Similarly, a recent study (MA Atkinson, MB Leonare, R Herskovitz, RN Baldassano, MR Denburg. JPGN 2018; 66: 90-4) showed improvement in iron metabolism with anti-TNF therapy.

In 40 children and adolescents with Crohn’s disease, the authors measured serum hepcidin-25 and hemoglobin at baseline and then 10 weeks after anti-TNF therapy.

Key findings:

  • Median hepcidin concentrations decreased (27.9–>23.2 ng/mL) and mean hemoglobin increased (10.6–>10.9).
  • Disease activity and markers of inflammation also decreased.

My take: This study shows that improvement in inflammation is associated with meaningful improvement in anemia.  However, most patients will need additional treatment for anemia, particularly as anemia may be related to blood loss in addition to anemia of chronic disease/inflammation.

Related blog posts:


Opioid Epidemic Affecting HCV Infection in Adolescents (as well as adults)

SA Barritt et al. J Pediatr 2018; 192: 159-64. Increasing Prevalence of Hepatitis C among Hospitalized Children Is Associated with an Increase in Substance Abuse

Background:  “After a sustained decline in new HCV cases, in recent years there has been a significant increase in HCV incidence in adults in many areas, primarily associated with the use and abuse of intravenous heroin and prescription opioids.” This study examines this trend in adolescents.

From abstract:

Study design

We examined hospitalizations in children using the Kids’ Inpatient Database, a part of the Healthcare Cost and Utilization Project. We identified cases using the International Classification of Diseases, 9th edition, codes for HCV infection during 2006, 2009, and 2012. Nonparametric tests for trend were used to calculate trend statistics.

Results

From 2006 to 2012 nationally, the number of hospitalizations of children with HCV increased 37% (2.69 to 3.69 per 10 000 admissions; P < .001). The mean age of children hospitalized was 17.6 years (95% CI, 17.4-17.8). HCV cases among those 19-20 years of age represented 68% of the total HCV diagnoses, with a 54% increase over the years sampled (P < .001 for trend). The burden of HCV in children was highest in whites, those in the lowest income quartile, and in the Northeast and Southern regions of the US (all P < .0001). The prevalence of substance use among children with HCV increased from 25% in 2006 to 41% in 2012 (P < .001).

Conclusion

The increases of HCV in hospitalized children are largely in teenagers, highly associated with substance abuse, and concentrated in Northeast and Southern states. These results strongly suggest that public health efforts to prevent and treat HCV will also need to include adolescents.

My take: Despite the availability of highly effective therapy for hepatitis C, the opioid epidemic undermines any prospect for eliminating hepatitis C infections.

Related blog posts:

Probiotics for Prevention of Nosocomial Diarrhea in Children

A recent review (I Hojsak et al. JPGN 2018; 66: 3-9) examined published trials regarding the role of probiotics in the prevention of nosocomial diarrhea. The review was conducted by a working group on behalf of ESPGHAN.

Key findings:

  • “Recommendation: If probiotics for preventing nosocomial diarrhea in children are considered, the WG [working group] recommends using L rhamnosus GG (at least 10 to the 9th CFU/day, for the duration of hospital stay).
  • Quality of evidence: Moderate
  • Strength of recommendation: Strong
  • Number needed to treat (in order for beneficial effect in one): 12 patients

The authors do not recommend L reuteri DSM17938 due to lack of efficacy; other probiotics did not receive a recommendation either due to lack of data or lack of efficacy.

It is possible that there have been unpublished negative probiotic studies which would alter the calculation of a beneficial effect.

My take: While the working group recommends L rhamnosus GG if probiotics are used to prevent diarrhea, the absolute benefit is low.

Related blog posts:

Bright Angel Trail, Grand Canyon

Probiotics for Colic –2018 Update

There is some debate about whether colic is truly a GI disorder.  A recent commentary (V Sung, MD Cabana. J Pediatr 2017; 191: 6-8) provides some insight.

Key points:

  • “‘Colic’ is a term coined by the ancient Greeks…derived from ‘kolikos,’ meaning crampy pain, sharing its root with the the word colon.”
  • “Since 1994, there have been at least a dozen case-control studies that have indicated differences in the gut microbiota between infants with and without colic.”
  • Studies have had conflicting results with whether calprotectin levels are increased in infants with colic compared with controls.
  • Among probiotics, L reuteri DSM17938 “is the best studied strain.” Despite several studies suggesting efficacy, “the largest and only double-blind randomized trial that included both breastfed and formula-fed infants with colic (n=167) in Australia was ineffective.
  • The commentary reviews a recent study (Fatheree NY et al. J Pediatr 2017; 191: 170-8) “although very small in comparison, adds to this literature, being the second double-blind randomized, placebo-controlled trial of L reuteri DSM17938 shown to be ineffective in breastfed infants with colic.” Sample size =20. “It is the first to document increased fecal calprotectin levels that decrease with reduced crying” …though this “may be reflections of normal levels in healthy young infants, which change over time.”  In addition, this study did not find evidence of systemic inflammation.  The authors speculate that the frequent use of antireflux medications could dampen the effects of probiotics.

My take: We still do not know whether efforts at changing an infant’s microbiome improve clinical outcomes in colic.

Related blog posts:

Near Bright Angel Trail, Grand Canyon

Crohn’s Disease Diagnosis Identified After Colectomy in Presumed Ulcerative Colitis

A recent retrospective single-center study (I Jones et al. JPGN 2018; 66: 69-72) identified a high rate of inflammatory bowel disease (IBD) reclassification.  From 2003-2014, 570 children were diagnosed with IBD, including 190 with ulcerative colitis.  29 of these patients underwent colectomy.  Among this select group, 24% (7/29) were subsequently reclassified as having Crohn’s disease, sometimes several years later.  Only two of the seven reclassified patients were younger than 10 years of age at the time of colectomy.

My take: This rate of Crohn’s disease following colectomy is higher than in previous reports (generally 5-10%).  The larger point is that the diagnosis of ulcerative colitis is more uncertain in the pediatric population, particularly in those in the first decade of life.

Related blog posts:

Near Bright Angel Trail, Grand Canyon

Pancreatitis -Feedings and Genetics

KM Ellery et al. J Pediatr 2017; 191: 164-9.  This prospective pediatric study examined 30 patients with mild acute pancreatitis in a “patient-directed nutrition” (PDN) pathway using a low fat diet and compared to a historical control of 92 patients in a “treatment team-directed nutrition” (TTDN) pathway. In the PDN group, patients were allowed a low-fat oral diet (<5 g fat per entrée, <1 g fat per snack, and only 1 entrée or snack at a time) at the time of admission.

Key findings:

  • PDN group had median length of stay of 48.5 hours compared with 93 hours for the TTDN group
  • PDN group was NPO for median of 14 hours compared to 34 hours for TTDN group
  • No patients in the PDN group had complications within 30 days of discharge

Y Xiao et al. J Pediatr 2017; 191: 158-63.  Among 55 pediatric patients with chronic pancreatitis and 14 with acute recurrent pancreatitis, there were 45 and 10 patients respectively who harbored 1 or more mutations in pancreatitis-associated genetic disorders: PRSS1, SPINK1, CFTR, CASR, CTSB, CTRC, KRT8

My take: These two studies indicate that oral feeding in mild acute pancreatitis leads to shorter hospital stays and that pediatric patients with chronic pancreatitis and acute recurrent pancreatitis frequently have predisposing genetic mutations.

Related blog posts:

Near Bright Angel Trail, Grand Canyon


The Half Empty Glass: Rumination Outcomes

Briefly noted:

A Alioto, C DiLorenzo. JPGN 2018; 66: 21-25.  In this study based on patient follow-up questionnaires, among 47 adolescents with rumination syndome who received inpatient treatment, Key findings:

  • ~20% reported complete cessation of rumination for at least 6 months; though, even in this group, 73% had at least some recurrent symptoms.
  • 40% reported a reduction in rumination intensity following discharge and ~80% reported having at least one day with no rumination.
  • Triggers for recurrence of rumination symptoms included stress (51.4%), illness (27%), menstruation (10.8%), and certain foods (18.9%).
  • Treatment of rumination syndrome helped eliminate the need for supplemental tube feedings in the “vast majority of patients.”

One important limitation of this study is the patient selection; this group of inpatients with rumination syndrome at a specialized center likely had more severe rumination syndrome.

My take: Like many GI conditions, the expectation for rumination syndrome should probably be improvement/management rather than resolution/cure.

Signage on Bright Angel Trail, Grand Canyon

Budesonide Looks Better for Eosinophilic Esophagitis

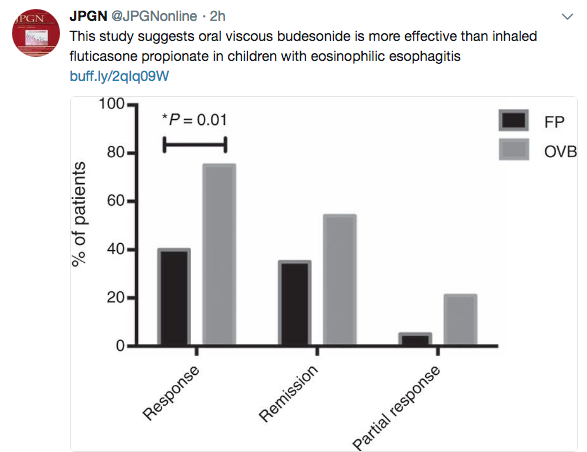
A recent retrospective study (JM Fable et al. JPGN 2018; 66: 26-32) found that patients with eosinophilic esophagitis (EoE) who were treated with oral viscous budesonide (OVB) had more favorable outcomes than those treated with fluticasone propionate (FP).  This single center study included 68 pediatric patients (mean age 10.6 years) with 20 receiving FP and 48 OVB.

Dosing in study:

  • FP 110 mcg/actuation 2 puffs twice a day if 1-10 years, and 220 mcg/actuation 2 puffs twice a day if >10 years
  • OVB: 0.5 mg twice a day if 1-10 years, and 1 mg twice a day if >10 years
  • The authors noted that Duocal (which contains cornstarch and coconut oil) was a suitable alternative to Splenda.  They note that Neocate Nutra is effective too (limited by cost/coverage) as is pasteurized honey and maple syrup.

Key findings:

  • Histologic response (<15 eos/hpf) was noted in 75% (36/48) of OVB group and 40% (8/20) of FP group
  • Mean post-treatment peak eos/hpf was 12 ± 16 in OVB group and 20 ± 29 in the FP group (P=0.002)
  • Histologic remission (<5 eos/hpf) was noted in 54% OVB group and 35% FP group
  • In OVB-treated patients, those without asthma were more likely to achieve a histologic response (P=0.031)

Since this is a retrospective study, there are several potential limitations, including possible selection bias.  In addition, higher doses of topical agents have been shown to have higher response rates.

My take: Budesonide is probably better than fluticasone for EoE and its high first-pass metabolism indicates that it is probably safer as well.

Related blog posts:

High-resolution Esophageal Manometry for Rumination Syndrome.

Briefly noted: While in most cases, rumination syndrome does not require manometry for diagnosis, in cases of uncertainty, it can be helpful.  A recent retrospective study (FR Grunder, A Aspirot, C Faure. JPGN 2017; 65: 627-32) highlights the utility of high-resolution esophageal manometry (HREM) in the diagnosis of rumination syndrome using 15 patients with rumination and 15 control patients.

Background: The sensitivity of HREM can be lower in a clinical setting as many “subjects with rumination are often able to tolerate the test meal during the manometry study with minimal or no symptoms.”

HREM also helps determine whether rumination is primary, secondary or if there is supragastric belch-associated rumination.

  • Primary rumination indicates that abdominal pressure increases before the retrograde flow
  • Secondary rumination indicates that abdominal pressure increases after a reflux event
  • Supragastric belch-associated rumination indicates an association of air inflow (detected with combined impedance) in the esophagus immediately followed by a rumination event

Key finding from this study:

  • HREM had a sensitivity and specificity of 80% and 100% respectively to confirm the diagnosis of rumination.  “the association of a clinical rumination episode with a rise in gastric pressure >30 mmHg seems to be specific for the diagnosis of rumination syndrome in children.”

My take: Manometry is usually not needed for the diagnosis of rumination syndrome but does help explain the pathophysiology.

Bright Angel Trail, Grand Canyon


Increasing Cost/Use of Biologic Therapies for Inflammatory Bowel Disease

As noted in a previous blog post (Changes in the Use of IBD Biologic Therapy), there has been an increased use of biologic therapy early in the course of patient’s with inflammatory bowel disease (IBD). Another retrospective study (H Yu et al AP&T 2018; 47: 364-70 -thanks to Ben Gold for this reference) examines the market share and costs of biologic therapy for IBD using the Truven Marketscan Commercial Claims and Encounters database (2007-2015).  This database consists of out-patient and in-patient pharmaceutical claims of approximately 40-50 million privately insured patients each year from patients from all 50 states (U.S.).

Key findings:

  • Among 415,405 patients with IBD (188,842 with Crohn’s, 195,183 with ulcerative colitis, 31,380 with indeterminate IBD), the proportion using biologics increased over the 9-year period (2007-2015); overall, the market share increase was from 7.1% (2007) to 20.5% (2015).
  • There were 28,797 pediatric patients with IBD (17,296 with Crohn’s, 9368 with ulcerative colitis, and 2133 with indeterminate colitis). The overall market share in pediatric patients was the highest, increasing from 19.1% to 45.9%.
  • For all patients with Crohn’s disease (CD) the proportion receiving biologic therapy increased from 21.8% to 43.8%.  For patients with ulcerative colitis (UC), the proportion increased from 5.1% to 16.2%.
  • Per-member per-year (PMPY) costs increased. “The average biologic-taking patient accounted for $25,275 PMPY in 2007 and $36,051 PMPY in 2015.”  This was similar in the pediatric population, going from $23,616 PMPY in 2007 to $41,109 PMPY in 2015.
  • The share of costs of medicines: the costs of biologics as a share of the total increased from 72.9% in 2007 to 85.7% in 2015. 95% of the pharmacy costs in children with IBD are attributed to biologics.

My take: This trend of increasing use of biologics and their associated costs is going to continue due to their effectiveness. While there are direct costs related to these medications, the net cost is unclear as they can prevent hospitalizations and surgeries. In addition, by helping to spare corticosteroids and increasing response rates, biologic therapies improve quality of life, minimize opportunity loss, and optimize long-term health outcomes.

Bright Angel Trail, Grand Canyon