Pictures from today’s CCFA Fundraiser -we had about 25 GI Care for Kids staff/family attending this year; this is not including Skittles (the dog)



Related blog post: Healthcare Hero: Dr. Benjamin Gold

Pictures from today’s CCFA Fundraiser -we had about 25 GI Care for Kids staff/family attending this year; this is not including Skittles (the dog)
Related blog post: Healthcare Hero: Dr. Benjamin Gold
Two recent commentaries discuss some of the problems for aspiring physicians:
In the first article, the authors detail the burden associated with the common-place high-volume applications to medical schools.
“The cost is approximately $150 per school for application fees, plus $345 for taking the MCAT and having the score distributed through AMCAS. These fees are waived for qualifying low-income applicants (as primarily defined by household income below 400% of the national poverty level) who apply to the AAMC Fee Assistance Program and provide the required financial documentation.2 After submitting the primary application, applicants face a flood of secondary applications, some requiring up to eight additional essays. Even when the essay prompts are similar to those from other schools, the instructions often specify different lengths. One premedical student posted on social media the findings of his review of 54 medical schools’ secondary applications: he identified 222 different prompts, which he provided to help applicants get a jumpstart on their frenzied essay writing.3..
Between 2013 and 2023, … the total number of applications and the average number of applications per student increased dramatically — by 40% (from 690,281 to 966,947) and 28% (from 14.4 to 18.4), respectively. Despite the disproportionate escalation in applications submitted, the success rate (matriculants divided by applicants) remained flat (range, 36 to 44%).”
The authors recommend limiting applications to 10 to 12 medical school applications per applicant. This would benefit students as well as faculty burdens.
“The secondary-application process also needs to be reined in. Medical schools could adopt standardized secondary essays… Under this model, a student applying to 10 schools would complete a maximum of 13 secondary essays — 3 standardized and 1 customized essay per school — rather than the current norm of 60 to 80 essays (e.g., 20 secondary applications with 3 to 4 distinct essays each).”
My take: In Charlie and the Chocolate Factory, there are only five golden tickets. If everyone buys twice as many Wonka bars, it is a lot more expensive and perhaps more time-consuming. For medical school applicants, applying to 20 or more programs does not help if almost everyone is doing this. It does disadvantage the minority who do not have the financial means or available time to complete this arduous task.
In the second commentary, the article details the problems with shadowing experiences.
“Medical school admission in the United States remains intensely competitive. In 2024, according to the Association of American Medical Colleges (AAMC), prospective students submitted an average of 18 applications apiece…Many medical school admissions committees consider shadowing a physician to be an essential clinical experience for professional identity formation, so nearly all applicants now do some shadowing: 95% of respondents to the 2024 AAMC Matriculating Student Questionnaire (MSQ) said they’d spent time observing a physician at work.1 …
Premedical students are spending more time shadowing — sometimes hundreds to thousands of hours, which often necessitate taking a “gap year” between college and medical school at a financial cost…Three quarters of medical school applicants report taking time off before medical school, 50% taking 1 to 2 years and 25% taking 3 or more years...
These additional years delay entry into the workforce and result in higher levels of debt than moving more quickly toward potential earnings as a physician; one lost year of a physician’s salary (an average of $265,000) would result in an estimated net loss of $2 million by retirement if the money were invested at a 7% return…
Although medical schools consider clinical experiences other than shadowing, a review of our own data suggests that applicants who have shadowed physicians for more than 50 hours are more likely than their peers to be admitted — and more likely to come from higher-income families.“
The authors point out that unstructured observation is of unclear benefit. A course from Stanford, that far fewer hours (11-20 hrs) was sufficient for more than 90% of students “to decide whether medicine was the right career for them….The current emphasis on shadowing not only contributes to a longer and more expensive medical education pathway but also discourages nontraditional applicants and pursuit of genuine interests in other areas that make for well-rounded physicians.”
My take: The pathway to medical school has become more time-consuming and expensive. At the same time, it is doubtful that lengthy shadowing experiences or extensive numbers of applications are benefiting aspiring students.
Related blog post:

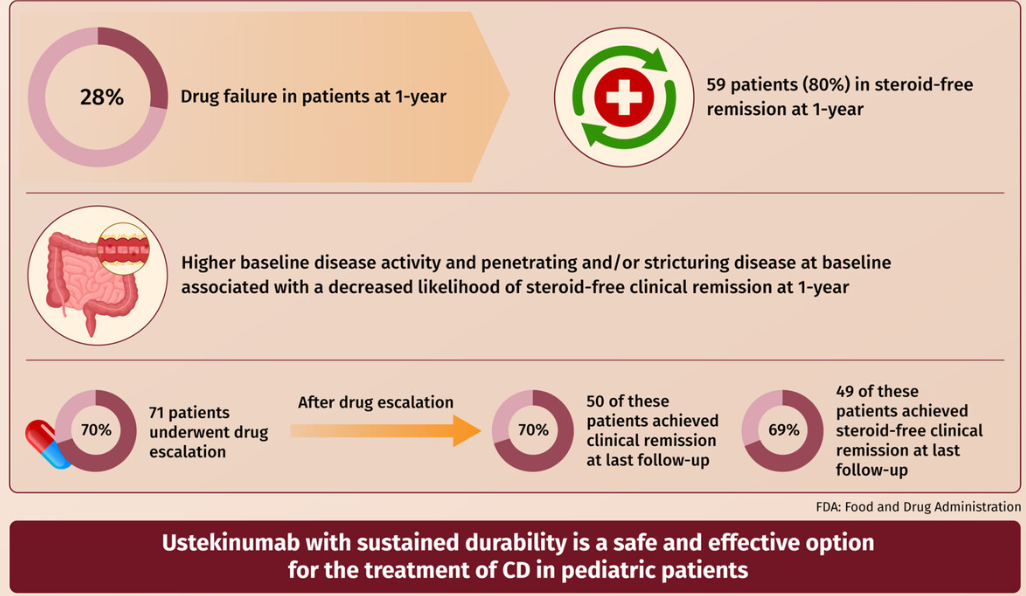
EB Mitchell et al. JPGN 2025;80:653–663. Ustekinumab is safe and effective in pediatric patients with Crohn’s disease
This was a retrospective longitudinal cohort study of 101 children with CD treated with ustekinumab from two large centers between 2015 and 2020. The median follow-up time on ustekinumab was 16.6 months.
Key findings:
My take: More pediatric data showing efficacy for ustekinumab is important. My sense, though, is that newer IL-23 specific agents are going to eclipse ustekinumab in pediatrics as they are doing in adults.
Related blog posts:
Z Gaibee et al. N Engl J Med 2025;392:1297-1309. The Genetic Architecture of Congenital Diarrhea and Enteropathy
Background:”Congenital diarrhea and enteropathies (CODEs) are a group of rare disorders that primarily affect the function of intestinal epithelial cells, leading to infantile-onset diarrhea and poor growth. Molecular defects in CODEs can be classified into six categories: epithelial trafficking and polarity, immune-cell-regulation, nutrient and electrolyte transport, enteroendocrine-cell development, nutrient metabolism, and other. CODEs are associated with substantial morbidity and mortality. Patients often receive lifelong fluid and nutritional management. Genetic causes include pathogenic variants in MYO5B (microvillus inclusion disease), EPCAM (tufting enteropathy), NEUROG3 (enteric anendocrinosis), DGAT1 (protein-losing enteropathy), and SLC9A3 (congenital sodium diarrhea). Treatment options are currently limited. However, an understanding of some of the genetic causes of CODEs has led to targeted therapies such as dietary treatments and the development of preclinical pharmacologic treatments.”
Methods: In this case series with 129 infants, the authors analyzed the exomes or genomes of infants with suspected monogenic congenital diarrheal disorders. Using cell and zebrafish models, we tested the effects of variants in newly implicated genes.
Key findings:

My take: Exome sequencing is an important part of the evaluation of infants with CODEs
Related blog posts:
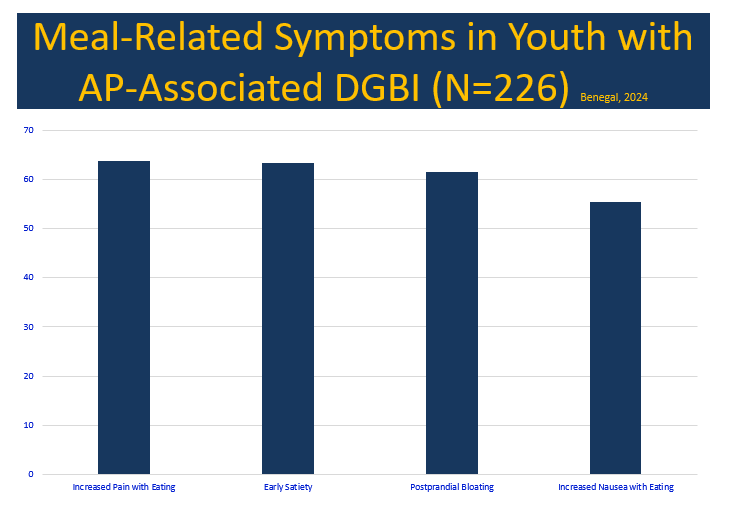
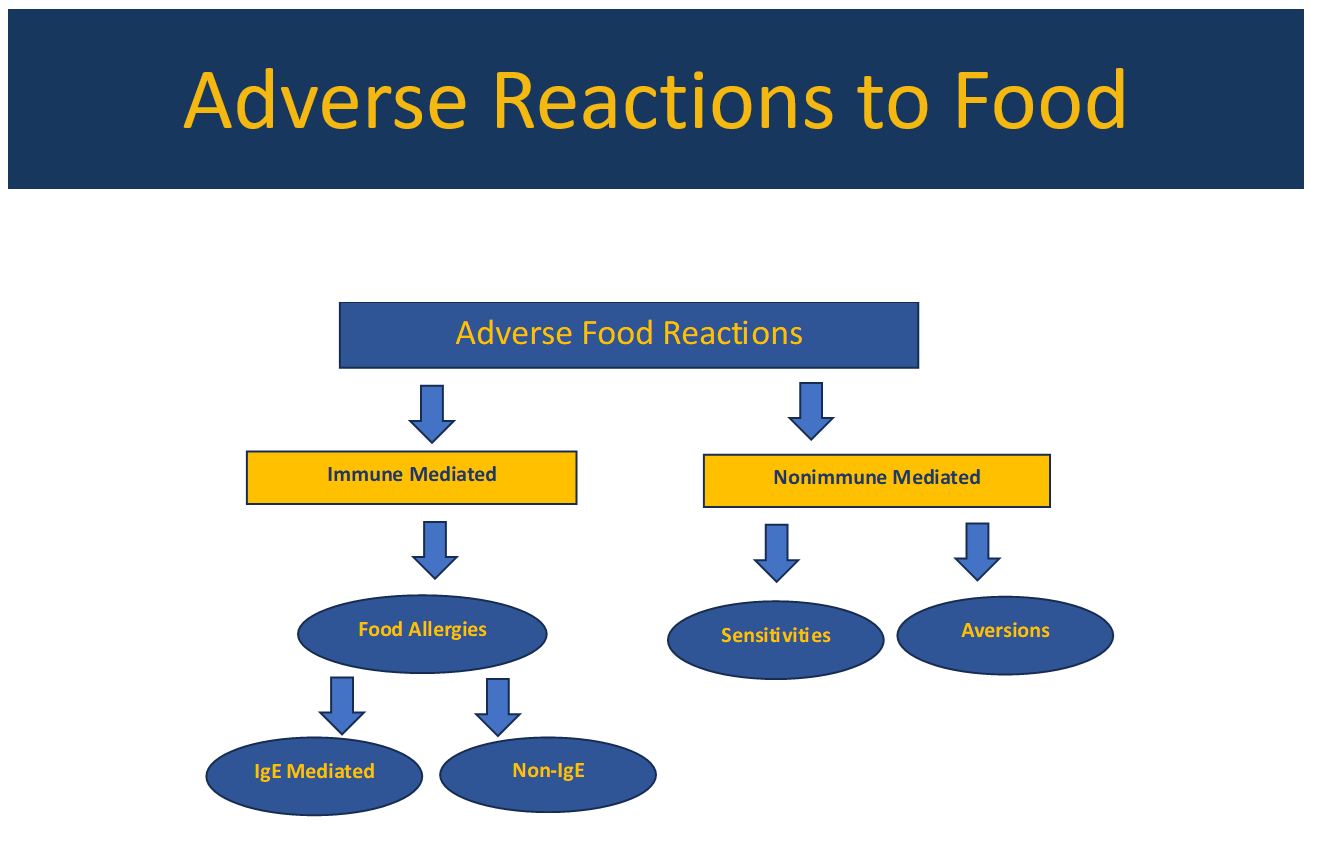
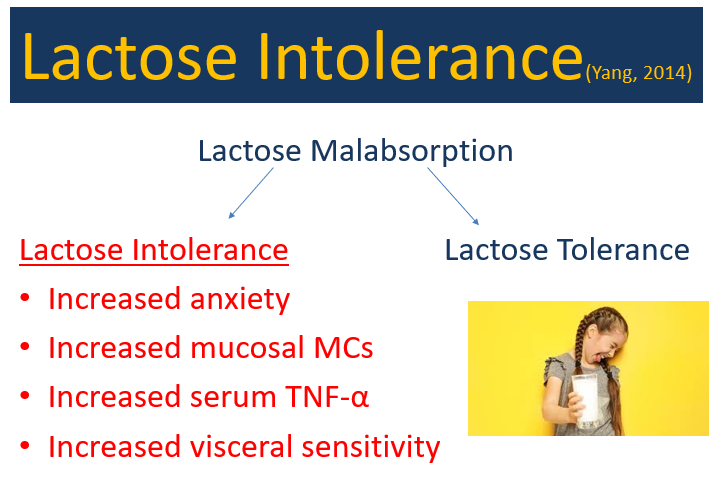
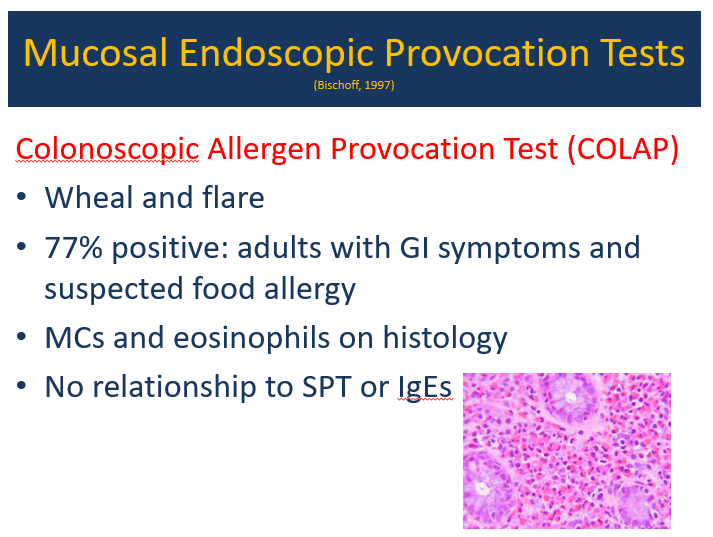
Dr. Craig Friesen gave our group an excellent update on food allergy and disorders of brain-gut interaction (DGBIs). His main disclosure was that he is not an allergist. My notes below may contain errors in transcription and in omission. Along with my notes, I have included many of his slides.

Key points:









Related blog posts:
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
Smith-Bindman R, Chu PW, Azman Firdaus H, et al. JAMA Intern Med. Published online April 14, 2025. doi:10.1001/jamainternmed.2025.0505. Open Access! Projected Lifetime Cancer Risks From Current Computed Tomography Imaging
Methods: Lifetime radiation-induced cancer incidence and 90% uncertainty limits (UL) were estimated by age, sex, and CT category using National Cancer Institute software based on the National Research Council’s Biological Effects of Ionizing Radiation VII (BEIR VII) models and projected to the US population using scaled examination counts.
Key findings:
Discussion: “The projected number of radiation-induced cancers in this analysis is 3 to 4 times higher than the earlier assessment of CT exposure for several reasons”
My take (borrowed from authors): “Even very small cancer risks will lead to a significant number of future cancers given the tremendous volume of CT use in the United States…CT could be responsible for approximately 5% of cancers diagnosed each year. This would place CT on par with other significant risk factors, such as alcohol consumption (5.4%) and excess body weight (7.6%)”
Related blog posts:

S Machado et al. NEJM 2025;392:1310-1319. Association between Wealth and Mortality in the United States and Europe
Methods: This was a longitudinal, retrospective cohort study with 73,838 adults (mean [±SD] age, 65±9.8 years), a total of 13,802 (18.7%) died during a median follow-up of 10 years.
Key findings:

In their discussion, the authors note that health care access should not be a factor for wealthy Americans. However, “systematic factors may influence longevity across social strata, such as diet; environment; behavioral, cultural, and social attitudes; and opportunities for social mobility.2,28,32,33 The poorest are most vulnerable to these systemic factors, but these factors are broad and probably affect the entirety of society.”
My take: This study indicates that mortality in the United States is higher than in Europe, even at higher wealth levels.
Commentary on this article from NBC News (4/2/25): Not even wealth is saving Americans from dying at rates seen among some of the poorest Europeans
“Fifty years ago, life expectancy in the U.S. and wealthy European countries was relatively similar. That began to change around 1980. As European life expectancy steadily increased, the U.S. struggled to keep pace — and its life expectancy even began declining in 2014…The wealthiest group in northern and western Europe had mortality rates about 35% lower than the wealthiest group in the U.S.”
Related blog posts:
This NEJM review describes recent developments in vaccines for C difficile.
Background: “Because the pathogenesis of C. difficile infection depends on the production of the potent toxins TcdA (toxin A) and TcdB (toxin B) by vegetative C. difficile cells, there is hope that the development of vaccines targeting these virulence factors…will be successful in limiting the development of C. difficile infection in patients receiving antibiotic treatment.2“
An excerpt:
“A trial of a vaccine composed of formalin-inactivated TcdA and TcdB purified from a highly toxigenic C. difficile strain was stopped at the first planned interim analysis on the basis of clinical futility,3 and the development of this vaccine was terminated. More recently, results were published from the Clostridium difficile Vaccine Efficacy Trial (CLOVER), a phase 3, randomized trial of a genetically detoxified C. difficile vaccine composed of recombinant TcdA and TcdB (containing targeted amino-acid substitutions to limit toxic activity) that were further detoxified by chemical means.4 Although the trial did not show a benefit with respect to the primary end point of preventing a first episode of C. difficile infection, vaccinated patients in whom C. difficile infection developed had a shorter duration of symptoms and were less likely to receive medical attention for their infection than patients who had received placebo.
In this setting, a new type of C. difficile vaccine candidate, described by Alameh, Semon, and colleagues,5 is of interest. These investigators developed a multivalent nucleoside-modified messenger RNA (mRNA) vaccine (see Key Concepts) delivered in lipid nanoparticles (LNPs)…The mRNA–LNP vaccine elicited higher antibody levels to all three vaccine targets than the recombinant vaccine with alum adjuvant. Furthermore, the mRNA–LNP vaccine provided complete protection against challenge with an intraperitoneally administered high dose of purified TcdA or TcdB: all the vaccinated mice survived, whereas all the unvaccinated mice were moribund within 2 days. The recombinant–alum vaccines protected only 20% of the vaccinated animals…
However, protection was not associated with the prevention of colonization: all the vaccinated animals shed high numbers of culturable C. difficile and had histopathological damage to intestinal tissue that was equivalent to that seen in unvaccinated animals according to analyses performed 2 days after infection. This finding suggests that protection was due to blocking of the systemic effects of the C. difficile toxins. However, additional data indicated that inclusion of the PPEP-1 antigen in the multivalent vaccine resulted in more rapid clearance of luminal toxin levels.”
My take: An effective vaccine would be a welcome advance and perhaps limit the shitty treatments we have had to date.
Related blog posts:

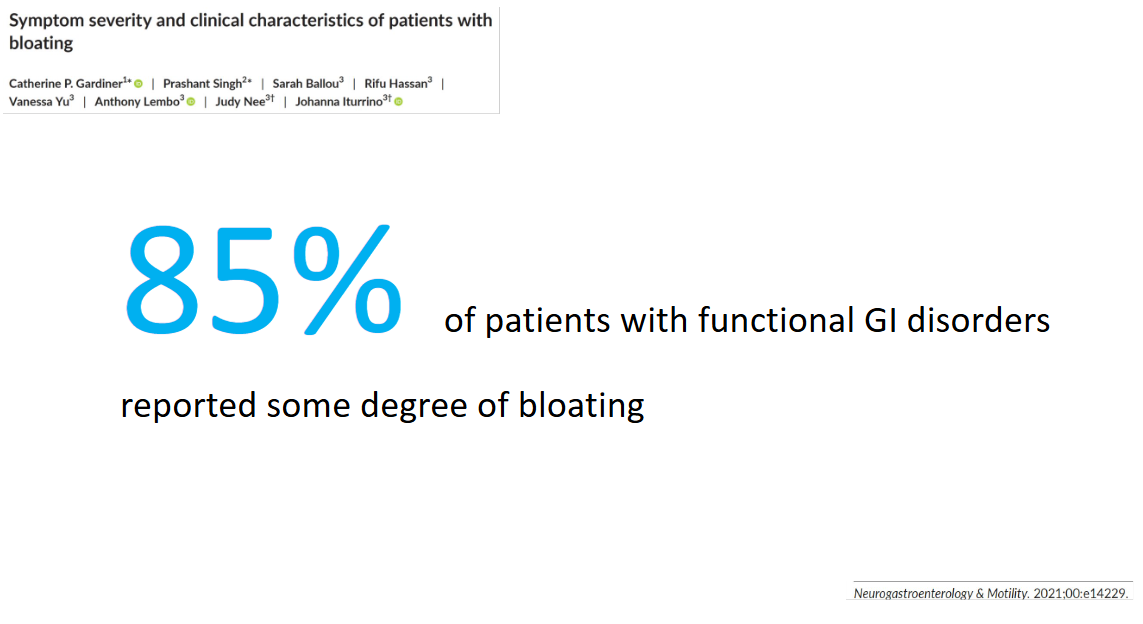
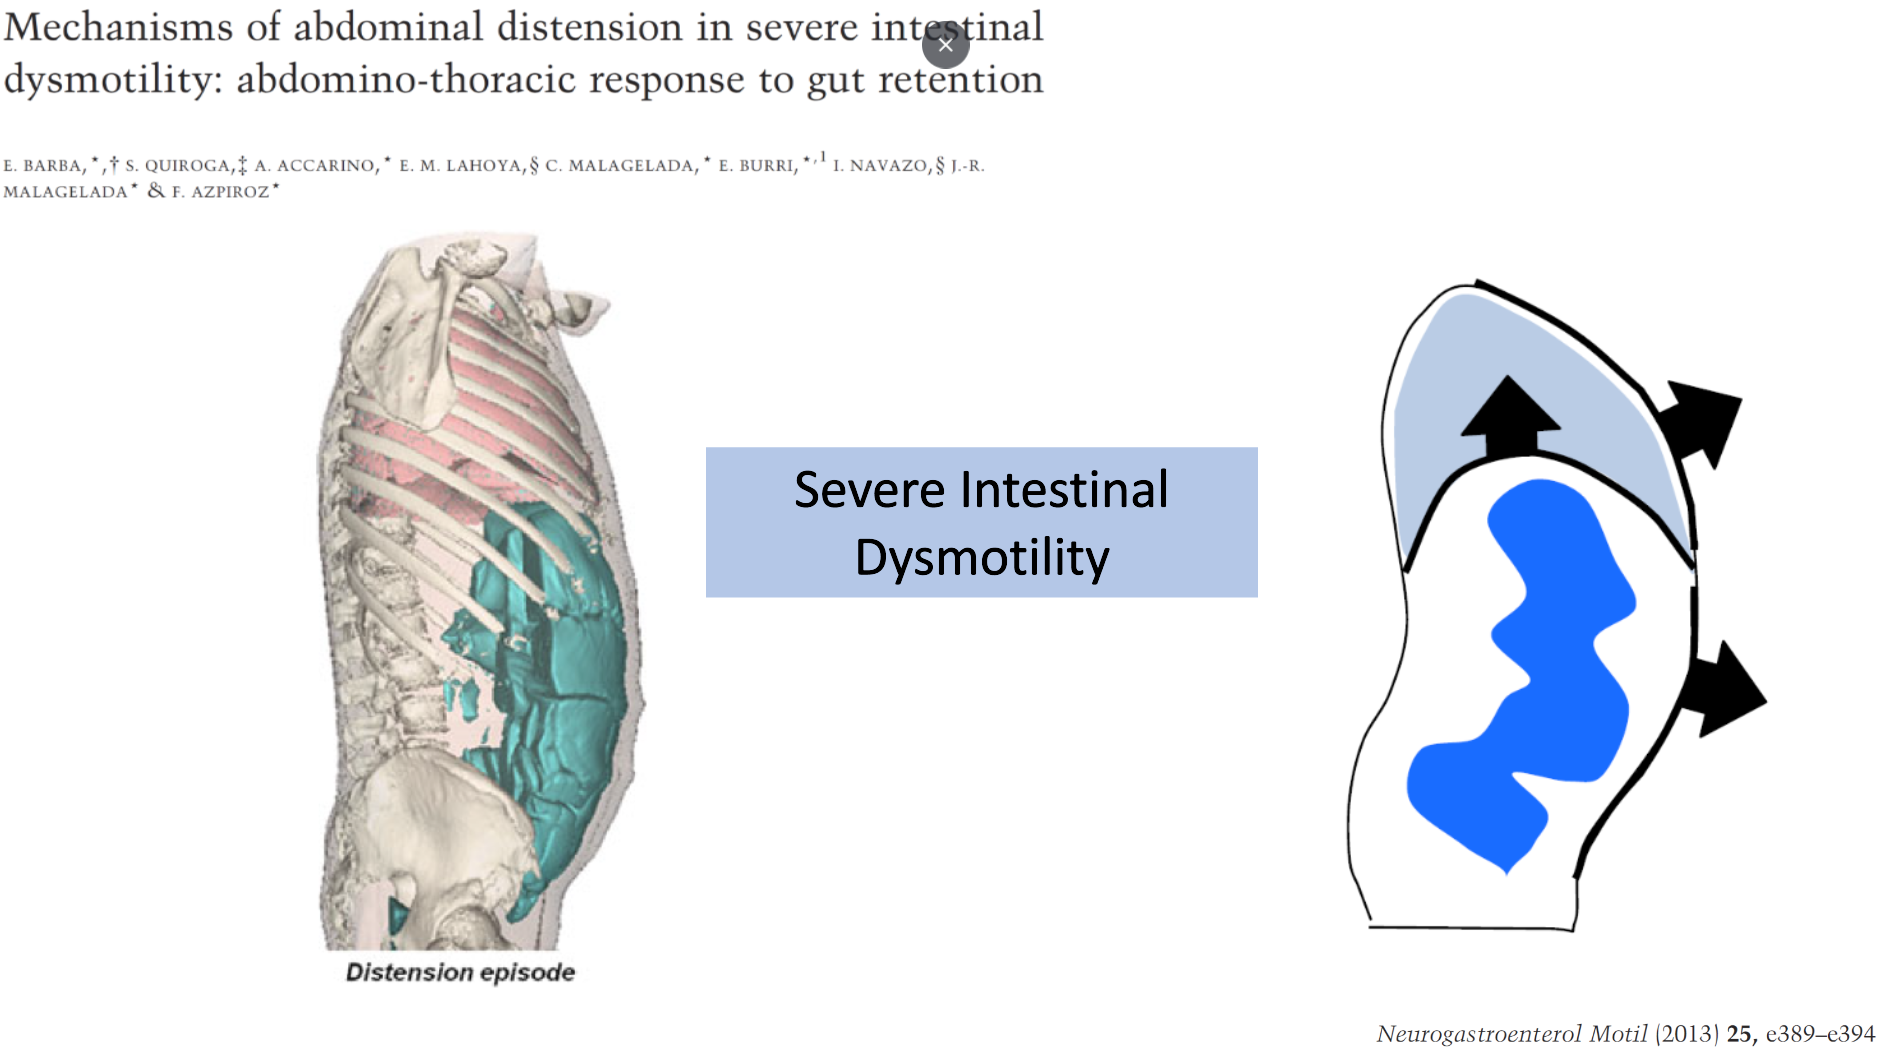
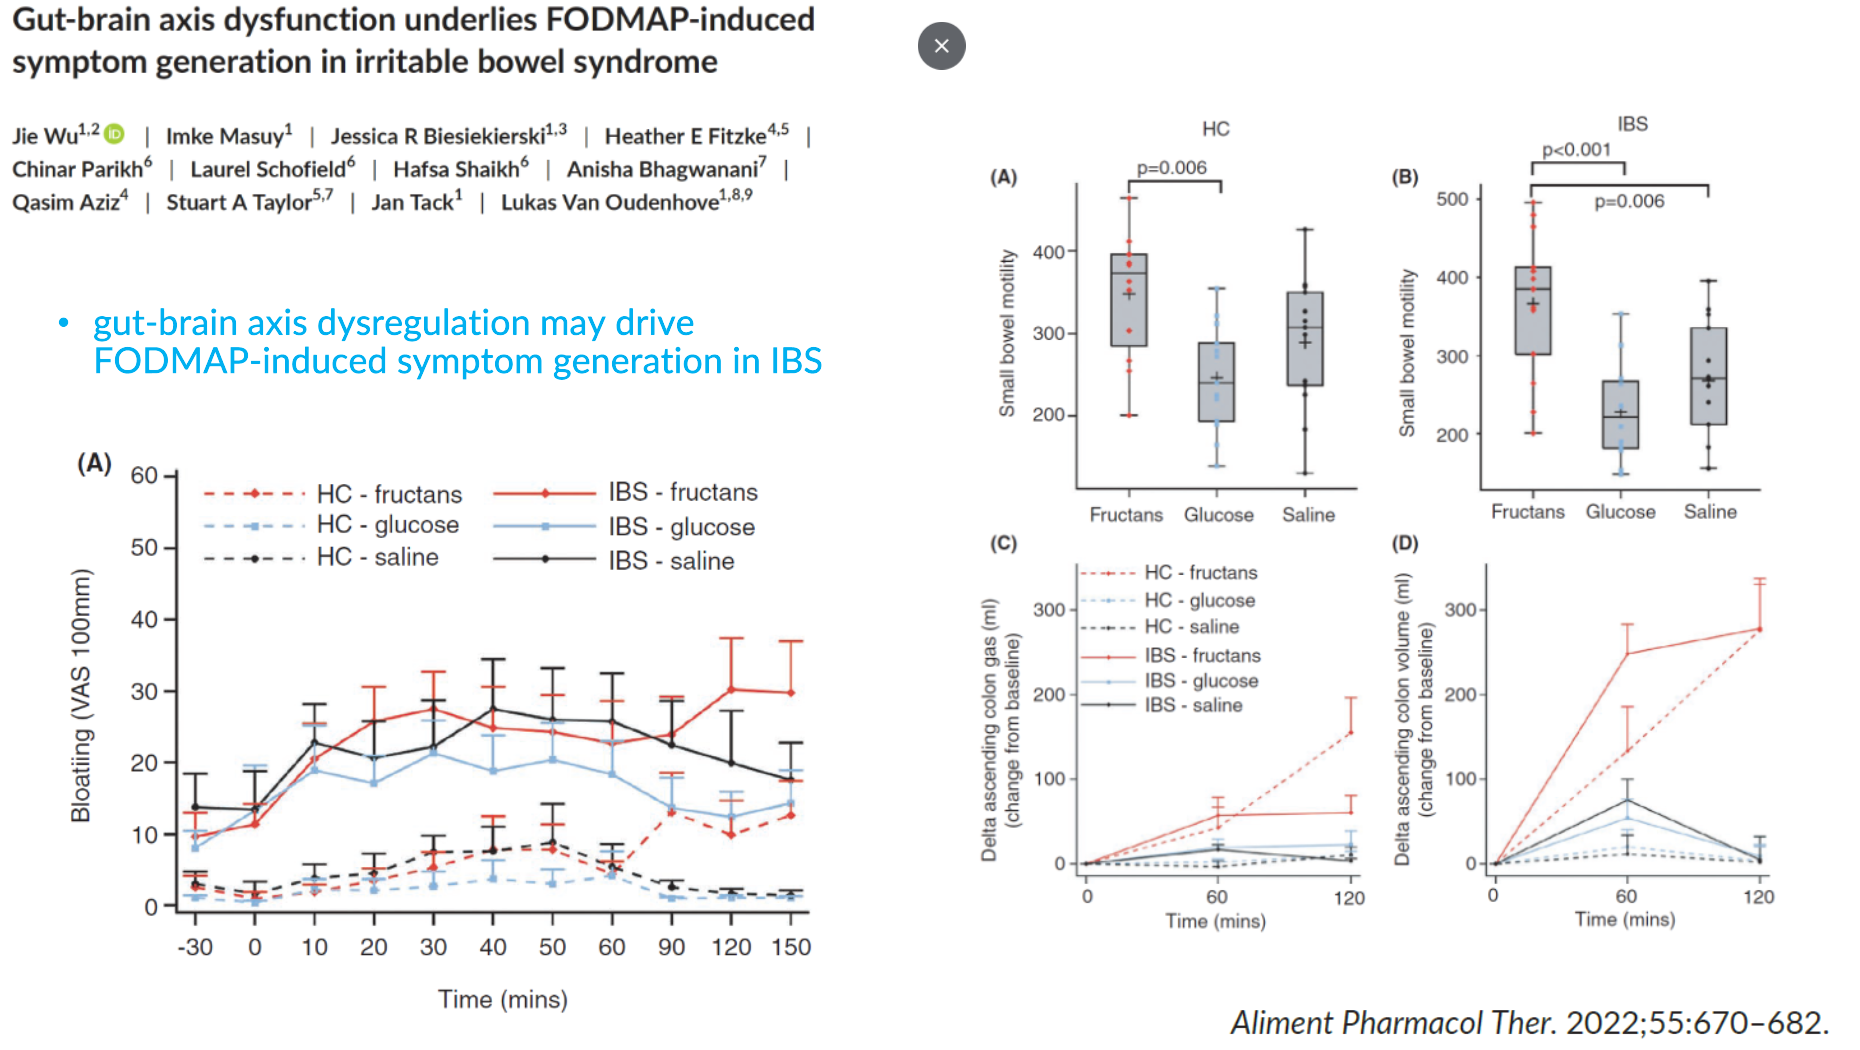
Recently Dr. Garza gave our group an excellent lecture. It is always great learning more about how the GI tract really works and what is going wrong when patients are having symptoms. I have taken some notes and shared some slides. There may be inadvertent omissions and mistakes in my notes.

Physiology:

Bloating:




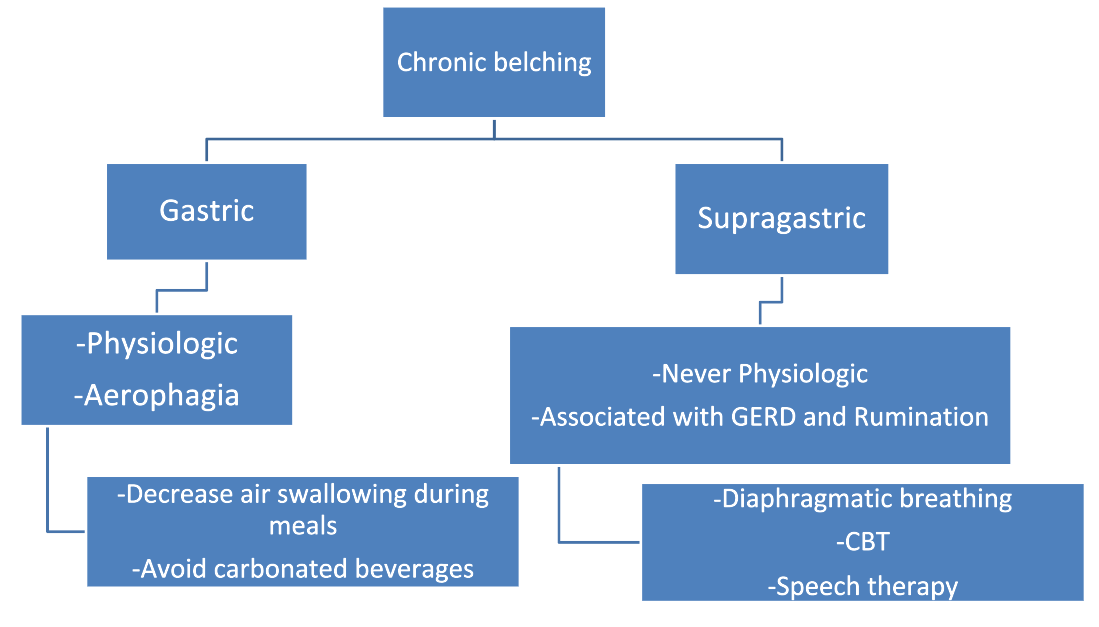
Belching:


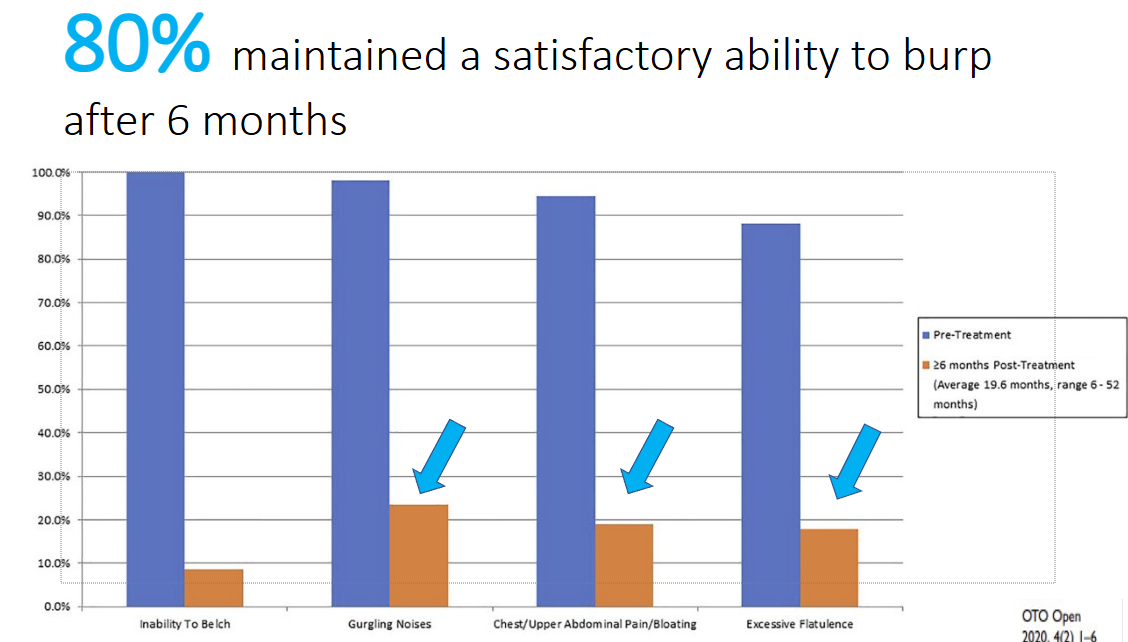
Inability to Belch:

Related blog posts:
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
JS Khoo et al. J Pediatr Gastroenterol Nutr. 2025;80:611–616. Impact of diagnostic testing on outcomes of children with rumination syndrome
Background: “A prior study from our institution showed that many patients undergo extensive diagnostic testing, which is associated with high financial cost with low clinical yield and delay in diagnosis.”
Methods: This was a retrospective study with 152 children (60% female, median age of diagnosis 13 years) with rumination syndrome (RS). 22 patients (14%) had diagnostic testing that confirmed RS.
Key findings:
Discussion Points:
“Our findings reveal that despite advancements in testing methodologies, undergoing diagnostic testing and receiving a positive result for RS is not associated with improved outcomes, specifically in cessation of vomiting, after treatment. In situations where patients and caregivers have difficulty accepting the clinical diagnosis, selective testing may be justified as acceptance of the diagnosis is a crucial aspect of the therapeutic plan for all gut-brain interaction disorders.”
Limitations included selection bias. While there were not overt differences in outcomes, the confirmatory testing group required more intensive treatment. As such, the testing may have some benefit in this group (though this was not identified in this retrospective study).
My take (borrowed in part from the authors): “We recommend that clinicians avoid diagnostic testing in children who clearly meet symptom-based criteria for RS and accept the diagnosis.”
Related blog posts:


