“Sub-10-minute High-quality Diagnostic Colonoscopy”

Like the last two days, this post addresses “high quality” colonoscopy…

A recent report (M Thomson et al. JPGN 2019: 69: 6-12) describes quicker pediatric colonoscopy times than previously reported and with 100% rate of ileal intubation.

In this report, there were 181 colonoscopies.

Time of colonoscopy:

  • The authors emphasize the fact that their mean time to the terminal ileum was 9.8 minutes.  Their good technical skill is probably related in part to experience: all 6 endoscopists had more than 10 years of experience (mean 19 years) and more than a thousand prior colonoscopies each.

Ileal Intubation Rate:

  • The 100% ileal intubation rate similarly indicates good technical skill.  It may indicate that their patient population was healthier as ileal structuring (which can prevent ileal intubation) can be noted in patients with Crohn’s disease.

Low Diagnostic Yield:

  • In my view, the study reports a low diagnostic yield.  They report 33% had abnormal histology (when excluding patients with IBD followup examinations)
  • 38% of their patients had colonoscopy due to abdominal pain. They reported a yield in this group of only 11.6% though this includes 4 patients with “TI lymphoid hyperplasia.”   Is this an abnormal finding?

My take: This study shows that with good technical skill colonoscopy can be done quickly with ileal intubation times averaging 10 minutes and with ileal intubation rates close to 100%.  In my view, another quality metric is diagnostic yield and their yield is lower than has been reported in most pediatric studies.

Related references:

  • K Siau et al. JPGN 2019; 69: 18-23.  This study describes “Direct Observation of Procedural Skills” (DOPS). Among 29 trainees, 81% of DOPS were rate competent after 125-140 procedures.
  • MT Barakat et al. JPGN 2019; 69: 24-31. This study noted that the vast majority of pediatric GI centers (>90%) were performing less than 25 ERCPs annually and that >70% “believe their institution’s current arrangement for performing pediatric therapeutic endoscopy is inadequate.”

Quality Metrics in Pediatric Colonoscopy

Continuing the theme from yesterday’s post…

Because of similar research in our group, I was interested in a recent study looking at pediatric colonoscopy quality indicators: CS Pasquarella et al.. JPGN 2019; 68: 648-54. (Editorial: CG Sauer, CM Walsh. JPGN 2019; 607-08.)

The authors analyzed 391 colonoscopies.

Key findings:

  • Ileal intubation rate of 91% (which is similar to our rate)
  • Ileal intubation rate was greater in their endoscopy suite where assistance was readily available.
  • Time for procedure: 34 minutes with staff alone compared to 42 minutes with a fellow trainee participant

To this point, we have not collected data on procedure duration at our institution –though 34 minutes seemed longer than I expected.

The authors also comment on cecal intubation.  I find this statistic to be less useful in pediatrics than adult medicine.  Reaching the cecum is important in cancer screening whereas reaching the ileum is important in identifying cases of inflammatory bowel disease.  The former is the main focus in adult gastroenterology and the latter is the main focus in pediatric gastroenterology.

My take: The editorial notes that “endoscopic providers and users can only know whether high-quality care is being delivered if it is being measured.”  I do think ileal intubation is important but other measures include good prep, low complication rate, appropriate patient selection (eg. good indication), and careful followup. Our work in this area will be presented at our upcoming NASPGHAN meeting–stay tuned.

Related blog posts:

Sagrad Familia, Barcelona


Colonoscopy and Isolated Abdominal Pain = Low Value Care

A recent study (HK Singh, LC Ee. JPGN 2019; 68: 214-7) reviewed a single center’s colonoscopy data (n=652) from 2011-15 with a focus on patients who underwent this procedure for abdominal pain.

Key findings:

  • Only 15 patients had isolated abdominal pain as an indication. In total 68 patients had abdominal pain as an indication but the majority had other ‘red flags’ such as rectal bleeding, family history of IBD or polyposis, weight loss, anemia, food allergy, or altered bowel habits
  • None of these 15 patients with isolated abdominal pain had organic disease
  • Among 36 patients with a measured fecal calprotectin and abdominal pain, all with elevated levels had positive histologic findings.
  • The ileal intubation rate/biopsy rate was 92.4%

I was particularly interested in this study because our group has reviewed our clinical experience in a large cohort undergoing outpatient colonoscopy (findings will be presented this fall).  Our group has a similar ileal intubation rate and a low rate of organic disease in those with isolated abdominal pain.

My take: More efforts are needed to carefully select pediatric patients undergoing endoscopy to minimize low value procedures.

Related blog posts:

Georgia Aquarium

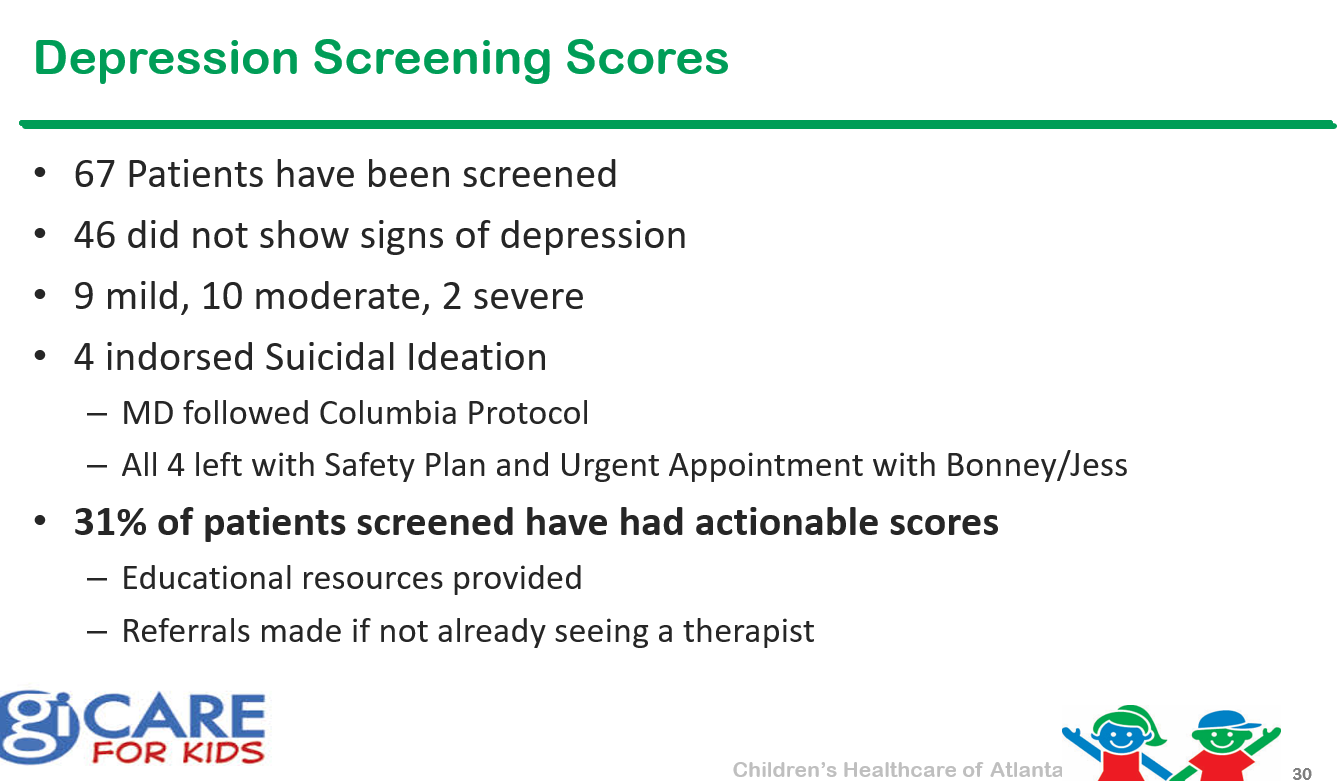
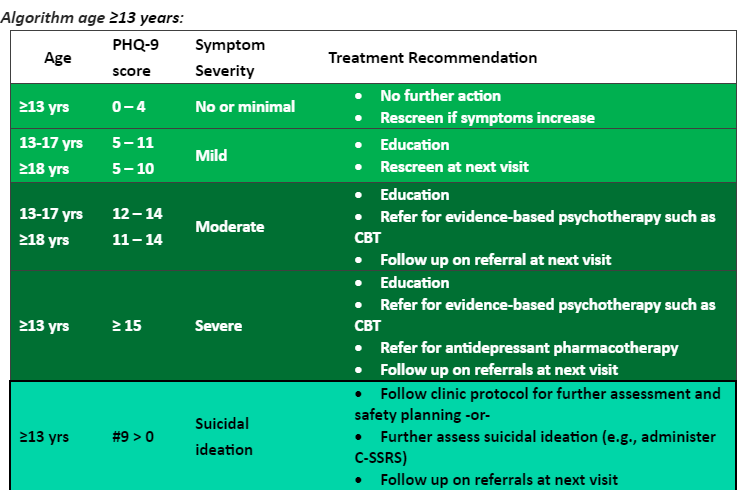
Depression Screening for Pediatric Patients with IBD

Recently, we had a morning conference to review depression screening for pediatric patients with IBD.  This lecture was led by Chelly Dykes, MD. Many of these slides were adapted from resources developed by the (ImproveCareNow) ICN Psychosocial Professionals group.

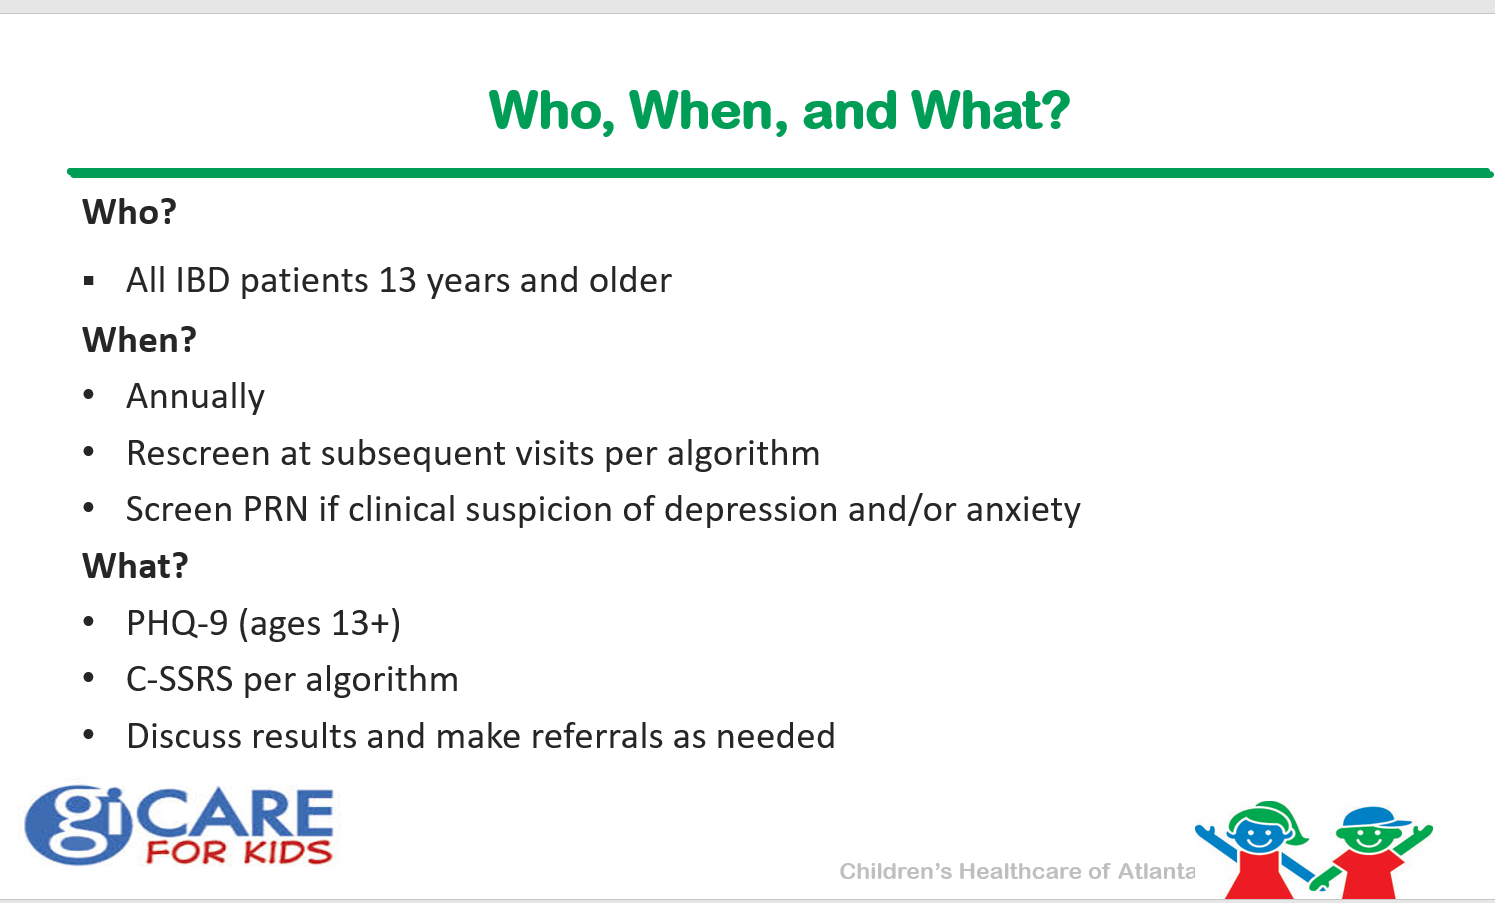
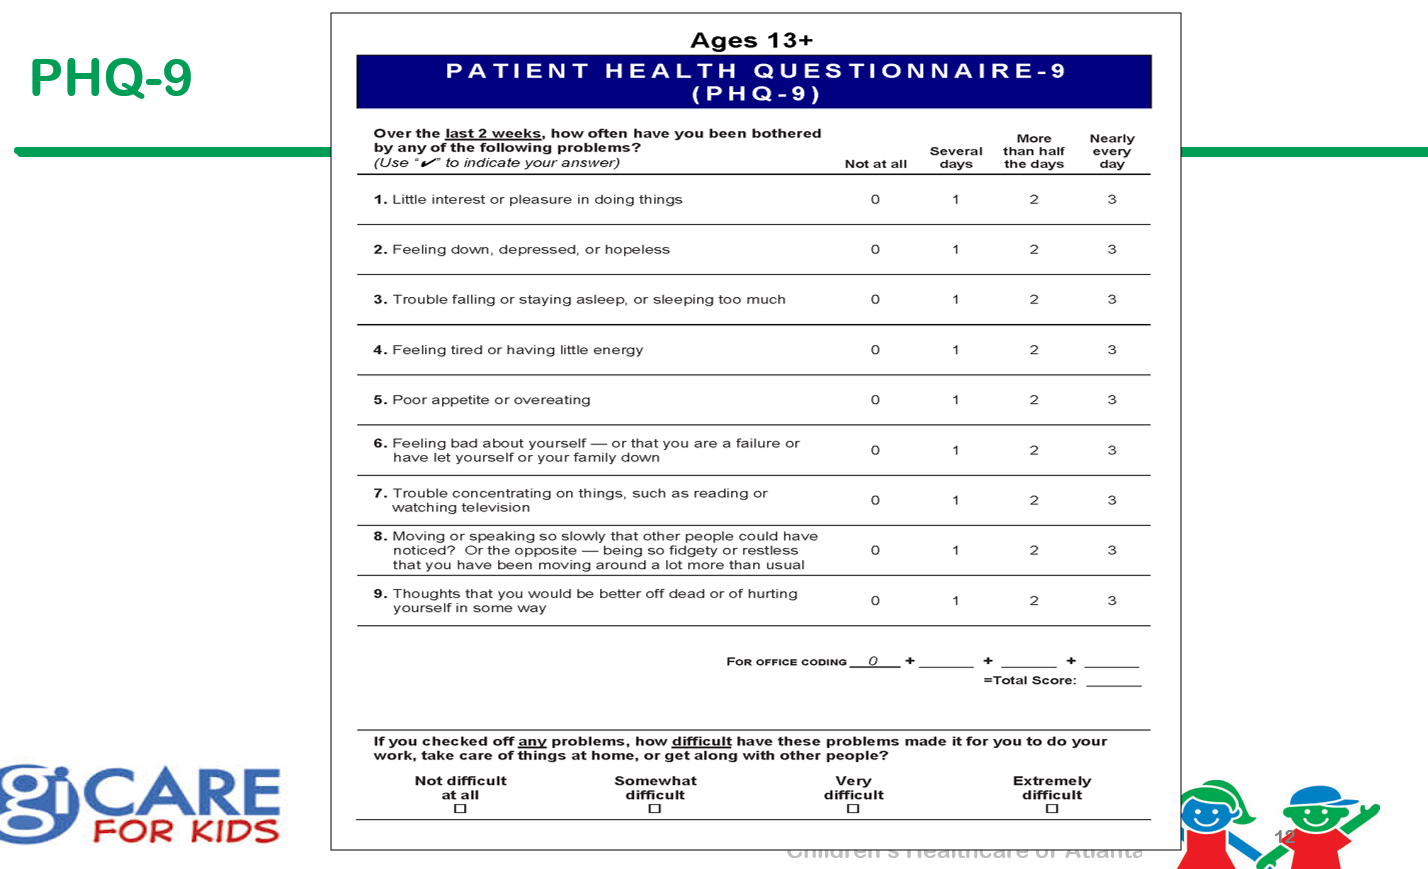
We have started depression screening with a subset of our patients and soon will start screening all children 13 years and older.  When this is working well, younger ages may be targeted as well.

Some of the key points:

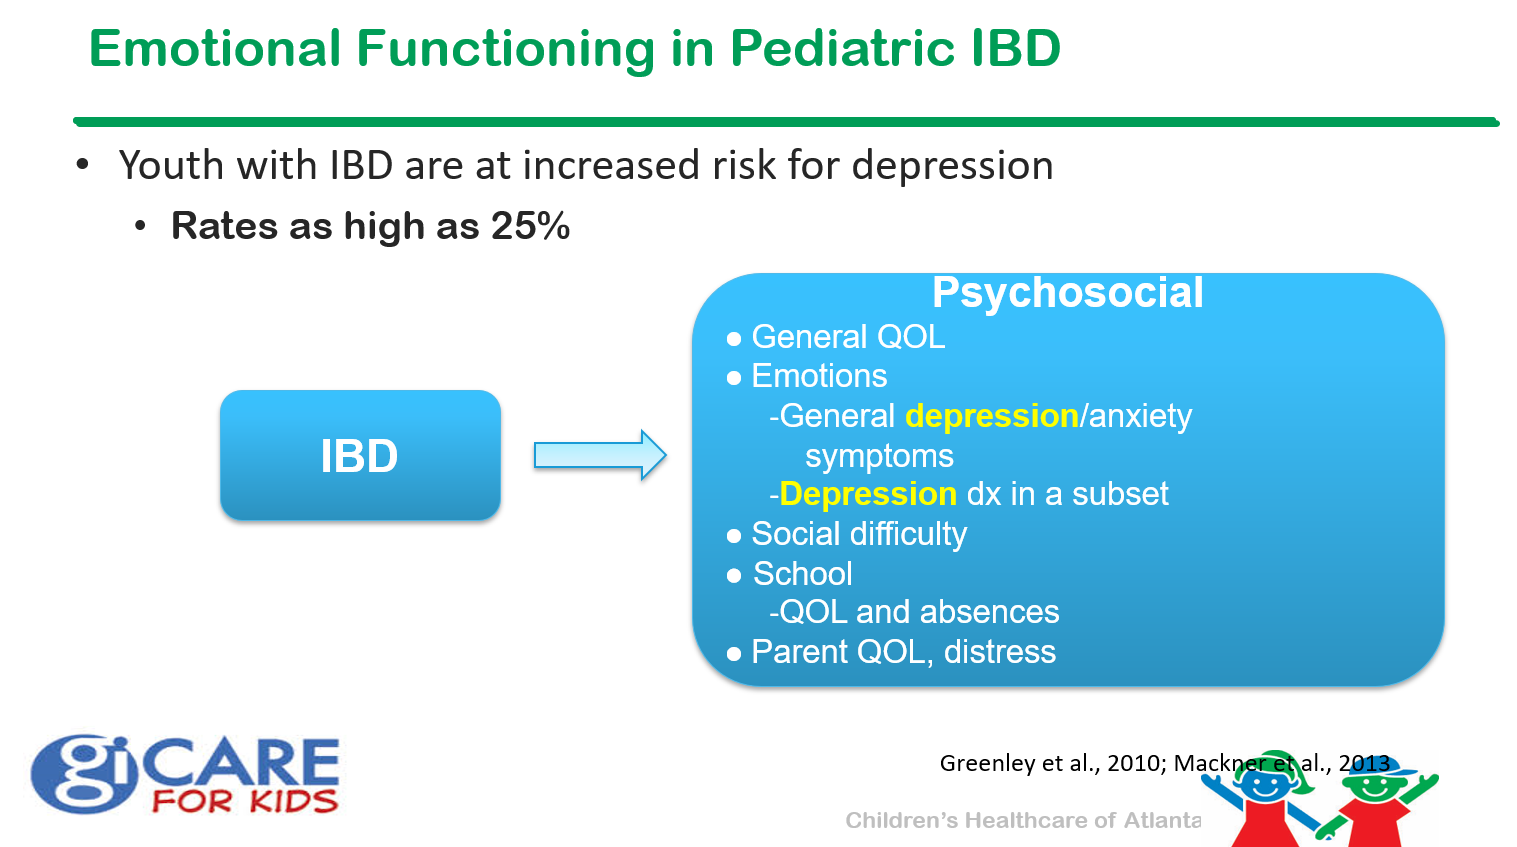
  • Depression/anxiety are common, particularly in patients with inflammatory bowel disease
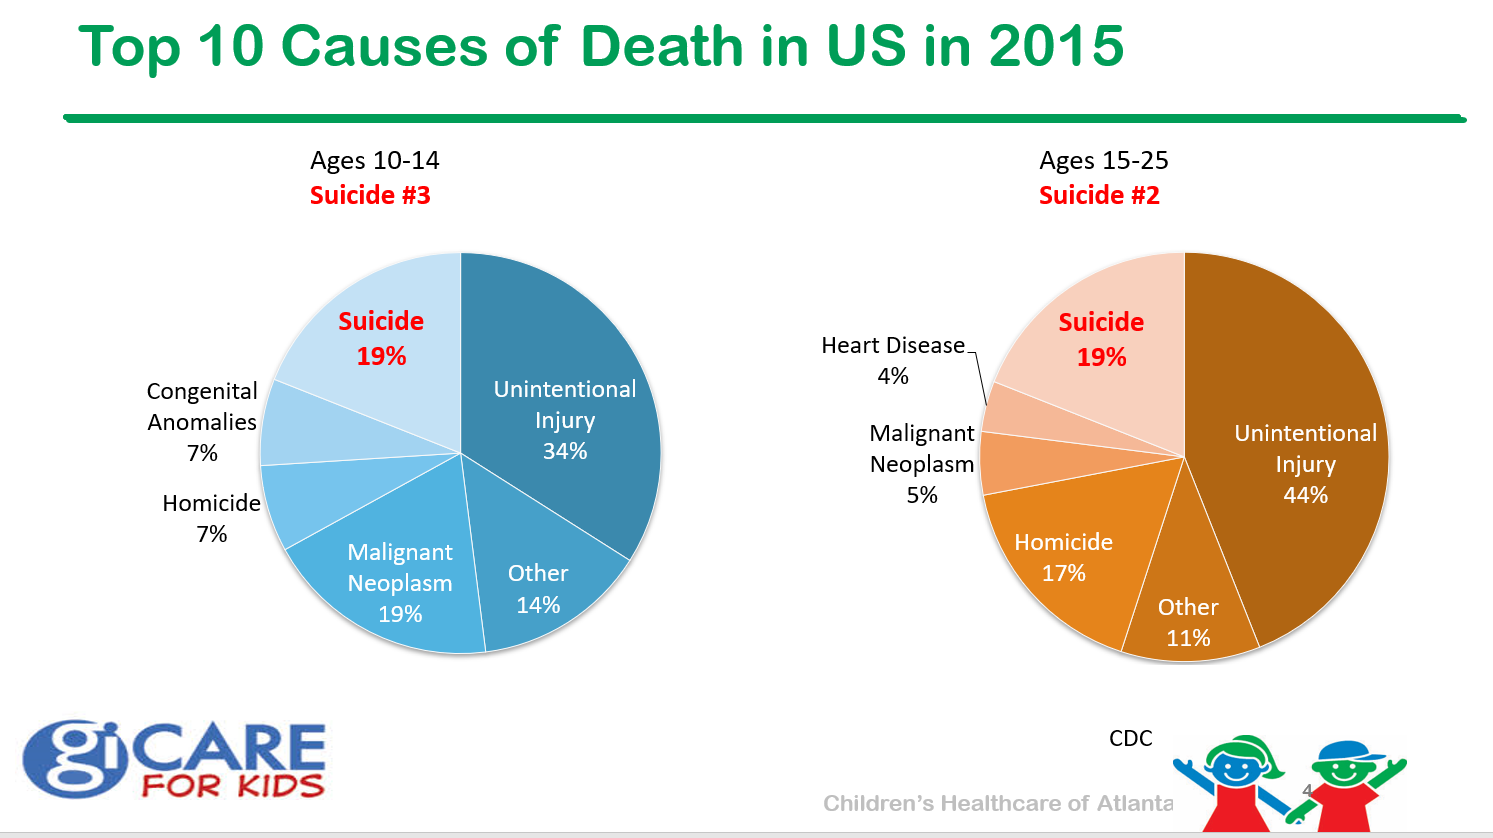
  • National rates of suicide have been increasing
  • Asking about suicide does not increase the risk of suicidality
  • We are fortunate to work closely with two psychologists, Bonney Reed-Knight and Jessica Buzenski

Some of the slides are listed below.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Is There Renal Toxicity with Mesalamine Therapy for IBD?

A recent study (V Jairath et al. AP&T 2019; https://doi.org/10.1111/apt.15408) provides evidence that 5-aminosalicylic acid therapy for IBD does NOT increase the risk of nephrotoxicity.  This paper’s findings run counter to more than thirty years of teaching on this medication.

Full Free Link: No increased risk of nephrotoxicity associated with 5‐aminosalicylic acid in IBD: a population‐based cohort and nested case‐control study

Abstract (bold highlighted by blog author):

Background

There is conflicting evidence about nephrotoxicity risk associated with 5‐aminosalicylates for treatment of IBD.

Methods

Retrospective cohort and nested case‐control study, using the Health Improvement Network primary care database linked to hospital discharge coding for patients in England, 1996‐2017. Nephrotoxicity risk analysis was a first recorded renal impairment diagnosis adjusted for key variables and was assessed between 2008 and 2017.

Results

A total of 35 601 patients with prevalent UC or CD were included. The proportion of patients prescribed 5‐aminosalicylates fell from 83% in 1996‐1999 to 71% in 2012‐2015 for UC patients and 64% to 45% for CD patients. Thirty per cent of patients had prolonged 5‐aminosalicylate use. Between 2008 and 2017, the incident rate of nephrotoxicity was similar and stable for UC (12.6/1000 person‐years) and CD (10.9/1000 person‐years) patients. Multivariate analysis showed no evidence for association between current prescription of 5‐aminosalicylate and nephrotoxicity in UC or CD patients, comparing ≤ 30 days prescription prior to index vs 31‐≤180 days. However, active disease, disease duration, concomitant cardiovascular disease or diabetes and nephrotoxic drug use were independently associated with development of nephrotoxicity in UC and CD.

Conclusions

Despite the paucity of evidence for their benefit, 5‐aminosalicylates were prescribed to approximately half of CD patients (30% prolonged therapy). Nephrotoxicity was rare in this patient cohort, and was not associated with 5‐aminosalicylate use, but rather with disease status, comorbidity and use of nephrotoxic drugs.

Related blog posts:

Park Guell, Barcelona

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition


Informed Consent: Sedation Risks in Children Younger Than 3 Years

A recent review (DS Fishman, DB Andropoulos, JR Lightdale. JPGN 2019; 69: 3-5) discusses the topic of sedation and an FDA warning from 2016 that should be familiar to pediatric GI physicians. Related blog post (2017): FDA Warning Anesthesia and Developing Brains

The medications which induce an ‘anesthetic state’ may cause cell death and may be “causing some degree of irreversible cellular injury –at least in developing brains, which are particularly vulnerable to apoptosis… [which leads to the] sobering thought that …sedatives could be associated with long-term neurological effects.”  At the same time, the authors caution of the potential for the warnings to cause “a delay in the care of the patient.”  The authors advocate the following talking points:

  • “A single short exposure (~60 minutes) does not appear to cause adverse neurodevelopmental outcomes”
  • “There is some evidence that longer (>3 hours) or repeated exposure could have negative effects on behavior or learning.”

Websites for physicians and families:

My take: These FDA warnings need to be taken seriously and low yield/low value endoscopy needs to be avoided.

Related Posts:

Park Guell, Barcelona

Briefly Noted: Microscopic Duodenitis and Autism

A recent study (C Alessandria et al JPGN 2019; 69: 39-44) enrolled 151 patients to examine for correlation between mucosal disease and autistic children with gastrointestinal symptoms. Patients were prescribed a gluten-casein free diet (GCFD)

Key findings:

  • 134 (89%) had negative celiac disease serology
  • 56 (*37%) showed microscopic inflammation of duodenum
  • Response to GCFD diet was much higher in those with duodenitis (OR 11.3). It was unrelated to HLA-DQ2/DQ8 positivity (which was present in 48%)
  • Response to GCFD occureed with both rigourous and partial adherence without statistical difference

My view: The authors suggest that an EGD may help predict who would respond to GCFD. An alternative approach would be to offer a GCFD in those with significant GI symptoms given the unclear clinical relevance of microscopic duodenitis.  This view is supported by previous studies which have indicated that the GI findings are similar among children with and without autism.

Related blog posts:

Park Guell, Barccelona


Orodispensable Budesonide Tablets for Eosinophilic Esophagitis

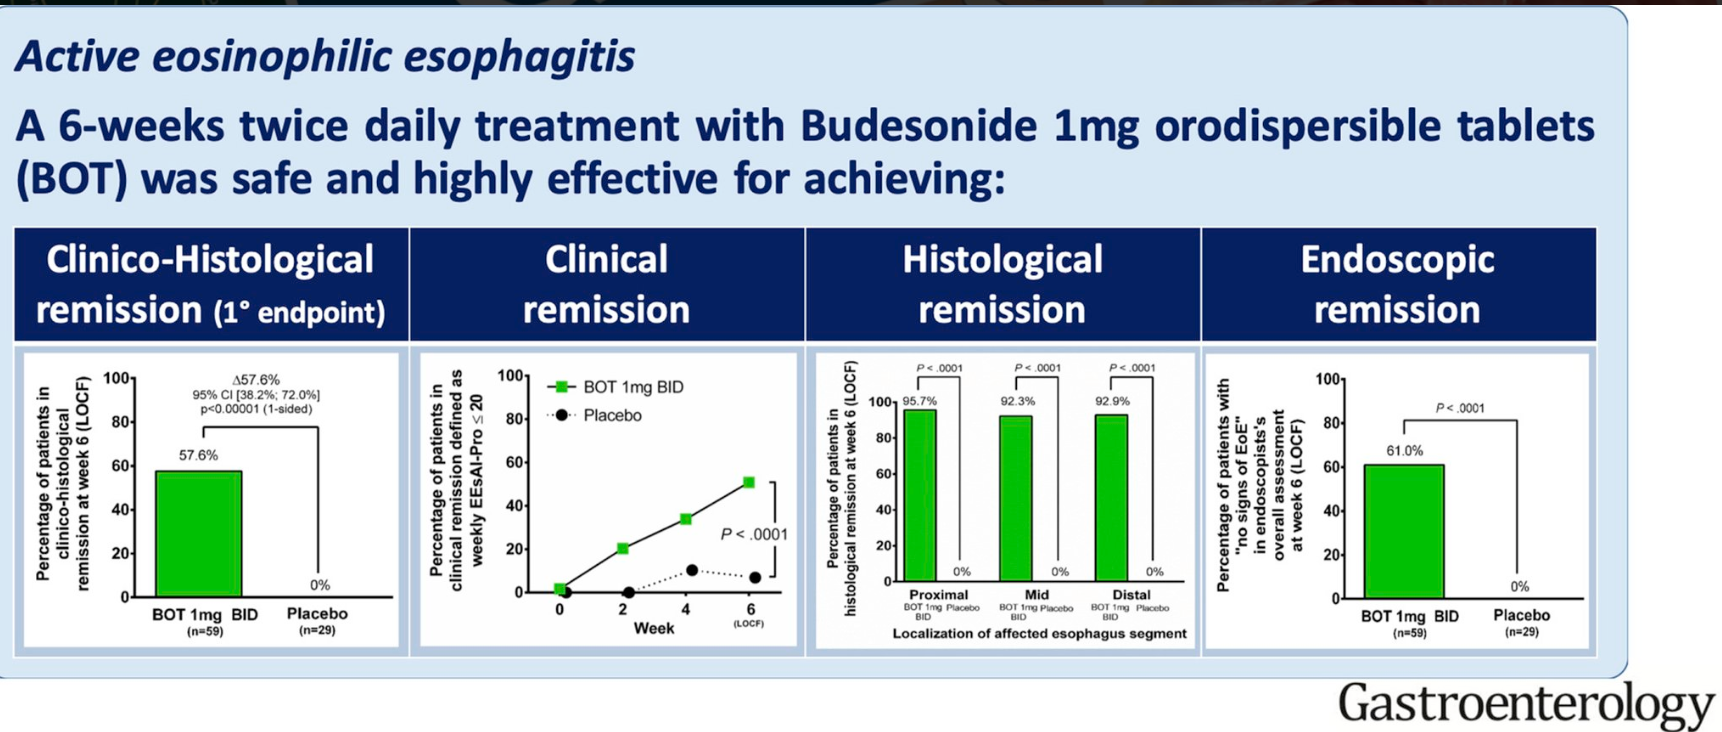
Full Text Link (courtesy of AGA twitter feed):Efficacy of Budesonide Orodispersible Tablets as Induction Therapy for Eosinophilic Esophagitis in a Randomized Placebo-Controlled Trial  AJ Lucendo et al. Gastroenterol 2019; 157: 74-86. https://doi.org/10.1053/j.gastro.2019.03.025

Abstract:

Background & Aims

Swallowed topical-acting corticosteroids are recommended as first-line therapy for eosinophilic esophagitis (EoE). Asthma medications not optimized for esophageal delivery are sometimes effective, although given off-label. We performed a randomized, placebo-controlled trial to assess the effectiveness and tolerability of a budesonide orodispersible tablet (BOT), which allows the drug to be delivered to the esophagus in adults with active EoE.

Methods

We performed a double-blind, parallel study of 88 adults with active EoE in Europe. Patients were randomly assigned to groups that received BOT (1 mg twice daily; n = 59) or placebo (n = 29) for 6 weeks. The primary end point was complete remission, based on clinical and histologic factors, including dysphagia and odynophagia severity ≤2 on a scale of 0–10 on each of the 7 days before the end of the double-blind phase and a peak eosinophil count <5 eosinophils/high power field. Patients who did not achieve complete remission at the end of the 6-week double-blind phase were offered 6 weeks of open-label treatment with BOT (1 mg twice daily).

Results

At 6 weeks, 58% of patients given BOT were in complete remission compared with no patients given placebo (P< .0001). The secondary end point of histologic remission was achieved by 93% of patients given BOT vs no patients given placebo (P < .0001). After 12 weeks, 85% of patients had achieved remission. Six-week and 12-week BOT administration were safe and well tolerated; 5% of patients who received BOT developed symptomatic, mild candida, which was easily treated with an oral antifungal agent.

Ustekinumab in Pediatric Clinical Practice

A recent study (JR Dayan et al. JPGN 2019; 69: 61-67) provides some helpful insight into the use of ustekinumab.

Background: The authors conducted a retrospective review of 52 patients (73% younger than 18 years, 27% 18-21 years).

  • Median age at induction was 16.8 years.
  • 10 patients were biologic-naive; 42 had received at least one anti-TNF agent (18 had received two anti-TNFs).
  • 42 of the 52 patients had Crohn’s disease.
  • Of note, 64% of their patients had a normal baseline CRP and they defined “biomarker remission at 52 weeks” as having a normal CRP.  The high rate of normal baseline CRP likely indicates milder disease than many other refractory populations; though nearly half of the patients with Crohn’s disease were receiving steroids when ustekinumab was initiated.
  • Steroid-free remission was defined by Harvey Bradshaw Index ≤4 or partial Mayo Score <2 and off steroids for >4 weeks.

Dosing: 47 (90%) received induction with ustekinumab IV (260 mg if <55 kg, 390 mg if 55-85 kg, 520 mg if >85 kg) followed by 90 mg subcutaneous injections every 8 weeks

Key findings:

  • 75% of patients continued to receive ustekinumab at 52 weeks.
  • 50% of bio-exposed patients were in steroid-free remission
  • 90% of bio-naive were in steroid-free remission
  • 57% received a dose escalation (increased frequency due to inadequate clinical response); such that at 52 weeks, 12 were receiving q4 weeks, 9 were receiving q6-7 weeks, and 15 continued with q8 weeks.
  • With a median f/u of 18 months, the authors reported few serious adverse events: two patients had an anaphylactoid reaction with IV induction (Rx with steroids and epinephrine). One of these two went on to experience arthralgias, fatigue and headaches with maintenance injection and treatment was discontinued. One patient experienced “self-limited paresthesia of bilateral lower extremities at 16 months on therapy” (CHOP experience with 22 patients reported one case of transverse myelitis: #NASPGHAN17 More Abstracts)

Discussion:

  • The authors note low immunogeiecity of ustekinumab and “suggest that ustekinumab monotherapy is possible and preferable in children”
  • Limitations: Lack of better objective markers for response to treatment

My take: This data indicates that ustekinumab therapy was associated with clinical remission in 50% of patients who had received anti-TNF therapy and had higher response in a small sample of biologically-naive patients.  More experience is needed to confirm drug safety with long-term usage

Related blog posts:

Barcelona


CDC Warns of Cryptosporidium in Pools

July 1, 2019: Washington Post: CDC warns swimmers about ‘Crypto,’ a parasite that can live for days in pools

An excerpt:

The Centers for Disease Control and Prevention published a report last week about the increased number of outbreaks caused by the fecal parasite Cryptosporidium, more commonly known as “Crypto.”…

The warning came from the CDC’s recent Morbidity and Mortality Weekly Report, which highlighted an average 13 percent increase in cryptosporidiosis outbreaks each year from 2009 to 2017.

The CDC said that over the past decade, there have been more than 400 reported outbreaks in the United States, leading to nearly 7,500 people becoming sick. Of those, more than 200 people were hospitalized, and one person died as a result of the disease, according to the report…

In about 35 percent of the outbreaks, sicknesses were linked to swimming pools and playgrounds, according to the report.

Related blog posts:

Bear and the Strawberry Tree, Puerta del Sol, Madrid