Explains biologic properties -typically 10-15 g of Albumin is synthesized daily (reduced in advanced liver disease). The half-life is between 12-18 days
Main uses: beneficial in patients undergoing large-volume paracentesis or who have hepatorenal syndrome or spontaneous bacterial peritonitis.
Studies have shown possible modest benefit in long-term albumin administration in patients with cirrhosis, especially ANSWER study which showed a reduction in ascites recurrence, HRS, encephalopathy, infections, hospital admissions and death. Costs of long-term infusion and the lack of benefit in the ATTIRE trial indicate the need for more studies to determine the best approach in this population.
Main adverse effects: allergic and transfusion reactions, volume overload, antibody formation and coagulation derangements
Generally, albumin infusions are not recommend for correcting isolated hypoalbuminemia. The primary disorder (eg. acute stress, trauma, infection, malignancy) should be treated.
This great little article humanizes and summarizes the discovery of Hepatitis C with first hand accounts and anecdotes.
A couple of interesting points:
Until you know the call is from Stockholm (and not a prank), the 4 am call informing you were awarded a Nobel prized is quite irksome
All of the Nobel Laureates (none are hepatologists) advocate for a vaccine but note that making it is difficult due to so many quasispecies. Only a fraction of the estimated 72 million persons with chronic HCV infection have been diagnosed and received curative therapy
Advice for young people: “There is no elevator to success. You have to take the stairs…It’s a step-by-step, slow process”
Hepatology humor: “Is life worth living?” “It depends upon the liver.”
Key milestones in HCV virology and therapeutics. Abbreviation: SVR, sustained virological response.
This article (link: PAs want to be called physician associates) notes that “Physician assistants, as they are still legally called, have been steadily granted greater autonomy over the years since 1967, when the Duke University School of Medicine graduated four former Navy medics as the nation’s first class of PAs.”
The authors searched MEDLINE, EMBASE and CENTRAL from inception to March 2021. Eligible studies were placebo-controlled trials of pharmacological interventions for CD
Key findings:
In 125 studies (91 induction, 46 maintenance), placebo clinical remission and response rates for induction studies were 18% [95% confidence interval (CI) 16-21%], and 32% (95%CI 29-35%), respectively, and for maintenance studies were 28% (95%CI 23-34%) and 30% (95%CI 24-37%), respectively
Endoscopic remission and response rates (for placebo) in induction studies were 8% (95%CI 4–18%), and 16% (95%CI 11–23%), respectively
Trials enrolling patients with prior biologic exposure, longer disease duration and higher CD activity index scores were associated with lower placebo clinical remission rates
Increased duration of follow-up, more follow-up visits and a greater proportion of patients with colonic disease distribution were associated with higher clinical placebo rates
My take: These studies show fairly high placebo responses and thus they reinforce the need for well-designed trials with objective endpoints.
Recent articles indicate the possibility of preclinical disease detection of inflammatory bowel disease; perhaps this is analagous to the “precrime’ detection in The Minority Report which allowed the police to arrest people before they committed their crime.
In this study from Sweden, the authors used biobanked plasma samples from 72 individuals with ulcerative colitis (UC) and matched healthy controls (n=140). Then the findings were validated in an inception cohort (n=101 with UC and 50 healthy controls. In addition, a cohort of heathy twin siblings of patients with UC (n=41) were matched with healthy controls (n=37).
Key findings:
Six proteins (MMP10, CXCL9, CCL11, SLAMF1, CXCL11 and MCP-1) were up-regulated (P < .05) in preclinical ulcerative colitis compared with controls
MMP10, CXCL9, CXCL11, and MCP1, but not CCL11 and SLAMF1, were significantly up-regulated among the healthy twin siblings. This up-regulation is triggered by exposure to genetic and early environmental factors.
The discussion elaborates on the role of these proteins.
“MMP10 is classified as a stromelysin. Upregulated levels of stromelysin have been detected in inflamed segments of the colon from patients with ulcerative colitis….The observed preclinical upregulation of MMP10 [thought to promote wound healing] in plasma might indicate that endogenous pathways for wound healing are up-regulated several years before clinically overt ulcerative colitis to counteract disease progression and maintain mucosal homeostasis”
“Eotaxin (CCL11) is a potent chemoattractant of monocytes…eosinophilic-driven inflammation represents an early element in the pathogenesis of ulcerative colitis”
“CXCL9 and CXCL11 has been observed previously in inflamed colonic tissue specimens and blood from patients with ulcerative colitis… Both chemokines are regulated by IFN-gamma and attract CXCR3-positive CD4þ T cells and natural killer cells to the inflammatory site”
My take: This study shows up-regulation of 6 plasma proteins indicating activation of both pro-inflammatory and tissue-repairing pathways several years before clinically overt UC. It offers hope of intervention to prevent the development of UC.
In this study, the authors measured host serum antibody response to 6 microbial antigens at enrollment (Prometheus enzyme-linked immunosorbent assay test: anti-Saccharomyces cerevisiae antibodies immunoglobulin A/immunoglobulin G, anti-OmpC, anti-A4-Fla2, anti-FlaX, anti-CBir1) and derived the sum of positive antibodies (AS).
Key finding:
“High baseline AS (≥2) (43% of cases, 11% of controls) was associated with higher risk of developing CD (adjusted odds ratio, 6.5; 95% confidence interval, 3.4–12.7; P < .001). Importantly, this association remained significant when adjusted for markers of gut barrier function, fecal calprotectin, C-reactive protein, and CD-polygenic risk score, and in subjects recruited more than 3 years before diagnosis. Causal mediation analysis showed that the effect of high AS on future CD development is partially mediated (42%) via preclinical gut inflammation.
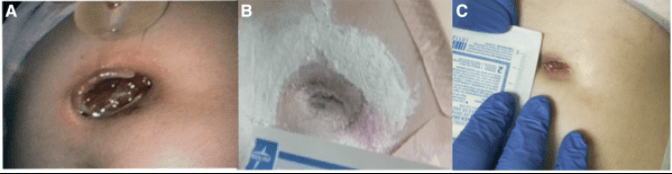
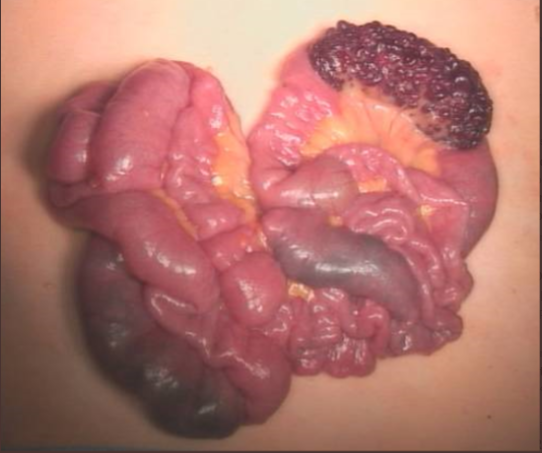
This case report describes a 10 yo with multiple medical problems with an expanding G-tube site with mucosal prolapse “where the G-tube balloon easily fell out of her gastrocutaneous fistula.”
The site was treated with three modalities, though the authors attribute the improvement to the use of sucralfate:
Nasojejunal feedings
Removal of Gastrostomy tube for 5 days
Sucralfate: “1 gram tablet, ½ tablet crushed sprinkled around the ostomy site 3 times a day. Powder was used to fill in the defect and any residual powder medication was gently cleaned off before the next application”
Images showing improvement noted below
The authors provide pathophysiological reasons for sucralfate’s effectiveness:
Treatment with sucralfate helped reduce the 2 cm x 1.5 cm site (Panel A) over 5 days to Panel B and over 4 weeks to Panel C
Background: “The general unavailability of culture-based susceptibility testing for H pylori has resulted in the almost universal reliance on hopeful (empiric) therapy and a high proportion of treatment failures.” Besides the lack of availability of culture-based susceptibility testing, the global increase in prevalence of antimicrobial resistance contributes to the poor cure rates obtained with empiric use of the currently most popular triple therapies for H pylori infection.
Methods:H pylori isolates (n=170) (clinical isolates and formalin-fixed, paraffin-embedded) were tested for susceptibility to amoxicillin, clarithromycin, metronidazole, levofloxacin, tetracycline, and rifabutin using agar dilution and NGS targeted to 23S rRNA, gyrA, 16S rRNA, pbp1, rpoB and rdxA. Agreement was quantified using κ statistics.
Key findings:
Agreement between agar dilution and NGS from culture isolates was very good for clarithromycin (κ = 0.90012), good for levofloxacin (κ = 0.78161) and fair for metronidazole (κ = 0.55880), and amoxicillin (κ = 0.21400)
Comparison of NGS from tissue blocks and agar dilution from isolates from the same stomachs demonstrated good accuracy to predict resistance for clarithromycin (94.1%), amoxicillin (95.9%), metronidazole (77%), levofloxacin (87.7%), and tetracycline (98.2%)
“By targeting all of the genes responsible for antibiotic resistance, it is possible to obtain genotypic susceptibility data for all of the antibiotics of potential use, without the need to perform” culture and antibiotic susceptibility testing
“Hulten et al show not only that they obtained comparable results with the reference method (phenotypic) for most of the antibiotics, but also that NGS can also be performed on both culture isolates and stored histologic preparations. This result is important because it avoids the need for extra biopsies and culture”
“NGS could also be applied on stools. In this particular environment where H pylori DNA is found in a low amount, excellent DNA extraction methods are mandatory and progress is being made in this field”
My take: NGS can bring H pylori treatment to a new era (like almost all other infections). “Molecular methods can potentially augment or even replace the current in vitro methods for susceptibility testing, which are cumbersome, technically challenging, and time-consuming.”
A recent article on simplifying the “simple” endoscopic assessment for Crohn’s disease reminded me of a scene from “There’s Something About Mary” (see below) where one of the characters plans to market a 7 minute abs video to replace the 8 minute abs video craze.
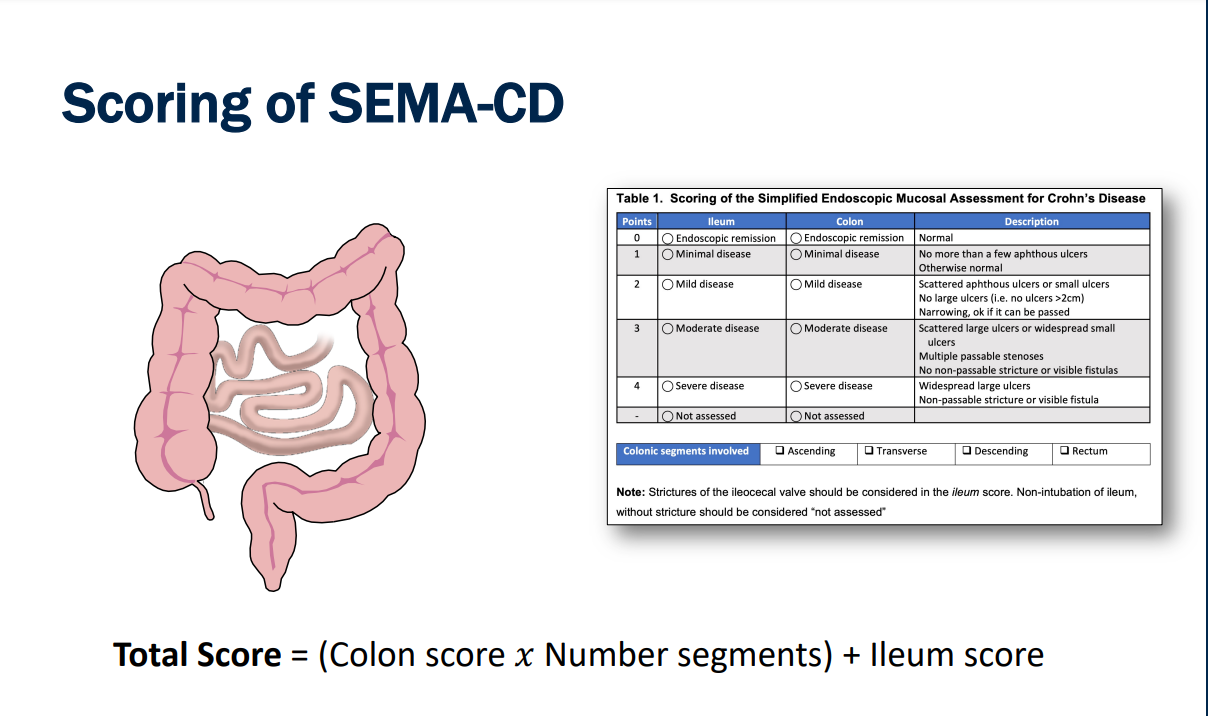
The article describes replacing the current “SES-CD” (or Simple Endoscopic Score for Crohn’s disease) with SEMA-CD (or Simplified Endoscopic Mucosal Assessment for Crohn’s disease).
The SEMA-CD was scored by assigning a numerical value ranging from 0 (remission) to 4 (severe disease) for each bowel region (ileum and colon). The colon score was multiplied by the number of involved colonic segments and then added to the ileum score. “For example, if overall the colon was felt to have moderate involvement, and only the ascending and transverse colon had mucosal abnormalities, then a score of 3 for moderate disease would be multiplied by a total of 2 segments for a total [colon] score of 6.”
Key finding:
While there was excellent correlation between SES-CD and SEMA-CD, SEMA-CD was much easier as it required one scoring for the entire colon rather than evaluation of each segment
The authors note that clinical assessment is inadequate to monitor CD. CDAI (PCDAI) are poor surrogates for mucosal improvement…”30-68% of patients in clinical remission have evidence of mucosal inflammation on colonoscopy….Patients whose disease is managed based on clinical information alone are more likely to have disease complications, need more surgeries, or lose response to medications.”
My take: The SEMA-CD appears to be much easier than the SES-CD and thus more likely to be useful in clinical practice (& research), especially as it becomes incorporated into routine endoscopy software. If the SEMA-CD is widely adopted, we will need to be on the lookout for the ‘6 minute ab’ version.
In this retrospective cohort study with 268 adult patients with inflammatory bowel disease, the authors compared the use of a GI PCR panel with 22 analytes (BioFire) and C diff testing to ‘conventional’ stool testing (culture, O&P and C diff). Key findings:
Pathogens were more frequently identified on GI PCR (26 vs 5%; P < 0.01)
GI PCR was associated with less escalation in IBD therapy (16 vs 29%; P < 0.01) and fewer posttest endoscopies (10% vs 18%; P = 0.04), with no differences in IBD outcomes
Those with recent travel had a higher pathogen detection rate: 38% vs 14%; P<0.01
In the GI PCR group, the most common pathogens were E coli species 22 (including 12 Enteropathogenic E coli), Campylobacter 10, Multiple pathogens 7, Norovirus 6, Yersinia 3, C diff 3,
The authors note that the group who underwent GI PCR panel testing were more likely to present with severe symptoms (eg. fever, rectal bleeding) as well as a history of recent travel. Even when controlling for symptoms and biomarkers of inflammation, GI PCR testing was still associated with lower likelihood of escalating IBD therapies.
My take: This study indicates that identification of an infectious pathogen which is more likely with a GI PCR panel helps avoid escalation of IBD therapy and need for endoscopy in the outpatient setting.