In this retrospective study with 218 inpatient pediatric patients with active ulcerative colitis, the key findings:
Use of enoxaparin did not result in a greater fall in hemoglobin among those with acute severe colitis (initial PUCAI ≥65) during the week following admission and there was not an increased risk of needing a transfusion
VTE occurred in 2 of 130 in control group and 1 of 88 in enoxaparin group (enoxaparin group was sicker)
My take: The absolute risk of VTE is low in the pediatric population. This study shows that enoxaparin prophylaxis is NOT associated with increased issues with blood loss. In those with active disease, the presence of CVC and use of steroids are known risk factors and require consideration of, at minimum, nonpharmacologic interventions.
This article is a large retrospective single-center (Boston Children’s) review of laparoscopic gastrostomy (LAP, n=545) compared to percutaneous endoscopic gastrostomy (PEG, n=545) (2010-2015). The authors note a shift in attitude in their institution in favor LAP due to perceived safety advantages (citing references 14-16 -reviewed below).
Key findings:
Total complication rate: 33% (146) in PEG group, 36% (197) in LAP group; cellulitis reported in 18% in PEG group compared with 10% of LAP group
ED visits: 89% (394) of PEG group had zero ED visits compared with 84% of LAP patients; In PEG group, 9% and 1% had one ED visit and two ED visits respectively compared to 15% and 1% in LAP group
In the early postoperative period (first week), patients undergoing PEG placement had more gastrostomy-related complications (PEG 30 [6.7%] vs LAP 13 [2.4%], P = 0.0007) and cellulitis (PEG 23 [5.1%] vs LAP 2 [0.4%], P = 0.03). Complications included postoperative pain, leakage, tube dislodgement, and stoma erythema
The authors reported higher total costs and operative time for LAP compared to PEG but note that in their institution, total cost may be higher for PEG due to frequent need for 2nd procedure for placement of a skin level device
In the discussion, the authors acknowledge that in their institution, “no differences in total complication rates within the first 6 months were seen.” My view is that the difference in cellulitis needs to interpreted cautiously in a retrospective study. The swelling and erythema around a PEG site in the first days postoperatively can be difficult to determine conclusively if there is cellulitis. With regard to potential cost advantages of LAP, this is affected in the PEG group by whether changing to a skin level device is done at the time of another procedure and whether the case is done in an outpatient surgery center where costs are lower.
My take: There is likely a lower rate of visceral perforation among children who have LAP placement over PEG placement. However, overall, it is uncertain if the complication rate from LAP placement is lower than PEG placement.
Review of some of the cited studies from this article:
F Sandberg et al. Pediatr Surg Int. 2018; 34 (12):1321-1327. Comparison of major complications in children after laparoscopy-assisted gastrostomy and percutaneous endoscopic gastrostomy placement: a meta-analysis While this meta-analysis with eight studies (n=1500 patients) found a lower risk of complications with LAP compared to PEG, the authors note that “there were no randomized-controlled trials. Overall, the quality of the included studies was determined to be unsatisfactory.” In addition, the results were heavily influenced by one study which reported 20 major complications (death or reoperation within 30 days) among 134 PEG patients.
L Baker et al.J Pediatr Surg 2015; 50: 718-725. A systematic review and meta-analysis of gastrostomy insertion techniques in children In this study, the authors examined 22 studies with 5438 patients that met inclusion criteria. No differences in major complications were noted in studies comparing open versus laparoscopic approaches or open versus PEG. Then, in a subset 10 studies (n=1599 laparoscopic, n=1161 PEG), the authors state that laparoscopic gastrostomy and PEG revealed a significantly increased risk in major complications with PEG (OR 0.29, 95% CI: 0.17–0.51, p < 0.0001). In this study, the most striking difference were 20 cases of visceral perforation with PEG and one case with LAP. Again, the data are limited by the retrospective nature of all but one study. This “suggest that individual-specific and/or institutional-specific factors likely influence outcomes and diminish the generalizability of the presented results.” Cited advantages of LAP: better visualization of site, ability to transfix stomach to abdominal wall, and ability to place primary button.
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
In this open-label trial of adults with mild-to-moderate biologic naive Crohn’s disease, key findings:
At week 6, 13 (68%) of 19 patients in the CDED plus partial enteral nutrition group and 12 (57%) of 21 patients in the CDED group had achieved clinical remission (p=0·4618)
Among the 25 patients in remission at week 6, 20 (80%) were in sustained remission at week 24 (12 patients in the CDED plus partial enteral nutrition group and eight in the CDED alone group)
14 (35%) of 40 patients were in endoscopic remission at week 24 (eight patients in the CDED plus partial enteral nutrition group and six in the CDED alone group)
My take: Dietary therapy may be effective option for motivated adult patients with Crohn’s disease.
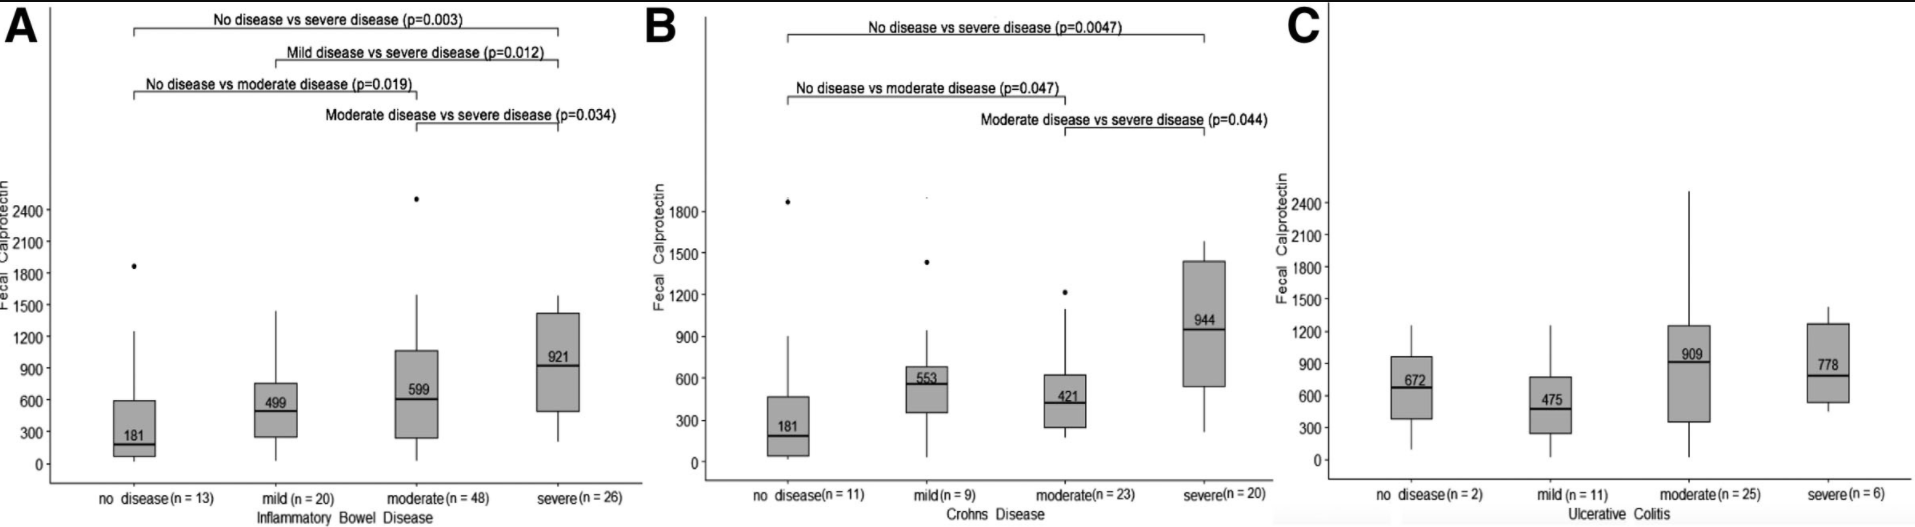
This retrospective study used data from 331 patients (n=107 with IBD). Fecal calprotectin (FC) was done between 30 days and 1 day before colonoscopy.
Key findings:
Correlation with endoscopy: median FC was lowest for all IBD patients with no active disease (181 μg/g) and highest in severe disease (921 μg/g), with significant difference between no disease and moderate and severe disease (P = 0.019, 0.003), and between mild and severe disease (P = 0.012)
Correlation with histology: median FC was lowest with no active disease (328 μg/g) and highest in severe disease (895 μg/g), with significant difference between no disease and moderate and severe disease (P = 0.021, 0.018)
The control population had median FC of 35.5 compared to 181 μg/g for the IBD population in endoscopic remission (P = 0.018).
My take: Calprotectin levels are particularly helpful as a screen for IBD (probably using threshold of at least 120) and its use to monitor clinical response. This study shows it has some utility in predicting disease severity.
Figure 1: Fecal calprotectin association with endoscopic disease severity of IBD (A), Crohn’s disease (B) and ulcerative colitis (C). IBD = inflammatory bowel disease.
Recently, Carlo DiLorenzo came to Atlanta as the speaker for the William Meyers Lectureship. He provided a terrific talk and was the perfect speaker for this lectureship which honors Billy.
Some of the key points:
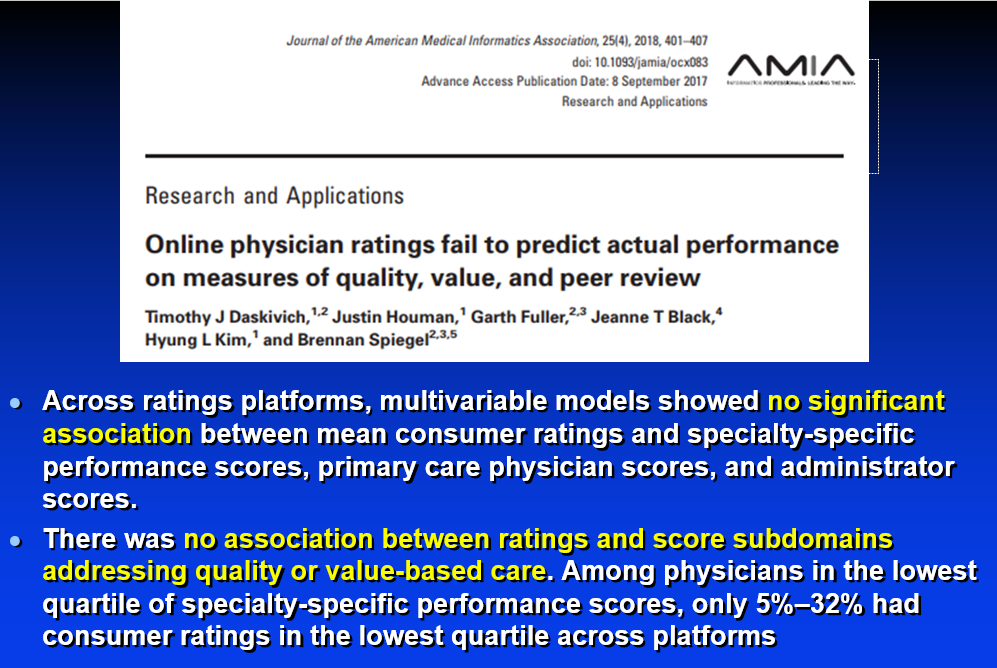
When giving a lecture, often ‘a great study is one that supports the speaker’s view’
Physicians often have biases against patients with functional disorders as compared to those who have “rightful” suffering (eg. cancer, pancreatitis)
Key part of patient-physician relationship is listening (by the physician). Patients report better satisfaction and perceive to be understood better when a physician is sitting (while listening). “The most important technological advance in the practice of medicine was the invention of the chair. For you to sit in. While you take the history” (Mark Reid, MD)
Diagnoses have side effects
Families remember our words for years
We are not well-equipped to deliver good news: “This is one of the best colons I have ever seen…Your child has irritable bowel and no other tests are needed.”
The most under prescribed treatment: 30 minutes of physical activity everyday
2nd most under prescribed treatment is a good night’s sleep. Increased symptoms when tired
“Psychobezoar,” referring to a fear of discomfort with eating, could be used as an alternative to ARFID
Most effective treatment for IBS: cognitive behavioral therapy
Distraction is helpful tool for pain but need to teach parents to accept this tool
Some of the axioms in the lecture are attributed to Mark Reid, MD
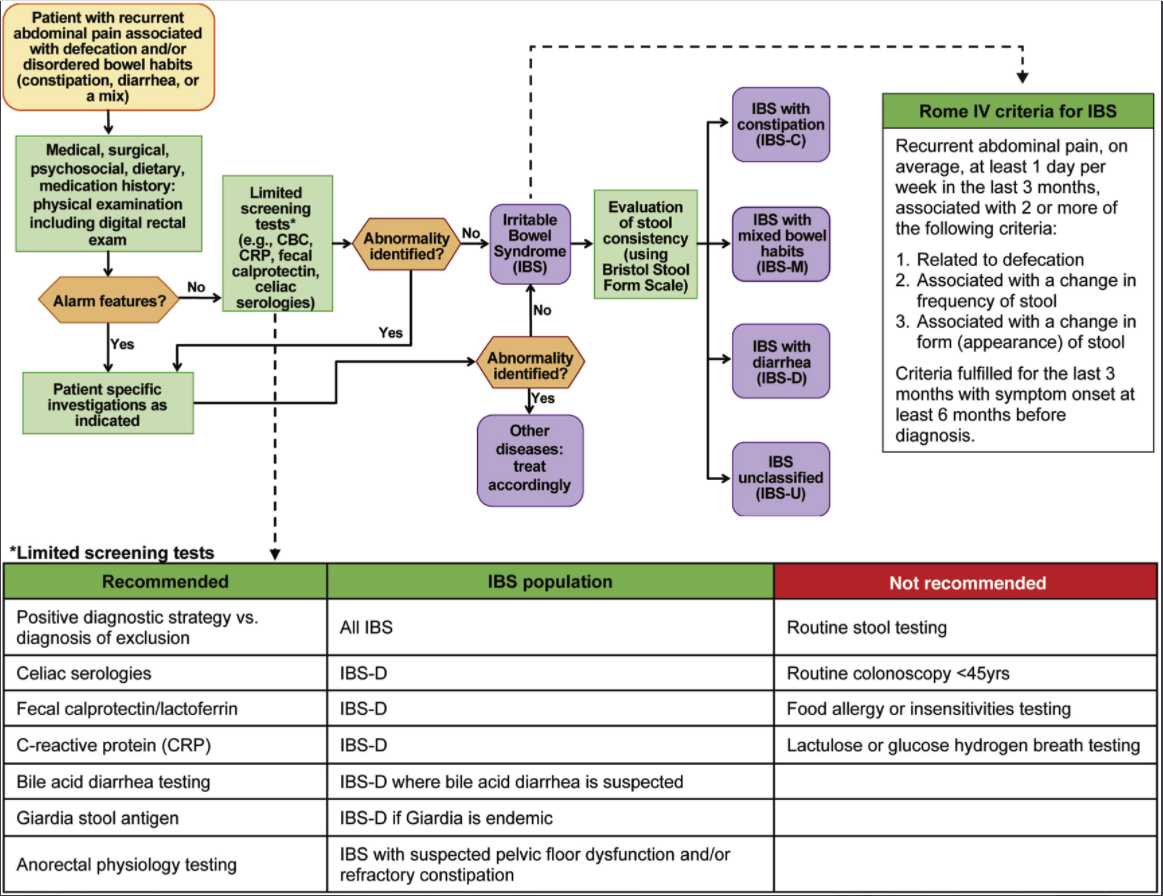
For a short article, this review provides a lot of practical advice. Challenges with IBS include the lack of objective biomarkers and “patients are often dissatisfied with a positive diagnostic approach or even after multiple negative tests.” The author recommends the following:
Confidently communicate the diagnosis of IBS
Explain visceral hypersensitivity and its associated with pain, and bloating and why central neuromodulators and behavioral therapy are often used. Explain that IBS can be associated with high-amplitude propagating contractures which can cause pain/diarrhea
Treatment focused on ‘RESET’ =Relationship with patient-provider, Education/reassurance, Symptom assessment, Exacerbating/alleviating factors, and Targeting treatment (see Table 1)
Treatment may need to target gut, brain and/or both
Dietary treatments considered 1st line approach
Treatment pharmacology options for IBS-D include antidiarrheals, antispasmotics, rifaximin, eluxadoline, alosetron (rarely, can cause ischemic colitis), bile acid sequestrants
Treatment pharmacology options for IBS-C include polyethylene glycol, lubiprostone, linaclotide, plecanatide, and tegaserod (restricted to women <65 yrs w/o cardiovascular dz)
Treatment pharmacology options for all IBS include TCAs (start with low dose and can titrate upwards; amitriptyline for IBS-C, nortriptyline or desipramine for IBS-M or IBS-C), SNRI (eg. duloxetine (may be better than TCAs in patients with IBS-C and comorbidities like fibromyalgia and depression), mirtazapine (small studies demonstrated benefit for IBS-D and functional dyspepsia), SSRIs (“consider…in patients with predominant anxiety and/or depression…advise against its use as primary treatment for IBS w/o comorbid psychological disorder”), delta ligand agent (eg. pregabalin) (consider if refractory to other treatments), and brain-gut therapies (eg. CBT, GDH)
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
My take: The need for a gastrostomy for nutritional support is associated with more severe CDH (~1/3rd of patients). Over a third of patients who received a GT, no longer needed a GT at a median of 26 months.
“Gastric adenocarcinoma and proximal polyposis of the stomach (GAPPS) is a rare gastric polyposis syndrome defined by numerous polyps (>100) in the fundus and body of the stomach with sparing of the lesser curvature and antrum.” Case report in a 16 yo who ultimately underwent a total gastrectomy. The geneticist identified the APC gene mutation with the OncoGeneDx Colorectal Panel by GeneDx. The rationale for the selection of this gene panel was its ability to examine 20 different genes involved in hereditary colorectal cancer and other gastrointestinal cancers. This panel checks APC, POLE,PTEN, STK11, BMPR1A, SMAD4, ATM, AXIN2, CDH1, CHEK2, EPCAM, MLH1, MSH2, MSH6, MUTYH, NTHL1, PMS2, POLD1, SCG5/GREM1, and TP53 genes
ESPGHAN Juvenile Polyposis Syndrome Recommendations These recommendations are different in that they do not recommend EGD in the pediatric age group: “Surveillance of the upper GI tract in affected or at-risk JPS patients is not required in childhood or teenage years, unless there is unexplained anaemia or upper GI symptoms.”
Are You Familiar with CMMR-D? The term CMMR-D refers to constitutional mismatch repair deficiency. This occurs when an individual inherits two MMR gene defects (rather than one gene defect in Lynch syndrome); with CMMR-D screening recommendations include yearly endoscopic evaluation beginning at age 3 years or at diagnosis.
Key findings from this retrospective review (n=233):
TCAs were not started in only 1.7% (4/233) due to ECG results
Eight (3.4%) had a cardiology referral; one (0.4%) had a prolonged QTc interval
No deaths and no emergency department or hospital visits for arrhythmia or drug overdose occurred
The discussion lists a number of studies generally questioning the utility of pre-medication ECGs while at the same time acknowledging that guidelines in the GI and psychiatric literature support an ECG prior to TCA use. In a large study of sudden cardiac deaths in an adult population, there was no increased risk of death with TCA dosing less than 100 mg/day (Clin Pharmcol Ther 2004; 75: 234-41).
My take (borrowed in part from authors): While “the benefit of screening ECGs remains elusive,” it is still needed to try to avoid “extremely rare but catastrophic events.” The authors, however, recommend followup ECGs only on “patients on concomitant QT prolonging medications or increases to higher dosing ranges.”