Why Stool Hoarding Might Be A Good Idea

SK Hourigan et al. JPGN 2021; 73: 430-432. Updates and Challenges in Fecal Microbiota Transplantation for Clostridioides difficile Infection in Children

This good update provides a lot of useful information regarding fecal microbiota transplantation (FMT) and a word of caution regarding its future availability.

Key points regarding FMT:

  • Long-term safety remains unknown. FMT may lead to susceptibility to chronic inflammatory, allergic, and autoimmune diseases. “FMT has been associated with durable transmission of pro-carcinogenic bacteria from adult donors to pediatric recipients…although the long-term consequences…are unknown.”
  • Due to transfer of extended spectrum beta-lactamase (ESBL) E coli to 2 immunocompromised adult recipients, further screening of FMT was implemented.
  • Though there is no published evidence of SARS-CoV-2 fecal transmission, the FDA “advised additional precautions and testing in March 2020; “however, there are no molecular tests with stool…which have received emergency use authorization.” Hence, most FMT programs were on hold as of January 2021.
  • After 2021, OpenBiome, whose product was recently available again, is expected to stop distribution of FMT donor product due to increased costs of screening and the “promising biotherapeutics” that are in phase III trials.
  • Biotherapeutic is “loosely defined as drug therapy products where the active substance is extracted from a biological specimen.” The new products are likely to have “increased standardization, safety and practicality.”
  • The problem in pediatrics: none of these biotherapeutic products have started trials in children. This will lead to treatment problems. Even if one wanted to set up donor-directed FMT, it will be difficult to complete all of the screening recommended by the FDA. It could lead to self-administration by families with uncertain risks.

My take: My first reaction to this article: ‘Oh crap!’ It is sad and ironic that I will miss having available commercial stool for FMT.

Related blog posts:

From The Onion: Things That Always Surprise Foreigners About American Health Care

From The Onion
From The Onion

Outcomes of Collagenous Gastritis

BC Beinvogl et al. JPGN 2021; 73: 513-519. Pediatric Collagenous Gastritis: Clinical and Histologic Outcomes in a Large Pediatric Cohort

In this retrospective single-center cohort study with 40 patients (1992-2020), the authors describe the outcomes and heterogeneity of treatments for pedicatric collagenous gastritis (CG). The mean age at diagnosis was 11 years with mean followup of 2.9 years.

Key points:

  • Presenting symptoms: abdominal pain, vomiting, symptomatic anemia, and nausea. 25 of 40 had a colonoscopy at time of index EGD
  • 75% had iron-deficiency anemia which responded well to iron supplementation
  • Comorbid conditions included autoimmune disorders in 12.5% and immunodeficiencies in 5%. 7 (17.5%) had excess collagen in duodenum, 3 (7.5%) had collagenous colitis, and 1 (2. 5%)had collagenous ileitis.
  • 85% of diagnosis were made on initial review of biopsy slides; other cases were identified subsequently either due to repeat endoscopy or further slide review. CG is “known to be patchy
  • No treatments were clearly effective in improving histology. Treatments included PPI/H2RAs in 40%, laxatives in 20%, cyproheptadine in 12.5%, antiemetics in 12.5%, cafafate in 7.5%, budesonide in 7.5% and others less frequently
  • 92% had persistent abnormal endoscopic findings and 73% had persistent thickened subepithelial collagen. In those without excess collagen deposition at last EGD, some of this could be related to patchy distribution as well as improvement
  • Though histology often did not improve, 87.5% had improvement or resolution of symptoms
  • Long-term outcomes remain unknown. While there is concern for possible malignant transformation, to date “no gastric epithelial or lymphoid malignancies have been…reported”

My take: Collagenous gastritis is poorly understood. Fortunately, most patients symptoms resolve/improve.

Related blog post: Collagenous gastritis (2020) -useful reference

Irritable Bowel After Campylobacter Enteritis

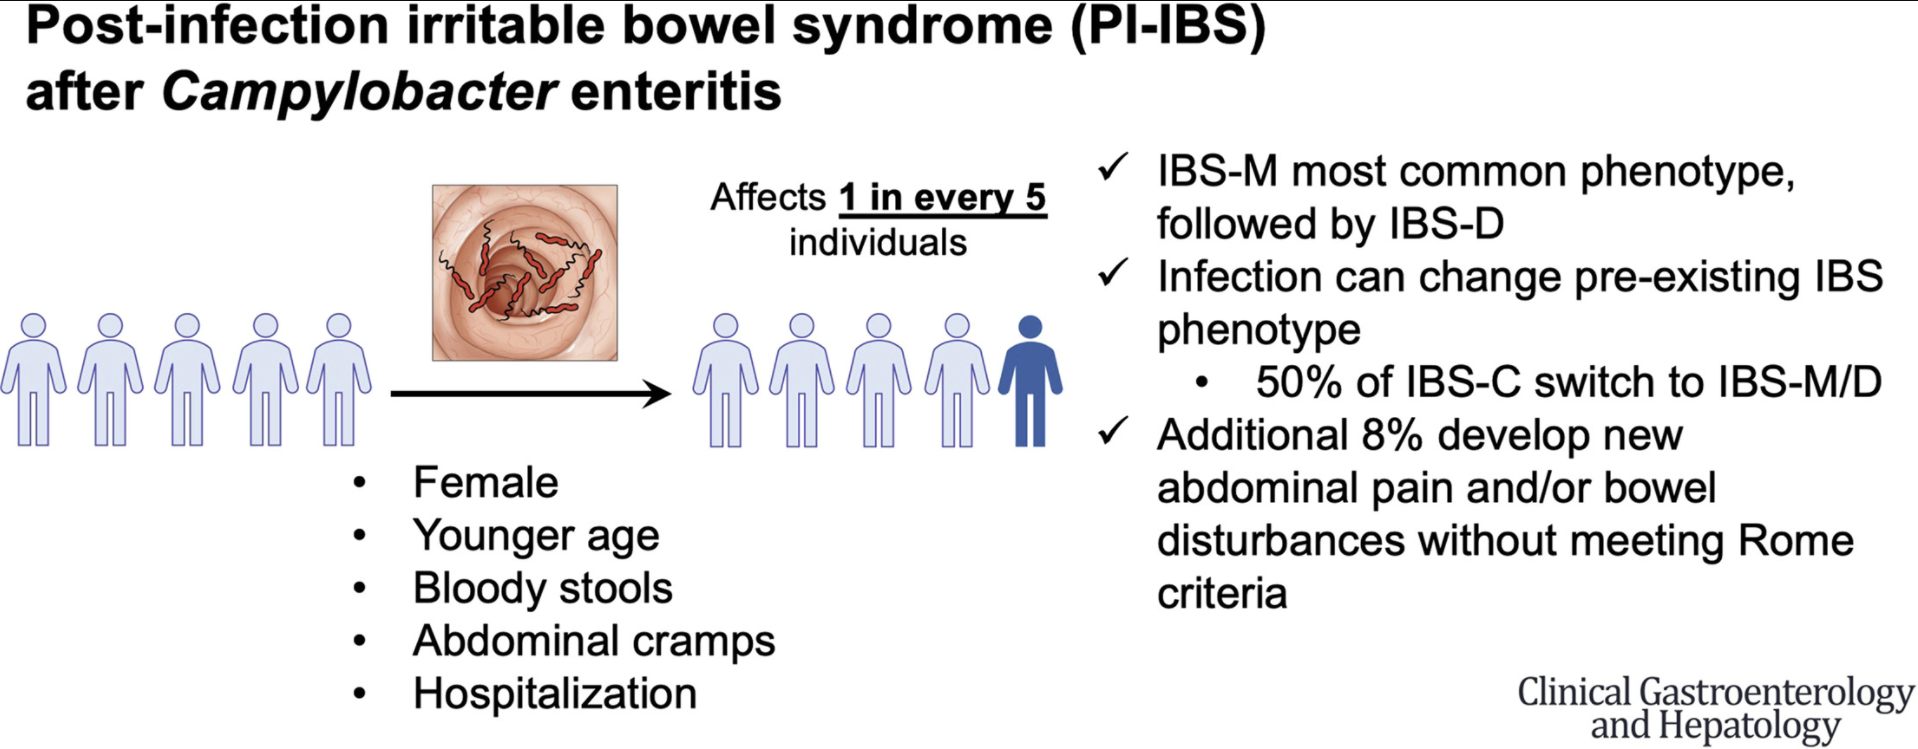
A Berumen et al. Clin Gastroenterol Hepatol 2021; 19: 1855-1863. Characteristics and Risk Factors of Post-Infection Irritable Bowel Syndrome (IBS) After Campylobacter Enteritis

The Minnesota Department of Health collects data on symptoms and exposures upon notification of Campylobacter cases. In this 6-9 month followup survey of 1667 (2011-2019) out of a total of 3586 patients, the authors identified 1418 without preexisting IBS.

Key findings:

  • 301 (21%) subsequently developed IBS. Most of these individuals had IBS-mixed (54%), followed by IBS-diarrhea (38%), and IBS-constipation (6%)
  • Additionally, the authors note that 121 patients (8.5%) had new GI problems after infection that did not meet thresholds set by Rome criteria
  • Among patients with IBS-mixed or IBS-diarrhea before infection, 78% retained their subtypes after infection. In contrast, only 50% of patients with IBS-constipation retained that subtype after infection;40% transitioned to IBS-mixed
  • Of patients with pre-existing IBS, 38% had increased frequency of abdominal pain after Campylobacter infection
  • One limitation of the study is ‘responder bias.’ There may be a lower rate of IBS/GI symptoms in the subset of patients who did not respond to survey.

My take: A lot of people develop IBS and other GI symptoms after Campylobacter infection; those with IBS often have intensification of their symptoms.

Related blog posts:

Related study: Am J Gastroenterol  2012 Jun;107(6):891-9. “Norovirus GE leads to the development of PI-IBS in a substantial proportion of patients (13%), similar to that reported after bacterial GE.”

Nutritional Management of Intestinal Failure in Pediatrics

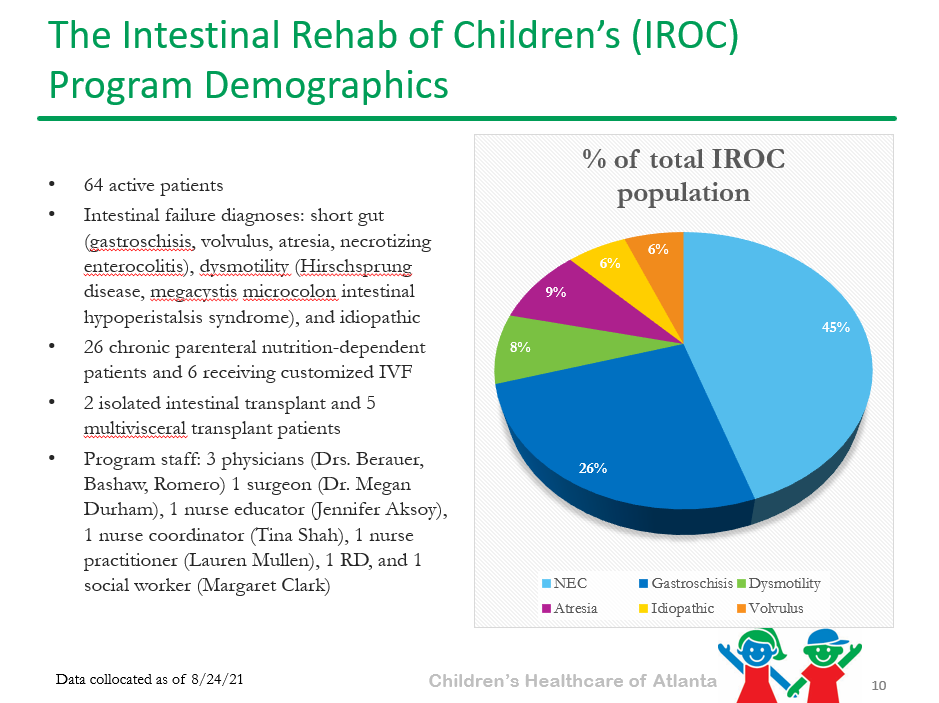
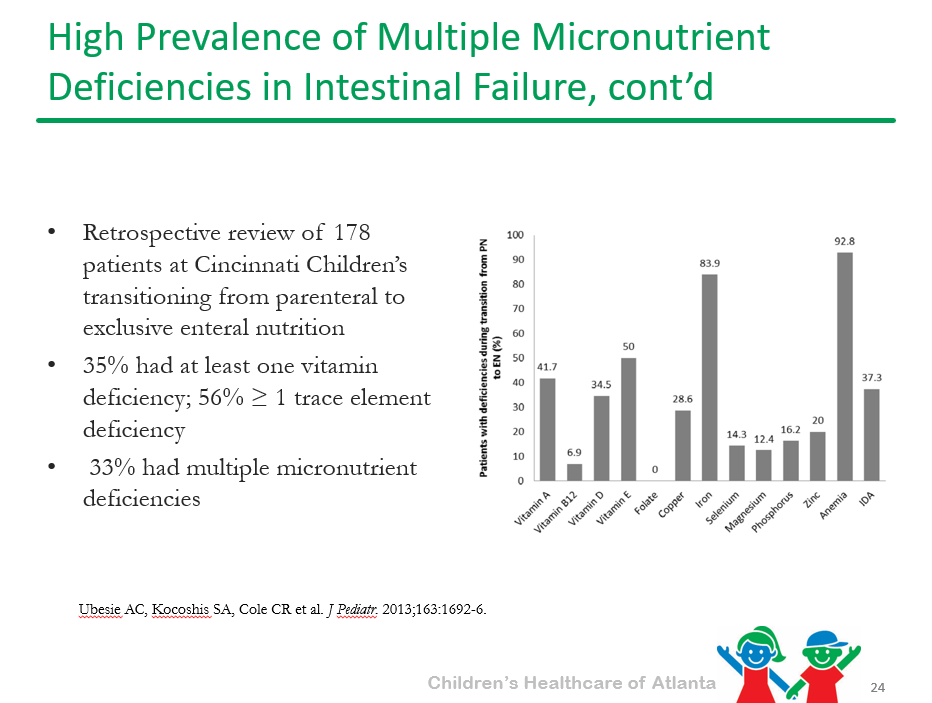
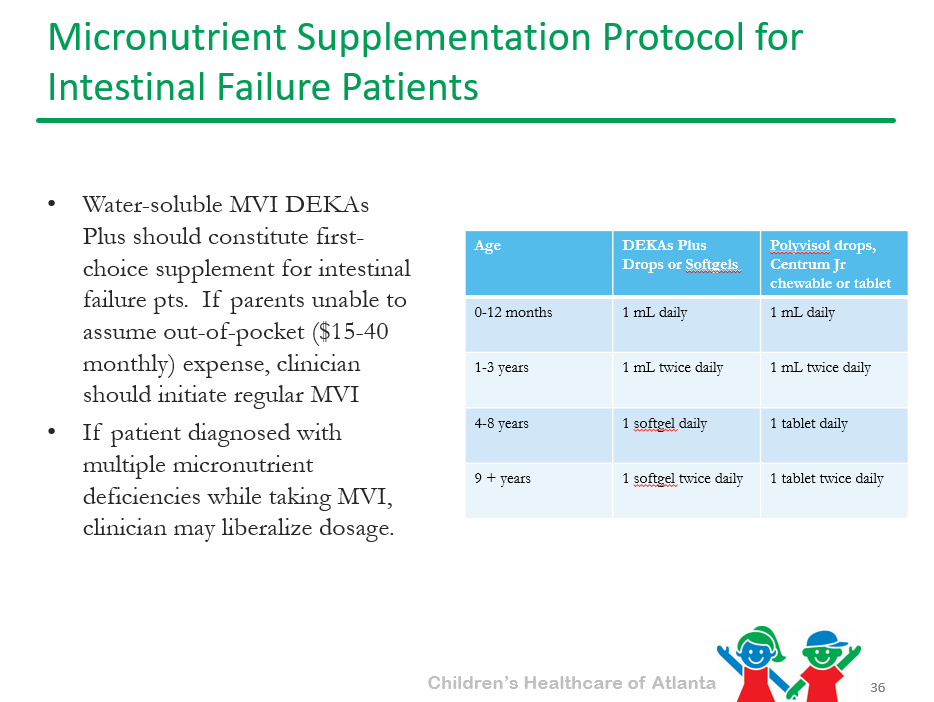
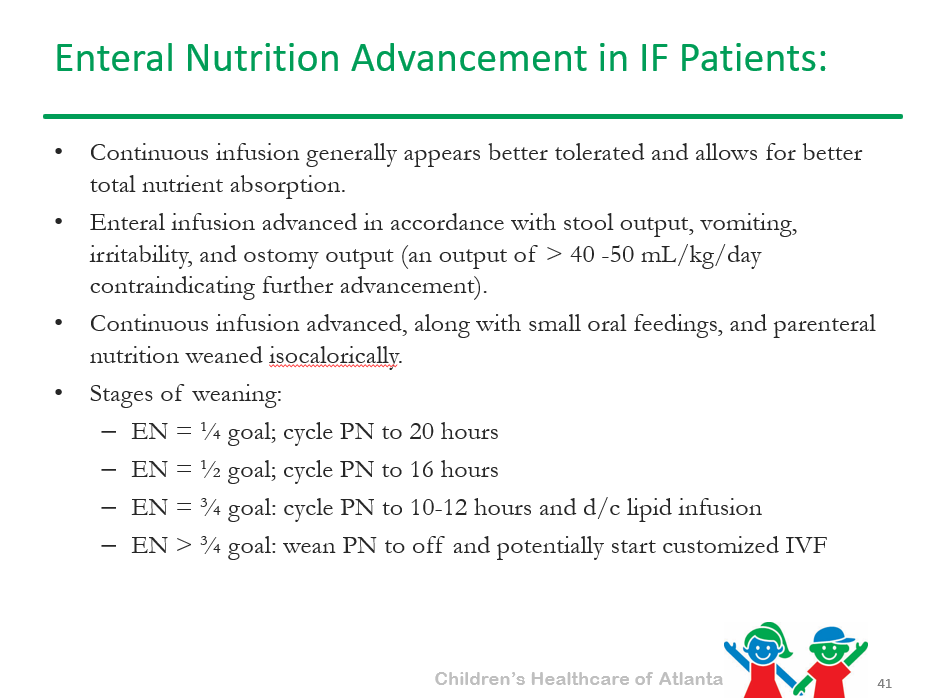
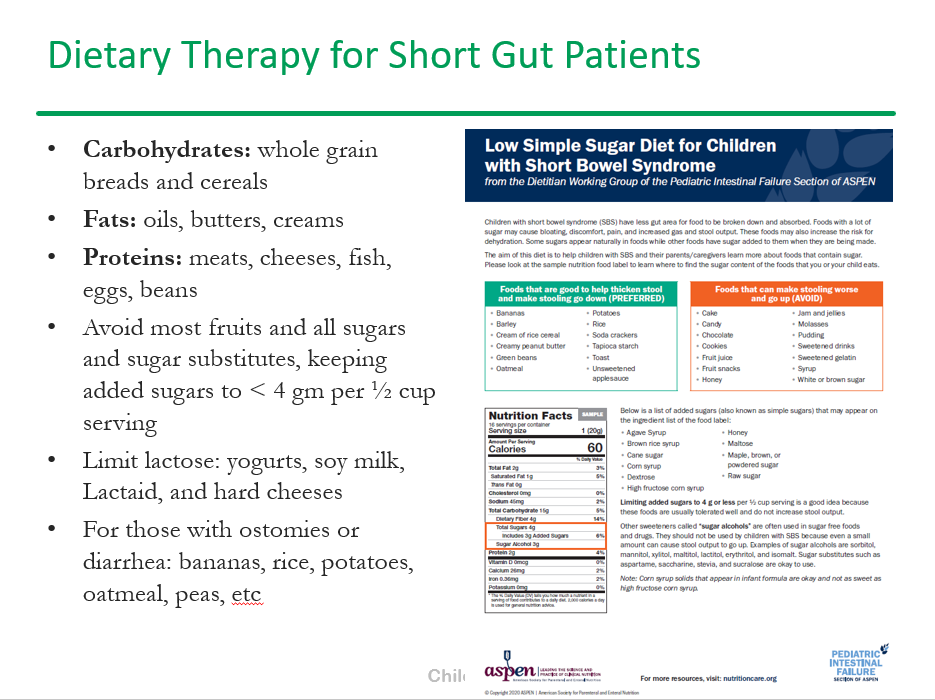
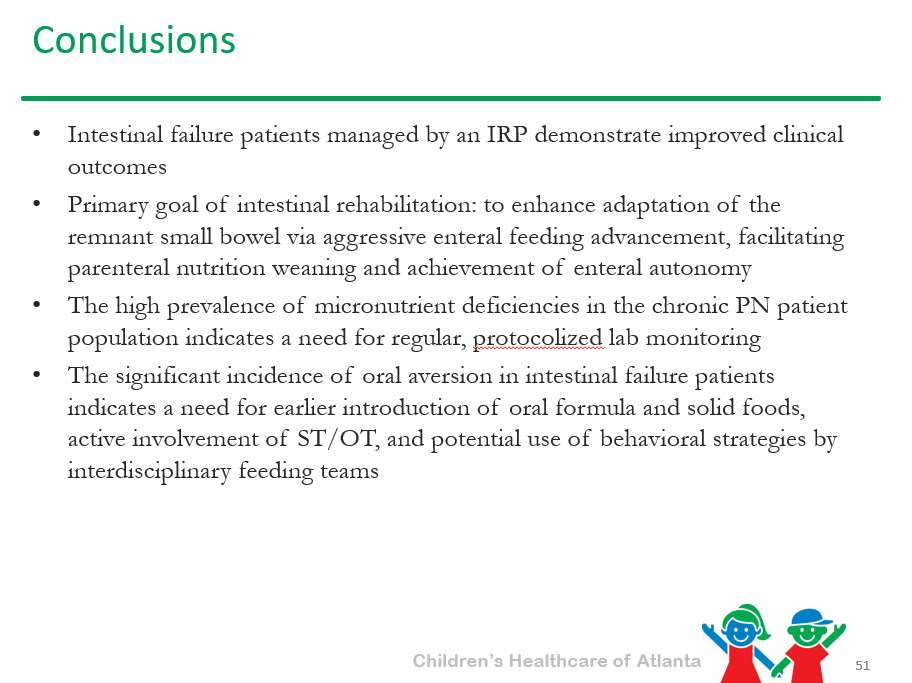
A recent terrific update from Kipp Ellsworth: Nutritional Management of Intestinal Failure Patients. Slides:

Some selected slides:

Related blog posts for Short Bowel Syndrome:

It Hurts Here and Here and Here

A recent study (below) reminded me of a joke. First the joke (better with the visual effect):

A guy goes to his doctor. The patient says, “Doctor when I touch here on my shoulder (with index finger) it hurts, when I touch here on my leg (with index finger) it hurts, and when I touch here on my stomach (with index finger) it hurts.”

The doctor says: “Your finger is broken.”

BP Chumpitazi et al. J Pediatr 2021; 236; 131-136. Multisite Pain Is Highly Prevalent in Children with Functional Abdominal Pain Disorders and Is Associated with Increased Morbidity

In this cross-sectional study of 7-17 year olds (n=406) with Rome III functional abdominal pain disorder (FAPD), the authors examined the frequency of pain outside GI tract over a 2 week study period. Patients were recruited from both a large academic pediatric GI practice and general pediatric offices in same hospital system.

Key findings:

  • In total, 295 (73%) children endorsed at least 1 co-occurring nonabdominal pain, thus, were categorized as having multisite pain with the following symptoms: 172 (42%) headaches, 143 (35%) chest pain, 134 (33%) muscle soreness, 110 (27%) back pain, 94 (23%) joint pain, and 87 (21%) extremity (arms and legs) pain
  • In addition, 200 children (49%) endorsed 2 or more nonabdominal pain symptoms
  • Participants with (vs without) multisite pain had significantly higher abdominal pain frequency (P < .001) and severity (P = .03), anxiety (P < .001), and depression (P < .001). Similarly, children with multisite pain (vs without) had significantly worse functional disability (P < .001) and health-related quality of life scores (P < .001).

The authors note that due to the design of their study, they cannot establish a causal association between pain symptoms and psychosocial functioning.

My take: A lot of kids with stomach pain have multisite pain as well as anxiety and depression. This study reminds us to ask about them.

Related blog posts:

More Pictures From Atlanta Beltline West End

Latest on VTE in Pediatric IBD

MA Aardoom et al. JCC 2021; https://doi.org/10.1093/ecco-jcc/jjab171 The incidence and characteristics of venous thromboembolisms in paediatric-onset inflammatory bowel disease; a prospective international cohort study based on the PIBD-SETQuality Safety Registry

Design: 2016-2020: paediatric gastroenterologists prospectively replied to the international Safety Registry, monthly indicating whether they had observed a VTE case in a patient <19 years with IBD. n=24,802 PIBD patients

Key findings:

  • Twenty cases of VTE were identified (30% Crohn’s disease)
  • The VTE incidence was 3.72 [95%CI 2.27 – 5.74] per 10,000 person-years, 14-fold higher than in the general pediatric population (0.27 [95%CI 0.18-0.38], p<0.001)
  • All but one patient had active IBD, 45% were using steroids and 45% hospitalized.
  • Cerebral sinus venous thrombosis was most frequently reported (50%) VTE

My take: The absolute risk of VTE is low in the pediatric population. In those with active disease, the presence of CVC and use of steroids are known risk factors and require consideration of, at minimum, nonpharmacologic interventions.

Related blog posts:

Clever Study to Assess Utility of TTG IgA For Monitoring Response to a Gluten-Free Diet

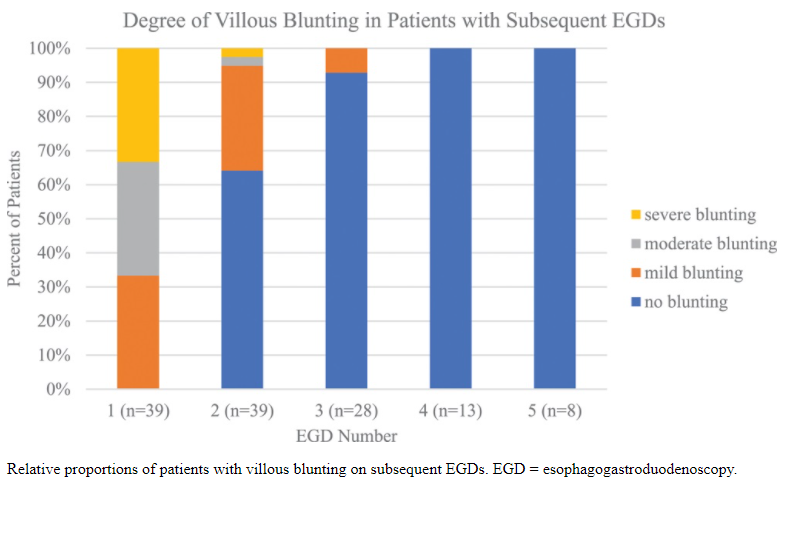
K Payne et al. JPGN Reports: 2021; August 2021 – Volume 2 – Issue 3 – p e097. Open Access Repeat Biopsy to Assess Duodenal Healing in Children With Celiac Disease and Eosinophilic Gastrointestinal Disorders

Background: “Current standard of care in the management of uncomplicated CD is not to undergo multiple esophagogastroduodenoscopies (EGDs)…  In this study, patients with both CD and eosinophilic gastrointestinal disorders (EGID) …) were identified to explore [the mucosal response to a gluten-free diet], as it is standard for patients with EGID to undergo repeat EGDs for disease surveillance.”

Key findings in this retrospective study from CHOP:

  • At second biopsy, 44% (17/39) of patients showed no histologic evidence of active CD and 36% (14/39) of patients had negative tTG-IgA values
  • 9/15 (60%) of patients with no evidence of CD on biopsy had abnormal tTG-IgA levels
  • 8/14 (57%) of patients with normal tTG-IgA levels had evidence of active disease on biopsy
  • Among the 18 who had been on a GFD for at least 2 years, 94% (17/18) had normal duodenal biopsies after 2 years, and 83% (15/18) had normal tTG-IgA values after 2 years
  • Of the patients with elevated tTG-IgA and normal duodenal biopsies, 66% (6/9) had inflammation elsewhere in the upper gastrointestinal tract, including 4 patients with active EOE and 2 patients with gastritis

My take: This study confirms that tTG-IgA levels are not optimal for monitoring. Current guidelines recognize this and recommend repeat biopsy in patients with persistent or relapsing symptoms even with negative serology

Related blog posts:

Biologic Treatment Effectiveness for Esophageal Crohn’s Disease

J Lui et al. Inflamm Bowel Dis 2021; 27: 1544-1547. The Use of Biologics for the Treatment of Esophageal Crohn Disease

In this retrospective review (1998-2018), the authors identified 39 patients with esophageal Crohn disease (ECD) who met inclusion criteria.

Key findings:

  • 35 (92%) had a clinical response to treatment and 21 (55%) went into clinical remission
  • ECD seems to be associated with more disabling intestinal CD phenotypes. Of the 39 patients, 10 (26%) had stricturing phenotype and 21 (54%) had penetrating phenotype; 19 (49%) had perianal disease
  • “Initial treatment after diagnosis with anti-TNFalpha agents compared to other biologics was associated with greater improvement in clinical (97% vs 71%; P=0.02) and endoscopic response (95% vs. 40%; P<0.01) and in clinical remission (64.5% vs. 14.2%; P=0.01).”
  • Initial treatment with an anti-TNFalpha agent was initial treatment in 18 patients with ECD; 14 had an inflammatory, 3 had a stricturing, and 1 had a fistulizing phenotype.

While this study showed better response to anti-TNFalpha agents compared to other biologics (eg. anti-IL-12/IL-23 agents), this may be due to a selection bias as other biologics are often used as a second-line treatment and are selected more often in refractory disease.

My take: Esophageal Crohn’s disease is a rare diagnosis and appears associated with more severe disease.

Chesapeake and Ohio Canal National Historic Park (near Washington D.C.)

Accolades: Bess Schoen

I want to recognize Dr. Bess Schoen. Bess is a colleague at Emory. I met her when I was a 4th year medical student. Since we work at different hospitals, I do not see her often but greatly respect her and her work.

From one of my colleagues, Tanya Hofmekler:

This month, we are celebrating Dr. Bess Schoen’s retirement and her long career in academic medicine.  She will be greatly missed.  Dr. Schoen has always modeled the best characteristics of a well-rounded academic physician. On top of those, she is smart, an excellent teacher and is an overall wonderful person.  She has trained and impacted many residents and fellows that have passed through Emory.  Her trainees walk away with practical medical knowledge and an example of compassionate care.  As one of her trainees, I find myself from time to time asking: “What would Dr. Schoen do?”

Dr. Schoen has also dedicated herself to improve the care of pediatric patients with Inflammatory Bowel Disease through her leadership of Improve Care Now at Emory.  This year, she will be honored by the Crohn’s and Colitis Foundation of America for her commitment and passion.

Disparity in the Care of Black Inflammatory Bowel Disease Patients

J Liu. Inflamm Bowel Dis 2021; 27: 1548-1549. Disparity in the Care of Black Inflammatory Bowel Disease Patients

This first-hand account of the challenges of IBD care for black patients comes from the first IBD specialist recruited to Grady Hospital (Atlanta) which has a predominantly Black patient population.

Key points:

  • “The clinical, endoscopic, and histologic end points…on treatment in this patient population are all largely unknown…Black people account for 13% of the U.S. population but only 1% of the patients in nearly 200 outcome-based IBD studies [and] less than 5% of the patients participating in clinical trials of IBD therapeutics.” This is important as “we just do not know how they work for Black people.” Treatment response could be much worse (author notes that prior treatments for Hepatitis C were much less effective in Black patients).
  • Yet, “the most severe forms of Crohn’s –peri-anal and fistulizing disease– are more common in Black patients.”
  • Review of emergency visits of IBD children “showed that Black children received less medication and had more repeat emergency room visits than white children.” (Inflamm Bowel Dis 2019; 25: 194-203)
  • Because IBD is not perceived to occur frequently in Black patients, the author states that some patients are not accommodated by their employers and patients are less comfortable with support groups.
  • “However, the incidence of Crohn’s disease …in Black people has risen sharply over the past 3 decades…now approaches that of non-Hispanic whites.”

My take: Inflammatory bowel disease is definitely a disease that affects Black people; it is often more severe and requires careful treatment.

Billy Goat Trail, Chesapeake and Ohio Canal National Historic Park
(outside Washington D.C.). Yes, we made it to the top!