Reappraisal of the Risk of Autoimmune Disease with Celiac, Plus One

Using a matched cohort design with 1215 cases of celiac disease and 6075 controls, C Canova and colleagues (J Pediatric 2016; 174: 146-52) provide data from 1989-2011 regarding the development of hypothyroidism and diabetes.  This retrospective, longitudinal, population-based Italian study relied on data from the integrated National Health Service.

Key findings:

  • Over this >20 year period, the risk of developing hypothyroidism was HR 4.64 and the risk of developing type 1 diabetes mellitus was HR 2.50 (not statistically significant)
  • The risk of hypothyroidism was more prevalent in males with HR 20.00.

The authors note: “The most plausible mechanism explaining the association between CD and T1DM/ATD [autoimmune thyroid disease] is a shared genetic background.”

Also noted: NASPGHAN Clinical Report on the Diagnosis and Treatment of Gluten-related Disorders. ID Hill et al. JPGN 2016; 63L 156-63.  Recommended monitoring for celiac disease, from Table 5:

  • At diagnosis: CD serology, CBC, Iron profile, HFP, Thyroid tests (TSH, free T4), Calcium, Vit D.
  • At 3-6 mo after diagnosis: CD serology (TTG IgA or DGP-IgG)
  • Annually:  CD serology, CBC, Thyroid tests (TSH, free T4), Vit D.

Related blog posts:

Congaree National Park (SC) and the "knees" of the Bald Cypress trees

Congaree National Park (SC) and the “knees” of the Bald Cypress trees

Fecal Calprotectin Monitoring Helpful at Identifying Relapse in IBD

Thanks to Ben Gold for this reference: Y. Zhulina et al. Aliment Pharm Ther 2016; 44: 495-504.

Methods: 

  • Patients aged 18 years or older, with a known diagnosis of IBD in clinical remission, were prospectively studied. Patients provided faecal samples every third month and were prospectively followed until the first clinical relapse or the end of the 2-year follow-up period.  
  • Relapse was defined as increasing symptoms necessitating intensified medical therapy or surgery.

Key finding:

  • Among 104 patients, Crohn’s disease (n = 49) and ulcerative colitis (n = 55), 37 had a relapse. A doubling of faecal calprotectin level between two consecutively collected samples was associated with a 101% increased risk of relapse (HR: 2.01; 95% CI: 1.53–2.65; P < 0.001).

My take: Another study showing that stool calprotectin is quite useful. How long will it be until I will not need to write letters to insurance companies to get this test covered?

Also noted in the same issue: 
“The safety of autologous and metabolically fit bone marrow mesenchymal stromal cells in medically refractory Crohn’s disease – a phase 1 trial with three doses” (pages 471–481) T. Dhere, I. Copland, M. Garcia, K. Y. Chiang, R. Chinnadurai, M. Prasad, J. Galipeau and S. Kugathasan. Aliment Pharm Ther 2016; 44: 471-81. This study examined the use of mesenchymal stromal cells in 12 patients.

In conclusion, a single infusion of fresh autologous bone marrow-derived mesenchymal stromal cells propagated ex vivo using a non xenogeneic human platelet lysate growth supplement at doses ranging 2–10 million cell/kg BW was well tolerated in patients with medically refractory moderate to severe Crohn’s disease in this preliminary study. Our data neither addressed long-term safety nor sustained efficacy. However, this study informs that a future phase 2 study 

A previous study of mesenchymal stromal cells was briefly discussed in a previous blog: Sanjay Gupta is Wrong…about Stem Cell Therapy

Related blog posts:

Hidden Lake at Glacier National Park

Hidden Lake at Glacier National Park

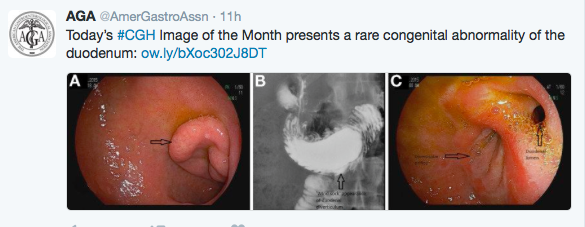
Image from CGH: Duodenal Diverticulum

Clin Gastroenterol Hepatol 2016; 14: e93

DOI: http://dx.doi.org/10.1016/j.cgh.2015.12.035

Intraluminal duodenal diverticulum is a rare duodenal congenital abnormality caused by an anomalous process of recanalization of the primitive foregut. It has a characteristic radiographic appearance on contrast studies, resembling a “windsock web” or “thumb of a glove”

Screen Shot 2016-07-29 at 10.30.28 PM

An upper gastrointestinal (GI) endoscopy was then performed that revealed a 3-cm pedunculated mass in the second part of the duodenum that was biopsied (Figure A), and the patient was referred for an endoscopic ultrasound. A repeat endoscopy before the endoscopic ultrasound revealed a large intraluminal diverticulum that had the appearance of a mass when inverted. Subsequently (Figure B), an upper GI series was performed that showed a large elongated tubular diverticulum arising from the second portion of the duodenum, 2.5 × 12 cm in size, with rapid filling and peristalsis with oral contrast, which extended to the left aspect of the spine when maximally distended

How often are acid blockers used in neonates?

A recent study (JL Slaughter et al. J Pediatric 2016l 174: 63-70) shows a high rate of acid blockers in neonatal intensive care units.  This study retrospectively analyzed the Pediatric Health Information System database (PHIS) from 2006-2013.

  • Of 122,0002 infants: 23.8% received either a histamine-2-receptor antagonist (H2RA) or proton pump inhibitor (PPI).
  • 19.0% had received an H2RA
  • 10.5% had received a PPI

My take (borrowed from authors): “despite limited evidence and  increasing safety concerns, H2RAs/PPIs are frequently prescribed to extremely preterm neonates…Our findings support the need for innovative studies.”  Wouldn’t it be nice if there was proof of efficacy in this population?

Vickery Creek, Roswell

Vickery Creek, Roswell

“Explain It To Me Like I’m a Six Year Old”

Sometimes when I read an article, I wish it was presented in a much simpler manner.  In the movie “Philadelphia,” the lawyer played by Denzel Washington tells his clients to “explain it to me like I’m a six-year-old.”

A recent clinical report (MI Ardura et al. JPGN 2016; 63: 130-55) probably would have benefitted from this idea to some degree.  This report examines infectious disease issues with regard to patients receiving tumor necrosis factor-α (TNFα) inhibitors.  All in all, it is very thorough and reviews more than 20 infectious agents (bacteria, fungi, mycobacteria, and viral agents).

Table 2 is most helpful.  In this table, the authors recommend that before starting TNF inhibitors:

  • Risk factor screening for Brucella (eg exposure to animals, unpasteurized dairy products), Bartonella (eg exposure to kitten), Listeria (eg dietary history), Salmonella (eg exposure to reptiles), Aspergillus (eg exposure to construction), coccidioidomycosis (exposure to endemic area), Histoplasma (long list of exposures listed in Table 3 includes barns, caves, chicken coops, old buildings), and Hepatitis C virus
  • Direct testing is recommended for Mycobacterium tuberculosis, Hepatitis B virus, HIV (≥ 13 yrs if in hospital or ≥15 years), and Varicella zoster virus

Table 4 lists recommended vaccines.  For live virus vaccines, the authors recommend to avoid unless they can be administered at least 4 weeks prior to immunosuppressive therapy.

Other useful information:

  • “Granulomatous infections caused by bacteria, mycobacteria, and fungi are the most frequently  described infections in patients receiving anti-TNFα therapies.”
  • Infection rates of 239/100,000 reported with infliximab between 1998-2002.
  • More than 70% of these infections occurred within 3 to 6 months of starting infliximab therapy, “suggesting the possibility of reactivation of latent infection.”
  • M tuberculosis was most common (54/100,000)
  • “In general, anti-TNFα therapy should be discontinued during any severe infection.”

My take: This report offers a lot of information. Its impact on daily practice would be much greater if the authors created a simple one-sheet screening questionnaire form with recommended bloodwork and vaccines.

Related blog posts:

Shem Creek Pelican Art

Shem Creek Pelican Art

Pediatric Nutritionist/Scott Pentiuk: Update on two topics: Blenderized diets and Eosinophilic Esophagitis

From the Pediatric Nutritionist blog –two lectures from Dr. Scott Pentiuk:

Two Lectures: Blenderized diets and Eosinophilic esophagitis

These lectures feature a lot of useful references and practical advice.

Related blog posts:

Shem Creek, SC

Shem Creek, SC


One Day Polyethylene Glycol 3350 Prep

A recent study (B Sahn et al. JPGN 2016; 63: 19-24) with 155 patients prospectively showed that a 1-day polyethylene glycol (PEG) 3350 prep was safe and fairly effective.

The prep: 4 g/kg PEG in children with weights 10-50 kg and (with 238 gm for those >50 kg along with a single dose of a stimulant: either bisacodyl 5 mg-15 mg orally (10 mg for 21-30 kg) or senna (17.6 mg for 20 kg, 26.4 mg for 21-30 kg, and 52.8 mg for >31 kg).  The PEG was mixed typically with a sports drink to a max of 64 oz.

Key findings:

  • Hypokalemia was noted in 37 (24%) but none lower than 3.3 mmil/L.
  • Hypoglycemia was identified in 5 (3 were younger than 7). The one patient with severe hypoglycemia (31 mg/dL) was a one-year-old with corticosteroid dependency and had missed his morning steroid dose.
  • Colon cleansing was excellent or good in 77%.  The authors note that this suboptimal cleansing is due in part to the difficulty of using split-dosing in pediatrics.
  • 3/4ths of patients found the prep to be easy or average to tolerate.

My take: This study validates the common approach of using 1-day PEG 3350 preps in children.  Due to the low risk of hypoglycemia, particularly in young children, and the frequent mild hypokalemia, some children may benefit from starting intravenous fluids prior to induction of anesthesia.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Arthur Ravenel Jr Bridge

Arthur Ravenel Jr Bridge


Quadruple Therapy for Helicobacter Pylori Favored in Toronto Guidelines

Toronto consensus guidelines (C Fallone et al. Gastroenterol 2016l 151: 51-69) for H pylori treatment in adults emphasize use of 14 day therapy and use of quadruple regimens.  Specific recommendations included the following:

  • PAMC: PPI/amoxicillin/metronidazole/clarithromycin OR
  • PBMT: PPI/bismuth/metronidazole/tetracycline

Full text link: Toronto Consensus for the Treatment of H Pylori

Abstract:

Background & Aims

Helicobacter pylori infection is increasingly difficult to treat. The purpose of these consensus statements is to provide a review of the literature and specific, updated recommendations for eradication therapy in adults.

Methods

A systematic literature search identified studies on H pylori treatment. The quality of evidence and strength of recommendations were rated according to the Grading of Recommendation Assessment, Development and Evaluation (GRADE) approach. Statements were developed through an online platform, finalized, and voted on by an international working group of specialists chosen by the Canadian Association of Gastroenterology.

Results

Because of increasing failure of therapy, the consensus group strongly recommends that all H pylorieradication regimens now be given for 14 days. Recommended first-line strategies include concomitant nonbismuth quadruple therapy (proton pump inhibitor [PPI] + amoxicillin + metronidazole + clarithromycin [PAMC]) and traditional bismuth quadruple therapy (PPI + bismuth + metronidazole + tetracycline [PBMT]). PPI triple therapy (PPI + clarithromycin + either amoxicillin or metronidazole) is restricted to areas with known low clarithromycin resistance or high eradication success with these regimens. Recommended rescue therapies include PBMT and levofloxacin-containing therapy (PPI + amoxicillin + levofloxacin). Rifabutin regimens should be restricted to patients who have failed to respond to at least 3 prior options.

Conclusions

Optimal treatment of H pylori infection requires careful attention to local antibiotic resistance and eradication patterns. The quadruple therapies PAMC or PBMT should play a more prominent role in eradication of H pylori infection, and all treatments should be given for 14 days.

Related blog posts:

Sullivan's Island, Low Tide

Sullivan’s Island, Low Tide

One Proposal to Reduce Thiopurine Combination Therapy

A recent review (X Roblin et al. Inflamm Bowel Dis 2016; 22: 1496-1501) provided a useful review of thiopurine/biologic combination therapy.  The part of this review that I found intriguing was their Figure 3: “Proposed algorithm that may guide drug discontinuation or de-escalation in patients with IBD who achieved sustained deep remission while on combination therapy.”

  • In those (in sustained deep remission) with an infliximab trough level >5 mcg/mL, this algorithm recommends discontinuation of thiopurine.
  • In those with an infliximab trough level 3-5 mcg/mL and with 6-TGN >250, this algorithm recommends reduction of thiopurine to obtain 6-TGN level >125.
  • In those with an infliximab trough level <2 mcg/mL and with 6-TGN >250, this algorithm recommends discuss stopping infliximab.

The authors acknowledge that this algorithm has not been studied and “needs to be investigated in prospective trials specifically addressing this issue.”

My take: Until more studies emerge, the best way to balance control of IBD and minimize drug toxicity remains uncertain.

Unrelated references:

  • “Crohn’s disease of the ileoanal pouch” AL Lightner et al. Inflamm Bowel Dis 2016; 22: 1502-8.
  • SZ Koh et al. Inflamm Bowel Dis 2016; 22: 1397-1402. This reference describes clinical factors associated with development of Crohn’s disease in patients with IBDU who have undergone ileal pouch (e.g. younger age).

Related blog posts:

Arthur Ravenel Jr Bridge

Arthur Ravenel Jr Bridge

Disease extent and need for higher infliximab dosing

A recent study (JM Shapiro et al. JPGN 2016; 62: 867-72) reviewed 98 pediatric patients treated with infliximab (2012-2014) with inflammatory bowel disease (IBD).

The authors divided their patients into three groups, mainly based on extent of colonic involvement.  In those with limited colonic involvement, they were labelled “limited” disease (n=53).  In those with patchy inflammation involving the entire colon, they were considered to have “moderate” disease (n=27).  In contrast, those with continuous pancolitis were ascribed to have “extensive” disease (n=18).  Overall, Crohn’s disease accounted for 85 patients (87%),  ulcerative colitis for 11 patients (11%), IBDU for 2 patients (2%).  Interestingly, the majority (9 of 11) of those patients without Crohn’s disease were considered to have extensive disease.

Key findings:

  • “Patients with moderate and extensive disease, started taking 5 mg/kg per dose, showed statistically significant shorter times to escalation that those with limited disease.”
  • 70% of those with extensive disease required dose escalation, compared with 58.3% of those with moderate disease and 26.4% of those with limited disease.
  • The authors note that patients (n=8) with extensive disease who started with 10 mg/kg dosing  “exhibited longer treatment durability;” all 8 patients who started on 10 mg/kg dosing remained on this dose at the study’s conclusion.  Among the 10 patients that started on 5 mg/kg dosing, only 7 were on IFX therapy at the study conclusion–3 remained on 5 mg/kg, 4 were escalated to 10 mg/kg; there were 3 patients who stopped IFX therapy (1 infusion reaction, 2 with nonresponse).

My take: This is a small study. Yet, the implication is that early optimal dosing of IFX is likely  helpful, especially in the setting of extensive disease.

Related blog posts:

Chattahoochee River

Chattahoochee River