An Overlooked Finding in a Recent Acute Severe Ulcerative Colitis Study

A recent study (S Choshen et al. JPGN 2016; 63: 58-64) examined 283 children who were treated with IV steroids for acute severe ulcerative colitis.  This study focused on steroid dosing.  Their conclusion: “there does not seem to be a consistent superiority of high dose (>2 mg/kg/day) versus standard (1.25 mg/kg/day) or low-dose (1 mg/kg/day) methylprednisolone in pediatric acute severe colitis.”

Before looking into the details a little closer, one finding that was not even discussed in the abstract or discussion was the colectomy rate of 31%.  Previous pediatric studies of patients with ulcerative colitis had found rates generally half that rate but notably included patients with milder presentations of ulcerative colitis.  Thus, this rate of 31% (by 1 year after discharge) is useful information to reference when considering pediatric patients with acute severe colitis (ACS).

This study used datasets from the prospective Outcome of Steroid therapy in Colitis Individuals (OSCI) (n=128) and from the retrospective OSCI study (n=99).

Other results:

  • By day 5 of steroids, 45% had at most mild disease (ie PUCAI <35)
  • 31% had failed IV steroids and required salvage therapy (biologic or calcineurin inhibitor)
  • 20% had colectomy by discharge
  • When examining steroid dosage and outcomes, the authors could not discern any differences in need for salvage therapy, PUCAI <35 at day 5, or need for salvage therapy within 1 year. There was a mild difference in length of stay with 9 days in the low-dose group and 10-days in the high dose group.

My take: This large cohort provides some reassurance that current steroid dosing recommendations are probably right, in that there was no discernible improvement with higher doses.  This is in agreement with previous studies in adults which have not shown advantages of methylprednisolone >60 mg/day.  The high colectomy rate of 31% is worth keeping in mind in this population.

Related blog posts:

NewAbxDiscovered


Expanding VEO Variants

A recent study (Q Li, CH Lee, LA Peters, et al. Gastroenterol 2016; 150: 1196-1207) provides a description of a new genetic variant causing very early onset inflammatory bowel disease (VEOIBD), which designates cases of IBD which presents <6 years of age.

Using whole exome sequencing, the authors identified TRIM22 mutations in 3 infants with fistulizing perianal disease and granulomatous colitis.  The authors further characterized the defect using functional studies that showed TRIM22 is important in the regulation of nucleotide binding oligomerization domain containing 2 (NOD2)–dependednt activation of interferon-beta signaling and nuclear factor (NF)-κB.

“NOD2 has long been recognized as a critical player in Crohn’s disease pathogenesis, where it is proposed to regulate innate immunity through NF-κB induced proinflammatory responses triggered by peptidoglycan…Simarlarly, mutations in XIAP..are associate with loss of NOD-2-dependent mediated NF-κB signaling” and has a similar phenotype.

My take: Identification of the numerous mutations that lead to VEOIBD is likely to help understand the pathogenesis and ultimately to better therapies.

Related blog posts:

How Much Lower Would The Braves Be Without the Marlins?

How Much Lower Would The Braves Be Without the Marlins?

Outcome with POTS –Better than Expected?

Adolescents with postural orthostatic tachycardia syndrome (POTS) are often seen in pediatric GI offices due to the associated GI symptoms.  A recent report (R Bhatia et al. J Pediatr 2016; 173: 149-53) offers up some encouraging data.

172 patients (of 502) responded to the authors’ survey.  The mean duration since the time of diagnosis was 5.4 years. Key findings:

  • 19% (n=33) reported complete resolution of their symptoms
  • 51% reported improvement, but persistent, symptoms
  • 28% reported intermittent symptoms
  • Thus, 86% reported that their POTS resolved, improved or was intermittent.

The authors note that some symptoms like dizziness and fatigue are common in patients without POTS and that “persistence of some symptoms can be part of a normal healthy life.”

My take: This study indicates that most adolescents with POTS are likely to have a good functional outcome.

Related blog posts:

BryceNat'l Park

Bryce Nat’l Park

Slipping Rib Syndrome

The entity, of “Slipping Rib Syndrome,” which could be mistaken for a gastronomical error at The Boathouse, is also called Cyriax syndrome.  A recent brief report (L Calvete et al. J Pediatric 2016; 172: 216) describes a typical case.  This teenager had a 1-year history of “brief, episodic, sharp upper left abdominal pain, accompanied by a [subtle] chest wall deformity, which started after physical activity.”

Key points:

  • This disorder is most common in middle-aged females but can occur at any age
  • It can result from hyper mobility of the false ribs, allowing “the affected rib to sublet or ‘slip’ under the adjacent rib,..and cause pain
  • The disorder can be elicited with the ‘hooking’ maneuver.  “In this test, the patient lies in the supine position, while the clinician hooks his or her fingers beneath the costal margins of the affected side, displacing them upward and anteriorly pulling gently.  A positive test reproduces pain.”
  • Treatment: avoidance of displacement and mild analgesics

My take: I’ve only seen this condition once but think it is important to consider in patients presenting with intermittent abdominal pain.

Atlanta Zoo 2016

Atlanta Zoo 2016

Ultra-Short Celiac Disease


It is well-recognized that obtaining a duodenal bulb biopsy increases the likelihood of making a diagnosis of celiac disease.  Another study (PD Mooney et al. Gastroenterol 2016; 150: 1125-34) has tried to quantitate the frequency of “ultra-short” celiac disease (USCD).

In this prospective study of 1378 patients (mean age 50.3 yrs) who underwent endoscopy between 2008-2014, there was a cohort who had a high clinical suspicion of celiac disease in which quadrantic biopsies of the duodenal bulb were obtained.

Key findings:

  • 268 (19.4%) were diagnosed with celiac disease
  • 26 (9.7%) of celiac population had disease identified primarily in the duodenal bulb.  These patients with USCD were younger (P=.03), had lower serologic titers of tissue transglutaminase antibody (tTG) (P=.001), and less frequently had diarrhea (P=.001).
  • In USCD, the tTG titers were a median of 4.8x ULN compared with 20x ULN in those with more extensive disease.
  • While the authors characterize 26 as having USCD, 19 of the 26 did have Marsh 1 (n=18, 69.2%) or Marsh 2 (n=1, 3.8%) lesions, indicating at least some involvement more distally. However, in these patients the duodenal bulb findings clinched the diagnosis.

Despite the protocol, the authors showed that a single biopsy from the bulb was sufficient to increase the diagnostic yield.

My take: This study reinforces the need for duodenal biopsies from both the bulb and more distally when the diagnosis of celiac disease is being considered.

Related blog posts:

Last Year at Turner Field

This is the last year at Turner Field

Gastrostomy Tubes: The First 30 Days

A retrospective study (AB Goldin et al. J Pediatric 2016; 174: 139-45) provides a better idea about the likelihood of complications by looking for ED visits and admissions within 30  days of placement.

This study involved 38 Children’s Hospitals and 15,642 patients the Pediatric Health Information System (PHIS) database. Key findings:

  • 8.6% had an ED visit within 30 days
  • 3.9% had an admission within 30 days
  • Common reasons for return visits: infection (27%), mechanical complication (22%) and replacement (19%).

The authors note that risk factors for ED visits and admission were mainly non modifiable like race/ethnicity and medical complexity.  They also note that problems in the early postoperative period are grossly underestimated due to many issues being addressed in the outpatient setting.

This study indicates that there is a tremendous opportunity for improvement.  There is great variation in hospital practices with regard to the type and method of placing gastrostomy tube.  In addition, there is a high variability in the determination of the need for fundoplication which is often undertaken at the time of gastrostomy tube placement.

My take:  Understanding these risks is important to give families accurate information prior to placement of gastrostomy tubes.  In addition, these high rates of complications indicate the need for head-to-head prospective trials comparing types of gastrostomy tube placement and education efforts.

Related blog posts:


betterbirthrate

Lower Teen Birth Rates

teen birth rate

Adverse Events Following Pediatric Endoscopy –Underestimated Previously

A recent study (RE Kramer, MR Narkewicz. JPGN 2016; 62: 828-33) report the frequency of adverse events that occurred within 72 hours in a prospective observational cohort of 9577 patients from a single center.

The authors characterized complications more precisely and identified a much higher rate of complications than what has previously been reported.  Key findings:

  • The overall adverse event rate was 2.6% with 1.7% of all cases requiring unanticipated medical care.
  • Absolute risk of bleeding was 0.11%, infection 0.07%, and perforation 0.1% (n=12).  In total, these standard measures of complications were 0.28%.
  • Advanced and therapeutic cases had much higher rates of adverse events. Perforations occurred after esophageal dilatation (5), esophageal food impaction (1), polypectomy (4), and primary GJ placement (2).
  • Adverse rate with ERCP was 11.54%
  • Adverse rate with PEG was 10.71%
  • Adverse rate with dilatation was 10.94%.  It is noted that a total of 319 dilatations were reviewed.  5 had perforations.
  • Adverse rate with polypectomy was 6.27%.  It is noted that a total of 128 polypectomies were reviewed.  4 had perforations.
  • The authors did not identify a significantly higher complication rate with trainee physicians.

As noted in a previous entry (see below), studies in adults have an estimated a perforation rate of 0.09% and serious complication rates (GI and non-GI complications) of 0.15% for upper endoscopy and of 0.2% for colonoscopy. In addition, a large pediatric study of endoscopies, found a perforation rate of 0.014% for EGDs and 0.028% for colonoscopies. Thus, this report identifies a higher rate (10-fold) of perforation (driven by therapeutic endoscopy) and a much higher rate of adverse events, including 2.08% in diagnostic EGD and 3.9% for diagnostic colonoscopy.  Furthermore, for diagnostic EGD and for diagnostic colonoscopy, grade 2 (needing ER or unanticipated physician evaluation) or higher adverse events occurred in 1.21% and 2.31% respectively.

My take: Using a broader (and more accurate) definition of complications after endoscopy, the authors have demonstrated a much higher rate of adverse events, particularly following dilatation, PEG, polypectomy, and ERCP.  This report indicates that our preop counseling needs to be modified to inform families that complications are not quite so rare.

Related blog post:  High Endoscopy Complication Rate After Intestinal …

Complication -Unrelated to endoscopy:

pontine myelinosis

Soap Suds Enemas & ED Management of Impactions

A recent retrospective single-center study (CE Chumpiitazi et al. JPGN 2016; 63: 15-18) identified 512 patients (8 mo-23 years) who were treated with soap suds enemas (20 mL/kg of water with one packet of castile soap).  Key findings: No serious adverse events were identified. “82% were successfully treated.”

While this large study provides a fair amount of reassurance, the associated editorial (pg 1-2) makes some key points:

  • ED diagnosis of fecal impaction is unreliable.  “Abdominal radiographs are often performed…[but] have shown unsatisfactory sensitivity and specificity.”  In this study, only 38% had reported history of constipation; thus a high number of children developed impactions without prior constipation.  Thus, either many of these children were not impacted or the history was unreliable.
  • “SSEs are likely to be very effective, but so are phosphate enemas and milk and molasses enemas that have fallen out of favor because of safety concerns.”
  • In the editorial, until prospective studies are completed, the authors advocate considering oral PEG (high-dose) or ducosate enemas, normal saline enemas, glycerin enemas, mineral oil enemas, or bisacodyl enemas.

My take: While the editorial makes some valid points, particularly making sure that treatment for an impaction is needed, I think this study provides good preliminary data on the safety of soap suds enemas.  As with all pediatric treatments, more high-quality studies would be welcome.

Related blog posts:

AJC Peachtree Road Race 2016

AJC Peachtree Road Race 2016

Apple Juice for Gastroenteritis

While oral rehydration solutions (ORS) are a major advance, particularly for severe diarrhea, for milder cases diluted apple juice is probably better for most children according to a recent study (Freedman SB et al. Effect of dilute apple juice and preferred fluids vs electrolyte maintenance solution on treatment failure among children with mild gastroenteritis: A randomized clinical trial. JAMA 2016 Apr 30; [e-pub]).  While the balance of sugar and salt in ORS enhance fluid absorption, administration of ORS can be complicated by limited acceptance, especially in children.

From Epocrates Summary:

Juice Is Best for Treating Mild Gastroenteritis with Minimal Dehydration

Dilute apple juice for initial hydration followed by fluids of the child’s choice was superior to electrolyte maintenance solution for treating children with mild gastroenteritis and minimal dehydration…

In a single-blind noninferiority trial, researchers randomized 647 children (aged 6−60 months) presenting to a Canadian pediatric emergency department with gastroenteritis and minimal dehydration to receive either 1) half-strength apple juice for initial hydration followed by fluids of the child’s choice or 2) apple-flavored electrolyte maintenance solution. The primary outcome was treatment failure, defined as occurrence of any of the following within 7 days: intravenous rehydration, hospitalization, unscheduled visit to a physician, treating physician’s request to cross over to other study arm, weight loss ≥3% or Clinical Dehydration Scale score ≥5 at follow-up.

Treatment failure was significantly lower in the juice/preferred fluids group (16.7% vs. 25.0%); the difference met the study’s criteria for noninferiority and superiority. Significantly fewer children in the juice/preferred fluids group received intravenous rehydration at the index visit (0.9% vs. 6.8%) and within 7 days (2.5% vs. 9.0%). Juice/preferred fluids was most beneficial in children ≥24 months of age (treatment failure rate, 9.8% vs. 25.9%).

Related blog posts:

freedom bell

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

How Gut Microbes Could Lead to Atherothrombotic Disease

About three years ago, this blog looked at the link between gut microbes, diet, genes and heart disease (Linking diet, genes, and gut microbes to…heart disease | gutsandgrowth).

A summary of the most recent information on this topic: H Tilg. “A Gut Feeling About Thrombosis” (NEJM 2016; 374: 2494-6).

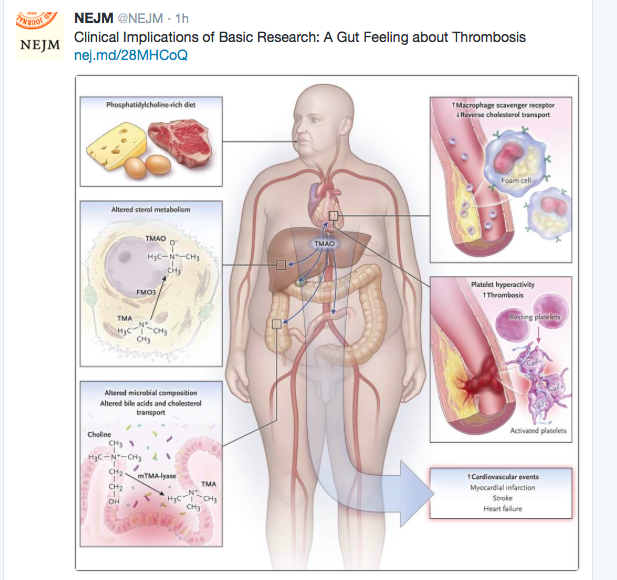
Background: Previous research has shown that certain dietary nutrients that include choline are processed by gut microbes to produce trimethylamine (TMA) which is converted into TMA-N-O (TMAO) by the liver.  Particular foods that have been associated with higher TMAO include meats and eggs.  It has been observed that antibiotics, presumably by their affect on gut microbes, reduce TMAO levels.

What’s new: Zhu et al (Cell 2016; 165: 111-24) “gave mice excess of dietary choline, microbe-generated TMAO enhanced platelet responsiveness in vivo, promoting a prothrombotic phenotype” was blocked by the administration of oral antibiotics.  Fecal microbiota transplantation, however, elevated the risk of thrombosis when administered to germ-free mice.

This data shows more clearly a causal relationship between TMAO and thrombotic mechanisms via platelet activation and a causal relationship between gut microbes and TMAO levels. However, this data does not determine exactly how we should modify our diets and or microbes to achieve improved clinical outcomes.

GutFeelingAbout