Refractory Constipation -Terrific Update

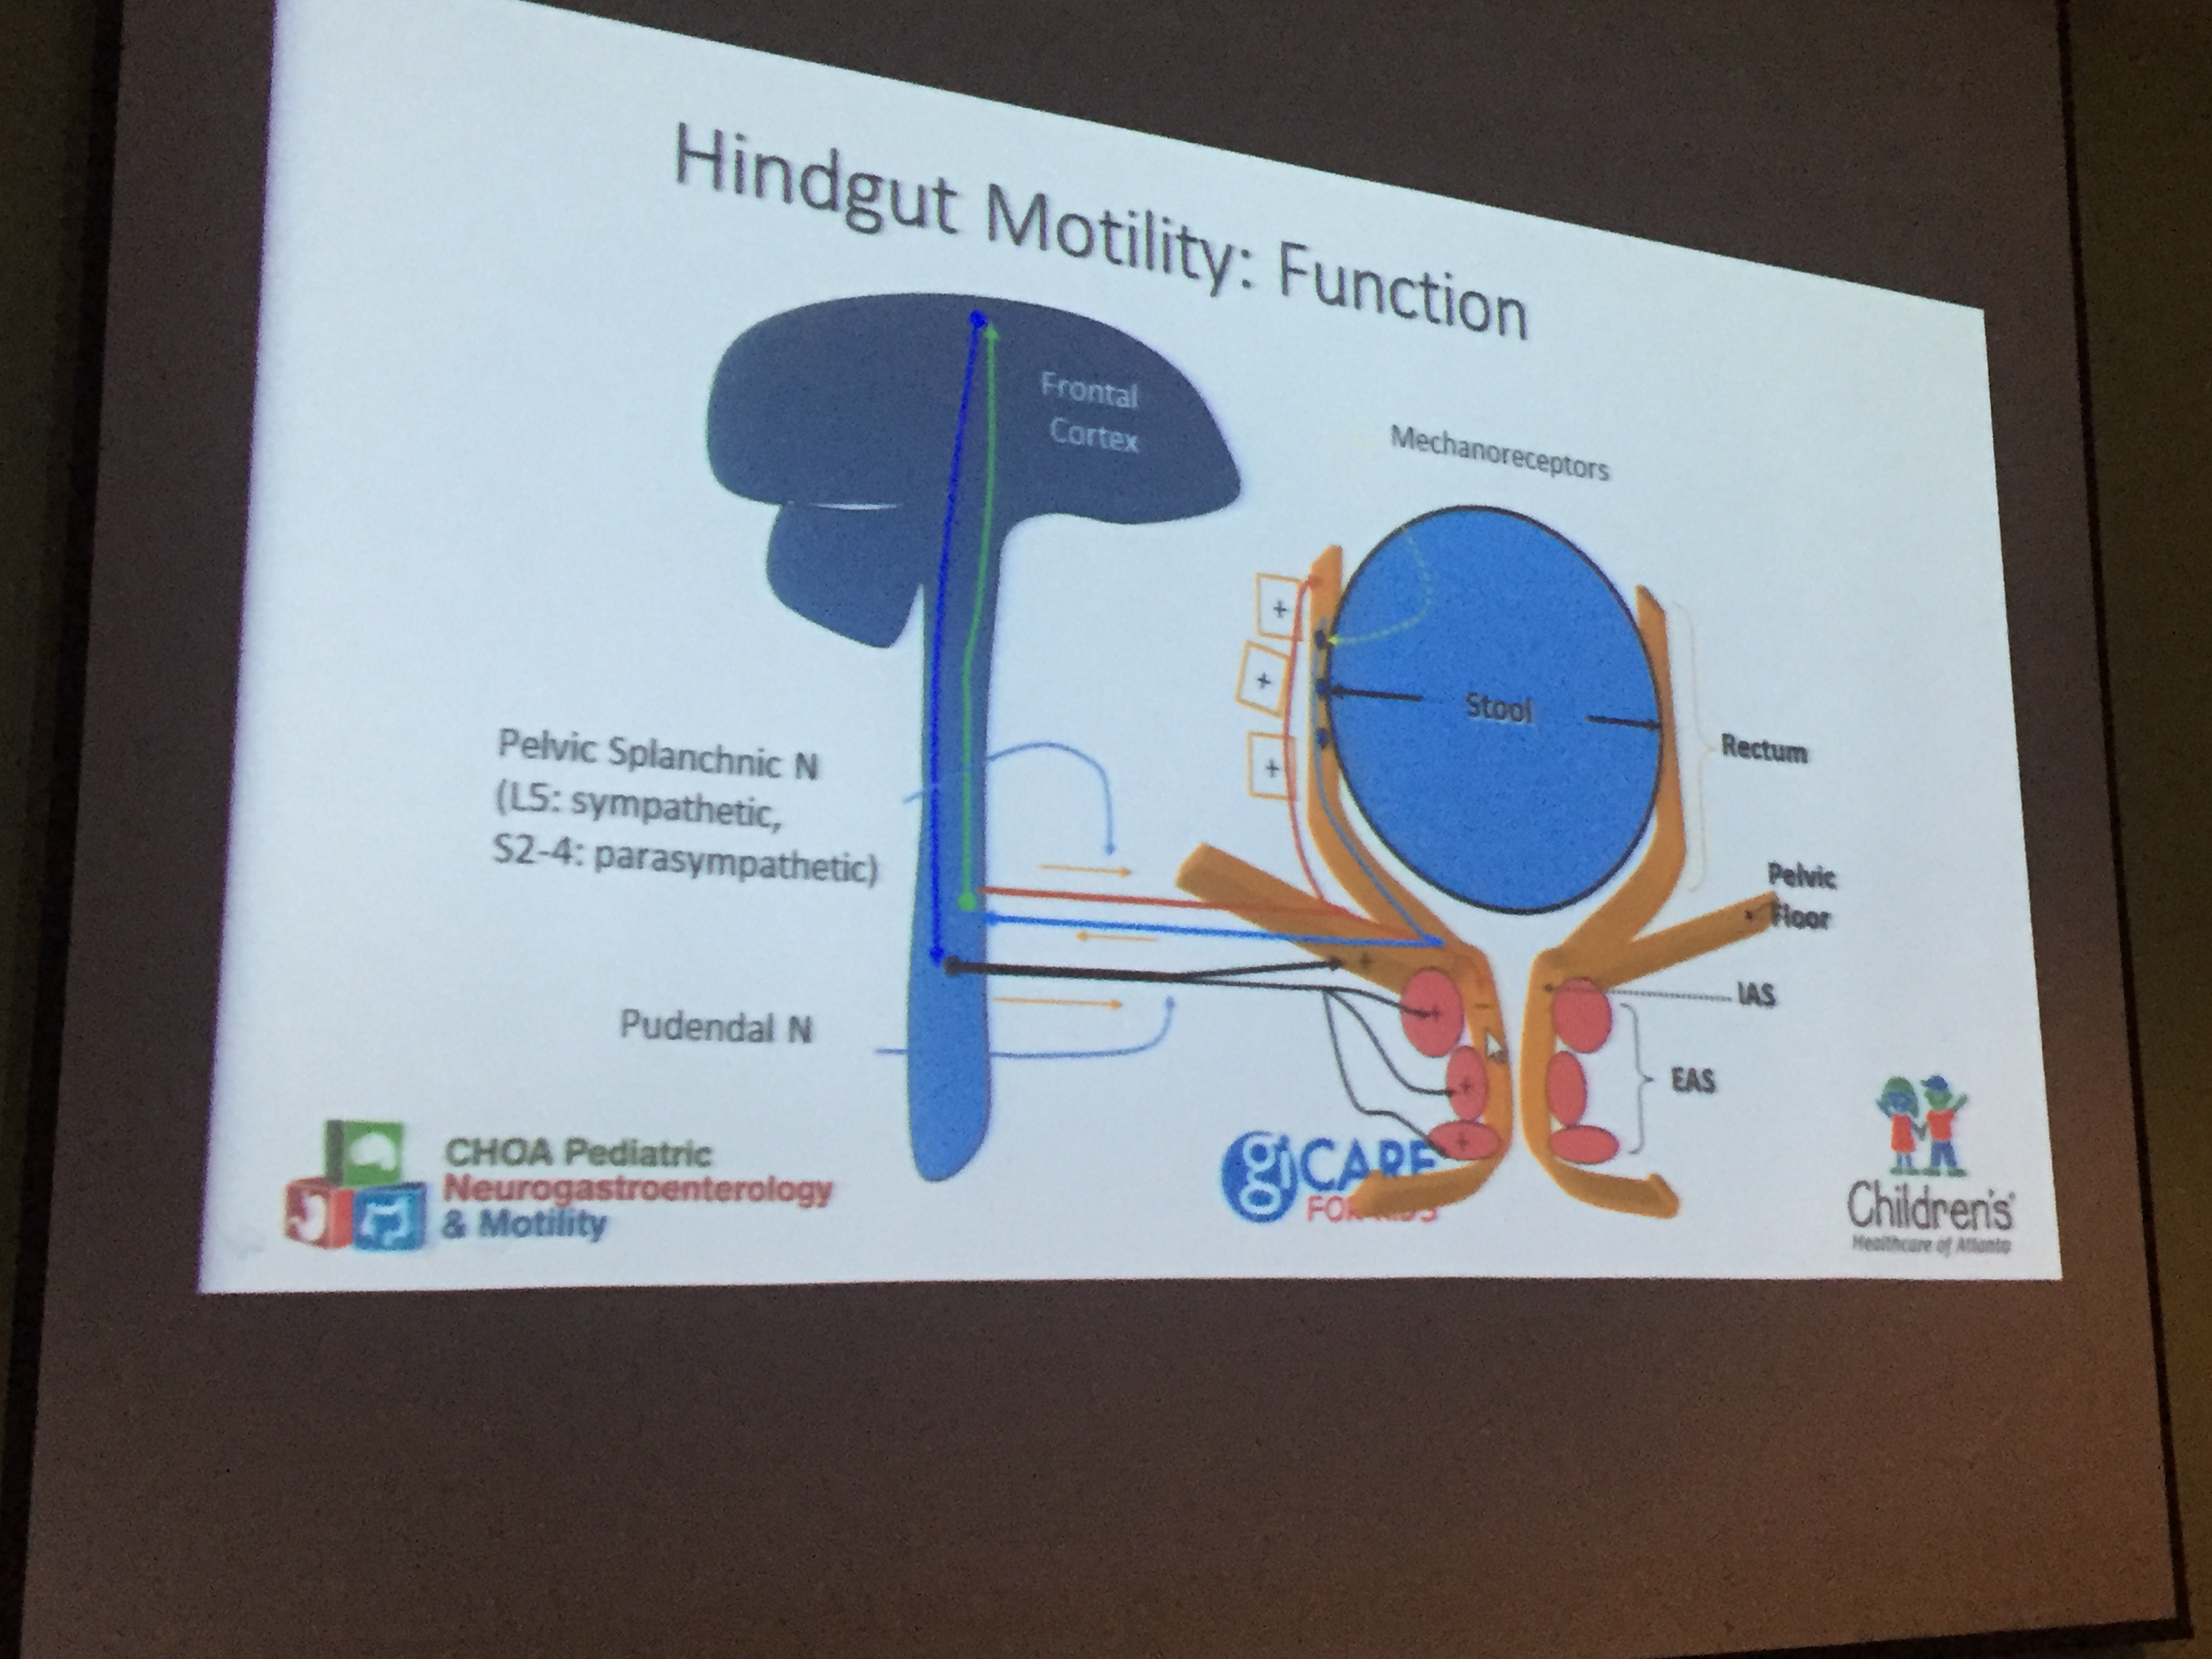
Recently I attended a terrific talk by my partner, Jose Garza.  This lecture provided a great deal of information on refractory constipation for both pediatricians and pediatric gastroenterologists alike.

Elements of the talk included diagnosis, pathophysiology and differential diagnosis.

Rome III Criteria -Helpful in Diagnosis of Constipation

Rome III Criteria -Helpful in Diagnosis of Constipation

JG1 pathophys

Is it Hirschsprung's Disease?

Is it Hirschsprung’s Disease?

Some of the more useful points.

  1. AXR should not be used to make diagnosis of constipation.
  2. Many refractory constipation patients are stooling fine and actually labeled as constipation instead of a functional abdominal pain disorder.  That is, they are complaining of stomach pain and have been erroneously told they are constipated (see point #1).
  3. Miralax remains a 1st line agent for constipation. In individuals with fecal soiling, if miralax is not working and they have had appropriate cleanout, then senna laxative may be helpful.
  4. Sitz markers are particularly helpful in proving stooling when teenager claims to not be stooling for a month and in proving functional fecal retention rather than nonretentive soiling.
  5. If good treatment is not working, then refer to neurogastroenterology.

Related blog posts:

JG3 -Help


FMT for Crohn’s Disease -Small Study

A recent prospective open-label study (Suskind DL, et al. Inflamm Bowel Dis 2015; 21: 556-63) adds a bit more information on fecal microbial transplantation (FMT) for individuals with Crohn’s disease (CD). This study included 9 patients, ages 12-19, and 11 authors.

Study details:

  • Pretreated with rifaximin 200 mg TID x 3 days and Miralax 17 gm TID x 2 days prior, and omeprazole day before and morning of procedure
  • Patients continued on prior treatment: 4 on methotrexate, 2 on thiopurine, and 3 on mesalamine (1 mesalamine patient was receiving methotrexate also)
  • Stool donor was a screened parent
  • Stool administered via NG
  • Stool DNA studied –>metagenomic sequencing

Key findings:

  • FMT engraftment was demonstrated in 7 of 9 patients
  • Mean PCDAI improved –baseline 19.7 –>6.4 at 2 weeks–>8.6 at 6 weeks
  • 5 of 9 patients who did not receive additional medical therapy were in remission at 6 and 12 weeks.

One particular advance with this study was the correlation between microbial species before and after FMT.  One speculation from the authors was that “the more divergent a Crohn’s patient is from his donor the more the potential benefit of transplantation.”  Thus, this same study with unrelated donor stool (eg. OpenBiome) would be of interest as well.

My Take: While this study offers encouragement for bigger studies, we will not know if FMT is effective (& how to administer optimally) until we have studies with more patients than authors.

Related blog posts:


Short Takes on IBD Articles

Singh S, et al. Gastroenterol 2015; 148: 64-76.  In this study, the authors identified 21 trials with 2006 participants to examine the comparative efficacy of pharmacologic interventions to prevent relapse of Crohn’s disease (CD) after surgery.  Conclusion: “anti-TNF monotherapy appears to be the most effective strategy for postoperative prophylaxis for CD.” The relative risk of clinical relapse and endoscopic relapse with anti-TNF monotherapy was estimated to be between 0.02-0.20 and 0.005-0.04, respectively. Thus, those at highest risk for recurrence, including younger individuals, smokers, penetrating CD, perianal CD, and recurrent surgeries) are most likely to benefit.(Related blog post: More Lessons in TNF Therapy (Part 1) | gutsandgrowth)

Pariente B, et al. Gastroenterol 2015; 148: 52-63. The researchers in this cross-sectional study developed the Lémann Index which measures cumulative structural bowel damage in patients with CD.  My only complaint with this study was the associated editorial on pages 8-10, titled “The Holy Grail, or Only Half Way There?”  There are too many medical advances compared to ‘the holy grail’ and, in my opinion, this shouldn’t be one of them.

Zitomersky NL et al. Inflamm Bowel Dis 2015; 21: 307-14.  In this study the authors examine the relationship between the development of antibodies to infliximab (ATI) and the risk of surgery in a cross-sectional cohort of pediatric and young adult patients.  Not surprisingly, development of ATI, which was noted in 20% of cohort, correlated with reductions in infliximab levels and higher risk of surgery.  Interestingly, prior (but not current) immunomodulator therapy was associated with lower antibody levels (P=0.007).  Perhaps, “step-up” therapy may lower the risk of ATI. (This was a point noted by James Markowitz in a previous post: More NASPGHAN Meeting Notes: IBD Hot Topics | gutsandgrowth)

Rogler G, Vavricka S. Inflamm Bowel Dis 2015; 21: 400-08. This review article discusses the exposome in IBD.  Exposures include air pollution, diet, drugs, infections, water pollution, food additives, and smoking.  These exposures influence the gut microbiome and genetic susceptibility. “Only environmental influences…explain the rising incidence in IBD worldwide. The investigation of the exposome…is an enormous challenge…[but] of crucial importance.” (Related blog post: What do you know about the “exposome”? | gutsandgrowth)

Kalmon RS. Inflamm Bowel Dis 2015; 21: 428-35. Review article provides information when there is a prior personal or family history of malignancy (=avoid thiopurines).  Figure 2 is a suggested algorithm for those with IBD and a previous diagnosis of cancer.

  • In those in which the cancer is adequately controlled, the recommendations indicate that if it has been more than 2 years since completion of therapy to use a ‘step-up’ management and favor methotrexate over thiopurines
  • In those with less than 2 years since completion of cancer treatment and not responsive to 5-ASAs/antibiotics, then “consider monotherapy with biologic agents.”
  • In those still receiving chemotherapy, the authors suggest “hold immunosuppression and follow course of IBD.  If IBD not well controlled despite chemotherapy, 5-ASAs and antibiotics, treat flares with steroids, then consider biologic agents.”

An Oral Oligonucleotide in the Crohn’s Treatment Pipeline & Smart Patients

The preliminary data are in from a phase II study regarding Mongerson, a oral pill for Crohn’s disease.

Here’s the link: Oral oligonucledotide shows efficacy, safety in Crohn’s

Here’s an excerpt from GI & Hepatology News:

Fourteen days of daily treatment with mongersen, an oral, antisense oligonucleotide, safely produced remissions in two-thirds of patients with Crohn’s disease in a phase II study with a total of 163 patients…

Mongensen “is not an anti-inflammatory drug. It removes a brake on the normal immunosupressant mechanism in the gut, and that is why the effect is long lasting. It allows TGF [transforming growth factor]-beta to work again [as an endogenous immunosuppressant] and promote healing,” said Dr. Monteleone, a professor of gastroenterology at the University of Rome Tor Vergata.

Oligonucleotide blockade of the production of the Smad7 intracellular protein prevented the inhibitory effect of Smad7 on TGF-beta and thus allowed TGF-beta to inhibit cytokine production and T lymphocyte signaling (J. Clin. Invest. 2001;108:601-9).

From ImproveCareNow — Smart Patients Online Community -may be helpful resource for families:

There are many social networks and online communities for IBD, but we have chosen to partner with the Smart Patients team because their custom-built, disease-specific forums offer a truly safe, warm and engaging experience for users. Smart Patients also offers conversation tagging, and clearly defined community norms, which means community members are highly likely to find the answers they need and highly unlikely to be trolled. And because the conversations are arranged using tags and completely searchable, you can always find what you’re looking for.

The Smart Patients team and ImproveCareNow have partnered to create an online IBD community that is supportive and also powerful. The Smart Patients IBDcommunity has the power to improve health and health care systems through patient and family peer-to-peer learning.


Taking One ‘Bite’ At A Time -For Celiac Diagnosis

A small study (reference from KT Park’s Twitter feed –Gastrointestinal Endoscopy DOI: http://dx.doi.org/10.1016/j.gie.2014.10.024) suggests that taking a single biopsy per pass rather than two biopsies per pass results in better quality specimens:

Link: Endoscopic Biopsy Technique in the Diagnosis of Celiac Disease

Here are the results and conclusion of the abstract:

Results

Patients (N = 86) were enrolled, 47% with known celiac disease, 36% with suspected celiac disease, and 17% with an unknown celiac disease status. Well-oriented biopsy specimens were noted in 66% of patients with the single-biopsy technique and 42% of patients with the double-biopsy technique (P < .01). Analysis of matched pairs showed improved orientation with the single-biopsy technique (odds ratio 3.1; 95% confidence interval, 1.5-7.1; P < .01). This persisted in subgroup analysis of patients with known celiac disease (P = .02), villous atrophy (P = .02), and a final diagnosis of celiac disease (P < .01).

Conclusion

The single-biopsy technique improves the yield of well-oriented duodenal biopsy specimens. Endoscopists should consider taking only 1 biopsy specimen per pass of the forceps in patients undergoing biopsies of the duodenal mucosa.

Related blog posts:

I'm the one on the right

I’m the one on the right

Accelerated Infliximab Dosing in Acute Severe Ulcerative Colitis -plus one link

A small retrospective study (n=50) suggests that more rapid induction with infliximab may improve response and lower colectomy rate in acute severe ulcerative colitis (UC).

Link: Accelerated Infliximab in Acute UC

Here’s the abstract:

Background & Aims

Administration of infliximab to patients with acute severe ulcerative colitis (ASUC) (rescue therapy) can reduce the rate of early colectomy (within 12 months), but long-term rates of colectomy are the same as those of the pre-biologic era for these patients. The half-life of infliximab is shorter in patients with ASUC than in patients with non-severe UC, so more frequent dosing might be required to produce a therapeutic effect.

Methods

We performed a retrospective analysis of 50 hospitalized patients who received infliximab for steroid-refractory ASUC at a single academic center from September 2005 through 2013. In 2011 an accelerated dosing strategy for infliximab was introduced; we compared outcomes of standard and accelerated dosing regimens. One group of patients (n = 35) were placed on a standard dosing regimen for infliximab and then given the drug at 0, 2, and 6 weeks and then every 8 weeks thereafter. A second group (n = 15) were placed on an accelerated regimen and received 3 induction doses of infliximab within a median period of 24 days. Rates of colectomy were compared between the groups during induction and follow-up periods.

Results

There were no differences between groups in median baseline levels of C-reactive protein, albumin, or hemoglobin. The rate of colectomy during induction therapy was significantly lower with the accelerated regimen (6.7%, 1 of 15) than with the standard regimen (40%, 14 of 35) (Fisher exact test, P = .039). The standard regimen was associated with shorter time to colectomy (log-rank test, P = .042). Among patients who completed induction therapy, subsequent need for colectomy was similar between the groups during the follow-up period. Multivariate analysis showed that factors independently associated with successful induction therapy were level of albumin (g/L) when the treatment began (P = .003) and the accelerated dosing regimen (P = .03).

Conclusions

In patients with ASUC, an accelerated infliximab induction strategy reduces the need for early colectomy. An intensified infliximab dosing strategy in response to clinical or laboratory signs of breakthrough inflammation merits consideration in prospective studies.

One other link: IBD and College: Do the two play nicely (from Jeremy Adler and UofM) -describes college transition issues for our IBD patients.  Probably the most important piece of advice: “Take your medicine.”  Many really good kids decide to see what happens off therapy, often to their detriment.

How Effective are the Treatments for Functional Abdominal Pain?

According to a recent systematic review (Korterink JJ et al. J Pediatr 2015; 166: 424-31), “there is no evidence to support routine use of any pharmacologic therapy” for pediatric functional abdominal pain (FAP).  How many pediatric gastroenterologists want to discuss this conclusion with their patients?

How did the authors reach their conclusion?

Design: The authors screened 557 articles and ultimately identified only four articles with a total of 6 studies met inclusion criteria which included the following:

  • systemic review or randomized control trial
  • children 4-18 years
  • diagnosis of FAP established with well-defined criteria
  • intervention was compared to placebo or alternative treatment

Results: All of the studies were reviewed –each received an overall quality rating by the authors as “very low.” The particular treatments included amitriptyline, peppermint oil, famotidine, miralax, tegaserod, and cyprohepatadine.  The study with the most patients had only 90 patients and the longest treatment period was 4 weeks.

In the discussion, the authors make several key points:

  • there is a lack of adequately powered, high-quality, placebo-controlled drug trials in children with FAP
  • weak evidence was found in support of peppermint oil, cyproheptadine, and laxatives at reducing pain; amitriptyline and famotidine had weak evidence supporting some improvement in global symptoms or quality of life.
  • problems with the studies: small sample sizes, poorly reported side effects, lack of follow-up, risk of bias
  • “several nonpharmacologic therapies (e.g.. hypnotherapy and cognitive behavioral therapy) have shown their efficacy in treating children with” FAP…with success rates up to 85%.  Moreover, these therapies are not hampered by severe side effects.”

Bottomline: Our office-based psychologist may be more helpful for our patients than all the medications combined.

Related posts:

Increased Narcotic Usage in Pediatric Patients with IBD

A summary from the AGA Journals Blog of a recent article highlights the increased use of chronic narcotics, not related to surgery, in pediatric patients with IBD.

Here’s a link:  Chronic Use of Narcotics in Children with IBD and here’s an excerpt:

Jessie P. Buckley et al used data from a large insurance claims database, collected from 2010 through 2011, to compare the prescription narcotic use among children (younger than 18 years old) with and without IBD who were not undergoing surgery. Buckley et al also searched for factors associated with narcotic treatment of pediatric patients with IBD.

Of 4344 children with IBD during the study period, 63% had Crohn’s disease, and 37% had ulcerative colitis.

Buckley et al found that 5.6% among children with IBD vs 2.3% in the general population received chronic narcotic therapy. Associations between IBD and narcotic use revealed a particularly high burden among children with concomitant anxiety or depression.

Cover of Clinical Gastroenterology & Hepatology

Cover of Clinical Gastroenterology & Hepatology –The pills look cool but wrong age depicted

More Evidence to Support Ethanol Locks

For many years, ethanol locks have been promoted as a way to reduce central catheter-associated bloodstream infections (CCABSI).  A recent study (Ardura M I, et al. JAMA Pediatr.doi.10.1001/jamapediatrics.2014.3291 -published online Feb 2, 2015, thanks to Ben Gold for this reference) showed a dramatic reduction in CCABSI among 24 children with intestinal failure.

This study examined outcomes from January 2011-Jan 2012 with the outcomes from February 2012-December 2013.  In the latter period, ethanol lock prophylaxis was added to the CCABSI “prevention bundle” both in inpatient and outpatient settings.

Key finding: Rates of CCABSI decreased from 6.99 per 1000 catheter days to 0.42 per 1000 catheter days.

One aspect of this study that is very important is that the QI team included a specialized CVC nurse who evaluated and performed all CVC care and teaching.

Their protocol is detailed in their methods section.  Some of the details:

  • Their ethanol lock utilized a 70% solution on a daily basis.
  • The CVC nurse verified that the catheter was silicone prior to initial lock.
  • CVC nurse used Alteplase prior to initial dwell.
  • Dwell volume was determined by CVC nurse by withdrawing flush until blood return and then adding 0.1 mL for children <15 kg and adding 0.2 mL for children >15 kg (max volume 3 mL).
  • Dwell times were minimum of 2 hours and maximum of 24 hours.
  • At the end of the dwell time, twice the amount of the predetermined ethanol volume was withdrawn and then 5 to 10 mL of normal saline was used as a flush.

Bottomline: Ethanol locks have the potential to reduce CCABSI by 90%; this can reduce hospitalizations, prevent complications, and possibly improve survival.

Related blog posts:

Heart-Shaped Polyp (from ACG twitter feed -recommends screening colonoscopy)

Heart-Shaped Polyp (from ACG twitter feed -recommends screening colonoscopy)

How Commonly Does Cystic Fibrosis Present as Rectal Prolapse?

Since residency, I have understood that patients with cystic fibrosis patients could present with rectal prolapse.  Yet, I can recollect only one instance in which a family told me that rectal prolapse was a presenting feature in the diagnosis of their child.  It turns out that rectal prolapse is a little less common as a presenting feature, at least these days, and that the majority of cases occur in individuals with cystic fibrosis who have already been diagnosed (JPGN 2015; 60: 110-12).

In this retrospective study (2000-2010), there were 262 patients with rectal prolapse identified: 65% were male and mean age was 4 years 8 months.  Newborn screening for cystic fibrosis(1994 in Wisconsin) had preceded the study period.

The most common reason for rectal prolapse was constipation (52.1%), and then acute diarrhea (12%).  Only 3.6% had cystic fibrosis. Two patients were diagnosed with cystic fibrosis based on testing performed due to rectal prolapse; the remaining five had already been diagnosed.

The authors note that among their cystic fibrosis population that 3.5% also had rectal prolapse.

Take-home message: In patients with rectal prolapse, testing for cystic fibrosis has a low yield in the era of newborn screening but is probably still necessary.

Boat in Chicago Marina

Boat in Chicago Marina –Like the Name?