Nutrition Week (Day 4) Trophic Hormone for Pediatric Short Bowel Syndrome

A recent study (BA Carter et al. J Pediatr 2017; 181: 102-11) provides some preliminary data on the use of glucagon-like peptide-2 (GLP-2) (Teduglutide) for pediatric short bowel syndrome (SBS).

This was a 12-week, open-label study in patients aged 1-17 years with intestinal failure (IF) associated with SBS. Prior to the study, patients had shown little to minimal advance in enteral nutrition for at least 3 months. Three doses of GLP-2 (0.0125 mg/kg/d, 0.025 mg/kg/day, and 0.05 mg/kg/day).

Key findings:

  • All treated patients (37) experienced mild or moderate adverse effects, including vomiting, pyrexia, catheter-related complications, and upper respiratory tract infections. No serious adverse events were identified. In the 5 patients who received standard care, adverse effects were recorded as well, including upper respiratory tract infections in 2 (40%) which was similar to the other groups.
  • By week 12, parenteral nutrition (PN) volume and calories were reduced in the higher dosed groups.  In the 0.025 mg/kg/day group, PN volume dropped by 41% and calories by 45%.  In the 0.05 mg/kg/day group, PN volume dropped by 25% and calories by 52%. Virtually no change in these parameters occurred in the lowest dose (0.0125 mg/kg/day) with no change in volume and 6% drop in calories.
  • Enteral feeding volume occurred in all groups: 22%, 32%, and 40% in the groups and was directly related to the GLP-2 dosing.
  • Citrulline levels (a biomarker of enteral autonomy) were monitored “but the results were clouded by wide variability of baseline values.”  In adult studies, citrulline levels increased significantly.

My take: This open-label study has many limitations; further studies are planned (ClinicalTrials.gov, NCT02682381). Nevertheless, this study indicates that GLP-2 holds promise as a therapy for SBS/IF.

Another slide in a recent lecture on PNALD (slide derived from Conrad Cole lecture in Octobler 2015 -available at Pediatric Nutritionist Blog, slide 49):

screenshot-109

Related blog posts:

Nutrition Week (Day 2) SMOFlipid

With newer lipid emulsions, there is the potential to give more lipids and have less liver injury.  A recent report by Diamond et al (JPEN J Parenter Enteral Nutr. 2016 Feb 2. pii: 014860711562692) provides some of the best data for the use of SMOFlipid in infants: Preventing the Progression of Intestinal Failure-Associated Liver Disease in Infants Using a Composite Lipid Emulsion: A Pilot Randomized Controlled Trial of SMOFlipid.

Here’s the abstract: and afterwards some slides from a recent lecture that I gave regarding parenteral nutrition associated liver disease (and intestinal failure associated liver disease):

BACKGROUND:

To examine whether SMOFlipid prevents progression of intestinal failure-associated liver disease (IFALD) in parenteral nutrition (PN)-dependent infants with early IFALD (conjugated bilirubin 17-50 µmol/L, 1-3 mg/dL).

STUDY DESIGN:

Pilot multicenter blinded randomized controlled trial comparing SMOFlipid with Intralipid. Patients received the trial lipid for up to 12 weeks, unless they achieved full enteral tolerance sooner. The primary clinical outcome was the serum conjugated bilirubin.

RESULTS:

Twenty-four infants (mean age, 6 weeks) participated in the trial (13 Intralipid and 11 SMOFlipid). At the time of trial enrollment, patients in both groups were receiving 90% of their calories by PN. Mean duration on trial was 8 weeks and did not differ according to treatment (P = .99). At trial conclusion, patients who received SMOFlipid had a lower conjugated bilirubin than those who received Intralipid (mean difference, -59 µmol/L; P = .03). Patients receiving SMOFlipid were also more likely to have a decrease in serum conjugated bilirubin to 0 µmol/L than those in the Intralipid group over the entire observation period (hazard ratio, 10.6; 95%; P = .03). The time to achievement of full enteral tolerance did not differ statistically (hazard ratio, 1.3; P = .59) between the groups. There was no significant difference in safety outcomes between the groups.

CONCLUSIONS:

Compared with Intralipid, SMOFlipid reduces the risk of progressive IFALD in children with intestinal failure. This trial was registered at clinicaltrials.gov as NCT00793195.

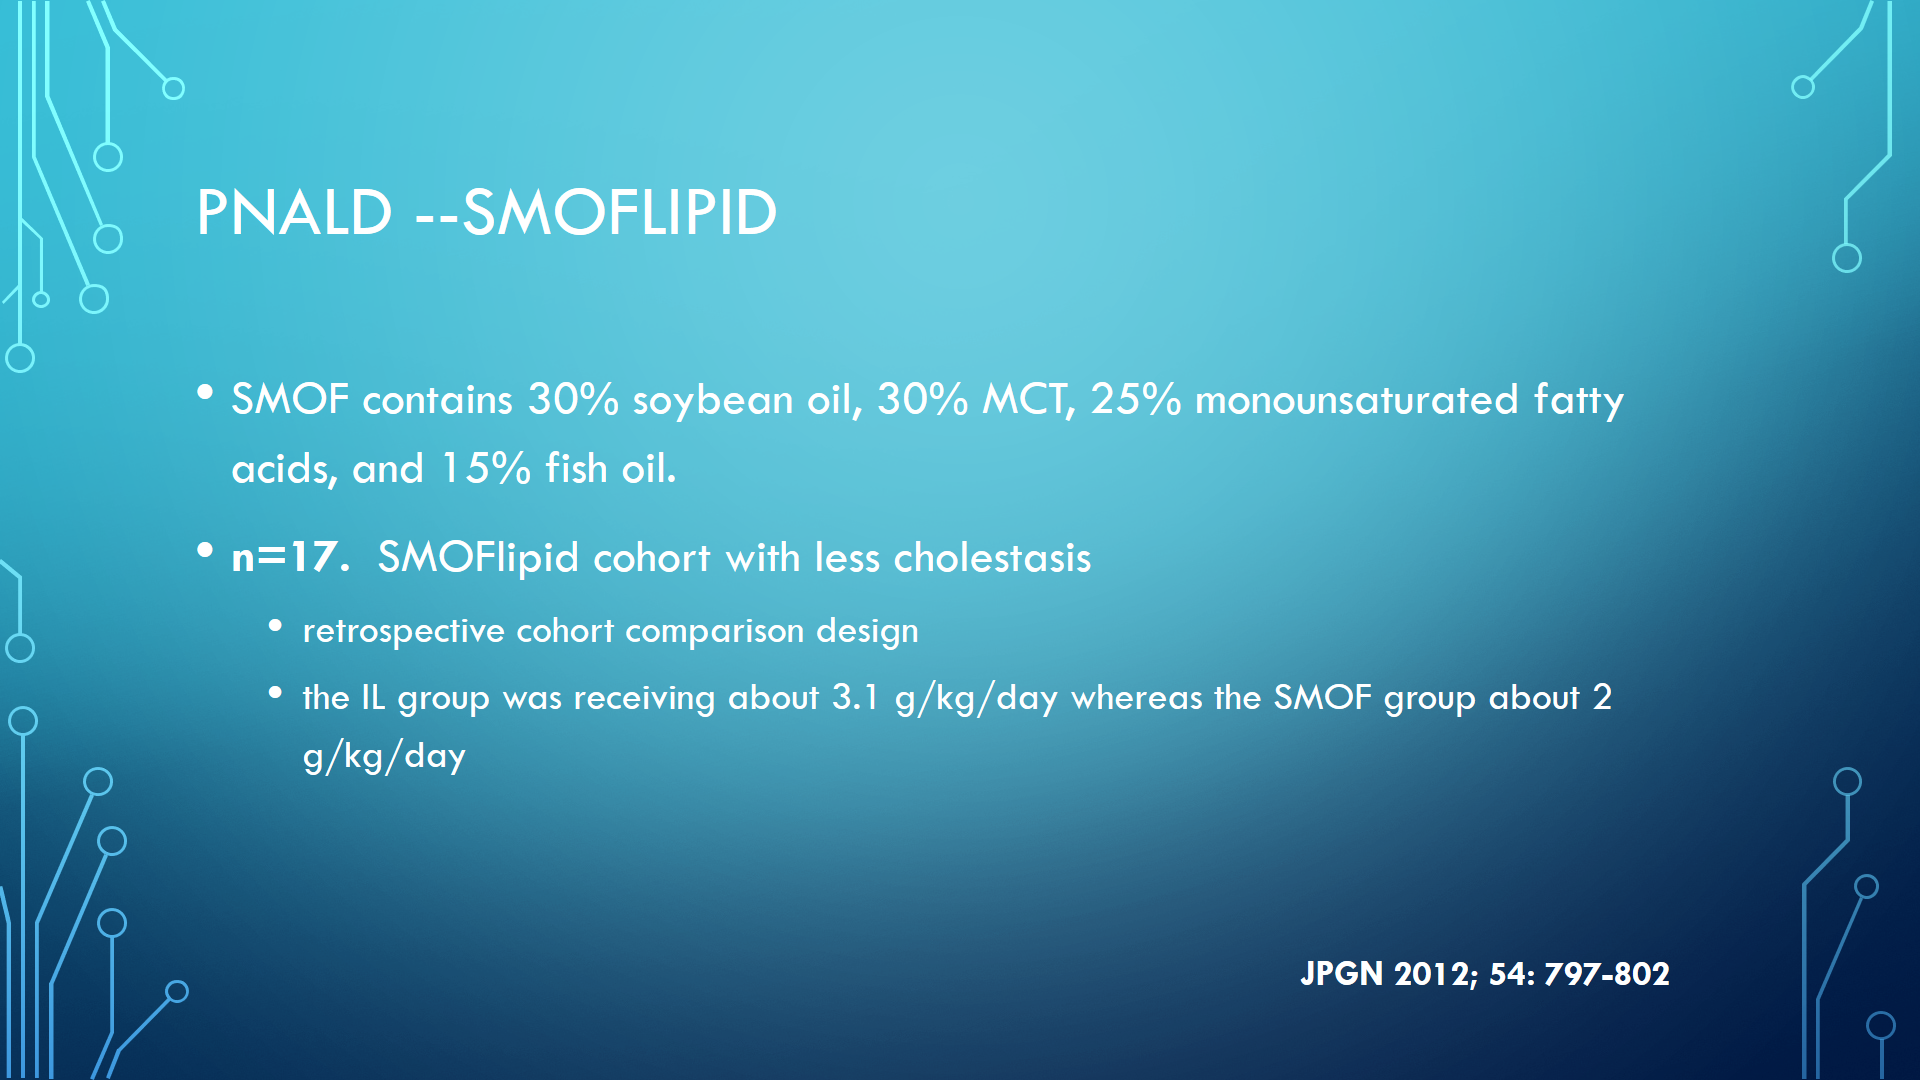
Here are a few more slides from my recent lecture on PNALD/IFALD:

screenshot-105

screenshot-104

screenshot-106

The above slide was borrowed from a talk by Dr. Conrad Cole on short bowel syndrome (available online via the Pediatric Nutritionist blog).

screenshot-107


Related blog posts:


Nutrition Week (Day1) Downside on Lipid Reduction

Recently I gave a lecture on parenteral nutrition associated liver disease (PNALD), though the term intestinal failure associated liver disease (IFALD) is probably more popular at this time.  The day afterwards, I read an important study (L Beauport et al. J Pediatr 2017; 181: 29-36) reiterating one of the concerns in the lecture.

This study showed that higher lipid intake in a cohort of neonates born at <30 weeks during the first 2 weeks after birth was associated with a lower incidence of brain lesions and dysmaturation when examined by MRI at term equivalent age (TEA).

Details: This prospective cohort study examined energy/lipid intake in the first 2 weeks of life. Eligible patients were neonates ≤30 weeks.  Group 1 with 27 patients had birth weight median of 900 gm compared with Group 2 with 15 patients had median weight of 844 gm. During the first year of the study, participants received a soybean emulsion whereas in the last year of the study, the neonates received a mixture of soybean and olive oil (Clinoleic).

Key finding: After adjusting for clinical risk scores and sepsis, the authors found that the higher energy/lipid intakes resulted in improved brain MRIs in group 1. A “10 Kcal/kg/day increase in energy of 0.7 g/kg/day increase in lipids intake would reduce the risk of having more severely abnormal MRI at TEA by >60%.”

Here are some slides from my talk relevant to this topic and to parenteral nutrition associated liver disease (PNALD):

screenshot-102 screenshot-103

Nutrition in Immune Balance -New Website for Inflammatory Bowel Disease

Dr. David Suskind and colleagues have developed a website which provides a great deal of information regarding nutritional therapy, particularly the Specific Carbohydrate Diet (SCD), and inflammatory bowel disease.  The website also facilitates contributions to Seattle Children’s Hospital and buying a book on the SCD.

Here’s a link to website: NIMBAL.org

Related blog posts:

Near Shem Creek, SC

Near Shem Creek, SC

Fasting Probably Not Needed Before Checking Lipids

A cross-sectional study (LN Anderson et al. J Pediatr 2017; 180: 47-52) of 2713 children extends prior observations that there is little evidence supporting the need for fasting prior to measurement of lipids.

Prior blog on this topic: Is Fasting Needed Before Checking Lipids

This study showed that fasting duration (0-5 hrs) was not significantly associated with total cholesterol, LDL, HDL, or triglycerides. This is most evident on the graphs on their Figure.

In the discussion, the authors note that the NHANES study 1999-2008 had similar results for the younger children.  Overall, there were 12,744 children aged 3-17 years;  80% fasted at least 8 hrs.  In this study, fasting did have a small effect on lipids, but among children 3-5 yrs, only LDL was statistically affected by fasting status.

My take: Based on this study and others, fasting seems to have only a small effect on lipid measurement and for routine screening, it is probably not needed.

Yosemite Natl Park

Yosemite Natl Park

Bariatric Surgery and Reversal of NASH

A small prospective study (M Manco et al. J Pediatr 2017; 180: 31-7) provides evidence that bariatric surgery/sleeve gastrectomy is effective at reversing nonalcoholic steatohepatitis (NASH) and hepatic fibrosis in adolescents (n=20).

All patients in this study had BMI >35 and weere 13-17 yrs of age.

Key findings at one year following intervention:

  • Among the 20 patients who underwent sleeve gastrectomy, there was a 21.5% loss in baseline weight, which compared with weight loss of 3.4% among 20 patients who received intragastric balloon device and weight increase of 1.7% among 53 patients who received lifestyle intervention counseling.
  • Sleeve gastrectomy group had resolution of NASH in all 20 and disappearance of hepatic fibrosis in 18 (90%).  In the intragastric balloon group, NASH reverted in 24% and fibrosis in 37% whereas there was no improvement in the lifestyle intervention group.

Full text link: Sleeve Gastrectomy for NASH

Limitations are discussed in the editorial by Inge and Xanthakos (pgs 6-7) and included small sample size, absence of patients with type 2 diabetes, and short followup period.  Nevertheless, this is “the largest and most informative series…in select adolescents with severe obesity.”

My take: Given the lack of effective pharmaceutical therapy and the typically impotent effects of lifestyle intervention, this data supports bariatric surgery to facilitate weight loss/NASH reversal in select adolescents.

Related article: JCF Leung et al. Hepatology 2017; 65: 54-64.  This study showed that the histologic severity and clinical outcomes are modestly better in nonobese patients (n=72) with NAFLD compared with obese patients (n=307). High triglycerides and higher creatinine were associated with more advanced liver disease in nonobese patients.

Briefly noted: D Houghton et al. Clin Gastroenterol Hepatol 2017; 15: 96-102.  This study with 24 subjects with nonalcoholic steatohepatitis showed that exercise reduced hepatic triglyceride content, visceral fat, and plasma triglycerides. However, circulating markers of inflammation and fibrosis was not reduced.  The implication is that exercise should be part of NASH treatment but that weight management/diet are needed as well.

Glacier Natl Park

Glacier Natl Park

. Related blog posts:

Eating Tips from Strong4Life Website

Our hospital has been working on childhood obesity and has developed a multifaceted program called “Strong4Life.”  Recently the associated website has added some useful content for families.

From recent Children’s Healthcare of Atlanta email:

New Feeding and Wellness Resources for Parents

Children’s has launched a new feeding and wellness resource section on its dedicated parenting website, Strong4Life.com. The site is full of articles, videos and tools that new parents will find essential. From birth through school-age, Strong4Life equips parents to deal with everything from bedtime battles and mealtime tantrums, to food parenting and picky eating, and everything in between. With filtering of content by age of child, parents can now access relevant, easy-to-try tips, facts and advice from Children’s doctors, registered dietitians and wellness experts, who are also parents.

A sampling of the many articles and videos can be found here:

Other recommendations from Strong4Life:

Added Sugars
In August, the American Heart Association released its recommendations on the consumption of added sugars for children ages two to 18 years old. Children in this age range should not consume more than six teaspoons or 25 grams of added sugar per day; and children under age two should avoid it altogether. To learn where sugar may be hiding in children’s diets and simple ways to avoid it, visit strong4life.com/sugar.

Screen Time
The American Academy of Pediatrics (AAP) fine-tuned their screen time guidelines, to align better with the digital world we live in:

  • Children 18 to 24 months—no screen time other than video chatting. If digital media is introduced, focus on high-quality programming/apps, and parents should co-view with their child
  • Children 2 years and older—limit digital media to one (1) hour or less per day, of high quality programming
  • All children—keep meals, bedrooms and playtimes screen-free

frogsinfront

Cystic Fibrosis Expert Update 2017

During one of our recent group clinical meetings, one of my partners (Edith Pilzer, MD) presented an update on cystic fibrosis.

Here is a link to her slides:Link: cf-presentation

Here are a few of my notes:

There has been a great improvement in survival of cystic fibrosis patients..  From the Cystic Fibrosis Foundation:

  • ” Today the median predicted survival age is close to 40. This is a dramatic improvement from the 1950s, when a child with CF rarely lived long enough to attend elementary school.”

cftr2org  —website provide information on specific genotypes, including whether genotype is associated with pancreatic insufficiency

From the website:

  • This website provides information for members of the general public, including cystic fibrosis patients and their family members, about what is currently known about specific genetic variants related to cystic fibrosis.
  • Patients and their family members are encouraged to visit the section, “For patients and family members” first.
  • This website also provides more in-depth research-related information for health care professionals and researchers

Pancreatic enzyme replacement therapy (PERT) (see slides)

  • Creon 3000 beads are small enough to go through Gastrostomy tube
  • Pertzye has bicarbonate; thus, additional acid blocker administration is usually not needed
  • Viokase is hard to obtain
  • Relizorb –external lipase cartiledge.  This allows formula, delivered by NG, to run through column and obviates the need for additional PERT dosing.  One cartridge designed for 500 cc but several cartridges can be ‘piggy-backed.’ Here is website: relizorb.com.  Relizorb intent is to eliminate enzymes for night feeds, though it only has lipase; yet, there still could be a need additional PERT for protease and amylase.  Potentially PERT could be administered before or after and hopefully avoid awakening at night for enzymes..

Cystic Fibrosis Related Diabetes (CFRD)

  • Frequent reason for poor growth
  • Now, with increased survival, ~35% of Cystic Fibrosis patients develop CFRD

Distal Intestinal Obstruction Syndrome (DIOS)

  • If mild, treatment with miralax is reasonable
  • If vomiting, consider surgery consult
  • If more than mild, consider water-soluble enema with 10% mucomyst

My take: Great update.  Edith has been taking care of children with cystic fibrosis for more than 30 years and has witnessed/participated in the improvement in the survival of these patients.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.


Puerto Rico

Puerto Rico

Blind Men and The Elephant: Lasting Consequences of Enteric Infections

Recently, Ben Gold handed me a supplement which alluded to the case of “the blind men and the elephant.”  So, of course, I wanted to know more about this.

According to Wikipedia:

In various versions of the tale, a group of blind men (or men in the dark) touch an elephant to learn what it is like. Each one feels a different part, but only one part, such as the side or the tusk. They then compare notes and learn that they are in complete disagreement. The stories differ primarily in how the elephant’s body parts are described, how violent the conflict becomes and how (or if) the conflict among the men and their perspectives is resolved.  In some versions, they stop talking, start listening and collaborate to “see” the full elephant. When a sighted man walks by and sees the entire elephant all at once, the blind men also learn they are all blind. While one’s subjective experience is true, it may not be the totality of truth. If the sighted man were deaf, he would not hear the elephant bellow.

It has been used to illustrate a range of truths and fallacies; broadly, the parable implies that one’s subjective experience can be true, but that such experience is inherently limited by its failure to account for other truths or a totality of truth. At various times the parable has provided insight into the relativism, opaqueness or inexpressible nature of truth, the behavior of experts in fields where there is a deficit or inaccessibility of information, the need for communication, and respect for different perspectives.

The rest of the supplement regarding chronic health consequences following acute enteric infections was less interesting but probably more important than learning a new anecdote.

The introduction notes that nearly 600,000 children under 5 years die from dehydrating diarrhea each year.  Many more suffer from consequences of disease-associated malnutrition with both physical and cognitive deficits.

Articles in supplement:

  • Am J Gastroenterol Suppl 2016; 3: 4-11. –details diarrhea-associated years lived with disability 51 per 100,000 in developed regions compared with 685 in developing regions.
  • Am J Gastroenterol Suppl 2016; 3: 12-23. –details the likelihood of consequences following enteric infections, including functional GI disorders, inflammatory bowel disease, celiac disease (data limited), Guillain-Barré syndrome, hemolytic uremic syndrome, chronic fatigue, and neurologic sequelae.
  • Other articles in the supplement describe changes in the microbiome, the micorbiome-gut-brain axis, and the relationship between autoimmunity and irritable bowel.


Nutrition Guidelines for Cystic Fibrosis

Wilschanski et al (JPGN 2016; 63: 671-5) provide a summary (“highlights”) of a full report (Turck D et al. Clin Nutr 2016; 35: 557-77) on nutritional recommendations for infant and children with cystic fibrosis.

What’s in here:

Table 1: criteria for adequate nutritional status including

  • Age <2 yrs: 50% for weight & height compared to healthy-age peers
  • Age 2-18 yrs: 50% BMI compared to healthy peers

Table 2: nutritional assessment and followup

  • Assess elastase-1 annually if pancreatic sufficient
  • Assess pancreatic enzyme supplementation
  • Annual blood tests: CBC/d, iron status, fat-soluble vitamins, LFTs.  Possibly: fatty acids
  • If older than 10 years, annual glucose tolerance
  • Dietary review every 3 months
  • Bone density assessment between 8-10 yrs and then every 1-5 yrs

Table 3: Energy requirements

  • Anticipate need for 110-200% compared with healthy peers

Table 4: Pancreatic enzyme replacement therapy (PERT)

  • 0-1 yr: 2000-4000 units lipase/120 mL of formula/breast milk & 2000 units lipase/gram of dietary fat
  • 1-4 yrs: 2000-4000 units of lipase/gram of dietary fat (max 10,000 units lipase/kg/day)
  • >4 yrs: starting dose; 500 units lipase/kg/meal -titrate up to 1000-2500 units lipase/kg/meal (max 10,000 units lipase/kg/day)

Table 5: Fat-soluble vitamin/vitamin guidelines

Table 6: Sodium supplementation

  • 0-6 months: 1-2 mmol/kg/day –give salt in small portions throughout the day, “diluted in water or fruit juice”.  In some infants, up to 4 mmol/kg/day if increased losses (eg. due to heat, gastrointestinal losses)
  • Older children: anticipate need for additional salty foods or use sodium chloride capsules, especially when excessive sweating (eg. fever, sports, hot weather)

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Maine Coast, near Acadia

Maine Coast, near Acadia