Another Look at “Step-up” IBD Therapy

Whether and how long to continue immunomodulators in patients who have undergone a “step-up” treatment to anti-tumor necrosis factor (anti-TNF) therapy remains murky.  This is due to conflicting data from different patient cohorts, changing treatment trends, (e.g. use of drug monitoring to enhance anti-TNF therapy), and different endpoints. With regard to the latter, dual therapy has been clearly more effective in some landmark studies (eg. SONIC, UC SUCCESS); however, there have been ongoing concerns regarding long-term outcomes and adverse effects.

Will more studies help resolve this question? Perhaps, but not today.

A recent study (MT Osterman et al. Clin Gastroenterol Hepatol 2015; 13: 1293-1301) examined a retrospective cohort of new users of anti-TNF therapy for Crohn’s disease in Medicare recipients.  The authors matched 381 combination with infliximab (ie. dual therapy) with 912 users of monotherapy. In addition, the authors did the same with adalimumab with 196 combination users and 505 monotherapy users. In their cohort, combination therapy occurred primarily as a “step-up” treatment after institution of thiopurine therapy.

Results:

  • Key outcome measures were unchanged: rates of surgery (hazard ratio [HR] 1.2, hospitalization HR 0.82, discontinuation of anti-TNF therapy or surgery HR 1.09, and serious infection HR 0.93
  • Opportunistic infections were increased in combination therapy with HR 2.64 and herpes zoster infection was increased with HR 3.16

Take-home message: This study suggests, at least in this elderly population, that once remission is achieved with anti-TNF therapy, discontinuation of thiopurine therapy or use of an alternative immunomodulator therapy may be worthwhile.  At the same time, definitive answers to these type of questions await carefully designed randomized trials.

Related blog posts:

Identifying Anastomotic Ulcers with Capsule Endoscopy

A retrospective review (LM Bass et al. JPGN 2015; 61: 215-9) showed that capsule endoscopy (CE) can be helpful in identifying anastomotic ulcers among patients with short bowel syndrome and chronic GI blood loss.

This study of 4 patients (& 6 CE procedures) indicated that two of these patients underwent surgery after identifying anastomotic ulcers.  The other common treatment was antibiotics. In the suggested evaluation CE was used after upper/lower endoscopy. The recommended role for patency capsule/small bowel imaging is not clearly spelled out, but should be carefully considered due to the risk of strictures.

“The decision to perform CE is made in conjunction with medical and surgical teams so that, although every effort is made to avoid a situation that may result in a retained capsule, both parents and care teams are prepared.”

Related blog posts:

Changing Practice Patterns with Pediatric Pancreatitis

A recent study (FK Szabo et al. J Pediatr 2015; 167: 397-402) supports the practice of early enteral nutrition and aggressive fluid administration with acute pancreatitis. Starting in January 2014, Cincinnati Children’s began using high rates of intravenous fluid and resuming enteral nutrition within 48 hours for children presenting with acute pancreatitis.  This retrospective study assessed this practice in 201 patients and compared with prior experience dating back to 2009. To be included, patients had to have mild acute pancreatitis based on the Atlanta criteria (Gut 2013; 62: 102-11). Exclusion criteria:

  • Severe acute pancreatitis: multiorgan failure, systemic inflammatory response, local pancreatic complications (eg. necrosis, hemorrhage, pseudocyst), or respiratory complications
  • Pancreatitis due to trauma, gallstones or postsurgical

With regard to enteral nutrition (EN), nasoenteric tubes were not placed during the first 48 hours, but preexisting enteral tubes were used. So, most patients were orally fed. With regard to IV fluids, 62% received 1.5-2 times the maintenance IVF during the first 24 hours of admission.  More than 90% of cases received dextrose 5% normal saline. Key Findings:

  • Length of stay was 2.9 days in the early EN group compared with 4.4 days in the NPO group (P <.0001).  It is noted that the NPO group did include 24% with severe acute pancreatitis compared with 6% in the early EN group.
  • The authors did not identify any change in measured outcomes based on high or low volume IVF.

From the discussion:

  • “EN remains an integral part of management which has been associated with a lower incidence of infection, multiorgan failure, lower mortality rates, and a shorter hospital stay in adult patients with AP [acute pancreatitis]”
  • “Our study shows that oral feeds represent a safe and a feasible strategy in mild AP.” There was not an increase in readmission rates within 72 hours of discharge, either.

Because this is a retrospective study, this limits the interpretation of these findings; there could be an element of reverse causation with regard to the outcomes.

My take: Increasing evidence supports the practice of early enteral feedings in mild acute pancreatitis.  The exact IV fluids to use remain unclear, though my preference is lactated ringer’s based on ERCP-induced pancreatitis studies.

Related blog posts:

  • Why an ERCP Study Matters to Pediatric Care | gutsandgrowth This post explains why LR may be best.
  • Nutrition University / gutsandgrowth What are the nutritional management recommendations for acute pancreatitis? Justine Turner indicated that too many centers continue to rely on parenteral nutrition.  Yet, guidelines recommend the use of enteral nutrition due to lower risk of poor outcomes (eg. infections when NPO and on parenteral nutrition). ‘Resting pancreas is not helpful.’ With acute pancreatitis, enzyme secretion is reduced.  Her approach is to start nasogastric (NG) feedings at about 24 hours after presentation, as long as hemodynamically stable.  She indicated that nasojejunal (NJ) feedings can be done if NG is not well-tolerated.  NJ feedings are effective at reducing enzyme secretion.  However, Praveen Goday stated that his practice was often starting with NJ feeds.  “Sometimes there is only one shot” before the ICU team starts HAL.  Both physicians indicated that polymeric formulas were probably acceptable; however, starting with semi-elemental or elemental feedings are often done, again as a practical matter to minimize the likelihood of reverting to parenteral nutrition.
Artist Point, Yellowstone

Artist Point, Yellowstone

1000th Tweet: GI Symptoms Preceding IBD Diagnosis

Another milestone for this blog: since 2012, the blog has been publicized on twitter; this is the 1000th tweet. It is also 1314th blog post over nearly 4 years.

A recent study (H Singh et al. Clin Gastroenterol Hepatol 2015; 13: 1302-09) indicates that children with inflammatory bowel disease (IBD) were more likely to have gastrointestinal symptoms in each of the 4 years before the diagnosis of IBD than children without IBD.

In this study, the researchers identified all children with IBD from a population-based Manitoba database; Manitoba had a population of 1.27 million in 2012.  651 children were matched with 5950 controls without IBD.  The study’s Table 1 & 2 indicates that children with IBD had increased clinic visits prior to diagnosis:

  • 54-66 months prior: standardized rate ratio for number of ambulatory visits 1.15; & for ≥1 visit due to GI symptoms odds ratio 1.44
  • 42-54 months prior: standardized rate ratio for number of ambulatory visits  1.22; & for ≥1 visit due to GI symptoms odds ratio 2.05
  • 30-42 months prior: standardized rate ratiofor number of ambulatory visits 1.19; & for ≥1 visit due to GI symptoms odds ratio 2.16
  • 18-30 months prior: standardized rate ratio for number of ambulatory visits 1.23; & for ≥1 visit due to GI symptoms odds ratio 2.93
  • 6-18 months prior: standardized rate ratio for number of ambulatory visits  1.15; & for ≥1 visit due to GI symptoms odds ratio 5.23

There was not a clear trend in increased symptoms between those who developed Crohn’s disease compared with Ulcerative Colitis. In addition, the study noted a trend towards decreased colectomy and resective surgery in Crohn’s in the time period 2002-2010 compared with 1987-2001.  One limitation of this study is the few number of pediatric gastroenterologists in Manitoba (only 1 before 2003); the lack of pediatric gastroenterology availability could impact timely diagnosis.

My take: This data shows that GI symptoms still predate diagnosis in many children and indicate a potential for diagnosis delay. The authors note that noninvasive tools like stool calprotectin have not been widely adopted (at least in Manitoba) and could be helpful in reducing diagnostic delays.

Estes Park, Colorado

Estes Park, Colorado

Latest News: ‘Georgia Girl Saved by Fecal Transplant’

For those not able to see the live presentation…

GI Care for Kids physician, Jeff Lewis, helped bring fecal microbiota transplant (FMT) to Georgia. Here’s a success story from Fox5 Atlanta from August 31, 2015.  Here’s the link:

Georgia Girl Saved by Fecal Transplant  This link includes a 4:08 video and written summary as well.

From Twitter:

Screen Shot 2015-08-31 at 6.38.42 PM


Higher Stool Infliximab Correlates with Poor Response in Severe Ulcerative Colitis

A recent study (full text link: “Loss of Infliximab into feces is associated with lack of response to therapy in patients with severe ulcerative colitis” Gastroenterol 2015; 149; 350-55.e2) provides information about patients with ulcerative colitis who do not respond well to infliximab therapy.

In this study, the authors obtained fecal samples from 30 consecutive patients with moderate to severe UC during the 1st 2 weeks of therapy.  In addition, they obtained serum infliximab levels as well as assessed clinical and endoscopic response at 2 weeks, 8 weeks, and 3 months after treatment began.

Key findings:

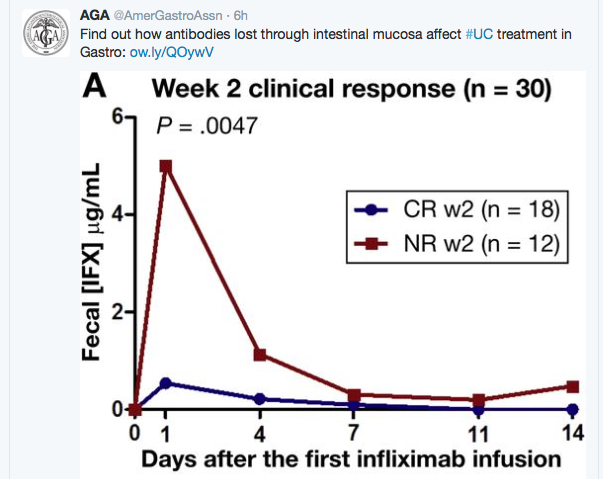
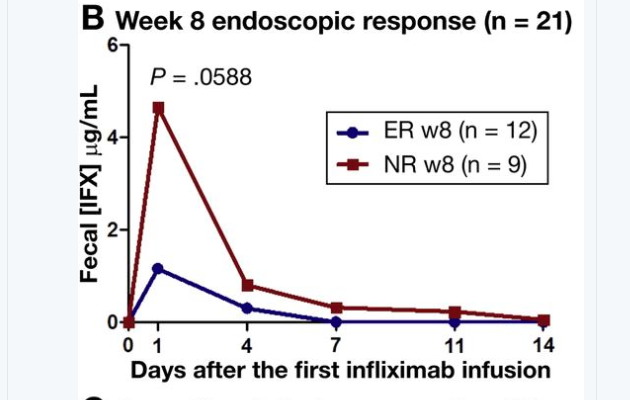
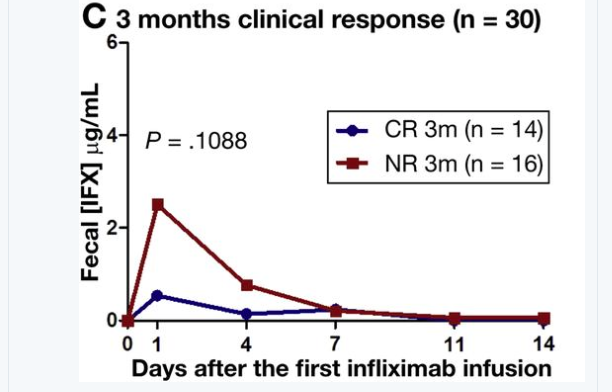
  • Fecal infliximab was detected in 129 of 195 (66%) samples.  The greatest loss was observed approximately 2 days after infusion. Low serum albumin was associated with greater infliximab levels in the stool.
  • Clinical nonresponders at week 2 had significantly higher fecal infliximab
  • The authors did not observe a correlation between fecal and serum infliximab concentrations.  However, it is possible that stool losses could indicate lower mucosal concentrations of infliximab.
From AGA twitter account

From AGA twitter account

From AGA twitter account

From AGA twitter account

From AGA twitter feed

From AGA twitter feed

Bottomline: It is not clear whether stool losses of infliximab directly contribute to drug failure or whether the loss is another biomarker of disease activity/high-risk patients.

The study authors note that “intestinal loss of IFX in moderate to severely active UC is associated with a diminished response to this treatment.  Patients with severe disease can, therefore, benefit from more intensive dosing regiments. This strategy warrants a prospective clinical trial.”

Related blog posts:

Head-to-Head: Nutritional Therapy versus Biological Therapy in Pediatric Crohn’s Disease

The best data to date: D Lee et al. Inflamm Bowel Dis 2015; 21: 1786-93. In this prospective study, the authors studied treatment initiation in children (N=90), comparing partial enteral nutrition (PEN, n=16), exclusive enteral nutrition (EEN, n=22), and anti-TNF therapy (n=52).

Results:

  • Clinical response, defined by PCDAI reduction ≤15 or final PCDAI ≤10, was achieved by 64% PEN, 88% EEN, and 84% anti-TNF.
  • Fecal calprotectin ≤250 noted in 14% PEN, 45% EEN, and 62% anti-TNF

Because of the discrepancy between EEN and PEN, the authors speculate that the “efficacy of EEN may be a consequence of elimination of table food rather than providing a uniquely therapeutic method of delivering nutrients.”  They note that “choice of formula has not impacted the efficacy of enteral nutrition.”

More extensive information on this subject: D Lee et al. Gastroenterol 2015; 148: 1087-1106.

Bottomline: Anti-TNF therapy was as effective or more effective than EEN. And, “for patients who prefer treatment with a nutrition-based therapy, EEN seems superior to PEN.”

Related blog posts:

Street Art, NYC

Street Art, NYC

Is Appendicitis No Longer a Surgical Emergency?

A recent study indicates that a fairly high number of adults with appendicitis could avoid surgery (JAMA 2015 June 15 [doi:10.1001/jama.2015.6154]).

In this study, patients with CT-confirmed acute uncomplicated appendicitis were randomly assigned to either immediate surgery (n=273) or a 1-day of IV ertapenem followed by 7 days of levofloxacin and metronidazole.

Here’s a summary of the study –from GIHepNews: Antibiotic therapy an option for acute appendicitis  Here’s an excerpt:

The primary endpoint for the antibiotic group – resolution of acute appendicitis with no recurrences for a full year – occurred in 73%. The remaining 27% of patients in this group underwent appendectomy during follow-up, at a median of 102 days after initial presentation. None of these patients developed abscesses or serious infections, “suggesting that the decision to delay appendectomy … can be made with a low likelihood of major complications,” the investigators said 

And commentary from Edward Livingston, M.D., is deputy editor of JAMA. Corrine Vons, M.D., Ph.D., is in the digestive surgery department at Jean-Verdier Hospital, Bondy, France. :

The study findings dispel the notion that appendectomy is always an emergency and suggest instead that, given our current precise diagnostic capabilities and effective wide-spectrum antibiotics, a trial of antibiotic therapy is reasonable. However, it’s important to note that children, adolescents, pregnant women, and patients with complications were excluded from this trial so the findings do not apply to those patient groups.

Dr. Livingston and Dr. Vons made these remarks in an editorial accompanying Dr. Salminen’s report (JAMA 2015;313:2327-8).

My Take: This study indicates, at least in adults with uncomplicated appendicitis, that antibiotic treatment is an option. I think resolving the problem definitively would be my preference.  If you had appendicitis, which therapy would you choose? Take the poll.

Related blog post:

This is Analogous to 'Negative' Studies

This is analogous to ‘negative’ studies


What Will They Think of Next? A Vomit Machine for Studying Norovirus!

A summary of a recent report from NBC news:

Yuck! Vomit Machine Shows Why Norovirus Spreads So Fast

Here’s an excerpt:

They used another virus called MS2 that’s similar to norovirus, that doesn’t make people sick and that’s easy to grow in the lab.,,

“We think that there’s a at least a million particles released in a vomiting event and maybe more.”

Not all of it goes into the air. In fact, very little did in their experiments. But it was enough. They estimate that as many as 13,000 virus particles can be released into the air with a single retch. They made a video that shows how it works.

“There was evidence of aerosolized MS2 after every simulated vomiting episode,” they wrote in their report, published in the Public Library of Science journal PLoS ONE.

People can be infected with as few as 20 to 1,300 microscopic viral particles, so their study shows that vomiting could indeed spread the infection through the air….

“WHEN ONE PERSON VOMITS, THE AEROSOLIZED VIRUS PARTICLES CAN GET INTO ANOTHER PERSON’S MOUTH AND, IF SWALLOWED, CAN LEAD TO INFECTION.”

“There are 21 million cases of human norovirus infection in the U.S. each year, and this virus genus is now recognized as the leading cause of outbreaks of acute gastroenteritis,” the researchers wrote.

It kills up to 800 people a year in the U.S. alone and puts 70,000 into the hospital, so understanding how it spread sand finding ways to stop it could prevent many illnesses, the researchers said.

Related blog posts:

Spice It Up? Curcumin for Ulcerative Colitis

This past week I’ve been on call and had not finished a few articles.  One article that was on the to do list: A Lang et al. Clinical Gastroenter Hepatol 2015; 13: 1444-9.

I’ve read it now.  However, even before finishing the article, I read a few good summaries of this article, including one from my colleague Stan Cohen/Nutrition4Kids: Curcumin Helps (A Lot) in Ulcerative Colitis

Here’s an excerpt:

The cover of a prestigious medical journal shows a pile of curcumin and over it, the announcement reads: Curcumin Helps Induce Remission in Mild-to-Moderate Ulcerative Colitis.  That’s big news for a lot of reasons: first, this Indian spice (derived from tumeric) is inexpensive and well-tolerated; second, in a well-designed scientific study, curcumin showed that it was more effective than some medicines; and third, it showed, again, that careful trials of long-used herbs can be done with important results being shown.  Again, because an earlier study (H Hanai, Clinical Gastroenterology 2006, pages 1502-6) had previously shown that curcumin can help keep ulcerative colitis (UC) patients from flaring for up to 12 months. 

This new study (A Lang, Clinical Gastroenterology 2015, pages 1444-9) compared curcumin to a placebo in patients who were not doing well on the standard therapy (mesalamine) for mild to moderate UC.  With a single daily dose of 3 grams of curcumin in capsule form, 65% responded (compared to 12% with a placebo) and 54% actually went into remission, having essentially no symptoms.  Perhaps even, more importantly, 38% of those taking the curcumin showed improvement in the intestinal tissue when a colonoscopy was performed.  That’s comparable or better than some of the medications that are being used.

A few other details: The researchers used a product called Cur-Cure from Bara Herbs Inc (Yokneam, Israel).  Also, the associated commentary in the same journal by CN Bernstein (pages 1450-52) suggests that the study may have targeted mild ulcerative colitis (rather than moderate ulcerative colitis). He comments that the increasing rates of ulcerative colitis among Indian immigrants could be related to including less curcumin in their now more westernized diets.  He also notes, as did Dr. Cohen, that there were previous promising studies dating back to 2006.  Why has it taken nine years for this report?

My Take: This is probably an article worth reading.  Although curcumin appears promising, I worry that a lack of financial incentive may hamper research efforts to better define its place as an agent for treatment of ulcerative colitis.

Related blog posts:

Curcumin

This has been a sad week in our office.  Here are links to two poems that come to mind: