Stick with the (intestinal) rehab program?

More data on the progress of treatment of short bowel syndrome (SBS) programs:

  • Avitzur J, et al. JPGN 2015; 61: 18-23

In this study, the researchers from Toronto and the Group for Improvement of Intestinal Function and Treatment (GIFT) retrospectively examine 84 patients over 3 time periods: 1999-2002, 2003-2005, and 2006-2009.

Key points:

  • Across those time periods, the authors find fewer SBS patients that needed to be listed for transplantation despite similar baseline characteristics.  In addition, many more patients in the late period were removed from the transplant waiting list due to clinical improvement.
  • Another important finding was a drop in mortality (15% vs >60%) and a shift from previous causes like liver failure and sepsis to death from other comorbid conditions.
  • “Since 2009, we have performed only 1 IT [intestinal transplant].”  They note this is a worldwide trend with ~50% reduction in pediatric IT since 2008.
  • Even with ultrashort bowel (small bowel length <30 cm), there are reports that “50% of these patients achieved PN independence within 2 years.”  As such, this is a declining indication for IT listing. In this study, ultrashort bowel was the reason for listing in 11% in the last period compared 21% in the first time period.

Why is this happening?

The authors credit the intestinal rehab program (IRP) for this impact along with specific management changes including new lipid emulsions/lipid minimization to reduce IFALD, use of ethanol locks to reduce bloodstream infections, and bowel reconstructive procedures (e.g. STEP).

Briefly noted: Merras-Salmio L, Pakarinen MP. JPGN 2015; 61: 24-9. This second retrospective study (n=48) from Finland reinforces the view of improvements in cholestasis  and prognosis from 1988-2014.  Similar strategies, as noted above, were implemented in SBS management protocols.

Bottomline: The outlook has improved for SBS.  While this is good news, at the same time, there will be less pediatric gastroenterologists with extensive intestinal transplantation experience.

In Wyoming often there are stretches of nearly deserted highways

In Wyoming often there are stretches of nearly deserted highways

Related blog posts:

Looking Twice for Eosinophilic Esophagitis

Not only do you have to take a lot of esophageal biopsies, now you may need to call your pathologist to make sure you do not miss a case of eosinophilic esophagitis (EoE), especially if there are mildly increased eosinophils.  At least, that’s the message I inferred from a recent study (Rothenberg ME, et al. JPGN 2015; 61: 65-8).

In this study, the researchers identified 477 biopsies from 429 patients with EoE; 316 were from “PPI confirmed patients.”

Key finding: Of the 477 biopsies, 106 had a peak count of between 1 and 14 eos/hpf cited in the pathology report.  However, 23/106 (22% with 1-14 eos/hpf) had ≥15 esos/hpf after a second review.

Overall, 5% of the 477 biopsies were mischaracterized as not meeting the threshold of ≥15 esos/hpf prior to review.  Given this frequency at a major medical center and frequent referral center for EoE, my suspicion is that the yield of a 2nd look would be at least as high in most other centers.

Take-home point: Look twice for EoE if eosinophil count is between 1/hpf and 14/hpf. Maybe some new diagnoses are being missed and maybe some of your EoE patients in histologic remission really aren’t.

Related blog posts:

Grand Tetons from Jenny Lake

Grand Tetons from Jenny Lake

Celiac Disease and Neuropathy

From GI & Hep News: Celiac Disease Associated with 2.5-fold Risk of Neuropathy

Here’s an excerpt:

The use of Swedish population registries enabled first author Dr. Sujata P. Thawani of Columbia University, New York, and her colleagues to find that the risk of neuropathy was increased both before and after a diagnosis of celiac disease (CD).

“We found an increased risk of neuropathy in patients with CD that persists after CD diagnosis. Although absolute risks for neuropathy are low, CD is a potentially treatable condition with a young age of onset. Our findings suggest that screening could be beneficial in patients with neuropathy,” they wrote (JAMA Neurol. 2015 May 11 [doi:10.1001/jamaneurol.2015.0475]).Neuropathy has a known association with CD, an immune-mediated disorder characterized by sensitivity to gluten with an incidence of about 1% in Western Europe…

Dr. Thawani and her associates used Swedish pathology registers to identify individuals whose small intestine biopsies showed villous atrophy between 1969 and 2008 (Marsh stage 3, n = 28,232)…Each CD patient was matched with up to five age- and sex-matched controls (n = 139,473) from the Swedish Total Population Registry, all of whom were diagnosed in the same year and were from the same county as the matched CD patient. 

Although 41.7% of CD patients were diagnosed in childhood, the median age at diagnosis was 29 years…

Surveillance bias may account for some of the increased risk for neuropathy…Notably, though, patients with a prior neuropathy diagnosis also were more likely to be diagnosed with CD, showing a bidirectional relationship. 

Grand Tetons

Grand Tetons

Rejected! Most Stool is Not Good Enough for FMT

I found a recent study (Paramsothy S. Inflamm Bowel Dis 2015; 21: 1600-06) interesting in that it shows how few individuals would qualify as long-term stool donors for fecal microbiata transplantation (FMT).  In previous discussions with colleagues, I’ve thought that getting paid to donate stool would be a pretty sweet deal.

In this study, the authors examined 116 potential donors.  The donor screening protocols and donor inclusion/exclusion criteria were similar to many others (outlined in their Tables 1, 2 and 3 & noted in previous gutsandgrowth blog post on FMT). What the researchers found is that 47 prospective donors declined to participate after learning the requirements and only 12 of the remaining 69 (17%) remained eligible after concluding screening; this represents only 10% of the initial cohort.  A large proportion of healthy asymptomatic donors failed stool testing –40% of those tested. The next most common reasons for rejection were medication comorbidities (n=13) or risk factors for Creutzfeldt-Jakob disease (n=6).

Bottomline: Now, I realize how these stool donors should be justifiably proud of their carefully-balanced uncontaminated microbiome.  The difficulty in identifying suitable donors further reinforces the value of human stool banks.

Briefly noted:

Vandenplas Y, et al. “Fecal Microbiota Transplantation: Just a Fancy Trend? JPGN 2015; 61: 4-7.  Brief overview which includes screening protocol used in Brussels.  One of the recommendations is to conserve a sample of the donated stool for >30 years.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Cumberland Island

Cumberland Island -Main Road

Not Using and Stopping Therapy in IBD

Two recent articles show that a lot of patients are not receiving much therapy in inflammatory bowel disease.

  • Moreno-Rincon E et al. Inflamm Bowel Dis 2015; 21: 1564-71.
  • Melesse DY et al. Inflamm Bowel Dis 2015; 21: 1615-22.

In the first article, a multicenter retrospective study of 102 patients, the authors examined the relapse rates of patients with ulcerative colitis who had withdrawal of thiopurines.  They defined “significant clinical relapse” (SCR) as “the occurrence of UC typical signs or symptoms requiring a rescue therapy such as oral or intravenous corticosteroids, biological therapy, immunosuppressant drugs, recapture with TP [thiopurine] or surgery.”

Key findings:

  • Overall SCR was 32.35%.
  • Predictors of relapse included pancolitis (HR 5.01) and duration of treatment with thiopurines (HR 0.15).

Among those without relapse, the mean duration of remission prior to withdrawal of thiopurines was 54 months compared with 34 months in those who relapsed. In figure 2, the authors note that the rate of relapse was 19.2% for those who received >48 months of thiopurine treatment compared with a 45% rate of relapse for those who received treatment for 13-47 months.  The authors note that several studies have shown higher relapse rates than reported in this cohort and that interruption of therapy is associated with a considerable risk of relapse.

Limitations: small retrospective study and the expectation that their SCR would capture the true relapse rate.

The second study, using a Manitoba database, shows a strikingly-high rate of nonuse of medical therapy. Between 1996-2012, 3902 patients with IBD were identified; 47% with Crohn’s disease (CD) and 53% with ulcerative colitis (UC).  While only 11.7% of IBD patients did not have medication dispensed in the first year after diagnosis, beyond this period, “roughly half of all patients with IBD have not used IBD-specific medications in the previous year.”  The authors are not certain how much nonuse is due to nonadherence or nonprescription. They note that there was higher nonuse in patients with CD, possibly due to use of surgical treatment.  However, they note that multiple medications have been shown to reduce postsurgical relapse in CD.

My take: There are a lot of patients off therapy, both due to withdrawal of therapy when doing well and others due to nonadherence or nonprescription.  With or without overt symptoms, these studies make one wonder whether undertreatment will lead to long-term complications or whether there could be a significant number of patients who are overtreated.  Either way, it remains quite difficult to predict which patients will do well off medical therapy.

Broadcasters Really Know the Key Points to Winning!

Broadcasters Really Know the Key Points to Winning!

What HBV Testing is Needed Before Tumor Necrosis Factor Inhibitor Therapy

As noted in a previous blog post (What’s Going on with Hepatitis A and Hepatitis B?):

Hepatitis B Reactivation risk & recommendation: (For all of the specifics — Full text article link)

  • High risk of reactivation (>10%): B cell depleting agents (eg. rituximab, ofatumumab), anthracycline derivatives (eg. doxorubicin, epirubicin), and daily moderate to high dose steroids (>10 mg) for at least 4 weeks. Recommendation: Use HBV prophylaxis
  • Moderate risk of reactivation (1-10%): anti-TNF therapy, integrin inhibitors (eg. ustekinimab, vedolizumab), tyrosine kinase inhibitors, low-dose steroids daily (<10 mg/day) for at least 4 weeks.  Recommendation: Use HBV prophylaxis if HBsAg-positive but not if only anti-HBc-positive
  • Low risk of reactivation (<1%): azathiopurine, 6-mercaptopurine, methotrexate. Recommendation: No antiviral prophylaxis required.

For those interested in a more detailed summary of the recommendations: AGA Website HBV Reactivation Recommendations

In line with the reactivation risk, a new study (and editorial) (M Barone et al. Hepatology 2015; 62: 40-6; editorial BP Perillo. Hepatology 2105; 62: 16-8) indicates that for those receiving tumor necrosis inhibitor (anti-TNF) monotherapy, hepatitis B screening requires only checking HBsAg. The study examined a total of 1218 Caucasian rheumatologic patients (receiving biologic agents) between 2001-12. In this cohort, the authors identified 179 patients who had a previously resolved HBV infection; 146 treated with anti-TNF, 14 with rituximab, and 19 with other biologic therapy. Key finding: HBV reactivation was not seen in these patients.

Bottomline: For most pediatric patients receiving anti-TNF monotherapy (eg. infliximab, adalimumab), screening with HBsAg alone should suffice.

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Grand Tetons from Jackson Lodge

Grand Tetons from Jackson Lodge

Is It Right? Anti-TNF Therapy Does Not Fix IBD-Related Anemia

A surprising study (Koutroubakis, IE et al. Inflamm Bowel Dis 2015; 21: 1587-93) of prospectively-collected data from 430 patients with inflammatory bowel disease (IBD) showed that the rate of anemia did not change after 1 year in patients treated with anti-tumor necrosis factor (anti-TNF) therapy and oral iron.

The data was derived from 2010-2012 and included 324 patients with Crohn’s disease (51.6% females) with a median age of 41 years.  Anemia was defined as hemoglobin (Hb) <13 g/dL in men and <12 g/dL in women.  Patients with Hb <10 g/dL were considered to have severe anemia. Key findings:

  • Prevalence of anemia in IBD patients treated with anti-TNF was 38.1% at baseline and then 36.6% at 1 year.
  • Severe anemia was identified in 10% at baseline and 9.9% at 1 year.
  • A hematopoietic response with a Hb ≥2 g/dL was observed in 33.6% (n=45 of 134 anemic patients) and 14 (40%) of those with severe anemia.
  • There were 45 new anemic patients at 1 year; 64.4% were nonresponders to anti-TNF treatment.
  • Using multivariate logistic regression analysis, the author noted that use of immunomodulators was associated with an odds ratio of 2.56 of improvement in hemoglobin levels.

The authors state that anemia is the most common extra intestinal manifestation of IBD and remains underappreciated.  Anemia in IBD correlates with the extent of intestinal disease and activity.

Bottomline: “Use of anti-TNF therapy had only a modest effect on patients’ Hb level.”

From related post: IBD Update January 2015 (Part 2)

Inflamm Bowel Dis 2014; 20: 2266-70.  This study with 749 patients from Sweden showed that a large number of inflammatory bowel disease patients did not receive with iron supplementation: “Only 46% of patients with anemia were treated with iron supplementation or blood transfusion.”  This study showed frequent persistence of anemia one year after diagnosis, especially in children. At time of diagnosis, 55% of children and 27% of adults had anemia and 28% and 16% at one year followup, respectively.

My take: Treatment of the underlying IBD, often helps anemia.  However, in some patients treating the anemia with iron may help improve symptoms as much or more than other aspects of treatment.

Related blog post: Microcytic Anemia Review | gutsandgrowth

Sandy Springs, Georgia

Sandy Springs, Georgia


Ulcerative Colitis with Questionable Response to Fecal Transplant

Fecal microbiota transplantation (FMT) is not going to be a “magic bullet” for most patients with inflammatory bowel disease. So far, it is unclear whether FMT works at all.  A recent study (full text link: Rossen NG et al. Gastroenterol 2015; 145: 110-8) with only 37 patients echo that experience. Here is the abstract:

Background & Aims

Several case series have reported the effects of fecal microbiota transplantation (FMT) for ulcerative colitis (UC). We assessed the efficacy and safety of FMT for patients with UC in a double-blind randomized trial.

Methods

Patients with mild to moderately active UC (n = 50) were assigned to groups that underwent FMT with feces from healthy donors or were given autologous fecal microbiota (control); each transplant was administered via nasoduodenal tube at the start of the study and 3 weeks later. The study was performed at the Academic Medical Center in Amsterdam from June 2011 through May 2014.

The composite primary end point was clinical remission (simple clinical colitis activity index scores ≤2) combined with ≥1-point decrease in the Mayo endoscopic score at week 12. Secondary end points were safety and microbiota composition by phylogenetic microarray in fecal samples.

Results

Thirty-seven patients completed the primary end point assessment. In the intention-to-treat analysis, 7 of 23 patients who received fecal transplants from healthy donors (30.4%) and 5 of 25 controls (20.0%) achieved the primary end point (P = .51). In the per-protocol analysis, 7 of 17 patients who received fecal transplants from healthy donors (41.2%) and 5 of 20 controls (25.0%) achieved the primary end point (P = .29). Serious adverse events occurred in 4 patients (2 in the FMT group), but these were not considered to be related to the FMT. At 12 weeks, the microbiota of responders in the FMT group was similar to that of their healthy donors; remission was associated with proportions of Clostridium clusters IV and XIVa.

Conclusions

In this phase 2 trial, there was no statistically significant difference in clinical and endoscopic remission between patients with UC who received fecal transplants from healthy donors and those who received their own fecal microbiota, which may be due to limited numbers. However, the microbiota of responders had distinct features from that of nonresponders, warranting further study. ClinicalTrials.gov Number: NCT01650038.

Related blog posts:

Cumberland Island

Cumberland Island


New Therapy for Celiac Disease: Larazotide Acetate

A recent randomized controlled trial study (Gastroenterol 2015; 148: 1311-9) examined the effectiveness of larazotide acetate in 342 adults with Celiac disease (CD) who had ongoing symptoms despite the use of a gluten-free diet for at least 12 months.

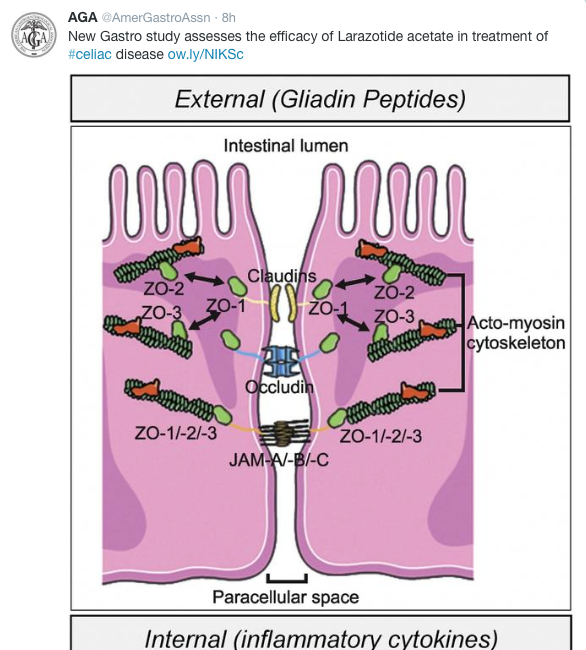
Larazotide acetate is a locally acting, nonsystemic 8-amino acid oral peptide which is a tight junction (TJ) regulator.  “Larazotide acetate appears to prevent opening of intestinal TJs by promoting TJ assembly and actin filament rearrangement, which prevents gluten from reaching the intestinal submucosas and triggering an inflammatory response.”

Screen Shot 2015-06-01 at 8.35.51 PM

Patients received either placebo, 0.5 mg, 1 mg, 2 mg three times daily. The majority of patients had normalized serology at the start of the study.  Key findings:

  • “The 0.5 mg dose showed a 26% decrease in celiac disease patient-reported outcome symptomatic days (P =.017), a 31% increase in improved symptom days (P =.034), a 50% or more reduction from baseline of the weekly average abdominal pain score for 6 or more of 12 weeks of treatment (P =0.022), and a decrease in the nongastrointestinal symptoms of headache and tiredness (P =0.010).”
  • The 1- and 2-mg doses were no different from placebo for any end point.
  • Safety was comparable to placebo.

The authors state that is unclear why the higher doses were not effective “but may involve peptide aggregation … reducing activity in vivo.”

Bottomline: There would be a benefit for an adjunct to a gluten-free diet due to the difficulty in adherence and due to ongoing symptoms in some despite the use of a GFD; in some cases, symptoms may be induced by inadvertent deviation from GFD.  More data is needed to determine if larazotide acetate will be useful in this role.

Related blog post: Good Educational Two Minute Celiac Video | gutsandgrowth

The Connection Between Anxiety and Gastroesophageal Reflux Disease

Why is it that reflux is so much worse during periods of anxiety and depression?

A recent prospective study (Kessing BF et al. Clin Gastroenterol Hepatol 2015; 13: 1089-1095) of 225 consecutive patients with symptoms of gastroesophageal reflux disease (GERD) looks into this issue.  All patients underwent ambulatory 24-hour pH-impedance (pH-MII) monitoring and had assessment of anxiety/depression with the Hospital Anxiety and Depression Scale.

GERD was defined by having pathologic acid exposure time and/or positive temporal correlation between the occurrence of symptoms ad reflux episodes. Hypersensitivity to reflux was considered if there was physiologic acid exposure times while having temporal association between reflux episodes and symptoms.  Functional heartburn indicated the presence of symptoms with a normal pH-MII.

Key findings:

  • 147 patients had GERD and 78 had functional heartburn; 36 patients were considered hypersensitive to gastroesophageal reflux.
  • Among patients with GERD (including patients with hypersensitivity), increased anxiety/depression levels were associated with more severe retrosternal pain/burning. However, anxiety/depression were NOT associated with an increased number of reflux episodes or number of symptoms reported on pH-MII.
  • Patients with functional heartburn had higher levels of anxiety than patients with GERD.

Bottomline: Anxiety is associated with increased GERD symptoms.  In addition, anxiety is more prevalent in patients with functional heartburn.

Briefly noted: Review (Lipa S, et al. Clin Gastroenterol Hepatol 2015; 13: 1058-67) of 4 trials with 153 analyzed patients:  “Stretta [radiofrequency ablation] for patient with GERD does not produce significant changes, compared with sham therapy, in physiologic parameters, including time spent at pH less than 4, LESP, ability to stop PPIs, or HRQOL.”.

Related blog posts:

Cumberland Island

Cumberland Island