Do You Know How Long to Use Antibiotics for Intraabdominal Infections?

Since 2010, there have been published guidelines for complicated intraabdominal infections which recommend a treatment course of 4 to 7 days. These include guidelines from the Surgical Infection Society (SIS) and the Infectious Diseases Society of America (IDSA). Now, a new study (Sawyer RG et al. NEJM 2015; 372: 1996-2005, editorial 2062-63) provides additional support for a short course of antibiotics when there is adequate source control. The study termed “Study to Optimize Peritoneal Infection Therapy” or STOP-IT included 23 institutions from the U.S. and Canada.

Video Summary (1:33): Trial of Short-Course Antimicrobials

Rationale: While traditional therapy of 10-14 days has been based on the premise that ongoing fever and leukocytosis indicate ongoing infection, “more recent experimental data, however, suggest that a prolonged SIRS [systemic inflammatory response syndrome] may be more a reflection of host immune activity than an indication of the presence of viable microorganisms.”

Design: 518 patients were randomly assigned to either a fixed 4-day course of antibiotics or to a control group that received antibiotics for 2 days after resolution of fever, leukocytosis, and ileus (max of 10 days).  The median number of days in the control group was 8 days.

Study characteristics:

  • Mean age 52 years
  • 34% of the infections originated in colon/rectum, 14% in small bowel, and 14% in the appendix
  • 11% had cancer, 10% had inflammatory bowel disease

Source-control procedures: “defined as procedures that eliminate infectious foci, control factors that promote ongoing infection, and correct or control anatomical derangements to restore normal physiological function”

  • Percutaneous drainage 33.1%
  • Resection and anastomosis or closure 26.5%
  • Surgical drainage alone 21.2%
  • Resection and proximal diversion 10.4%
  • Simple closure 7.7%
  • Surgical drainage and diversion 1.2%

Results:

  • Surgical site infection, recurrent intraabdominal infection, or death occurred in 21.8% of the experimental 4-day group compared with 22.3% of the control group. Death occurred in 3 experimental patients and 2 control patients.
  • No significant differences were found between the two groups in terms of primary or secondary outcomes.

Limitations:

  • 18% of the experimental group and 27% of the control group deviated from the protocol.  In the control group, this included 26 patients who received less than 10 days of therapy but more than 2 days longer than the resolution of the physiological findings.
  • Patients without adequate source control were excluded

The editorial notes that if these findings are incorporated into clinical practice, more than $97 million would be saved on antibiotic costs alone; in addition, there would be less diarrhea and phlebitis.  The editorial suggests that the reason why more than 20% of both groups had complications is likely related to source control.  If inadequate course of antibiotics was the culprit, “we would have expected still more complications after treatment in the short-course therapy group.”

(From editorial): “We have encouraging data from the STOP-IT trial that suggest cost savings and improved safety.”

Take-home message Because of years of practice patterns, it is going to be difficult to stop antibiotics at 4 days when patients are still having fevers, especially since 20% will not have resolution of their infection. These data should, however, make it easier to shorten antibiotic courses.

Related blog posts:

Zoo Atlanta

Zoo Atlanta

IBD Shorts -Skin, Adalimumab Kinetics

From the IMAgINE study with 192 pediatric patients (Sharma S et al. Inflamm Bowel Dis 2015; 21: 783-92), the authors determined levels for adalimumab, that at week 52, were associated with remission and response.  A cutoff level of 3.6 mcg/mL had a sensitivity of 32.7%  and specificity of 88.6% for predicting remission; the same cutoff had a sensitivity of 46.2% and specificity of 83% for predicting a response.  Overall, the authors noted dose proportionality with patients who received higher (or more frequent) doses with higher serum levels.

Related posts:

“Concomitant Use of Azathioprine/6-Mercaptopurine Decreases the Risk of Anti-TNF-Induced Skin Lesions” (Soh JS et al. Inflamm Bowel Dis 2015; 21: 832-9). Among a cohort of 500 Korean patients, the incidence of psoriaform and eczematiform lesions was 6.2%.  Concomitant use of a thiopurine was associated with a hazard ratio of 0.452 (lower risk) for developing these adverse skin reactions.

Related posts:

Helicobacter Pylori: Relationship to Cancer and Dubious Beneficial Claims

I found a recent review (Gastroenterol 2015; 148: 719-31) regarding Helicobacter pylori (HP) of interest.  David Graham explores the issue of HP eradication with regard to cancer and whether there are benefits to the infection that result in detrimental effects with HP eradication.

The potential mechanisms in which HP infection can increase the risk of gastric cancer are depicted in Figure 2; the most important:

  • Inflammation induced by infection
  • Genetic/epigenetic changes –> genetic instability in gastric epithelial cells

Lessons regarding eradication therapy:

  • Sequential therapy has been shown in some studies to be effective/superior (in Italy) yet inferior in others (eg. Korea).  “The results are explained entirely by differences in patterns of drug resistance, which typically were not assessed before studies were initiated.”
  • Findings from many studies cannot be applied to other populations without resistance data.

Does HP infection reduce the risk of obesity or childhood asthma?  Probably not.

  • “Any claim that a major human pathogen also might provide a meaningful health benefit, and that plans to eradicate it should be reconsidered, is guaranteed to elicit interest from the press.”
  • As a counter example, Dr. Graham notes “because 2 events are associated does not mean that one causes the other. For example, one study reported a correlation between the number of storks in Brandenburg, Germany, and the birth rate in Berlin.” [Backen MB. Harm. In: Bracken MB. Risk, chance, and causation. New Haven: Yale University Press, 2013; 108-09.]
  • He notes that HP can both promote or inhibit acid secretion/acid reflux.  Increased acid secretion with resultant esophageal disease could increase the risk of adenocarcinoma of the esophagus; however, “the risk of developing adenocarcinoma of the stomach remains higher than the risk of adenocarcinoma of the esophagus.”  This indicates that if there is an increased esophageal cancer risk, eradication would still be favorable by lowering gastric cancer risk.
  • Asthma: “overall, the studies do not support the hypotheses that increases in childhood asthma were related to the absence of H pylori.”
  • Obesity: “A meaningful causative association between H pylori and obesity is unlikely.”
Screen Shot

Screen Shot

Take-home message: H pylori is a pathogen and should be treated as such.

Related blog posts:

University of Chicago

University of Chicago

Prospective Monitoring of Calprotectin for Crohn’s Disease

A recent study (full text link: Wright EK, et al. Gastroenterol May 2015 Volume 148, Issue 5, Pages 938–947) shows that stool calprotectin levels can be useful to monitor Crohn’s disease (Links from AGA twitter feed).  This study measured levels as part of The Post-Operative Crohn’s Endoscopic Recurrence (POCER) study.

Here’s the abstract, followed by some comments:

Background & Aims

Crohn’s disease (CD) usually recurs after intestinal resection; postoperative endoscopic monitoring and tailored treatment can reduce the chance of recurrence. We investigated whether monitoring levels of fecal calprotectin (FC) can substitute for endoscopic analysis of the mucosa.

Methods

We analyzed data collected from 135 participants in a prospective, randomized, controlled trial, performed at 17 hospitals in Australia and 1 hospital in New Zealand, that assessed the ability of endoscopic evaluations and step-up treatment to prevent CD recurrence after surgery. Levels of FC, serum levels of C-reactive protein (CRP), and Crohn’s disease activity index (CDAI) scores were measured before surgery and then at 6, 12, and 18 months after resection of all macroscopic Crohn’s disease. Ileocolonoscopies were performed at 6 months after surgery in 90 patients and at 18 months after surgery in all patients.

Results

Levels of FC were measured in 319 samples from 135 patients. The median FC level decreased from 1347 μg/g before surgery to 166 μg/g at 6 months after surgery, but was higher in patients with disease recurrence (based on endoscopic analysis; Rutgeerts score, ≥i2) than in patients in remission (275 vs 72 μg/g, respectively; P < .001). Combined 6- and 18-month levels of FC correlated with the presence (r = 0.42; P < .001) and severity (r = 0.44; P < .001) of CD recurrence, but the CRP level and CDAI score did not. Levels of FC greater than 100 μg/g indicated endoscopic recurrence with 89% sensitivity and 58% specificity, and a negative predictive value (NPV) of 91%; this means that colonoscopy could have been avoided in 47% of patients. Six months after surgery, FC levels less than 51 μg/g in patients in endoscopic remission predicted maintenance of remission (NPV, 79%). In patients with endoscopic recurrence at 6 months who stepped-up treatment, FC levels decreased from 324 μg/g at 6 months to 180 μg/g at 12 months and 109 μg/g at 18 months.

Conclusions

In this analysis of data from a prospective clinical trial, FC measurement has sufficient sensitivity and NPV values to monitor for CD recurrence after intestinal resection. Its predictive value might be used to identify patients most likely to relapse. After treatment for recurrence, the FC level can be used to monitor response to treatment. It predicts which patients will have disease recurrence with greater accuracy than CRP level or CDAI score.

Some key points from the discussion:

  • “The POCER study recently showed that postoperative endoscopic monitoring, together with treatment intensification for early recurrence, is superior to standard drug therapy alone in preventing disease recurrence, at least in the short term. However, such endoscopic monitoring is invasive, expensive, cannot be repeated frequently, and, in some patients, will yield a normal result.” [De Cruz, P., Kamm, M.A., Hamilton, A.L. et al. Crohn’s disease management after intestinal resection: a randomised trial. Lancet. 2014; (Epub ahead of print)]
  • The POCER study had all postoperative patients receive 3 months of metronidazole.  High-risk patients also received thiopurine or adalimumab (if thiopurine intolerant) therapy.  High-risk was defined as patients who were smokers, patients with perforating disease, or patients with 1 or more previous resections.
  • “In our study we have shown that FC concentration is increased markedly before surgery and decreases substantially after resection of all macroscopic disease at 6 months”
  • “The present study has shown that FC concentration is sufficiently sensitive to monitor for recurrence of Crohn’s disease, and has a high enough negative predictive value to be confident that few patients with recurrence will be missed.” The authors, though, recommend serial measurement rather than relying on a single assay.
  • Calprotectin: “At each time point in our study, a cut-off value of 100 μg/g had an NPV of 90% or greater, with the best combination of sensitivity and specificity.”
  • An important limitation of these findings is that patients had to have all macroscopic disease removed at the time of surgery.  Thus, these findings are not generalizable to patients with residual upper gastrointestinal disease.
  • “These results confirm the accuracy, utility and superiority of fecal calprotectin compared with CRP or CDAI as a monitoring tool and screening test for endoscopic recurrence of Crohn’s disease in the postoperative population.”

Additional summary of this information on AGA Journals blog:  Measurement of Fecal Calprotectin.  An excerpt:

In an editorial that accompanies the article, Alain M. Schoepfer and James D. Lewis explain that the role of fecal calprotectin in assessing post-operative recurrence has been debated because of inconsistent results in mainly small studies. The strengths of the study of Wright et al include its large size, prospective design, endoscopic validation, and longitudinal inter-individual measurements of fecal calprotectin.

Tests for biomarkers such as fecal calprotectin can be repeated more frequently than colonoscopies. This advantage could overcome the lower levels of sensitivity with which single measurements of biomarkers detect recurrence. Schoepfer and Lewis say that studies are needed to determine the optimal frequency for measuring fecal calprotectin.

However, they conclude that measurement of fecal calprotectin could have an important role in monitoring Crohn’s disease recurrence after intestinal resection; it is clearly superior to measurement of c-reactive protein or CDAI score.

Proposed algorithm for using calprotectin: In the editorial, they propose that patients with low or medium risk of “permanent bowel dysfunction as a consequence of post-operative recurrence” could use fecal calprotectin measurements every 3-6 months.  They propose a cut-off of 50 mcg/g in those with medium risk and a cut-off of 100 mcg/g in those with low risk.  Those who exceeded cut-off would need colonoscopy.  Among high risk patients, they recommend proceeding directly to colonoscopy every 6-12 months to assess for recurrence.  All patients who had recurrence of disease greater than i1 would need treatment for recurrence. (Related gutsandgrowth blog: Only One Chance to Make a First Impression).

This year’s 22Q at the zoo was on May 17th, 2015:

22Q at the Zoo.  More than 100 zoos across the world participate to improve awareness of 22Q deletion syndrome

22Q at the Zoo. More than 100 zoos across the world participate to improve awareness of 22Q deletion syndrome.  With Karlene Coleman, Nancy Morris, and Jennifer Hochman.

Why ImproveCareNow is Needed

A few recent articles make a strong argument for collaborative networks, like ImproveCareNow, to improve data collection to determine the most effective therapies.

  1. Kierkus J, et al. JPGN 2015; 60: 580-85.
  2. Audu GK, et al. JPGN 2015; 60: 586-91
  3. Dotson JL, et al. Inflamm Bowel Dis 2015; 21: 1109-14
  4. Saps M, et al. JPGN 2015; 60: 645-53.

A brief description of each study.

1. This study presented a multi-center randomized open-label trial of 99 pediatric patients with Crohn’s disease (CD) who were administered infliximab (IFX) along with an immunomodulator (azathioprine or methotrexate).  After a 10 week induction, 84 were randomized to either monotherapy for 54 weeks or dual therapy for 26 weeks. The authors did not find significant differences in response between the groups.  However, they reached a conclusion: “Twenty-six weeks likely represent (sic) the safe duration of combined IFX/immunomodulator therapy in our sample of pediatric patients with CD.”

2. The second study described three cases of chronic recurrent multifocal ostesomyelitis (CRMO) associated with inflammatory bowel disease.  They tried to identify all pediatric cases in UK in the last 10 years. (As an aside, I have treated one teenager with CRMO and ulcerative colitis.)

3. The third study is a retrospective single center of 30 patients with pediatric Crohn’s disease (CD) who developed intra-abdominal abscesses (IAA) over a 12-year period.  The authors note that this is “the largest single-center review of children and adolescents with CD and IAA to date.” Yet due to the small sample size, the study provides little guidance on this important medical problem; there were no predictors of successful medical or percutaneous drainage therapy.  In addition, with the increasing use of biologics, the authors note that “the issue of which patients will eventually require surgery is even less clear.” Changes in imaging (eg. MRE) and changes in medical management (eg. more enteral nutrition and less corticosteroids) are not discussed.

4. The fourth study is a comprehensive review of randomized placebo-controlled pharmacological clinical trials in children with functional abdominal pain disorders.  They found “no evidence to support the use of most commonly used drugs in children. Only 7 pharmacological RCTs on AP-FGIDs in children were found. Most studies were single center based and had a small sample size.  The methods and outcomes were heterogeneous…We found a considerable risk of bias in most studies…There is an urgent need for well-designed randomized clinical trials using age-appropriate validated outcome measures.”

Each of these studies makes a compelling argument for collaborative research networks.  The first study had a relatively small number of patients, short follow-up period, lack of blinding, and numerous methodological limitations.  How did the authors determine that 26 weeks was the time to stop dual therapy? Among adults with CD, a well-designed SONIC study (NEJM 2010; 362: 1383) showed the superiority of dual therapy during the study period.  In children, because of concerns about thiopurine safety, the best approach is still unclear. The second study identified only three patients despite examining a large population.  Similarly, the third study describes 30 patients with a common complication of CD but provides little insight.

The fourth study is a cautionary tale illustrating the lack of progress due to the absence of collaborative research.  Reports indicate a high prevalence of functional abdominal pain; one study indicated that abdominal pain affects “38% of school children weekly” (J Pediatr 2009; 154: 322-6).  In fact, studies on the high prevalence of this disorder dates back for 60 years (Apley, 1975; Apley & Hale, 1973; Apley & Naish, 1958). Despite the prevalence of this problem, the data for all of the treatments is poor.  The lack of progress in defining treatments for functional abdominal pain is multifactorial, including the following:

  • Cost: For many of the available treatments, there is not a financial incentive to conduct research.
  • Biomarker: lack of objective markers for improvement
  • Disease Stigma: many people attribute functional disorders as being due solely to psychological factors
  • Physician Champions: in pediatric gastroenterology, it took concerted physician efforts over many years to develop ImproveCareNow.  Similar physician champions would be needed to improve the outcomes for children with functional disorders

Bottomline: While ImproveCareNow has a lot of work ahead including improving data reliability and ascertaining accurate outcome measures, I think the effort is forward-thinking and will make a difference in understanding and treating children with IBD.  ImproveCareNow has more than 600 participating pediatric gastroenterologists and more than 20,000 patients. What I would like to see is a sister network to address the morbidity from functional disorders so that in 60 years (or sooner), we will be better equipped to treat children with abdominal pain that is not due to IBD.

Related blog posts:

Fox Theater

Fox Theater

New Mutations: Achalasia, Pseudoobstruction, & IBD

The ability to use whole exome sequencing and widely available genetic testing is yielding a plethora of new information regarding the genetic causes for many conditions.  In gastroenterology, here are a few recent examples:

  • Shteyer E, et al. “Truncating mutation in the nitric oxide synthase 1 gene is associated with infantile achalasia.” Gastroenterology. 2015 Mar;148(3):533-536.e4. doi: 10.1053/j.gastro.2014.11.044. Epub 2014 Dec 3.
  • Bonora E, et al. “Mutations in RAD21 Disrupt Regulation of APOB in Patients with Chronic Intestinal Pseudo-Obstruction” Gastroenterology 2015; 148: 771-82.  Genetic defect in RAD21 identified in Turkish family with consanguinity; in addition, APOB48 serum levels was identified as a potential biomarker for intestinal pseudo-obstruction and intestinal ganglion numbers.
  • Alonso A, et al. “Identification of Loci for Crohn’s Disease Phenotypes Using a Genome-Wide Association Study.” Gastroenterology 2015; 148: 794-805. Variants in MAG11, CLCA2, 2q24.1, LY75 identified as associated with Crohn’s phenotypes.

For me, I am not sure whether these findings should be considered mundane or amazing. On the one hand, each of the findings helps understand these diseases; yet, I came across all of these articles in the span of 24 hours and from the same journal.

Hard-to-Treat Shigella Infections

From the CDC (4/2/15): Multidrug-resistant Shigellosis Spreading in the U.S.

International travelers are bringing a multidrug-resistant intestinal illness to the United States and spreading it to others who have not traveled, according to a report released today by the Centers for Disease Control and Prevention (CDC). Shigella sonnei bacteria resistant to the antibiotic ciprofloxacin sickened 243 people in 32 states and Puerto Rico between May 2014 and February 2015…

In the United States, most Shigella is already resistant to the antibiotics ampicillin and trimethoprim/sulfamethoxazole. Globally, Shigella resistance to Cipro is increasing…

Until recently, Cipro resistance has occurred in just 2 percent of Shigella infections tested in the United States, but was found in 90 percent of samples tested in the recent clusters.

Because Cipro-resistant Shigella is spreading, CDC recommends doctors use lab tests to determine which antibiotics will effectively treat shigellosis. Doctors and patients should consider carefully whether an infection requires antibiotics at all…

For more information on Shigella, please visit: www.cdc.gov/shigella.

Travelers can learn more about food and water precautions to prevent Shigella at: http://wwwnc.cdc.gov/travel/yellowbook/2014/chapter-2-the-pre-travel-consultation/food-and-water-precautions.

To view the full MMWR report, please click here.

Related blog posts:

Sandy Springs

Sandy Springs

Brains and Bowels: Kids with IBD Do Fine in School

Screen Shot 2015-05-04 at 8.11.32 PM

A recent study (Singh H, et al. J Pediatr 2015; 166: 1128-33) showed that overall academic performance was not affected for children with inflammatory bowel disease (IBD).

Study characteristics:

University of Manitoba Database IBD population (n=337) was matched by age, sex, and area of residence to 10 randomly selected controls (n=3093).

Key findings:

  • There were no significant differences in the 2 groups in standardized scores or enrollment in grade 12
  • Lower socioeconomic status and diagnosis with a mental health problem (6-month before or after IBD diagnosis) were independent predictors of worse outcomes

Akin to the quote above, I’ve often felt that it is difficult to think clearly when having severe bowel dysfunction.  At the same time, some of our patients accomplish so much despite their physical setbacks.

Bottomline: This study provides reassurance that children with IBD should be able to complete their course work.

Chicago

Chicago


Tackling Crohn’s Perianal Fistulizing Disease

I am fortunate to work closely with several well-qualified pediatric surgeons and colorectal surgeons.  When faced with perianal fistulas, I have discussions with them to help optimize therapy.  Understanding exactly what and why the surgeons do what they do has not always been clear to me.  Four recent articles provide guidelines for the management of Crohn’s perianal disease.  The color figures in the articles make understanding what is done pretty obvious.

  • Schwartz DA et al. Inflamm Bowel Dis 2015; 21: 723-30. Overview.
  • Ong EMW et al. Inflamm Bowel Dis 2015; 21: 731-36. Focus on imaging.
  • Schwartz DA et al. Inflamm Bowel Dis 2015; 21: 737-52. Critical evaluation of Medications
  • Fichera A, Zoccali M. Inflamm Bowel Dis 2015; 21: 753-58. Critical evaluation of Surgical Approaches

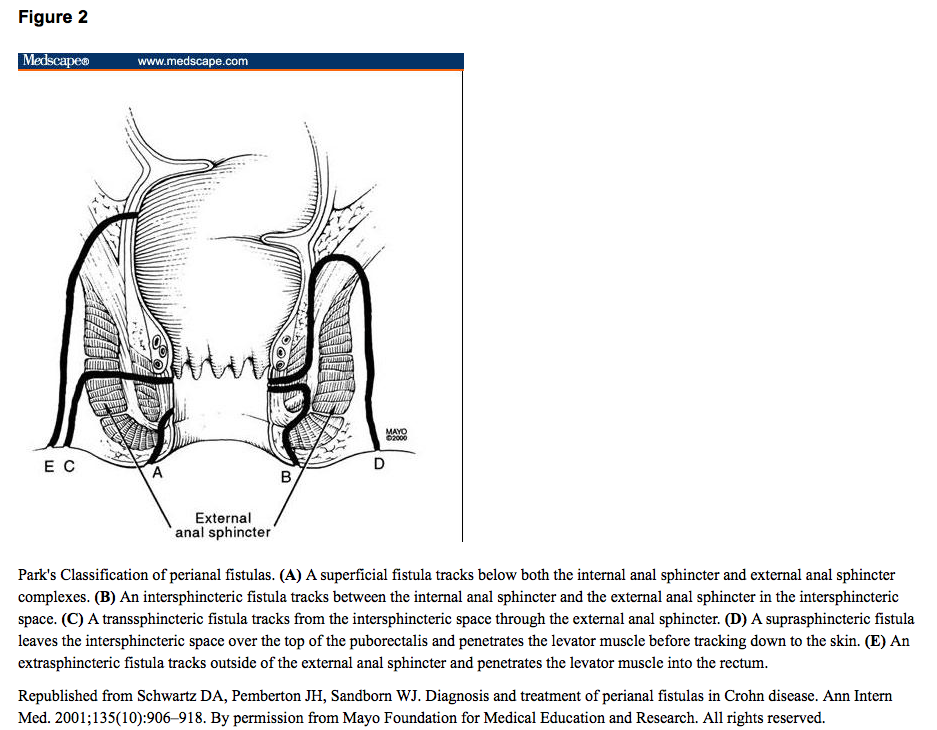
The first guideline provides a summary statement combining aspects of both medical and surgical management.  Basic anatomy and classification are reviewed (a color figure similar to reproduction below helps describe the types of fistula).

Simple vs Complex fistula is reviewed.  A “Simple fistula is a superficial, intersphincteric or low transspincteric fistula that has only 1 opening and is not associated with an abscess and/or does not connect to an adjacent structure such as the vagina or bladder.”  All others are complex fistulas.  The MRI classifcation is also reviewed (Figure 5).

Other points:

  • For fistulizing disease, top-down cotherapy (anti-TNF/immunomodulator) therapy is recommended.  Antibiotics are recommended in the short term.
  • Placement of a draining seton (for complex fistulas) helps to maintain fistula drainage until the track becomes inactive on medical treatment.
  • A treatment algorithm (Figure 7) notes that endoscopy, imaging (EUS or MRI) and exam under anesthesia are key first steps.  Decision tree then divides based on whether there is rectal inflammation, and whether fistula is simple or complex.
  • Surgical options include fistulotomy, fibrin glue, fistula plug, seton placement, advancement flaps and proctectomy.

Bottomline: These set of articles should serve as a useful reference when managing perianal disease.

Related blog posts:


Keeping Up with Clostridium Difficile

It is difficult to keep up with all of the relevant publications regarding Clostridium difficile–there are so many.  This likely reflects its emergence as a frequent and important pathogen.

Recent references:

  1. Sandberg KC et al. “Disproportionate Rise in Clostridium difficile Associated Hospitalizations Among US Youth with Inflammatory Bowel Disease, 19978-2011.” JPGN 2015; 60: 486-92 (editorial 421-22).
  2. Leffler DA, Lamont JT. NEJM 2015; 372: 1539-48.

In the first study, the researchers note that there has been a 5-fold increase in inflammatory bowel disease (IBD) hospitalizations with concomitant Clostridium difficile infection (CDI).  Whereas, the hospitalization without CDI increased 2-fold.  Associated with this 5-fold increase in hospitalizations, there were increased costs and longer length of stays.  Interestingly, IBD patients with CDI had a  lower likelihood (OR 0.31) of colectomy in this study. This epidemiology yields more questions than answers.  Certainly, a significant fraction of this increase is due to the use of more sensitive PCR-based assay. In addition, many of these patients may not be symptomatic due to CDI; it can be difficult to determine if IBD symptoms are due to IBD or due to CDI. Even treatment with antibiotics like vancomycin does not fully differentiate as the response could be nonspecific.

In the second review, severe useful points were made.

Risk factors:

  • Antibiotics –this remains most important risk factor
  • Older age (especially if >65 years)
  • Possible acid suppression -not confirmed in some studies when adjusting for coexisting conditions
  • Inflammatory bowel disease
  • Immunosuppression
  • Chronic kidney disease

Diagnosis:

  • Use of DNA assays has allowed for detection of “low levels of toxigenic organisms of uncertain clinical significance.”  Thus, these assays may detect clinically-insignificant infections.
  • Endoscopy is rarely needed, but sometimes helpful in ovelapping conditions like coexistent CDI from IBD
  • Negative PCR assay has a negative predictive value of “more than 95% in average-risk groups.”
  • Testing and treating persons with solid stools is not recommended

Prevention:

  • Probiotics “have an uncertain effect on the prevention of C difficile infection, and their routine use for the prevention or treatment of active infection is not recommended.”  The authors note that initial favorable studies of antibiotic-associated diarrhea were underpowered and that more recent studies have shown mixed results.  In studies of patients with unusually high rates of CDI, probiotics were shown to confer benefit.

Treatment:

  • Metronidazole and vancomycin remain 1st line treatments.
  • Fidaxomicin use has been limited due to expense, but has been shown to reduce recurrence of CDI in those who do not have the b1/NAP1/027 strain.
  • Alternative antimicrobials, including rifaximin, nitazoxanide and others, are “not recommended except in cases of unacceptable adverse effects.”
  • For recurrent infection, 1st line approach is retreatment with either metronidazole & vancomycin. Second recurrences are often treated with fidaxomicin or tapered vancomycin course.
  • Fecal microbial transplantation –noted to be highly effective and safe as salvage therapy. The precise components that are important are uncertain; however, “the phyla Bactteroidetes and Firmicutes are thought to comprise critical components.”  “More work is neede to understand the possible role for fecal microbial transplantation for primary CDI”

Bottomline: CDI remains an important pathogen and significantly complicates the management of IBD.

Related blog posts: