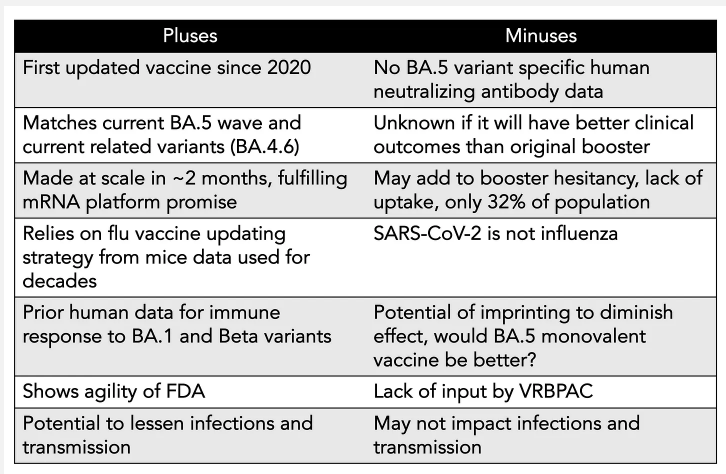
“There are no data for a BA.5 booster in people…Each year the flu vaccine quadrivalent program is updated using mice data, so there’s certainly a precedent for using such data.”
“It’s actually striking that in 2 months from the June 28th FDA meeting, there is a BA.5 vaccine booster made at scale. That is finally in keeping with all the excitement about the plasticity of the mRNA vaccine platform, that it could be ideal for rapid updating.”
In an ancillary study of the Vitamin D and Omega-3 Trial (VITAL), the investigators tested whether supplemental vitamin D3 would result in a lower risk of fractures than placebo. Design: VITAL was a two-by-two factorial, randomized, controlled trial with 25,871 participants with a median followup of 5.3 years.
Key findings:
Supplemental vitamin D3, as compared with placebo, did not have a significant effect on total fractures (hazard ratio, 0.98), nonvertebral fractures (hazard ratio, 0.97), or hip fractures (hazard ratio, 1.01).
From the editorial:
This study reinforces a recent trial which found that Vitamin D supplementation did not significantly improve bone mineral density/structure with high-resolution CT.
“There is no justification for measuring 25-hydroxyvitamin D in the general population or treating to a target serum level.” Exceptions may include some patients at high-risk for deficiency like persons living in residential settings with little sunlight exposure and those with malabsorptive conditions (eg. celiac disease, cholestatic liver disease).
“Providers should stop screening for 25-hydroxyvitamin D levels or recommending vitamin D supplements and people should stop taking vitamin D supplements to prevent major diseases or extend life.”
This report showed a significant temporal association between esophageal air events (EAEs) and hiccups using impedance-pH monitoring (I-pHM). EAEs include air swallows, gastric belching, and supragastric belching
This article reviews physiology of hiccups:
“Hiccups are physiologically normal but can become pathological when they occur with increasing regularity or for extended periods of time (1). The occurrence of hiccups is mediated through a reflex arc that consists of 3 basic branches: (1) afferent/sensory limb involving vagal, phrenic, and sympathetic nerves; (2) medulla and possibly the cervical spine (8) where central processing occurs; and (3) efferent/motor limb involving motor fibers of phrenic nerves and accessory nerves that innervate the diaphragm and intercostal muscles, respectively (1,9). A hiccup may be caused by any disturbance that triggers one of these branches (1).”
Understanding reasons for hiccups may help with treatment:
“We initially tried treating this patient’s hiccups with acid suppression. When symptoms persisted despite H2 blocker, PPI, and cyproheptadine therapy, I-pHM confirmed minimal GER and allowed us to focus instead on other treatments: behavioral techniques, diaphragmatic breathing, and baclofen.”
My take: It is nice to see a correlation between hiccups and physiology with I-pHM. In some patients, baclofen along with diaphragmatic breathing may be a consideration prior to definitive testing.
Key point: This study examines the marketing of unhealthy food and non-alcoholic beverages on TikTok. Videos posted by top food brands frequently feature branding, product images, engagement and celebrities/influencers. These videos reach billions of views.
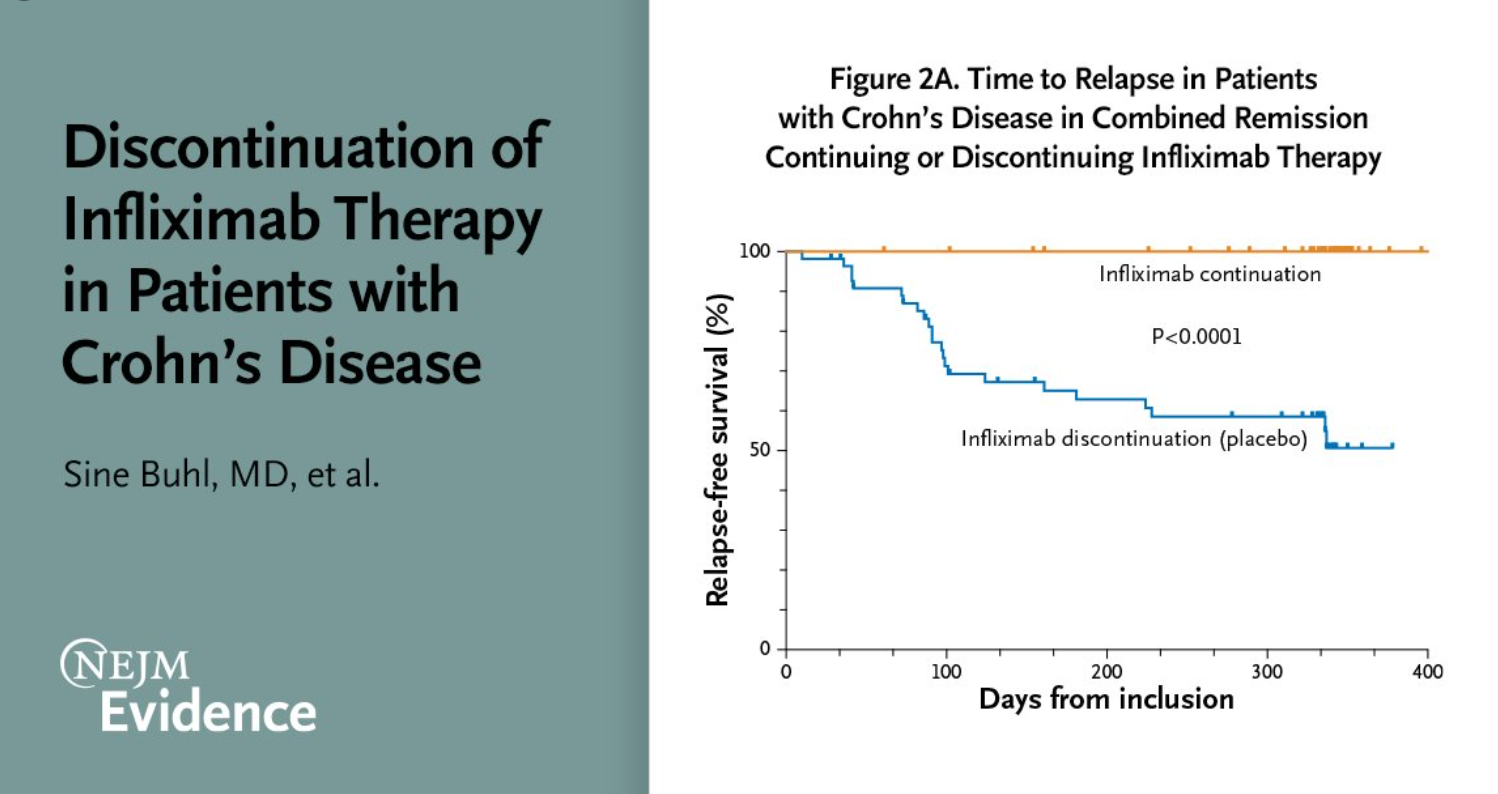
Design: This was a multicenter, randomized, double-blind, placebo-controlled withdrawal study of infliximab in patients (n=115) with Crohn’s disease who were in clinical, biochemical, and endoscopic remission after standard infliximab maintenance therapy for at least 1 year. Patients were randomly assigned 1:1 to continue infliximab therapy or to receive matching placebo for 48 weeks.
Key finding:
At the end of the trial at week 48, relapse-free survival was 100% in the infliximab-continuation group and 51% in the infliximab-discontinuation group
My take (borrowed from authors): Discontinuation of infliximab for patients with Crohn’s disease receiving long-term infliximab therapy and in clinical, biochemical, and endoscopic remission leads to a considerable risk of relapse
Key findings–The following variables were associated with clinical relapse:
female sex (adjusted hazard ratio [aHR] = 1.52, P = 0.0007)
exposure to oral 5-ASA (aHR = 1.44, P = 0.04),
use of immunomodulatory agents compared with tumor necrosis factor-alpha inhibitors (methotrexate aHR = 1.73, P = 0.003; thiopurines aHR = 1.63, P = 0.002)
presence of granulomas (aHR = 1.34, P = 0.02)
increased eosinophils on intestinal biopsies (aHR = 1.36, P = 0.02)
high levels of C-reactive protein (aHR = 1.01, P < 0.0001)
11.4% had iron deficiency, 3.5% had iron deficiency anemia, 8.2% had anemia, and 76.9% were normal.
“The authors showed that the hemoglobin threshold of 110 g/L that is currently recommended for diagnosing anemia at 1-year-old well-child visit corresponds with a very low serum ferritin (4.42 mcg/L).”
In a previous study, TARGet Kids!, “a higher serum ferritin was associated with higher cognitive function, with a serum ferritin of 17 mcg/L corresponding with the maximum level of cognition.” That is, iron deficiency, even in the absence of anemia, can contribute to detrimental cognitive outcomes.
Thus, current hemoglobin levels and ferritin need to be revised. Neither a hemoglobin of 11.0 g/dL nor a ferritin of 12 mcg/L is sensitive in detecting iron deficiency in toddlers.
In the U.S., only ~40% of anemia in toddlers is attributable to iron deficiency; thus, checking a ferritin can help determine if iron supplementation is worthwhile.
My take: Iron deficiency anemia is a late indicator of iron deficiency and relying on hemoglobin alone could have irreversible detrimental effects on cognitive outcomes. These articles make a strong argument for the following:
Use a ferritin threshold of at least 18 mcg/L to determine if iron deficient
Check a ferritin along with a hemoglobin at 1-year well-child check.
“Catheter occlusion, which occurs when the powder contacts blood or fluid within the catheter, is the main technical obstacle to successful powder delivery. Here is a cost-effective technique that overcomes this issue via the addition of a protective bone wax plug and stopcock (VideoGIE. 2021;6(9):387-389).”
“To set up, a tiny piece of bone wax is shaped into a 1-mm bead and applied to the tip of the 7 or 10 Fr delivery catheter (Figure 1). The catheter is then affixed to the Luer-lock end of a 3-way stopcock. The activated hemostatic powder device and an air-filled syringe are attached to the remaining ends of the stopcock. The stopcock initially is turned to oppose the device (Figure 2)…To fire without drying the working channel or air flushing the catheter, pass the bone wax–tipped catheter down the channel. The catheter tip is protected from moisture, and fluid can be suctioned, especially when using the 7 Fr catheter in a therapeutic gastroscope. When ready to fire, the bone wax plug is ejected with an air flush (Figure 3), the stopcock is turned to oppose the syringe (Figure 4), and the hemostatic powder is deployed.”
My take: If you follow the hemospray instructions carefully, this minimizes issues with catheter occlusion. This clever technique is likely to further eliminate this problem.
For thickeners, Dr. Rosen recommends Gelmix for infants with reflux who are breastfed or receiving amino acid formulas. Cereal does not work for breastmilk or amino acid formulas.
For infants, acid suppression, especially proton pump inhibitors, have not been shown to be effective but could contribute to a higher risk of allergies, infections and possibly bone complications.
The podcast reviewed the rationale for a time-limited trial of hydrolysates for infants with reflux symptoms due to the overlap of symptoms between reflux and MSPI. However, if it is not effective in several weeks, then it should be stopped.
Dr. Rosen does use “spit-up formulas” which can help reduce reflux symptoms and potentially help with swallow dysfunction. These are particularly well-suited for NG tubes as additional cereal in other formulas result in clogged NG tubes.
Several new technologies have helped understand esophageal physiology much better including pH-impedance, high-resolution manometry and FLIP device. PH-impedance can help better categorize reflux symptoms into non-erosive reflux disease, reflux hypersensitivity, and functional heartburn; however, this test is used fairly infrequently at Dr. Rosen’s center as the test is burdensome.
For older children/teenagers with functional heartburn symptoms, Dr. Rosen most frequent neuromodulator is gabapentin, which may alleviate coughing as well.
Fundoplications have fallen out of favor and are undertaken much less frequently. The use of blenderized formulas or gastrojejunostomy tubes are often used to manage reflux symptoms in patients with neurologic impairment.
Other treatments like prucalopride are emerging but quite limited in use in part due to lack of insurance coverage/cost.
Closing points:
Red throat on ENT exam is not specific for reflux
Aspiration, not reflux, is a common reason for infants who have coughing or BRUEs
In infants, nonacid reflux is the main issue, not acid reflux
My take: If you like one of these podcasts, is it proper to say “I liked hearing your bowel sounds?”
If you want to listen to the episode click this link: https://www.buzzsprout.com/581062/10918260 or listen to it on apple podcast, Spotify, or where every you listen to podcasts.
This blog has discussed safe sleep many times. Sleep-related infant deaths exact an enormous toll. All pediatric physicians should take the opportunity to counsel parents to reduce this risk.
Sleep surfaces: Use a flat, noninclined sleep surface. A crib, bassinet, portable crib or play yard should conform to the safety standards of the Consumer Product Safety Commission (CPSC). Recent biomechanical analyses have demonstrated that sleep surfaces that are inclined more than 10 degrees from horizontal are unsafe for infant sleep.
Sleep locationInfants should sleep in the parents’ room, close to the parents’ bed but on a separate surface designed for infants, ideally for at least the first six months.
BeddingDo not place any soft objects, including pillows, blankets or bumper pads, in the infant’s sleep environment.
PacifiersPacifier use is associated with a reduced risk of SIDS. For infants who are not directly breastfed, pacifiers can be introduced at any time. For breastfed infants, the pacifier can be started once breastfeeding is firmly established
Bed-sharing “Although the AAP cannot recommend bed-sharing based on the evidence, it also respects that many parents choose to bed-share routinely for a variety of reasons. It is important for clinicians and parents to have frank and nonjudgmental discussions about the family’s bed-sharing circumstances. The policy provides a risk-stratification analysis to guide these discussions…The safest place for a baby to sleep is on a separate sleep surface designed for infants close to the parents’ bed.
These situations “increase the risk of SIDS or unintentional injury or death while bed sharing, and these should be avoided at all times:
Bed sharing with a term normal weight infant aged <4 mo and infants born preterm and/or with low birth weight…even for breastfed infants…
Bed sharing with a current smoker (even if he or she does not smoke in bed) or if the mother smoked during pregnancy
Bed sharing with someone who is impaired in his or her alertness or ability to arouse because of fatigue or use of sedating medication
Bed sharing on a soft surface, such as a waterbed, old mattress, sofa, couch, or armchair
Bed sharing with soft bedding accessories, such as pillows or blankets
My take: It is a good idea to incorporate safe sleep messages when infants are seen for a variety of disorders including reflux and colic.
Related blog posts:
Safe Sleep A terrific website that focuses on this crucial issue: Charlieskids.org; it has videos, do’s and don’ts as well as a link to Cribs for Kids (discounted safe crib website). In addition,this website has a book called “Sleep Baby Safe and Snug” which incorporates updated recommendations on safe sleep practices.
The High Toll of Sudden Infant Death From 2013-2015, there was an average of 3523 US infants each year who died from SUID (sudden unexpected infant death), peaking at 1-2 months of life. More black infants died of SUID in the first year than black children who died from firearm homicides in all of childhood through age 19 years. SUID deaths from 2013-2015 (10,568) was similar to the total number of motor vehicle-traffic deaths in all of childhood (10,714) and greater than the total number of any of the other causes.
This large retrospective cohort study (2006-2017) identified 960 infants with in utero biologic medicine exposures (most commonly etanercept, anakinra, adalimumab, and infliximab) among 582,759 infants. Key findings:
Receipt of live-attenuated rotavirus vaccine in their first year or measles vaccine during their first 24 months were not at increased risk of prespecified adverse events compared to unexposed children
There was not a significant difference in diarrhea, bloody stools, intussusception, vomiting, encephalitis, myelitis, hepatitis, ataxia, or fevers
Receipt of the recommended number of doses of rotavirus vaccines in the first year of life was lower among biologic-exposed than among unexposed children (81.00% vs 85.20%, adjusted OR = 0.74)
Examples of guideline recommendations with regard to live-virus vaccination:
In their discussion, the authors note that this “provide some reassurance to parents and pediatricians regarding live-attenuated vaccines for children exposed to BRM [biologics] in utero. Professional societies may want to consider reevaluating their live-attenuated vaccines recommendations for these children as new safety data accumulates.”
My take: There are clearly theoretical concerns about biologic-exposures of infants in utero since some are actively transported across the placenta barrier and can remain in infants for up to 12 months after birth. However, this study could not identify significant adverse effects in exposed infants.
This is an impression from a starfish (no starfish in this picture)
Using a post hoc analysis of 2 large Crohn’s disease (CD) trial with 420 biologic-naive adult patients, the authors found the following Key Findings:
At week 6, a comparable number of patients achieved clinical remission with infliximab compared with patients treated with ustekinumab (44.9% vs 37.9%; adjusted odds ratio [aOR], 1.22)
At week 6 the clinical response rates were not significantly different (58.4% infliximab vs 54.9% ustekinumab; aOR, 1.25)
At week 6, 42.3% infliximab vs 34.7% ustekinumab had fecal calprotectin level less than 250 mcg/L in those with increased values at baseline
My take: A true head-to-head trial, rather than a post-hoc analysis, would more definitively determine relative efficacy and relative time to response. This study indicates that both agents have similar efficacy by week 6.