Does It Make Sense to Look for Celiac Disease in Children with Functional Constipation?

A recent study (AC Fifi et al. J Pediatr 2020; 227: 77-80.Full text PDF: Celiac Disease in Children with Functional Constipation: A School-Based Multicity Study) shows that celiac disease was not more prevalent in Colombian children with functional constipation(n=203) than in matched healthy controls (n=419). Patients were recruited from public schools.

Key finding:

  • The overall prevalence of celiac disease in the entire cohort was 0.6%. Of those with functional constipation, 1 (0.5%) was diagnosed with celiac disease, and 3 (0.7%) of the control patients

The authors note that some prior publications (references 11 and 12) have found a slight increase risk of celiac disease in children with constipation.

My take: In children with functional constipation, the yield from testing for celiac disease is very low and probably not significantly greater than the general population. In children with irritable bowel syndrome (which is often confused with constipation), the yield is probably a bit higher.

Related blog posts:

Chicago

A New FDA Warning for Tofacitinib

2/4/21: FDA: Initial safety trial results find increased risk of serious heart-related problems and cancer with arthritis and ulcerative colitis medicine Xeljanz, Xeljanz XR (tofacitinib)

“The U.S. Food and Drug Administration (FDA) is alerting the public that preliminary results from a safety clinical trial show an increased risk of serious heart-related problems and cancer with the arthritis and ulcerative colitis medicine Xeljanz, Xeljanz XR (tofacitinib) compared to another type of medicine called tumor necrosis factor (TNF) inhibitors. FDA required the safety trial, which also investigated other potential risks including blood clots in the lungs and death. Those final results are not yet available….

Patients should not stop taking tofacitinib without first consulting with your health care professionals, as doing so may worsen your condition. Talk to your health care professionals if you have any questions or concerns.”

Related blog post: FDA Warning on Tofacitinib (July 2019)

Growth in Inflammatory Bowel Disease: Better Late Than Never

Briefly noted: N Gupta et al. Inflamm Bowel Dis 2020; 26: 1880-1889. Continued Statural Growth in Older Adolescents and Young Adults With Crohn’s Disease and Ulcerative Colitis Beyond the Time of Expected Growth Plate Closure

In this retrospective observational longitudinal cohort study with 3007 patients with IBD from the ImproveCareNow Network, the authors found a high rate of continued linear growth after expected growth plate closure (15 years in females, 17 years in males).

Key findings:

  • 80% manifested continued growth beyond the time of expected growth plate closure, more commonly in CD (81%) than UC (75%; P = 0.0002)
  • Median height gain was greater in males with CD (1.6 cm) than in males with UC (1.3 cm; P = 0.0004), and in females with CD (1.8 cm) than in females with UC (1.5 cm; P = 0.025)

My take: This study provides additional information about delayed skeletal maturation in the pediatric population with inflammatory bowel disease. Interestingly, the rate of continued growth with ulcerative colitis was nearly as high as with Crohn’s disease.

Related blog posts:

Statin Use May Help in Fatty Liver Disease

J Lee et al. The American Journal of Gastroenterology: January 2021 – Volume 116 – Issue 1 – p 116-124. Full text link: Effects of Statin Use on the Development and Progression of Nonalcoholic Fatty Liver Disease: A Nationwide Nested Case-Control Study,

Using more than 11 million subjects enrolled in Nationwide Korean database, the authors explored the associations between statin use and fatty liver disease in adults (20 yrs or older).

Key findings:

  • The use of statin was associated with a reduced risk of NAFLD development (adjusted odds ratio [AOR] 0.66; 95% confidence interval [CI] 0.65–0.67). NAFLD was diagnosed by calculating fatty liver index (FLI).
  • The use of statins reduced the risk of significant liver fibrosis (AOR 0.43; 95% CI 0.42–0.44). Fibrosis was based on a BARD score ≥ 2.

The effects of statins may be mediated by anti-inflammatory and antifibrotic actions, which have been evident in experimental models of chronic liver disease.

My take: Statin use appears beneficial in patients with NAFLD. Since dyslipidemia is frequent in patients with NAFLD, there should be a low threshold for using statin therapy.

Related blog posts:

“Golden Half Hour in Chronic Pain”

A recent editorial (NL Schecter et al. JAMA Pediatr. 2021;175(1):7–8. doi:10.1001/jamapediatrics.2020.1798. Full text: The Golden Half Hour in Chronic Pediatric Pain—Feedback as the First Intervention -thanks to Ben Gold for this reference) notes that with pain we need to take a more holistic approach: ” Commonly, patients with chronic pain are evaluated by multiple clinicians, including pediatricians and specialists, each of whom may have addressed only one of the child’s persistent symptoms (ie, headache, abdominal pain, dizziness, nausea, or fatigue). When each symptom is addressed in isolation, it seldom provides comprehensive relief. Moreover, this process can foster a family’s belief that each symptom represents a distinct illness.”

Key points:

  • Brief feedback discussion following an assessment for pediatric chronic pain may be akin to the “golden hour” in trauma or neonatal care.  During this critical time, there is an opportunity to connect with a family, clarify misconceptions, move toward a shared biopsychosocial understanding of pain, and engage families in a comprehensive plan for recovery.”
  • Tips for mastering the golden hour:
    • Elicit Parent and Child Expectations at the Outset “This facilitates a thorough understanding of a family’s main concerns, reduces anxiety, and improves satisfaction. For example, if a parent reports that they expect their child to undergo additional diagnostic testing, this needs to be appreciated and addressed during the feedback.”
    • Validate Symptoms  “Explicitly stating that you do not believe the child is “faking” or that the problem is merely due to psychological stress is critical”
    • Offer a Positive Diagnosis “Although you are special, your symptoms are not unique or mysterious…. If the focus is on what has been ruled out, there are always additional diagnoses that you, the patient, or the internet can introduce.”
    • Provide Education “it can be helpful to explain that chronic pain is like a fire alarm that keeps ringing although there is no fire. “
    • Emphasize a Multidisciplinary Intervention Plan plan for medical intervention, psychological support, and physical activity
    • Stay Connected “Plan follow-up visits (every 4-6 weeks)”
    • Offer an Optimistic Appraisal  “optimistic appraisals are most effective when a clinician has first validated a child’s pain, provided a positive diagnosis and education, and outlined an evidence-based, multidisciplinary approach to care”

My take: This article offers helpful advice. However, whether there is a “golden hour” of opportunity is not clear. Having better outcomes with early intervention could easily be related, at least in part, to selection bias.

Related blog posts:

From Ashish Jha Twitter Feed 2/1/21:

Does Reflux Therapy Help Chronic Throat Symptoms? (Probably Not)

A recent study (J O’Hara et al. BMJ 2021;372:m4903. Full text: Use of proton pump inhibitors to treat persistent throat symptoms: multicentre, double blind, randomised, placebo controlled trial) will probably be another thorn in the side of our ENT colleagues who frequently assert that reflux is likely causing a persistent sore throat. This study is likely to influence empiric treatment by GI physicians as well.

Methods:

  • Random blinded allocation (1:1) to either 30 mg lansoprazole (n=172) twice daily or matched placebo (n=174) twice daily for 16 weeks of patients with persistent throat symptoms.
  • Eligible patients had persistent (>6 weeks) unexplained throat symptoms—principally hoarseness, throat pain, globus sensation, throat clearing, postnasal secretions or excess mucus, cough, or choking sensation
  • Primary outcome was symptomatic response at 16 weeks measured using the total reflux symptom index (RSI) score.

Key finding:

  • No evidence was found of benefit from PPI treatment in patients with persistent throat symptoms. RSI scores were similar between the lansoprazole and placebo groups after 16 weeks of treatment and at the 12 month follow-up.
  • Improvements (reduction in RSI score) were observed in both groups—score at 16 weeks: lansoprazole 17.4 (15.5 to19.4) and placebo 15.6 (13.8 to 17.3). No statistically significant difference was found between the treatment arms. Furthermore, “no trends were in favour of lansoprazole.”
  • Limitation: “Our trial could be criticised for lacking any objective measure of GORD within the methodology or for employing any such test as an inclusion criteria. However, we did address the use of PPIs in an empirical setting, which was a near universal practice at the time of our study.”

My take (borrowed in part from authors): “No evidence supports the empirical use of PPIs to treat persistent throat and voice symptoms.” Despite this finding, “old habits die hard” and I predict that it will be a long time before this finding is widely adopted into clinical practice.

Related blog posts:

Progression of Fatty Liver Disease in Children

SA Xanthakos et al. Gastroenterol 2020; 159: 159: 1731-1751. Progression of Fatty Liver Disease in Children Receiving Standard of Care Lifestyle Advice

This prospective study followed the natural history of NAFLD in children with timed liver biopsy reassessment in children (n=122) using the placebo arms of 2 large multicenter clinical trials; patients received standard of care lifestyle advice. The study population had a mean age of 13 years; 71% were Hispanic participants

Key findings:

  • At enrollment, 31% of the children had definite NASH, 34% had borderline zone 1 NASH, 13% had borderline zone 3 NASH, and 21% had fatty liver but not NASH
  • Over a mean period of 1.6 ± 0.4 years, borderline or definite NASH resolved in 29% of the children, whereas 18% of the children with fatty liver or borderline NASH developed definite NASH
  • Fibrosis improved in 34% of the children but worsened in 23%
  • Progression was more likely with increasing ALT, increasing GGT, type 2 diabetes/increasing HgbA1c
  • Overall, one-third had histologic features of progression within 2 years, in association with increasing obesity and serum levels of aminotransferases and loss of glucose homeostasis.
  • The study conclusions are limited by selection bias, potential liver biopsy sampling errors, limited enrollment of non-Hispanic children, and relatively short duration of follow-up

Related blog posts:

Sickle Cell Related Liver Disease

A terrific review of sickle cell disease (SCD) associated liver problems: F Lacaille et al. JPGN 2021; 72: 5-10. The Liver in Sickle Cell Disease

While the most frequent liver-related problem in individuals is cholelithiasis (>25% after age 5 yrs), a host of other problems can develop –this article is a good reference.

Key points:

  • Acute Sickle Cell Hepatic Crisis, Intrahepatic cholestasis, and acute hepatic sequestration
    • ~6% of children and 10% of adults develop severe liver complications of SCD
    • With sequestration, indications include pain with acute drop in hemoglobin (>2 g/dL)
    • Acute hepatic crisis is often signaled by elevated conjugated bilirubin
    • With severe liver disease/liver ischemia, authors advocated for exchange transfusion which “more efficiently decreases HbS percentage, faster restoring the blood flow than simple transfusion.” Consider after excluding biliary complication if INR is >1.4 with increased conjugated bilirubin (>3 mg/L). “Simple transfusion should be discussed in other cases.”
  • Cholangiopathy and autoimmune liver disease
    • Although autoimmune sclerosing cholangitis/autoimmune hepatitis are rare, it may account for 8% of children with SCD referred for hepatic dysfunction
    • Liver biopsy, needed for diagnosis, “is a dangerous procedure in SCD, which cannot be performed without at least a transfusion”
    • “Steroids can induce sickle crisis”
    • Look for ANA, SMA, LKM, and ANCA
  • Iron Overload
    • “It is not usually a significant concern in children…In our patients, the median ferritin level was about 3000 ng/mL, and none had a severe overload on MRI”
  • Infections/Drug toxicity
    • Need to consider hepatitis B, hepatitis C, and hepatitis E in particular
    • Inquire about herbal medicines and recreative drugs
  • Liver transplantation
    • Results are often poor.
    • Problems include sickle cell crisis in the transplanted liver, and drug toxicity which can add to the neurological and renal morbidities of SCD
  • Stem cell transplantation
    • Consider for severe complications of SCD including hepatic complications

Related blog posts: 

From NY Times

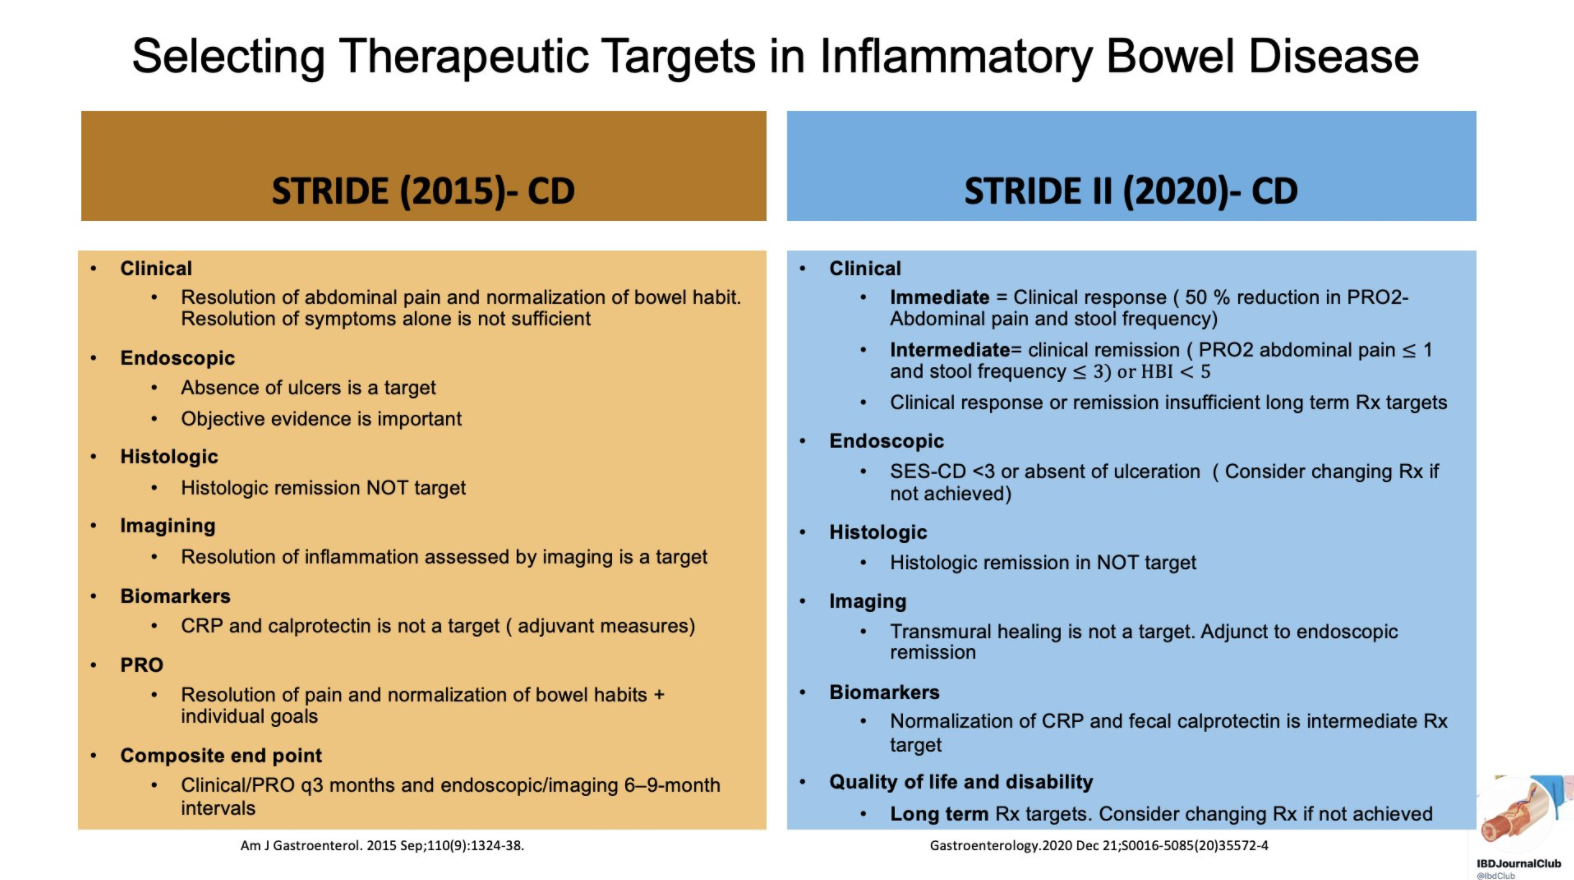
STRIDE II -Updated Crohn’s Disease Target Goals

From Tauseef Ali’s Twitter Feed — a summary slide of Crohn’s disease targets for both pediatric and adult patients and a slide showing typical response/remission/healing times to medications.

From the following article: D Turner et al. Gastroenterology (12/31/20, Online Ahead of Print): DOI: 10.1053/j.gastro.2020.12.031 STRIDE-II: An Update on the Selecting Therapeutic Targets in Inflammatory Bowel Disease (STRIDE) Initiative of the International Organization for the Study of IBD (IOIBD): Determining Therapeutic Goals for Treat-to-Target strategies in IBD

Recommendations were based on a systematic review of the literature and iterative surveys of 89 IOIBD members, recommendations were drafted and modified in two surveys and two voting rounds.