Nutrition Therapy for Intensive Care Patients

JJ Patel, SA McClave. NEJM 2026; 395: 162-174. Nutrition Therapy in Critically Ill Adults

Key points: (for adults)

  • Early enteral nutrition preserves gut integrity and supports the microbiome, so it is the preferred approach, although contemporary randomized, controlled trials show that early short-term parenteral nutrition is safe when enteral nutrition is contraindicated.
  • Providing full-dose nutrition early may lead to more metabolic and gastrointestinal complications than restrictive or trophic feeding.
  • High-dose protein (>2.0 g per kilogram of body weight per day) offers no outcome benefit over standard dosing (≤1.2 g per kilogram per day) and may be harmful in patients with acute kidney injury.
  • Adverse events with enteral feeding (often called enteral feeding intolerance) are common during critical illness, and the safe delivery of nutrition requires gradual advancement, strategies for prevention of refeeding syndrome, glycemic control (glucose level, <180 mg per deciliter), and avoidance of routine gastric residual volume monitoring.

TIMING, ROUTE AND DOSE OF NUTRITION:

  • “The receipt of nothing by mouth…impairs gut health by reducing epithelial-cell proliferation, increasing apoptosis, and disrupting mucosal integrity, enteral nutrition supports gut function by enhancing tight-junction protein expression, reducing enterocyte apoptosis, preserving villous and crypt architecture, maintaining Paneth-cell function, supporting gut-associated lymphoid tissue, and helping to sustain commensal microbiota.11,12 The collective evidence from 21 randomized, controlled trials has shown that early enteral nutrition, initiated within the first 24 to 36 hours after ICU admission, leads to better outcomes than delayed delivery or no provision of enteral nutrition.13” [if no contraindications]
  • “The CALORIES and NUTRIREA-2 trials randomly assigned critically ill adults to receive early enteral nutrition or early short-term parenteral nutrition, and the results showed no between-group differences in 30-day and 28-day mortality, respectively”
  • “Thirteen randomized, controlled trials questioned the practice of providing full-dose nutrition during the acute phase of critical illness and compared restrictive strategies — such as hypocaloric feeding, permissive underfeeding, and trophic feeding (Table 2) — with full-dose regimens.18–22,36–43 Nine trials showed no significant between-group differences in mortality.18,19,21,37–41,43 Four trials showed that restrictive-dose enteral nutrition led to better outcomes, including reductions in mortality and duration of mechanical ventilation and earlier time-to-readiness for ICU discharge, than full-dose nutrition.20,22,36,42 …Early aggressive full-dose nutrition may cause net harm by increasing the risk of bowel ischemia, refeeding syndrome, overfeeding (exogenous nutrients combined with hepatic gluconeogenesis), suppression of autophagy, increased demand on dysfunctional mitochondria, delivery of excessive fluid volume, and gastrointestinal adverse effects.28

HIGH PROTEIN NUTRITION:

Several large well-designed studies have looked at higher protein dosing, including the EFFORT Protein Trial, the PRECISE trial and the TARGET Protein trial. Even in patients with preexisting malnutrition which was assciated wiht higher mortality, provision of high protein did not modify this outcome. “These findings were supported by two meta-analyses that showed that a high dose of protein did not lead to better outcomes in critically ill adults than a lower dose.56,57 Moreover, a high dose of protein may be harmful in patients with severe illness and acute kidney injury.”

GASTRIC RESIDUALS:

” A meta-analysis of seven trials (involving 1240 patients) indicated that not monitoring gastric residual volume reduced unnecessary feeding interruptions and showed no between-group differences in the incidence of ventilator-associated pneumonia, the length of ICU stay, or mortality.67 Current evidence does not support the use of gastric residual volume monitoring to reduce the risk of aspiration or pneumonia in ICU patients. Gastric residual volume monitoring may hinder enteral nutrition delivery… Routine monitoring of gastric residual volume — as a marker of adverse events with enteral feeding — should be strongly discouraged.”
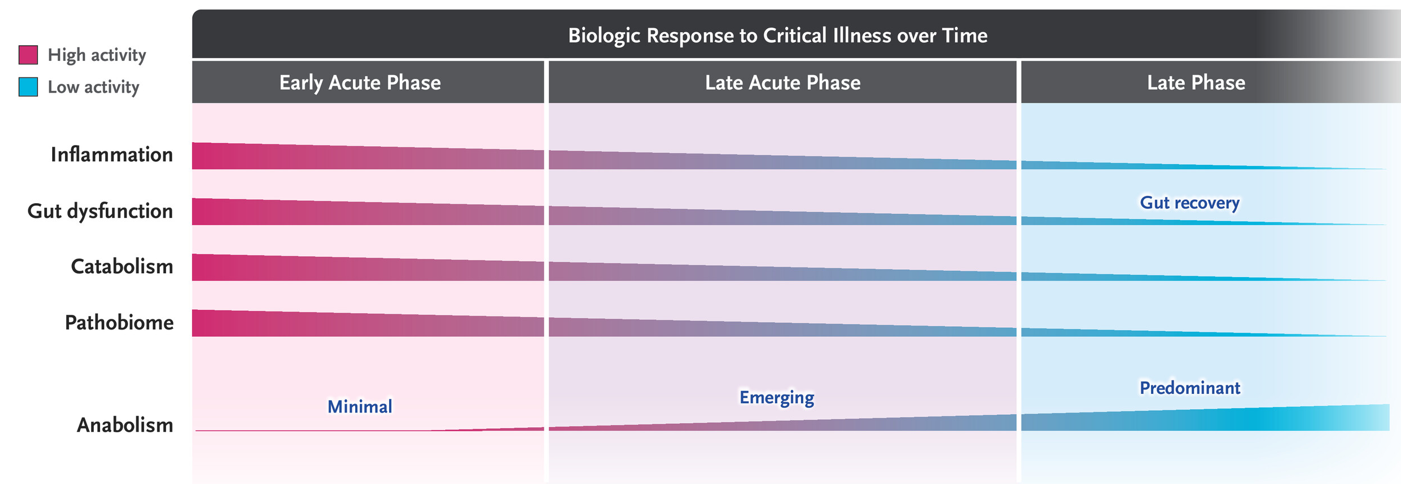
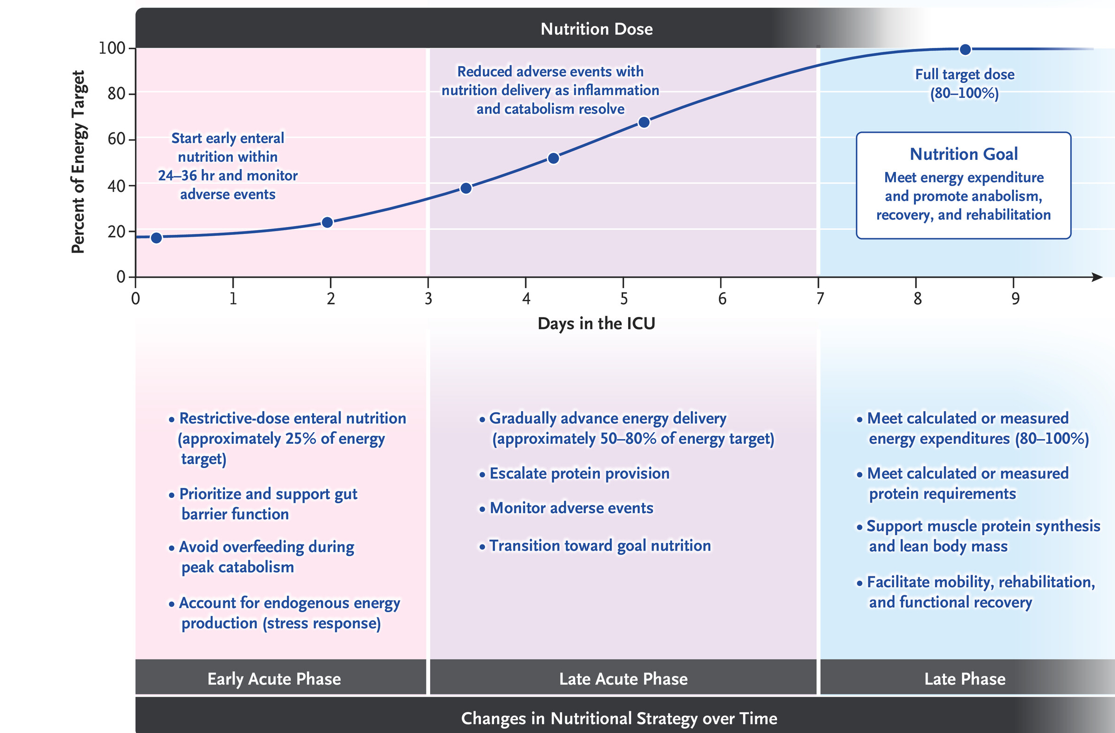
Figure 2. Conceptual model of evolution of physiological responses and nutrition strategy across phases of critical illness.

Long Term Outcomes:

“Over the past four decades, survival from critical illness has improved but is marred by substantial loss of lean body mass, which is a major long-term consequence for survivors.4 Loss of lean body mass contributes to acquired muscle weakness and functional disability, which can persist for up to 5 years after the initial ICU admission.74 In healthy persons, resistance exercise combined with protein supplementation has been shown to elicit a greater anabolic response than protein supplementation alone.75

My take: While this article is geared towards adult patients, my expectation is that the recommendations are largely applicable to pediatric patients. However, there is much more data in adults and pediatric care needs to be adjusted based on size.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Advancements in Pediatric Cholestatic Liver Disease Management

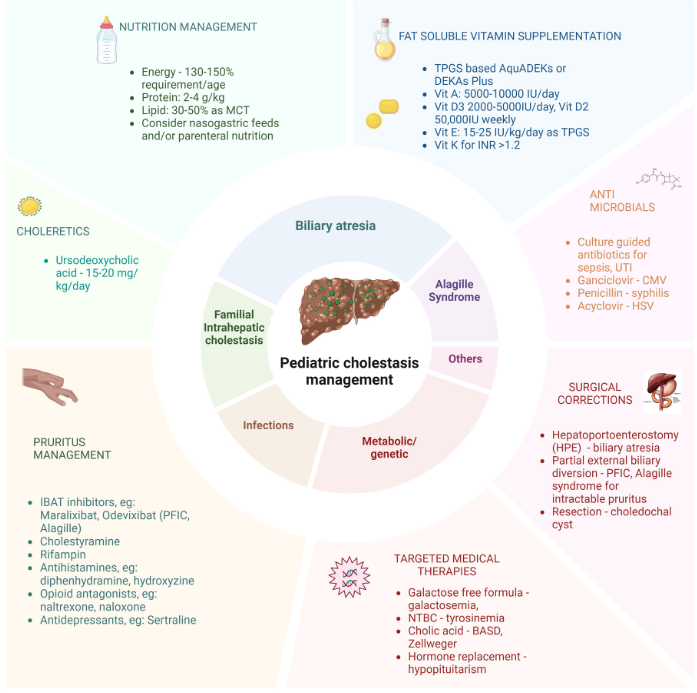
KR Mysore et al. J Pediatr Gastroenterol Nutr. 2025;80:549–558. Recent advances in the management of pediatric cholestatic liver diseases

This is a useful review summarizing advances in the management of cholestatic diseases.

Treatment with IBAT inhibitors:

“Improvement in both pruritus and serum BAs/bilirubin levels has been associated with improved event‐free survival and 6‐year transplant‐free survival in ALGS patients treated with maralixibat. Additionally, this class of medication improved overall growth of the patient by improving mean height and weight Z scores that may be related to reduced impact of high serum bile acid levels on the growth axis although further studies are needed to better define the mechanism responsible for this out-come. This finding suggests these parameters could be used as surrogate end‐points for disease severity in diseases like ALGS or PFIC, where the time course to develop the need for LT commonly occurs over many years.”

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

IBD Shorts: Ustekinumab in Kids, Subcutaenous Infliximab, Nutrition Highlights

MT Dolinger et al. J Crohns Colitis 2022.  doi: 10.1093/ecco-jcc/jjac055. Online ahead of print. Outcomes of Children With Inflammatory Bowel Disease Who Develop Anti-Tumor Necrosis Factor Induced Skin Reactions

In this retrospective study, among those who developed skin reactions to anti-TNF agents, 71 (64%) continued anti-TNF and 40 (36%) switched to ustekinumab (UST). Key findings:

  • Switching to UST had a higher rate and odds of resolution of skin findings (29/40 (73%) vs. 24/71 (34%); p <0.0001) and combined remission (21 (52%) vs. 22 (31%); p=0.03) vs. continuing anti-TNF at 6 months

PJ Smith et al. J Crohns Colitis, jjac053, https://doi.org/10.1093/ecco-jcc/jjac053 Open Access: Efficacy and Safety of Elective Switching From Intravenous to Subcutaneous Infliximab (Ct-P13): A Multi-Centre Cohort Study

Patients (n=181) on established maintenance IV infliximab who switched to SC CT-P13 were included in this retrospective multi-centre cohort study. Key findings:

  • Treatment persistence rate was high (N=167, 92.3%) and only 14 patients (7.7%) stopped treatment during the follow-up period. There were low rates of immunogenicity with no change in clinical disease activity indices or biomarkers

Link: Crohn’s and Colitis Congress 2022 Nutritional Highlights (Nutritional Therapy for IBD Website). This website has a summaries, and links to extensive information (videos/posters) from recent IBD meeting.

Sunrise in Sandy Springs (4/9/22) -no filter

ESPGHAN Position Paper: Nutrition for Critically Ill Neonates

SJ Moltu et al JPGN 2021; 73: 274-289. Full Text: Nutritional Management of the Critically Ill Neonate: A Position Paper of the ESPGHAN Committee on Nutrition

Background: The authors of this position paper are trying to modulate the treatment recommendations based on the PEPaNIC trial. This “large randomized trial, the Early versus Late Parenteral Nutrition in the Pediatric Intensive Care Unit (PEPaNIC) trial, showed that withholding parenteral nutrition (PN) during the first week of acute illness improved early outcomes as compared to PN initiated during the first 24 hours after admission in children [Fivez T, Kerklaan D, Mesotten D, et al. Early versus late parenteral nutrition in critically ill children. N Engl J Med 2016; 374:1111–1122] (71). Effects were similar in the subgroup of 209 term-born neonates recruited to the trial (72). Despite this finding, many clinicians appear reluctant to limit early nutritional support due to (1) concerns about possible harm by not providing adequate nutrients during the first week of critical illness, particularly in neonates and undernourished children (73), and (2) the belief that exogenous dietary protein provision is essential during critical illness (73).”

Key recommendations:

  • In preterm infants, available evidence does not support any significant changes to current guidelines, which recommend that critically ill preterm infants should receive nutritional support started at (or reduced to) the minimal amount needed to cover basal metabolic rate and basic macronutrient needs during the early acute phase (26,27,129,149). For many preterm infants, this means that they will need PN.
  • In critically ill term neonates, initiation of PN within 24 hours is not routinely recommended; however, considering the limitations of the PEPaNIC trial and the observed low risk of long-term harm from early PN in critically ill neonates, the ESPGHAN-CoN does NOT support a change towards withholding parenteral nutritional support for 7 days as standard nutritional care. This position paper suggests considering careful initiation of nutritional support, including micronutrients, just below or at predicted REE after 48–72 hours… when adequate enteral nutrition is not feasible

My take: Particularly in preterm infants, adequate nutrition should not be withheld due to their very limited reserves. In term critical infants, these guidelines offer a logical approach until more studies are available.

Related blog posts:

NY Times: “Our Food is Killing Too Many of Us”

NY Times: D Mozaffarian, D Glickman Our Food is Killing Too Many of Us

“Improving American nutrition would make the biggest impact on our health care”

An excerpt:

“Instead of debating who should pay for all this, no one is asking the far more simple and imperative question: What is making us so sick, and how can we reverse this so we need less health care? … our food…

Poor diet is the leading cause of mortality in the United States, causing more than half a million deaths per year. Just 10 dietary factors are estimated to cause nearly 1,000 deaths every day from heart disease, stroke and diabetes alone…

Taxes on sugary beverages and junk food can be paired with subsidies on protective foods like fruits, nuts, vegetables, beans, plant oils, whole grains, yogurt and fish….Levels of harmful additives like sodium, added sugar and trans fat can be lowered through voluntary industry targets or regulatory safety standards

Nutrition standards in schools, which have improved the quality of school meals by 41 percent, should be strengthened; the national Fresh Fruit and Vegetable Program should be extended beyond elementary schools to middle and high schools…

Coordinated federal leadership and funding for research is also essential. This could include, for example, a new National Institute of Nutrition at the National Institutes of Health. Without such an effort, it could take many decades to understand and utilize exciting new areas, including related to food processing, the gut microbiome, allergies and autoimmune disorders, cancer, brain health, treatment of battlefield injuries and effects of nonnutritive sweeteners and personalized nutrition.”

Related blog posts:

Crater Lake, OR


The Pediatric Nutrionist Blog

One of my colleagues, Kipp Ellsworth, at Children’s Healthcare of Atlanta has started a pediatric nutrition blog: 

The Pediatric Nutritionist | Covering the world of infant, child … (www.childrensnutrition.org)

The site contains:

  • Core lectures section containing several presentations addressing the basics of pediatric nutrition
  • Feature Articles (long-form articles covering expansive clinical nutrition topics)
  • Protocol Development (articles covering institutional efforts to develop nutrition support protocols for various populations)
  • Journal Club
  • Clinical Vignettes (short-form articles or discussions on issues facing  clinical practice)

I’ve reviewed the site and I think it will be a useful resource for pediatric gastroenterology providers as well as general pediatricians.  Kipp has had a twitter feed which has provided links to a large number of nutrition articles and this site is likely to be a helpful extension.  Already on the site, there are a few powerpoint lectures; the one on formulas for infants and children provides a particularly good overview.