Unknown's avatar

About gutsandgrowth

I am a pediatric gastroenterologist at GI Care for Kids (previously called CCDHC) in Atlanta, Georgia. The goal of my blog is to share some of my reading in my field more broadly. In addition, I wanted to provide my voice to a wide range of topics that often have inaccurate or incomplete information. Before starting this blog in 2011, I would tear out articles from journals and/or keep notes in a palm pilot. This blog helps provide an updated source of information that is easy to access and search, along with links to useful multimedia sources. I was born and raised in Chattanooga. After graduating from the University of Virginia, I attended Baylor College of Medicine. I completed residency and fellowship training at the University of Cincinnati at the Children’s Hospital Medical Center. I received funding from the National Institutes of Health for molecular biology research of the gastrointestinal tract. During my fellowship, I had the opportunity to work with some of the most amazing pediatric gastroenterologists and mentors. Some of these individuals included Mitchell Cohen, William Balistreri, James Heubi, Jorge Bezerra, Colin Rudolph, John Bucuvalas, and Michael Farrell. I am grateful for their teaching and their friendship. During my training with their help, I received a nationwide award for the best research by a GI fellow. I have authored numerous publications/presentations including original research, case reports, review articles, and textbook chapters on various pediatric gastrointestinal problems. In addition, I have been recognized by Atlanta Magazine as a "Top Doctor" in my field multiple times. Currently, I am the vice chair of the section of nutrition for the Georgia Chapter of the American Academy of Pediatrics. In addition, I am an adjunct Associate Clinical Professor of Pediatrics at Emory University School of Medicine. Other society memberships have included the North American Society for Pediatric Gastroenterology Hepatology and Nutrition (NASPGHAN), American Academy of Pediatrics, the Food Allergy Network, the American Gastroenterology Association, the American Association for the Study of Liver Diseases, and the Crohn’s and Colitis Foundation. As part of a national pediatric GI organization called NASPGHAN (and its affiliated website GIKids), I have helped develop educational materials on a wide-range of gastrointestinal and liver diseases which are used across the country. Also, I have been an invited speaker for national campaigns to improve the evaluation and treatment of gastroesophageal reflux disease, celiac disease, eosinophilic esophagitis, hepatitis C, and inflammatory bowel disease (IBD). Some information on these topics has been posted at my work website, www.gicareforkids.com, which has links to multiple other useful resources. I am fortunate to work at GI Care For Kids. Our group has 17 terrific physicians with a wide range of subspecialization, including liver diseases, feeding disorders, eosinophilic diseases, inflammatory bowel disease, cystic fibrosis, DiGeorge/22q, celiac disease, and motility disorders. Many of our physicians are recognized nationally for their achievements. Our group of physicians have worked closely together for many years. None of the physicians in our group have ever left to join other groups. I have also worked with the same nurse (Bernadette) since I moved to Atlanta in 1997. For many families, more practical matters about our office include the following: – 14 office/satellite locations – physicians who speak Spanish – cutting edge research – on-site nutritionists – on-site psychology support for abdominal pain and feeding disorders – participation in ImproveCareNow to better the outcomes for children with inflammatory bowel disease – office endoscopy suite (lower costs and easier scheduling) – office infusion center (lower costs and easier for families) – easy access to nursing advice (each physician has at least one nurse) I am married and have two sons (both adults). I like to read, walk/hike, bike, swim, and play tennis with my free time. I do not have any financial relationships with pharmaceutical companies or other financial relationships to disclose. I have helped enroll patients in industry-sponsored research studies.

IBD Shorts July 2018

DJ Gracie et al. Gastroenterol 2018; 154: 1635-46. This study of 405 adults indicated that IBD triggers anxiety and that anxiety triggers IBD. Specifically: “Baseline CD or UC disease activity were associated with an almost 6-fold increase in risk for a later abnormal anxiety score (hazard ratio [HR], 5.77; 95% CI, 1.89-17.7).  In patients with quiescent IBD at baseline, baseline abnormal anxiety scores were associated with later need for glucocorticosteroid prescription or flare of IBD activity (HR 2.08; 95% CI, 1.31-3.30).”

RL Dalal, B Shen, DA Schwartz. Inflamm Bowel Dis 2018; 24: 989-96.  This review provides updated information on epidemiology, diagnosis, and treatment recommendations for pouchitis.

A Alper et al. JPGN 2018; 66: 934-6. Key finding: Celiac disease is “not increased in children with IBD compared with non-IBD children with gastrointestinal symptoms.”  False-positive tTG serology can occur.

AK Shaikhkhalil et al. JPGN 2018; 66: 909-14. The authors showed that using a quality-improvement effort, there was increase utilization of enteral exclusive therapy (EEN).  Baseline 5.was <5% and by completion of intervention, utilization increased to approximately 50%. The interventions to achieve this are specified in this article, including talking points.  EEN is described as “nutrition therapy.” Patients are offered oral EEN and if not adequate by 3-4 days, nasogastric feedings are initiated (~15%).  Interestingly, of those to complete EEN therapy, 97% did not need NG placement.

Pictures from Ameilia Island:

Amelia Island

ICN Travel Toolkit -Tips for Patients with Inflammatory Bowel Disease

ImproveCareNow’s Patient Advisory Committee: ICN Travel Toolkit – a collection of personal stories, plus tips and techniques for traveling with IBD – written by members of the ICN Patient Advisory Council (PAC).

In addition to the tips offered by the PAC (see below), I would recommend that those travelling keep a succinct medical summary with the following (minimum):

  • Diagnosis and extent of disease
  • Other medical problems
  • Physician (contact info)
  • Allergies –food/medicines
  • Current list of medications including dosage and frequency
  • List of prior treatments
  • Previous surgeries

Also, below are other travel -related links, including to the CDC travel website which makes recommendations based on travel destination along with underlying problems.

A summary of the ICN travel tips from the PAC PowerPoint Presentation:


Fluid Management for Abdominal Surgery

A recent study (PS Myles et al. NEJM 2018; 378: 2263-74, editorial 2335-6) throws some shade on the idea that restricting IV fluids during surgery results in better outcomes.

With ERAS (enhanced recovery after surgery) procedures, one of the components has been restricting IV fluids during surgery due to concerns that excessive fluid will result in bowel wall edema and slower recovery.  To better determine if a restrictive IV fluid approach or a more liberal approach was better, this RELIEF study randomized approximately 3000 patients who were receiving major abdominal surgery into two arms: a restrictive group and a  liberal group; they received a median of 3.7 liters of IV fluids and 6.1 liters respectively during and up to 24 hours after surgery.

Key findings:

  • Rate of disability-free survival at 1 year was 81.9% in the restrictive group and 82.3% in the liberal group (hazard ratio for death or disability was 1.05, CI 0.88-1.24, P=0.61)
  • Rate of acute kidney injury was 8.6% in the restrictive fluid group compared to 5.0% in the liberal fluid group (P<0.001). Renal replacement therapy was 0.9% in the restrictive fluid group compared to 0.3% in the liberal fluid group (P=0.048).
  • Rates of surgical site infection was 16.5% in the restrictive fluid group compared to 13.6% in the liberal fluid group (P=0.02).  The authors speculate that this could be related to perfusion of surgical anastomosis.

The associated commentary notes that in this age of minimally invasive surgery, a modestly liberal administration of IV fluids does not create substantial fluid retention.

My take: Restrictive fluid regimen during major abdominal surgery resulted in higher rates of kidney injury and surgical site infections.  This study indicates that for ‘enhanced recovery’ that a more liberal fluid regimen is safer.

Related posts:


Pediatric Intestinal Pseudo-obstruction: Consensus Recommendations

A new report from an ESPGHAN-Led Expert Group (N Thapar et al. JPGN 2018; 66: 9991-1019) provides detailed recommendations for pediatric intestinal pseudo-obstruction (PIPO).  In addition, this report serves as an excellent self-assessment of your vision.  If you can read figure 1, which has some incredibly tiny font size, then your vision is fantastic.

Full Link: “Paediatric Intestinal Pseudo-obstruction: Evidence and Consensus-based Recommendations From an ESPGHAN -Led Expert Group”

Aside from that snarky comment, the report offers a great deal of useful advice.

  • After obstruction has been excluded, the authors recommend that patients should undergo a basic laboratory evaluation (including CBC, CMP, ESR/CRP, Celiac serology, Cortisol, Thyroid testing, Metabolic tests [urine organic acids, ammonia, lactate]) and to consider more extensive evaluation.
  • If primary, rather than secondary, PIPO is suspected, the authors recommend neurogastroenterology evaluation.

Subsequently, the authors review management: potential medications (Table 6), enteral feeds, gastrostomy and ileostomy, and in more than 80% then need for parenteral nutrition. At the time of therapeutic procedures, it is recommended to obtain full-thickness biopsies to further characterize the PIPO.

Clinical features which distinguish pediatric chronic intestinal pseudo-obstruction (CIPO) from adult CIPO are listed in Table 2. These include the following:

  • Frequent urologic involvement in pediatric CIPO which is rare in adults with CIPO.
  • Dilated bowel loops are commonly absent (~40%) in pediatric CIPO in the neonatal period and universal in adult cases.
  • Unlike in adults, there is a high risk of colonic and small bowel volvulus in pediatric CIPO and malrotation is evident in ~30% of pediatric CIPO (rarely seen in adults).
  • Also, in pediatrics, fabricated cases are more commonly encountered.

Intestinal transplantation should be considered in patients with PIPO who develop life-threatening complications associated with TPN or poor quality of life/high morbidity.

Pictures below from yesterday’s Peachtree Road Race and previous T-shirts from previous years.


Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Why Does this Patient Have Colitis?

Just in time for this year’s Peachtree Road Race…

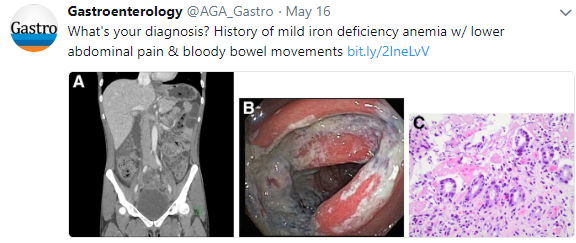
A brief report (RS Robinson et al. Gastroenterol 2018; 154: 1582-83) presents a case of a 28 year old, who had been in training for a marathon, with mild iron deficiency anemia, lower abdominal pain, and bloody bowel movements. The CT scan and colonoscopy showed diffuse colonic/ileal inflammation; the histology showed mucosal necrosis, crypt atrophy and acute inflammation (see below).

Answer to title question: Runner’s Colitis.  The authors note that in some long-distance runners an ischemic colitis can develop in part due to rerouting of blood with prolonged exercise.  Dehydration may exacerbate poor perfusion.  The splenic flexure and the rectosigmoid junction are particularly susceptible due to the ‘watershed’ nature of their blood supply.

The majority of individuals recover fully from this insult, though the literature describes one individual who required a subtotal colectomy after perforation.

HCV Treatment and “MELD Purgatory”

A recent study (A Kwong et al. Liver Transplantation 2018; 24: 735-43) and associated editorial (P Martin, pg 727-8) highlight an unintended consequence of HCV therapeutic success –“MELD purgatory.”

The study notes that with the availability of more effective direct-acting antivirals for HCV, there has been a decrease in wait-list mortality and a decrease in disease severity.  This was determined by reviewing 3 timed cohorts (2004 n=2408, 2009 n=2402, and 2014 n=2817) from the Organ Procurement and Transplantation database.

  • For example, the 2014 had a 21% lower risk of wait-list death (HR 0.79) than the 2009 cohort.  This is in contrast to other (non-HCV) disease in which there was no change in mortality.
  • Also, the MELD rate of change was 2.35 per year for the 2009 cohort compared to 1.90 for the 2014 group.
  • In their discussion, the authors note that while patients with HCV can achieve a sustained virologic response, those with advanced liver disease still need liver transplantation.  In these patient, there is a much lower prospect of attaining a high enough MELD score to receive organ offers –“leaving them with persistent complications and a decreased quality of life.”  This situation has been termed “MELD purgatory.”

The editorial notes that in the five years since the introduction of sofosbuvir, HCV has been displaced as the single commonest indication for liver transplantation by nonalcoholic fatty liver disease.  These agents have led to a decrease in advance HCV-related liver disease.  In addition, in the past, HCV infection had near universal recurrence after transplantation and this is no longer the situation.

My take: Undeniably, the advent of DAA have made a huge dent in progressive HCV liver disease. However, those with advanced liver disease may be stuck in a purgatory between good health and poor quality of life even after clearance of HCV infection.

Related blog posts:

VICTORY Consortium Showing Good Results for Vedolizumab

A presentation at the 13th Congress of the European Crohn’s and Colitis Organization (ECCO, Feb 2018) indicated that Vedolizumab had similar effectiveness as anti-TNF agents for both ulcerative colitis and Crohn’s disease. This data has been presented at a recent meeting in our office, some of the GI news magazines, and also ImproveCareNow listserv.

From Takeda website: Entyvio® (vedolizumab) Shows Higher Rates of Mucosal Healing Versus TNFα-Antagonist Therapy in Ulcerative Colitis and Crohn’s Disease Patients in Comparative Effectiveness Real-World Data Analysis

These analyses observed that patients with UC treated with Entyvio compared to TNFα-antagonist therapy had statistically significant higher 12-month cumulative rates of mucosal healing (50% vs 42%, hazard ratio [HR] 1.73, 95% confidence interval [CI] 1.10‑2.73) and clinical remission (54% vs 37%; HR 1.54, 95% CI 1.08‑2.18), and numerically higher steroid-free clinical remission rates (49% vs 38%; HR 1.43, 95% CI 0.79‑2.60). In CD, results reported statistically significant higher 12-month cumulative rates of mucosal healing (50% vs 41%; HR 1.67, 95% CI 1.13‑2.47), and numerically higher rates of clinical remission (38% vs 34%; HR 1.27, 95% CI 0.91‑1.78) and steroid-free clinical remission (26% vs 18%; HR 1.75, 95% CI 0.90‑3.43) compared to TNFα-antagonist therapy. These analyses were conducted by the VICTORY (Vedolizumab Health OuTComes in InflammatORY Bowel Diseases) Consortium.

My take: While the data compare anti-TNFs to vedolizumab in a “real-world setting,” the reported outcomes for anti-TNFs are lower than in other studies.  Vedolizumab had the best results in those with colonic disease.  Patients with Crohn’s disease with isolated small bowel disease had lower response rates.

Related study: AK Waljee et al Inflamm Bowel Dis 2018; 24: 1185-95. Using phase 3 clinical trial data with 594 subjects, the authors note that the majority of patients who will respond to vedolizumab can be identified by week 6 using a laboratory algorithm based on hemoglobin, albumin, vedolizumab level and CRP. Fformula: Hgb*Albumin*VDZ level/CRP*Weight. A cutoff of 185.96 predicted success with an AuROC of 0.75.   Higher hemoglobin, higher albumin, and higher vedolizumab level, and lower CRP are associate with higher response rates.

Related blog posts:

Red Top Mountain, Homestead Trail