FDA IBD Workshop -Take-Home Points

From a previous blog lecture from Athos Bousvaros (NASPGHAN Postgraduate Course 2014)

Off-label does not equate to experimental

FDA Statement: The FD&C Act does not, however, limit the manner in which a physician may use an approved drug. Once a product has been approved for marketing, a physician may prescribe it for uses or in treatment regimens or patient populations that are not included in approved labeling. Such “unapproved” or, more precisely, “unlabeled” uses may be appropriate and rational in certain circumstances, and may, in fact, reflect approaches to drug therapy that have been extensively reported in medical literature.

A Bunch of Data on Vedolizumab

DE Yung et al. Inflamm Bowel Dis 2018; 24: 2327-38.  This systematic review and meta-analysis of four studies “did not detect an increased risk of postoperative complications with preoperative vedolizumab” (VDZ).  This study included 281 patients who received VDZ.

SC Ng et al. Inflamm Bowel Dis 2018; 24: 2431-41. The authors examined the frequency of opportunistic infection among 4 VDZ trials and postmarketing surveillance, accounting for ~114,000 patient-years of exposure. The most common infection was C difficile (0.5 per 100 patient-years); tuberculosis was reported at 0.1 per 100 patient years. This study showed “that the rate of serious opportunistic infections in patients receiving VDZ was low and most patients could continue VDZ treatment.”

SL Gold et al. Gastroenterol 2018; 155: 981-2. This clinical image showed a case of Henoch-Schonlein Purpura (HSP) that developed in a 53 year receiving VDZ.

E Shmidt et al. Inflamm Bowel Dis 2018; 24: 2461-7.  This retrospective review of a prospectively maintained IBD registry provides information of risk factors for VDZ loss of response and management. 444 patients out of 788 who received VDZ had a significant response.The majority of VDZ recipients 75) had failed prior anti-TNF Rx. Key points:

  • Loss of response (LOR) at 6 months and 12 months was 20% and 35% respectively
  • UC patients compared to Crohn’s disease (CD) patients were more likely to have LOR with R of 1.54.
  • Shortening VDZ infusion interval from q8 weeks to q4-6 weeks recaptured response in 49% and led to remission in 18% of this cohort.
  • LOR was more common (2-fold) among those who had a LOR to anti-TNF agent. Patients with primary nonresponse were less likely to have LOR with VDZ.

U Kopylov et al. Inflamm Bowel Dis 2018; 24: 2442-51. This retrospective multicenter study examined VDZ effectiveness among anti-TNF naive patients, n=184.

  • For CD, 42/50 (82%) responded by week 14, and 32 (64%) were in clnical remission. At last followup (30-52 weeks), clinical remission was noted in 24/35 (69%)
  • For UC, 116/134 (79%) responded at week 14 and 53 (40%) were in clinical remission.  At last followup (30-52 weeks), 67% were in remission (69/103)

The authors conclude that VDZ is similarly efffective for anti-TNF naive CD and UC patients.

My take: These studies show that we still have a lot to learn about the effectiveness of VDZ as its use becomes more widespread.

Related blog posts:

Jasper, Canada


Increased Risk of Eosinophilic Esophagitis in Esophageal Atresia Patients

Briefly noted: U Krishnan et al. Analysis of eosinophilic esophagitis in children with repaired congenital esophageal atresia. JACI 2018. Published online Oct 24, 2018.

This retrospective, single-center study examined 4 eosinophilic esophagitis (EoE) study cohorts and identified EoE in 20 of 110 patients (18%) who had surgically-repaired esophageal atresia.

This association has been seen previously: . 2014 Dec 21; 20(47): 18038–18043.  This case study stated ” We are suggesting that EoE is a frequent concomitant problem in patients with history of congenital esophageal deformities, and for this reason any of these patients with refractory reflux symptoms or dysphagia (with or without anastomotic stricture) may benefit from an endoscopic evaluation with biopsies to rule out EoE.”

Related blog posts:

Transpyloric Feedings -A Reassessment

A recent commentary (MH Wallenstein, DK Stevenson. JAMA Pediatr. 2018;172(11):1004-1005.) discusses the potential advantages of transpyloric feedings in premature infants. Thanks to Ben Gold for this reference.

Key points:

  • First, preterm infants are highly susceptible to pulmonary aspiration, primarily due to, among other factors, immature tone of the lower esophageal sphincter and use of uncuffed endotracheal tubes.”
  • Second, aspiration of gastric contents probably contributes to bronchopulmonary dysplasia..
  • Third, transpyloric feeding is an effective strategy to reduce the risk of aspiration…we believe that early prophylactic transpyloric feeding may be the only effective strategy to prevent aspiration-associated lung injury.
  • Transpyloric feedings “fell out of favor in the 1980s after a single trial showed an increased risk of mortality”

My take (borrowed from authors): “the practice of early transpyloric feeding with human breastmilk merits a thorough reevaluation of its risks and benefits in the setting of modern neonatal practice.”

More from Banff

Time to Change Upper GI Default Orders -No Routine Scout

When I place an order for an upper GI, the computer prompt asks whether this should be with or without a scout film.  A recent retrospective study (S Abdullah et al. JPGN 2018; 67: 576-9) provides data indicating that the default setting should be without a scout xray.

After reviewing UGIs in 197 outpatients over a 2 year period, the authors found that

  • 97% found no significant findings in scout xray
  • 1.5% (n=3) had findings that were not addressed
  • 1% (n=2) had findings that required additional evaluation –both minor lung findings, later deemed insignificant
  • 0.5% (n=1) had a finding which resulted in a change in management –>a cleanout for excessive stool.  The report does not state whether this patient had a rectal exam which generally is more accurate with regards to the need for a cleanout

My take: This study provides convincing data that scout studies are usually unnecessary.  For inpatients, the main reason to order a scout xray would be if a patient had previous contrast that needs to be cleared prior to UGI.

Related blog post: Pre-PEG UGIs Often Unnecessary

Lake Maligne, near Jasper Canada

Association and Causation: Early Life Risk Factors for Eosinophilic Esophagitis

A recent case-control study (CP Witmer et al. JPGN 2018; 610-5) using the Military Health System Database examined 1410 cases of eosinophilic esophagitis (EoE) and matched them with 2820 controls; the study period was 2008-2015.

  • The authors found that early exposure to proton pump inhibitors (PPIs), histamine-2 receptors (H2RAs), and antibiotics were all associated with an increased risk of developing EoE with adjusted odds ratios of 2.73, 1.64, and 1.31.
  • In addition, among atopic problems, milk protein allergy had an adjusted odds ratio of 2.37 and eczema 1.97. –for developing EoE.

My take: This study does not determine whether the use of PPIs, H2RAs or antibiotics are involved in causation of EoE or whether patients with EoE simply receive these medications more frequently.  Nevertheless, the findings reinforce the idea that these medications should be used less frequently in infants.

Related blog posts:

Somewhere near Banff

Differential Microbiome Effects of Prebiotics and low FODMAPs

A recent study (J-W Huaman et al. Gastroenterol 2018; 155: 1004-7) examined the effects of a prebiotic (Bimuno) and a low FODMAPs diet for the treatment of functional GI disorders and their effects on the microbiome.

This was a randomized controlled 4-week trial with a 2-week followup period.  Those who received the prebiotic (N=19) received a placebo diet (Mediterranean-type) and those who were randomized to a low FODMAP diet (n=21) were instructed to consume a placebo.  The prebiotic contained beat-galactooligosaccharide.

Key findings:

  • Both groups had significant reduction in GI symptoms, though low FODMAPs was the only treatment helpful for flatulence/borborygmi.
  • The symptom reduction persisted in the prebiotic group for the 2 -week follow-up period, whereas symptoms reappeared immediately in the low FODMAP group.
  • The two treatments had opposite effects on the intestinal microbiota –the prebiotic treatment led to an increase in bifidobacteria and a decrease in Bilophilia wadsworthia.

My take: (borrowed from editorial pg 960-2): This study “may indicate that the effect of the prebiotic is mediated through its effects on gut microbiota composition, whereas the effect of the low FODMAP diets is more related to the meal composition…than to its effects on gut microbiota composition.”

Related blog posts:

From two of the missions in San Antonio


Sex-Based Differences in Incidence of Inflammatory Bowel Disease

Briefly noted: SC Shah, H Khalili et al. Gastroenterol 2018; 155: 1079-89.

This study evaluated pooled data with 207,600 incident cases of IBD from a population of 478 million. Key findings:

  • Female patients had lower a lower risk of Crohn’s disease during childhood until 10-14 years of age, but then a risk afterwards
  • For ulcerative colitis, there was a divergence in risk after 45 years of age, when men had a significantly higher incidence.

My take: the differences indicate that genetic factors (men with a Y chromosome and only one chromosome X) along with sex hormones play a role in the pathogenesis of IBD.

Graphs depict Female/Male Incidence Rate Ratio

AGREE proceedings: Briefly noted: ES Dellon, CA Liacouras, J Molina-Infante, GT Furuta et al. Gastroenterology 2018; 155: 1022-33.  This report provides updated recommendations from AGREE conference –which have been widely cited previously on this blog and elsewhere.  One of the remarkable features on this report is the fact that there are 64 authors (by my count) –thus reading the affiliations and the conflict of interest disclosures alone would take some time.

For a good review on this topic:

Methotrexate -Not Effective as Monotherapy for Ulcerative Colitis

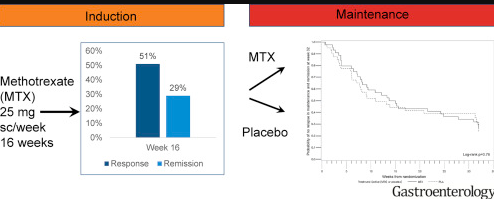
A recent study (H Hansfarth et al. Gastroenterol 2018; 155: 1098-1108) examined the use of methotrexate for ulcerative colitis (UC).  The authors performed a 48-week trial (MERIT-UC trial) with 179 patients with a mean age of 42 years in the induction period.  In those who improved during induction, methotrexate was continued in 44 patients and compared to 40 patients who received placebo; this was a double-blind, placebo-controlled trial.

Key findings:

  • During induction which included 16 weeks with methotrexate at 25 mg per week SC and a 12-week steroid taper, 51% had achieved a response.
  • During maintenance, 60% of patients receiving placebo and 66% of patients receiving methotrexate had a relapse of UC.  At 48 weeks, 30% in the placebo group and 27% in the methotrexate group were in steroid-free clinical remission.
  • No new safety signals were evident with methotrexate.

The associated editorial by Dulai (pg 967-69) which reviewed this study and a prior study (METEOR) comes to the conclusion that: “there is likely no place for methotrexate monotherapy in UC.”

Related blog posts: