“The Fruit Juice Delusion”

From NY Times: The Fruit Juice Delusion

A recent commentary revisits the common misconception of fruit juice being healthy.

Key points:

  • “Americans drink a lot of juice…children consume on average 10 ounces per day, more than twice the amount recommended by the American Academy of Pediatrics.”
  • “One 12-ounce glass of orange juice contains 10 teaspoons of sugar.”
  • Eating whole fruit is “associated with a reduced risk of diabetes, drinking fruit juice is associated with the opposite.”
  • “Juice may also be a ‘gateway beverage’–[to drink] more soda in their school-age years
  • “There is no evidence that juice improves health…Parents should instead serve water and focus on trying to increase children’s intake of whole fruit.”

My take (borrowed from authors): “we have succeeded in recognizing the harm of sugary beverages like soda. We can’t keep pretending that juice is different.”

Related blog posts:


IBD Shorts July 2018

DJ Gracie et al. Gastroenterol 2018; 154: 1635-46. This study of 405 adults indicated that IBD triggers anxiety and that anxiety triggers IBD. Specifically: “Baseline CD or UC disease activity were associated with an almost 6-fold increase in risk for a later abnormal anxiety score (hazard ratio [HR], 5.77; 95% CI, 1.89-17.7).  In patients with quiescent IBD at baseline, baseline abnormal anxiety scores were associated with later need for glucocorticosteroid prescription or flare of IBD activity (HR 2.08; 95% CI, 1.31-3.30).”

RL Dalal, B Shen, DA Schwartz. Inflamm Bowel Dis 2018; 24: 989-96.  This review provides updated information on epidemiology, diagnosis, and treatment recommendations for pouchitis.

A Alper et al. JPGN 2018; 66: 934-6. Key finding: Celiac disease is “not increased in children with IBD compared with non-IBD children with gastrointestinal symptoms.”  False-positive tTG serology can occur.

AK Shaikhkhalil et al. JPGN 2018; 66: 909-14. The authors showed that using a quality-improvement effort, there was increase utilization of enteral exclusive therapy (EEN).  Baseline 5.was <5% and by completion of intervention, utilization increased to approximately 50%. The interventions to achieve this are specified in this article, including talking points.  EEN is described as “nutrition therapy.” Patients are offered oral EEN and if not adequate by 3-4 days, nasogastric feedings are initiated (~15%).  Interestingly, of those to complete EEN therapy, 97% did not need NG placement.

Pictures from Ameilia Island:

Amelia Island

ICN Travel Toolkit -Tips for Patients with Inflammatory Bowel Disease

ImproveCareNow’s Patient Advisory Committee: ICN Travel Toolkit – a collection of personal stories, plus tips and techniques for traveling with IBD – written by members of the ICN Patient Advisory Council (PAC).

In addition to the tips offered by the PAC (see below), I would recommend that those travelling keep a succinct medical summary with the following (minimum):

  • Diagnosis and extent of disease
  • Other medical problems
  • Physician (contact info)
  • Allergies –food/medicines
  • Current list of medications including dosage and frequency
  • List of prior treatments
  • Previous surgeries

Also, below are other travel -related links, including to the CDC travel website which makes recommendations based on travel destination along with underlying problems.

A summary of the ICN travel tips from the PAC PowerPoint Presentation:


Fluid Management for Abdominal Surgery

A recent study (PS Myles et al. NEJM 2018; 378: 2263-74, editorial 2335-6) throws some shade on the idea that restricting IV fluids during surgery results in better outcomes.

With ERAS (enhanced recovery after surgery) procedures, one of the components has been restricting IV fluids during surgery due to concerns that excessive fluid will result in bowel wall edema and slower recovery.  To better determine if a restrictive IV fluid approach or a more liberal approach was better, this RELIEF study randomized approximately 3000 patients who were receiving major abdominal surgery into two arms: a restrictive group and a  liberal group; they received a median of 3.7 liters of IV fluids and 6.1 liters respectively during and up to 24 hours after surgery.

Key findings:

  • Rate of disability-free survival at 1 year was 81.9% in the restrictive group and 82.3% in the liberal group (hazard ratio for death or disability was 1.05, CI 0.88-1.24, P=0.61)
  • Rate of acute kidney injury was 8.6% in the restrictive fluid group compared to 5.0% in the liberal fluid group (P<0.001). Renal replacement therapy was 0.9% in the restrictive fluid group compared to 0.3% in the liberal fluid group (P=0.048).
  • Rates of surgical site infection was 16.5% in the restrictive fluid group compared to 13.6% in the liberal fluid group (P=0.02).  The authors speculate that this could be related to perfusion of surgical anastomosis.

The associated commentary notes that in this age of minimally invasive surgery, a modestly liberal administration of IV fluids does not create substantial fluid retention.

My take: Restrictive fluid regimen during major abdominal surgery resulted in higher rates of kidney injury and surgical site infections.  This study indicates that for ‘enhanced recovery’ that a more liberal fluid regimen is safer.

Related posts:


Pediatric Intestinal Pseudo-obstruction: Consensus Recommendations

A new report from an ESPGHAN-Led Expert Group (N Thapar et al. JPGN 2018; 66: 9991-1019) provides detailed recommendations for pediatric intestinal pseudo-obstruction (PIPO).  In addition, this report serves as an excellent self-assessment of your vision.  If you can read figure 1, which has some incredibly tiny font size, then your vision is fantastic.

Full Link: “Paediatric Intestinal Pseudo-obstruction: Evidence and Consensus-based Recommendations From an ESPGHAN -Led Expert Group”

Aside from that snarky comment, the report offers a great deal of useful advice.

  • After obstruction has been excluded, the authors recommend that patients should undergo a basic laboratory evaluation (including CBC, CMP, ESR/CRP, Celiac serology, Cortisol, Thyroid testing, Metabolic tests [urine organic acids, ammonia, lactate]) and to consider more extensive evaluation.
  • If primary, rather than secondary, PIPO is suspected, the authors recommend neurogastroenterology evaluation.

Subsequently, the authors review management: potential medications (Table 6), enteral feeds, gastrostomy and ileostomy, and in more than 80% then need for parenteral nutrition. At the time of therapeutic procedures, it is recommended to obtain full-thickness biopsies to further characterize the PIPO.

Clinical features which distinguish pediatric chronic intestinal pseudo-obstruction (CIPO) from adult CIPO are listed in Table 2. These include the following:

  • Frequent urologic involvement in pediatric CIPO which is rare in adults with CIPO.
  • Dilated bowel loops are commonly absent (~40%) in pediatric CIPO in the neonatal period and universal in adult cases.
  • Unlike in adults, there is a high risk of colonic and small bowel volvulus in pediatric CIPO and malrotation is evident in ~30% of pediatric CIPO (rarely seen in adults).
  • Also, in pediatrics, fabricated cases are more commonly encountered.

Intestinal transplantation should be considered in patients with PIPO who develop life-threatening complications associated with TPN or poor quality of life/high morbidity.

Pictures below from yesterday’s Peachtree Road Race and previous T-shirts from previous years.

 

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.


Why Does this Patient Have Colitis?

Just in time for this year’s Peachtree Road Race…

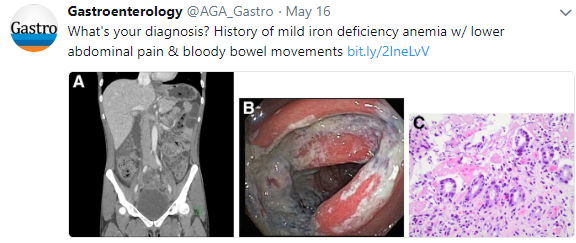
A brief report (RS Robinson et al. Gastroenterol 2018; 154: 1582-83) presents a case of a 28 year old, who had been in training for a marathon, with mild iron deficiency anemia, lower abdominal pain, and bloody bowel movements. The CT scan and colonoscopy showed diffuse colonic/ileal inflammation; the histology showed mucosal necrosis, crypt atrophy and acute inflammation (see below).

Answer to title question: Runner’s Colitis.  The authors note that in some long-distance runners an ischemic colitis can develop in part due to rerouting of blood with prolonged exercise.  Dehydration may exacerbate poor perfusion.  The splenic flexure and the rectosigmoid junction are particularly susceptible due to the ‘watershed’ nature of their blood supply.

The majority of individuals recover fully from this insult, though the literature describes one individual who required a subtotal colectomy after perforation.

VICTORY Consortium Showing Good Results for Vedolizumab

A presentation at the 13th Congress of the European Crohn’s and Colitis Organization (ECCO, Feb 2018) indicated that Vedolizumab had similar effectiveness as anti-TNF agents for both ulcerative colitis and Crohn’s disease. This data has been presented at a recent meeting in our office, some of the GI news magazines, and also ImproveCareNow listserv.

From Takeda website: Entyvio® (vedolizumab) Shows Higher Rates of Mucosal Healing Versus TNFα-Antagonist Therapy in Ulcerative Colitis and Crohn’s Disease Patients in Comparative Effectiveness Real-World Data Analysis

These analyses observed that patients with UC treated with Entyvio compared to TNFα-antagonist therapy had statistically significant higher 12-month cumulative rates of mucosal healing (50% vs 42%, hazard ratio [HR] 1.73, 95% confidence interval [CI] 1.10‑2.73) and clinical remission (54% vs 37%; HR 1.54, 95% CI 1.08‑2.18), and numerically higher steroid-free clinical remission rates (49% vs 38%; HR 1.43, 95% CI 0.79‑2.60). In CD, results reported statistically significant higher 12-month cumulative rates of mucosal healing (50% vs 41%; HR 1.67, 95% CI 1.13‑2.47), and numerically higher rates of clinical remission (38% vs 34%; HR 1.27, 95% CI 0.91‑1.78) and steroid-free clinical remission (26% vs 18%; HR 1.75, 95% CI 0.90‑3.43) compared to TNFα-antagonist therapy. These analyses were conducted by the VICTORY (Vedolizumab Health OuTComes in InflammatORY Bowel Diseases) Consortium.

My take: While the data compare anti-TNFs to vedolizumab in a “real-world setting,” the reported outcomes for anti-TNFs are lower than in other studies.  Vedolizumab had the best results in those with colonic disease.  Patients with Crohn’s disease with isolated small bowel disease had lower response rates.

Related study: AK Waljee et al Inflamm Bowel Dis 2018; 24: 1185-95. Using phase 3 clinical trial data with 594 subjects, the authors note that the majority of patients who will respond to vedolizumab can be identified by week 6 using a laboratory algorithm based on hemoglobin, albumin, vedolizumab level and CRP. Fformula: Hgb*Albumin*VDZ level/CRP*Weight. A cutoff of 185.96 predicted success with an AuROC of 0.75.   Higher hemoglobin, higher albumin, and higher vedolizumab level, and lower CRP are associate with higher response rates.

Related blog posts:

Red Top Mountain, Homestead Trail


What to Make of Median Arcuate Ligament Syndrome

A recent study (C Stiles-Shields et al. JPGN 2018; 66: 71) reports on 32 cases of median arcuate ligament syndrome (MALS) from a single center, 2011-17.  To me, this is an astounding number of individuals who were operated on for this disorder.  As the authors note, “MALS remains a controversial and vexing condition. 13% to 50% of healthy patients may exhibit radiographic features of celiac artery compression.”

While the authors note that pain symptoms improved significantly, they report that “comorbid psychological conditions were common, occurring in about half the sample before and after surgery.”

My take: If one finds celiac artery compression and suspects MALS, it is unclear to me if an operation is indicated and how to determine when it is indicated.

Related blog post:

Proctor Creek Trail

Which Proton Pump Inhibitor is the Most Potent?

A recent study (DY Graham, A Tansel. Clin Gastroenterol Hepatol 2018; 16: 800-808) analyzed 56 randomized trials to determine relative potency of proton pump inhibitors (PPIs) based on time in which intragastric pH was 4 or less (pH4time).

Key findings:

  • Pantoprazole 20 mg was equivalent to 4.5 mg of omeprazole
  • Lansoprazole 15 mg was equivalent to 13.5 mg of omeprazole
  • Esomeprazole 20 mg was equivalent to 32 mg of omeprazole
  • Rabeprazole 20 mg was equivalent to 36 mg of omeprazole

The authors note that peak effectiveness for PPIs was at ‘approximately 70 mg of omeprazole equivalents’.  In addition, they state that twice a day dosing was more effective than increasing once a day dosing; however, three times a day dosing was not more effective than twice a day. “Dexlansoprazole, a quasi-twice-a-day formulation produced similar acid suppression to the lowest twice-daily PPI regimen and 20 mg vonoprazan once daily provided similar efficacy aas high-dose twice-daily PPI.” The authors also compare costs; generics of pantoprazole, omeprazole, and esomeprazole cost as little as $0.02-0.04 per omeprazole equivalent.  Thus, 20 mg of omeprazole would be as little as 40 cents.

My take: Using the lowest effective dose of a PPI is recommended.  In patients needing higher dosing or with suboptimal response to acid suppression, this data can be very helpful.


Proctor Creek Trail