From ImproveCareNow: Resources for Mind Body Interventions

From ImproveCareNow: Resources for Mind Body Interventions

The above linked-website has links to many others for patients and providers: meditation, mindfulness, yoga and guided imagery.  The links on this page borrowed from Chelly Dykes and KT Park who credits Dr. Sindu Vellanki and Dr Ann Ming Yeh from Stanford.

 

Literature on these topics (also from ImproveCareNow): Mind Body Interventions and IBD

Mind Body Interventions and IBD – Journal Articles

Overview:

  • Yeh, A. M., Wren, A., & Golianu, B. (2017). Mind–Body Interventions for Pediatric Inflammatory Bowel Disease. Children, 4(4), 22. doi:10.3390/children4040022
  • Mindfulness/ Meditation/ Mindfulness based Stress Reduction (MBSR):
  • Kabat-Zinn, J., Lipworth, L., Burney, R., & Sellers, W. (1987). Four-Year Follow-Up of a Meditation-Based Program for the Self-Regulation of Chronic Pain: Treatment Outcomes and Compliance. The Clinical Journal of Pain, 3(1), 60.

**Note: This is an overview of MBSR, not IBD specific

Mindfulness:

  • Neilson, K., Ftanou, M., Monshat, K., Salzberg, M., Bell, S., Kamm, M. A., . . . Castle, D. (2016). A Controlled Study of a Group Mindfulness Intervention for Individuals Living With Inflammatory Bowel Disease. Inflammatory Bowel Diseases, 22(3), 694-701.
  • Jedel, S., Hoffman, A., Merriman, P., Swanson, B., Voigt, R., Rajan, K., . . . Keshavarzian, A. (2014). A Randomized Controlled Trial of Mindfulness-Based Stress Reduction to Prevent Flare-Up in Patients with Inactive Ulcerative Colitis. Digestion, 89(2), 142-155.
  • Hood, M. M., & Jedel, S. (2017). Mindfulness-Based Interventions in Inflammatory Bowel Disease. Gastroenterology Clinics of North America, 46(4), 859-874.
  • Berrill, J. W., Sadlier, M., Hood, K., & Green, J. T. (2014). Mindfulness-based therapy for inflammatory bowel disease patients with functional abdominal symptoms or high perceived stress levels. Journal of Crohns and Colitis,8(9), 945-955. doi:10.1016/j.crohns.2014.01.018
  • Gerbarg, P. L., Jacob, V. E., Stevens, L., Bosworth, B. P., Chabouni, F., Defilippis, E. M., . . . Scherl, E. J. (2015). The Effect of Breathing, Movement, and Meditation on Psychological and Physical Symptoms and Inflammatory Biomarkers in Inflammatory Bowel Disease.Inflammatory Bowel Diseases,21(12), 2886-2896.

Clinical Hypnosis:

  • Keefer, L., Taft, T. H., Kiebles, J. L., Martinovich, Z., Barrett, T. A., & Palsson, O. S. (2013). Gut-directed hypnotherapy significantly augments clinical remission in quiescent ulcerative colitis. Alimentary Pharmacology & Therapeutics,38(7), 761-771.
  • Mawdsley, J. E., Jenkins, D. G., Macey, M. G., Langmead, L., & Rampton, D. S. (2008). The Effect of Hypnosis on Systemic and Rectal Mucosal Measures of Inflammation in Ulcerative Colitis. The American Journal of Gastroenterology,103(6), 1460-1469.
  • Shaoul, R., Sukhotnik, I., & Mogilner, J. (2009). Hypnosis as an Adjuvant Treatment for Children With Inflammatory Bowel Disease. Journal of Developmental & Behavioral Pediatrics,30(3), 268.
  • Vlieger, A., Govers, A., Frankenhuis, C., & Benninga, M. (2010). Hypnotherapy for children with functional abdominal pain or irritable bowel syndrome: Long term follow-up. European Journal of Integrative Medicine,2(4), 191.

Yoga: 

IBS + Yoga:

  • Schumann, D., Anheyer, D., Lauche, R., Dobos, G. Langhorst, J., Cramer, H. Effect of Yoga in the Therapy of Irritable Bowel Syndrome: A Systematic Review. Clin. Gastroenterol. Hepatol.  2016, 14, 1720-1731.
  • Selvan, S. R., Kavuri, V., Selvan, P., Malamud, A., & Raghuram, N. (2015). Randomized clinical trial study of Yoga therapy for Irritable Bowel Syndrome (IBS). European Journal of Integrative Medicine,7, 23.
  • Kuttner, L., Chambers, C., Hardial, J., Israel, D., Jacobson, K., Evans, K. A Randomized Trial of Yoga for Adolescents with Irritable Bowel Syndrome. Pain Research & Management 2006, 11, 217-223.
  • Evans, S., Lung, K., Seidman, L., Sternlieb, B., Zeltzer, L., & Tsao, J. (2014). (567) Iyengar yoga for adolescents and young adults with irritable bowel syndrome (IBS). J. Pediatri. Gastroenterol. Nutri. 2014, 59, 244-253.

IBD + Yoga:


Concurrent Infections in Inflammatory Bowel Disease Flares

Briefly noted: Y Hanada et al. Clin Gastroenterol Hepatol 2018; 16: 528-33.

In this retrospective review with 9247 patients with IBD, the incidence of bacterial pathogens (non-C diff) identified was <3% of those who were tested; in this group (n=25), Aeromonas was detected in 8,Salmonella in 7, Plesiomonas in 4, Campylobacter in 2, and Yersinia in 2.  From authors: “These infections did not have a significant negative impact on patient outcomes.  Given these findings, routine testing for infections other than CDI is not recommended.”

Chattahoochee River

Algorithm for “Cursed” Dyspepsia

A recent review (P Koduru et al. Clin Gastroenterol Hepatol 2018; 16: 467-79) provides a good review of dyspepsia and in addition provides some literary perspective.

In their introduction, the authors quote James Joyce in Ulysses: “Tom Rochford split powder from a twisted paper into the water set before him –That cursed dyspepsia, he said before drinking. –Breadsoda is very good Davy.”

After reviewing the definition and the pathophysiology, the authors provide a suggested algorithm (Figure 2).

Initial options:

  • In areas with high H pylori, there is an option of “test and treat” and relying on endoscopy in those who fail to respond
  • Empiric PPI therapy which works best if reflux-type symptoms are present and relying on endoscopy in those who fail to respond
  • Endoscopy without empiric treatment

In those with a negative endoscopy –>functional dyspepsia treatment is driven by symptoms:

  • If pain, the first line option recommended is a tricyclic antidepressant (pain modulator)
  • If nausea, the first line option recommended is an antiemetic
  • If early satiety, the first line option recommended is buspirone

For those with resistant and disabling symptoms, “consider nonpharmacologic approaches, such as psychotherapy or acupuncture.”

Related posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Hemospray for GI Bleeding

From MD Mag: Gastrointestinal Bleeding Spray Gets FDA Marketing Go-Ahead

An excerpt:

 According to Wilson-Cook, Hemospray represents a different approach to treat GI bleeds by reaching hemostasis in patients without the precision or direct visualization required by competing treatments. This makes the device a treatment option for bleeding from damaged tissue where the bleeding source cannot be easily identified.

Hemospray is intended to treat most forms of upper or lower GI bleeding, and is backed by clinical evidence in more than 700 patients.

Its approval was supported by data from clinical studies that consisted of 228 patients with upper and lower GI bleeding, and real-world evidence from medical literature reports that featured another 522 similar patients. According to FDA review, the device stopped GI bleeding in 95% of patients with 5 minutes of its administration. Re-bleeding, as defined by a recurring event from 3-30 days after the use of Hemospray, occurred in 20% of all patients.

Pediatric Experience with Presumed Biliary Dyskinesia

A recent study (SR Matta et al. JPGN 2018; 66: 808-10) highlights the frequency of cholecystectomies for “presumed biliary dyskinesia” in the United States.

Using a nationwide inpatient database, the authors examined the indication for cholecystectomy in the pediatric population from 2002 to 2011.

Key findings:

  • During the study period, the authors identified 66,380 cholecystectomies in children.  The leading indications were calculus cholecystitis (73.6%), biliary dyskinesia (10.8%), and chronic cholecystitis without calculus.
  • The frequency of biliary dyskinesia as the indication for cholecystectomy jumped significantly during the study period, particularly the first few years: 6.6% (2002), 7.8% (2003), 9.8% (2004), 10.4% (2005 & 2006), 9.9% (2007), 11.8% (2008), 9.6% (2009), 11.9% (2010), and 10.6% (2011).
  • 75% of cases were children >12 years, and 77.5% were females.

The results from the study and the way that biliary dyskinesia is controversial are reviewed in the discussion.

  • A large proportion of biliary dyskinesia patients will develop symptoms suggestive of another functional GI disorder
  • Long-term resolution of symptoms with cholecystectomy is highly variable after surgery and “55-85% of  children with biliary dyskinesia will improve with medical management.”
  • Prospective studies are lacking, but some retrospective studies have recommended using lower cut off values for ejection fraction(eg. <15-% instead of <35%); whereas, other studies have shown no correlation between ejection fraction and outcomes.

My take: Sometimes a ‘quick fix’ is not a fix at all. As this study notes, it is difficult to rely on the diagnosis of biliary dyskinesia.  Many will improve without surgery and many develop divergent symptoms.

Related blog posts:

Big Creek Greenway, not far from McFarland

Esophageal Atresia and Barrett’s Esophagus

Briefly noted: FWT Vergouwe et al. Clin Gastroenterol Hepatol 2018; 16: 513-21.

In this prospective study of adult patients with esophageal atresia (EA) with 151 participants, 6.6% had Barrett’s Esophagus (BE); squamous cell cancer (SCC) was identified in 0.7% (youngest at 42 years).  The authors note that the prevalence of BE and SCC were ~4-fold and ~100-fold higher, respectively, compared to the general population.

Related blog posts:

Creek near Chattahoochee River

How Helicobacter pylori Survives in the Stomach

A recent basic science study (P Morey et al. Gastroenterol 2018; 154: 1391-1404) explains one of the mechanisms whereby Helicobacter pylori survives in the stomach.

The researchers used MKN45 gastric epithelial cells and human gastric cells obtained from patients undergoing gastric resections and exposed them to H pylori strains. They did additional studies in infected mice.

This report has a number of cool figures demonstrating that H pylori blocks the assembly of interferon and other cytokines.  Infected gastric cells were depleted of cholesterol which rendered them unable to respond properly to inflammatory signals from immune cells.  H pylori is able to decrease inflammation at sites of colonization while inducing inflammation in adjacent noninfected epithelium.  The authors note that patients with increased serum cholesterol (especially LDL) are at increased risk for severe H pylori gastritis.

Big Creek Greenway, Alpharetta

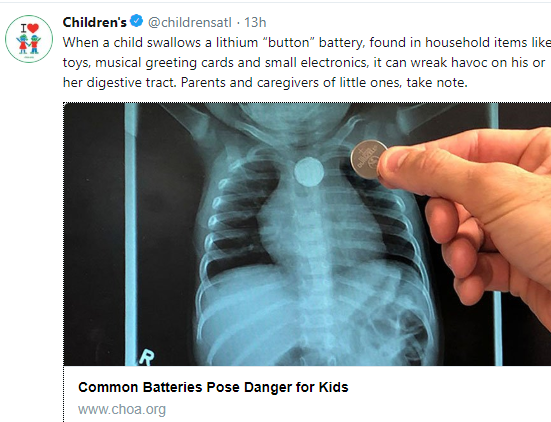
Button Battery -Update For Families

Children’s Healthcare of Atlanta Hope & Will blog: Common Batteries Pose Danger For Kids

Related blog posts:

Reliability of High Serology in Asymptomatic Celiac Disease

Another study (SP Paul et al. JPGN 2018; 66: 641-44) has shown that high anti-TTG IgA levels are reliable in establishing the diagnosis of celiac disease in asymptomatic children from high-risk groups. In this study with prospectively-collected data from 2007-2017, 84 of 157 children had anti-TTG titers >10x ULN.  75 of these 84 were from high-risk groups, mainly type 1 diabetes (36), and first degree relatives (24)

Key finding:

  • All 75 with high titers from high-risk groups had histologic evidence of celiac disease.

Related blog posts:

Related study: R Mandile et al. JPGN 2018; 66: 654-56. This prospective study showed that 19 of 35 (54%) patients with potential celiac disease had a complete clinical response on a gluten-free diet to symptoms like abdominal pain and diarrhea.  Thus, in many patients with potential celiac disease, a gluten-free diet will not be effective.

Related blog posts: