Neuro-Stim for Refractory Cyclic Vomiting?

K Karrento et al. JPGN 2023; 77: 347-353. Percutaneous Electrical Nerve Field Stimulation for Drug-Refractory Pediatric Cyclic Vomiting Syndrome

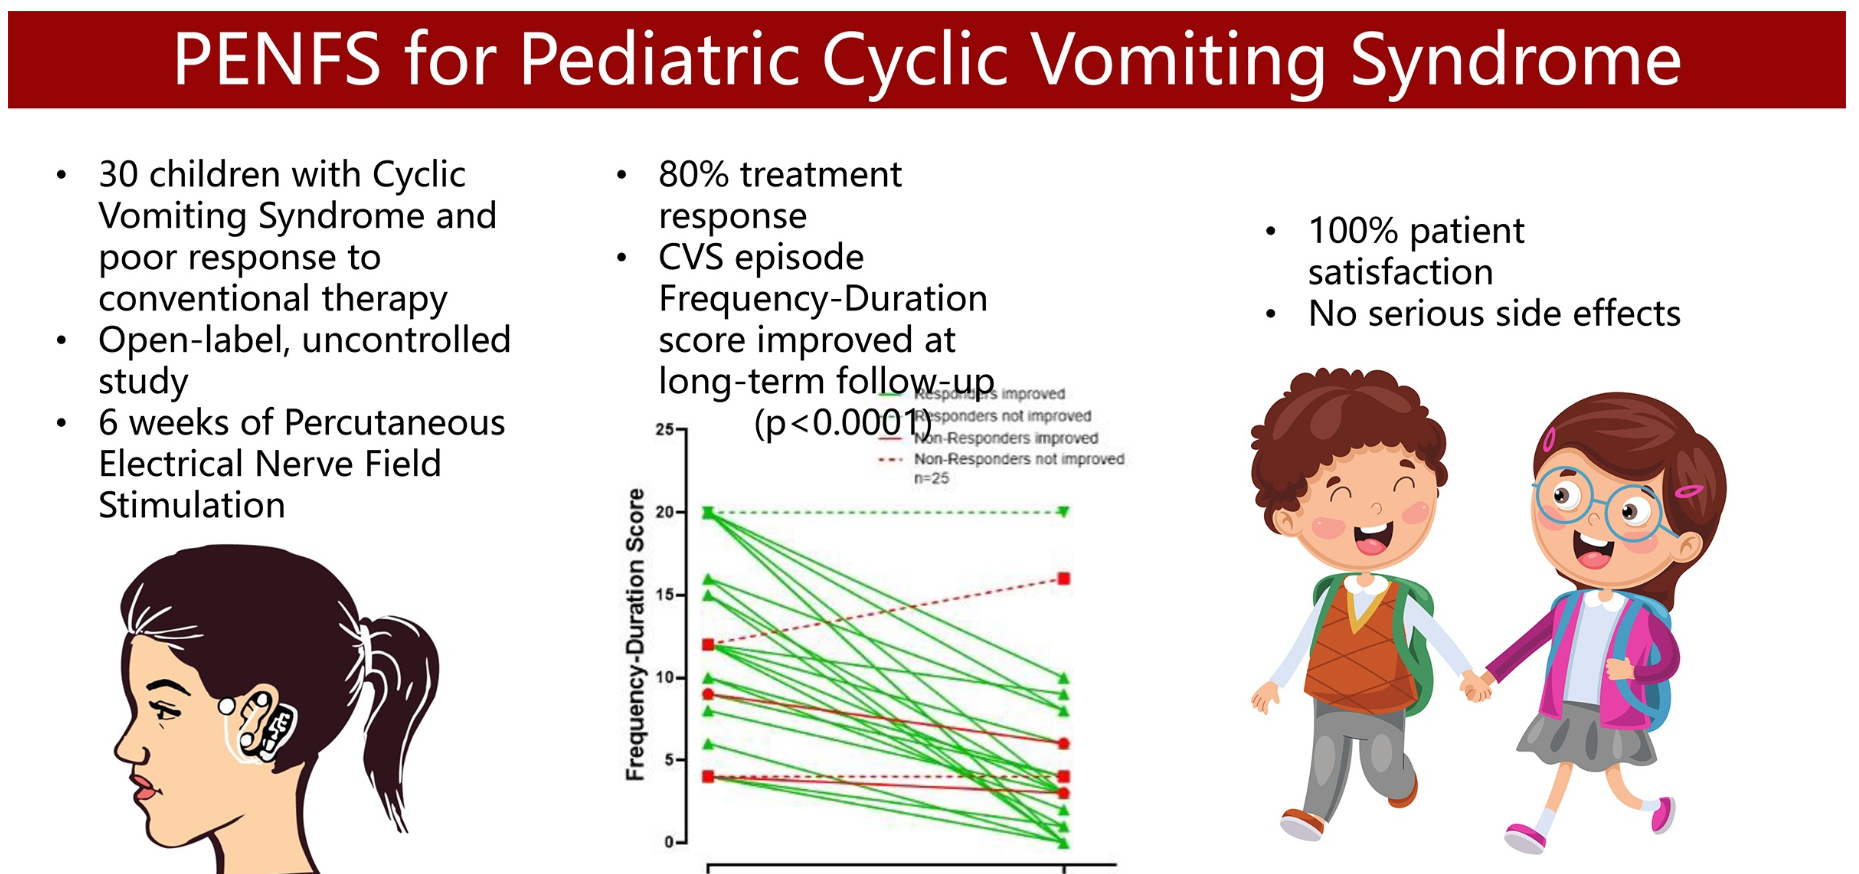
In this prospective study with 30 children with drug-refractory CVS, response was classified as ≥50% improvement in either frequency or duration of attacks at extended follow-up.

Key findings:

  • At follow-up, 80% met criteria for treatment response with a median (IQR) response duration of 113 (61–182) days.
  • At end of therapy, 66% and 55% patients reported global response of at least “moderately better” and “a good deal better,” respectively.
  • There were no serious side effects.

Limitations: episodic nature of CVS, no control group, hx/o strong placebo control group and lack of validated assessment tool

My take: 1. As with the drug therapies with CVS, it is difficult to know how effective PENFS is for CVS. At the same time, its good safety profile makes this therapy an intriguing option in those not responding to more typical treatments. 2. The visual abstract is funny -mainly due to the two laughing kids holding hands. Though it would be even better if the person on the left was puking a lot instead of having a PENFS device.

Related blog posts:

How to Provide More Cost-Effective Celiac Care

PF Farmer et al. J Pediatr 2023; 259: 113487. Single-Center Analysis of Essential Laboratory Testing in Patients with Newly Diagnosed Celiac Disease

In this study, the authors analyzed laboratory testing results from pediatric patients newly diagnosed with celiac disease (2018-2021) to determine the usefulness of each test derived from recommended guidelines (J Snyder et al. Pediatrics 2016; 138: e20153147). Screening protocols in their center resulted in an estimated cost of approximately $320,000 during the study. Tests at diagnosis included hemoglobin, alanine/aspartate aminotransferase, ferritin, iron, TSH, Free T4, and vitamin D screening. These screening tests were done in ~80% of 468 patients.

Key findings:

  • Ferritin was abnormal in 29%, hemoglobin was abnormal in 12%, and iron was abnormal in 22%. Abnormal ferritin captured all patients in this cohort with an abnormal iron. If ferritin was used as an isolated screen with reflective iron testing, this would have reduced costs by about $12,000
  • AST and ALT were abnormal in 2% and 11% respectively
  • 25-OH Vitamin D was abnormal in 14%. Recent data indicated that low Vit D levels are similar among patients with and without celiac disease (R Ahlawat et al. JPGN 2019; 69: 449-454)
  • TSH and Free T4 were abnormal in 7% and 0.3% respectively. For thyroid disease, TSH and free T4 testing did not lead to any new diagnosis of thyroid disease (7 carried a preexisting diagnosis). There were 19 additional patients with abnormal lab values who had more testing due to initial abnormalities. If TSH alone were used for screening, costs savings would be about $29,000. If no thyroid testing were done, this would have reduced costs by about $40,000.
  • Hepatitis B immunity was NOT present in 69%. However, recent studies have shown similar levels of immunity in those with and without celiac disease. In addition, it is not clear that a low level hepatitis B surface antibody always indicates a lack of immunity. Eliminating hepatitis B screening would have reduced costs by about $63,000.
  • The authors note that the cost savings by adopting their recommendations would have saved about $104,000 (out of $320,000).

My take: This is a very useful study and indicates that curtailing initial testing for celiac disease could reduce costs substantially and without compromising care. This would include not checking a serum iron, a free T4, or hepatitis B studies. The authors note that the value of Vit D testing is also questionable but may be worthwhile due to increased risk of bone disease in individuals with celiac disease.

Related blog posts:

Blackwater Falls near Davis, WV
Seneca Rocks Trail, WV

Nonanaphylactic Alpha-Gal and Chronic Gastrointestinal Symptoms

D Glynn et al. J Pediatr 2023; 259: 113486. Nonanaphylactic Variant of Alpha-Gal Syndrome as an Etiology for Chronic Gastrointestinal Symptoms in Children

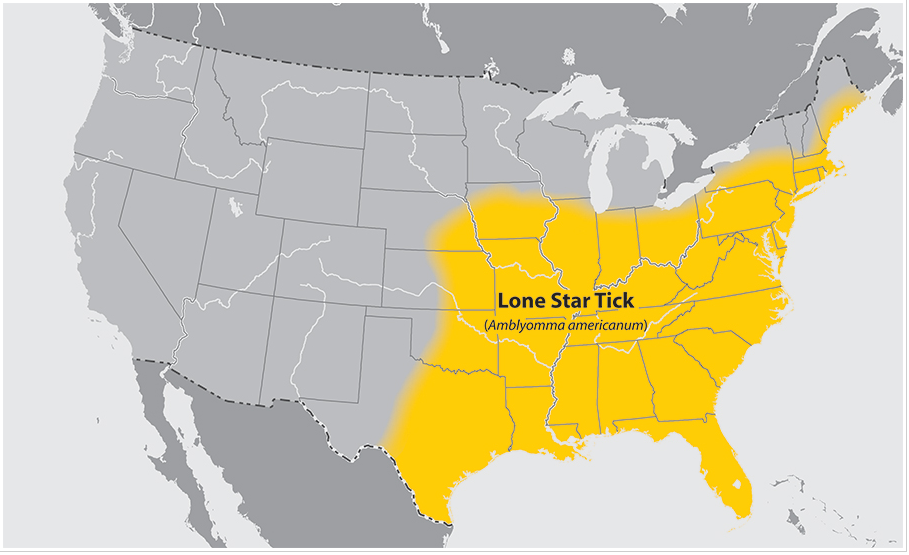
Background: A CDC report showed that between 2010 and 2022, more than 110,000 suspected cases of alpha-gal syndrome were identified. The majority of cases are linked to bites from the lone star tick which affects much of the U.S. (map below) as well as Central and South America, Asia, Africa, Australia and parts of Europe.

Findings: This study reports 3 pediatric patients who presented with only nonanaphylactic symptoms of alpha-gal syndrome. These patients with recurrent gastrointestinal distress and emesis after consuming mammalian meat, even in the absence of an anaphylactic reaction.

The diagnosis in these three patients was established by history, serum alpha-gal immunoglobulin E elevation and response to avoidance of red meat.

My take: Checking a serum Alpha-gal IgE seems like a good idea in some children with unexplained abdominal pain with episodic exacerbation with vomiting, especially if tick exposure. Anecdotally, I have checked this a few times and so far I have not I identified a case. Most cases of Alpha-gal will be associated with urticaria.

Related blog post: Tick Bites Can Lead to Allergy to Red Meat

CDC: Alpha-gal syndrome “Symptoms commonly appear 2-6 hours after eating meat or dairy products, or after exposure to products containing alpha-gal (for example, gelatin-coated medications).”

CDC: Food products that may contain alpha-gal: Mammalian meat (such as beef, pork, lamb, venison, rabbit, etc.) can contain high amounts of alpha-gal. Food products that contain milk and milk products typically contain alpha-gal (though many patients tolerate dairy products)

Foods that do NOT contain alpha-gal (unless cross contamination):

  • Poultry, such as chicken, turkey, duck, or quail
  • Eggs
  • Fish and seafood, such as shrimp
  • Fruits and vegetables
From CDC website: https://www.cdc.gov/ticks/maps/lone_star_tick.html

Case Report: 20 month old with Abrupt Vomiting and Multisystem Disease

Case history: A well-nourished previously healthy 20 month old was admitted to the hospital with a one week history of frequent vomiting. He had a history of frequent lint ingestion. He had been seen by three different health care providers during the week prior to his admission.

At the time of admission, he had numerous electrolyte derangements (Na 124, K 3.2, CL 76) and acute kidney dysfunction with a BUN of 118 and Creatinine of 3.06. He had severe multisystem disease including severe ventricular dysfunction (BNP 2196). He needed an oscillator ventilator, dialysis and cardiac medications (including epinephrine, and milrinone).

He had an extensive evaluation. After he had stabilized and then markedly improved (12 days after admission), an UGI study demonstrated an obstruction near the 2nd-3rd portion of the duodenum with a dilated proximal duodenum.

UGI study:

Due to the obstruction which was thought to be anatomic, the GI service deferred management to pediatric surgery. The surgical service requested GI inspection with endoscopy immediately prior to surgery. If a bezoar was identified, the surgical plan was for a mini-laparotomy. If not, the surgical plan was for laparoscopy repair.

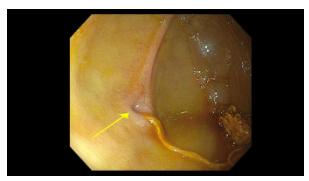
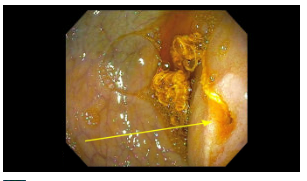
Endoscopy findings: There was a narrowed opening (different orientation of same narrowing in both pictures) with a string-like material.

Surgical findings: A duodenal web with a piece of lint was identified. The patient had a laparoscopic wedge excision with a transverse closure of the duodenotomy. The lint may have occluded the tiny opening of the web that he had been living with since he was born.

My take: This is the first time I have seen the endoscopic appearance of a duodenal web.

In my view, this was a ‘great case.’ In a commentary by Jerome Groopman (N Engl J Med 2004; 351:2043-2045), his wife noted that a case is “a great case because you not only make the diagnosis — you do something fundamental about it. You can really help.” However, Dr. Groopman stopped using the words, ‘a great case’ after his personal experience when his son was severely ill as an infant with a bowel obstruction due to intussusception: “For me and for Pam, the experience had no resonance of “a great case.” There was no intellectual pleasure in solving a clinical puzzle, no charge of exhilaration from the drama of the operation. Instead, there was terror, raw and palpable, as we realized how close we had come to burying our first son….I still find myself unable, except in retrospect, to retrieve the language of my youth and speak about “a great case.” It is as if medicine at this stage of my life has split into two streams — a current of marvelous biology and an undertow that pulls at the soul.”

Subcutaneous Vedolizumab Now FDA-Approved for Adults with Ulcerative Colitis

9/27/23 Takeda: U.S. FDA Approves Subcutaneous Administration of Takeda’s ENTYVIO® (vedolizumab) for Maintenance Therapy in Moderately to Severely Active Ulcerative Colitis

” Takeda (TSE:4502/NYSE:TAK) today announced that the U.S. Food and Drug Administration (FDA) has approved a subcutaneous (SC) administration of ENTYVIO® (vedolizumab) for maintenance therapy in adults with moderately to severely active ulcerative colitis (UC) after induction therapy with ENTYVIO intravenous (IV).1 ENTYVIO SC is expected to be available in the U.S. as a single-dose pre-filled pen (ENTYVIO Pen) by the end of October. Additionally, a Biologics License Application for an investigational SC administration of ENTYVIO for the treatment of adults with moderately to severely active Crohn’s disease is currently under review by the FDA.”

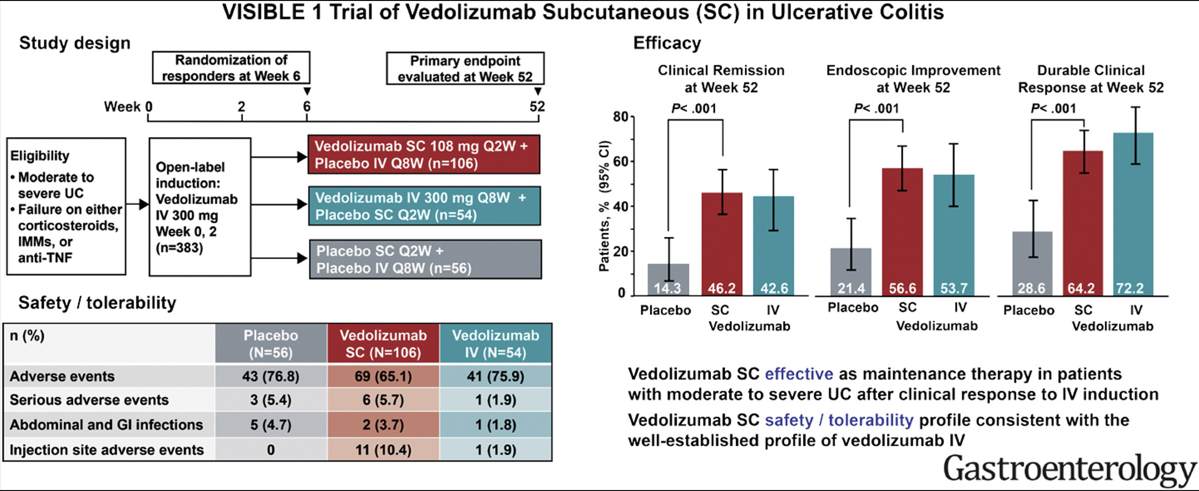
From WJ Sandborn et al. Gastroenterol 2020; 158: 562-572. Open Access! Efficacy and Safety of Vedolizumab Subcutaneous Formulation in a Randomized Trial of Patients With Ulcerative Colitis

In the VISIBLE1 Trial, dosing was IV for week 0 and 2, then every other week SC for maintenance.

Out of Pocket Maximum (Sad Humor)

Dr. Glaucomflecken Twitter Link (w/o login): Out of Pocket Maximum (1:13 min)

There are a bunch of new videos (one for everyday in September) similar to this on related topics -search 30 Days of US Healthcare. Here’s another one: 30 Days of US Healthcare: Surprise Billing (YouTube)

My take: As usual, Dr. Glaucomflecken humor sheds light on the faults in our nation’s health care insurance coverage.

The Quality of Evidence for Dietary Treatments in Inflammatory Bowel Disease

BN Limketkai et al. Clin Gastroenterol Hepatol 2023; 21: 2508-2525. Open Access! Dietary Interventions for the Treatment of Inflammatory Bowel Diseases: An Updated Systematic Review and Meta-analysis

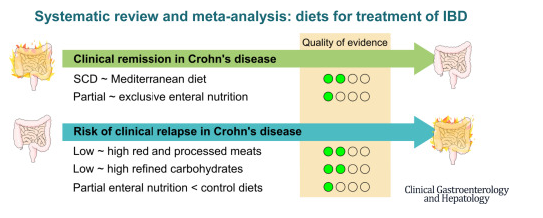
This was a systematic review of prospective controlled trials (n=27) of solid food diets for the induction or maintenance of remission in IBD.

Key findings:

  • For induction of remission in Crohn’s disease (CD), the Mediterranean diet was similar to the Specific Carbohydrate Diet (low certainty of evidence), and partial enteral nutrition (PEN) was similar to exclusive enteral nutrition (very low certainty of evidence).
  • PEN reduced risk of relapse (very low certainty of evidence), whereas reduction of red meat or refined carbohydrates did not (low certainty of evidence).
  • For ulcerative colitis, diets were similar to controls (very low and low certainty of evidence).

My take: Most of the dietary treatments for IBD have low to very low certainty of evidence regarding their effectiveness. Dietary changes are very likely to be helpful but more studies with rigorous endpoints are still needed.

Related blog posts:

Gastroparesis is Frequently Misdiagnosed

D Cangemi, L Stephens, BE Lacy. Clin Gastroenterol Hepatol 2023; 2670-2672. Misdiagnosis of Gastroparesis is Common: A Retrospective Review of Patients Referred to a Tertiary Gastroenterology Practice

In this retrospective study with adult patients (n=339) referred specifically to a tertiary center for evaluation of gastroparesis (GP) from 2019-2021, the key findings:

  • Nausea was most common symptom (in 89%), followed by abdominal pain (76%, constipation (71%), vomiting (66%), bloating (38%) and early satiety (35%)
  • 196 (58%) had undergone a prior gastric emptying study; though only 23 (7%) had ingested radiolabeled eggs as the test meal.
  • 66 (19.5%) ultimately received a diagnosis of GP; 80.5% received alterative diagnosis including functional dyspepsia in 44.5%. In those with GP, diabetes was more common (40% vs. 17%, P=.017).
  • GP patients more often had retained food in the stomach during EGD (23% vs. 11%, P=.013)

My take: In adults (& probably in children), most individuals labelled as having gastroparesis actually have an alternative explanation, usually functional dyspepsia. The symptoms are indistinguishable and improperly performed scintigraphy contributes to confusion.

Related blog posts:

Nelson Rocks, Circleville, WV

Getting over the Stigma of Medicines for Anxiety/Depression and Obesity

This is a terrific personal account of starting medications for anxiety/depression and obesity.

NY Times: Aaron Carroll 9/9/23, What Obesity Drugs and Antidepressants Have in Common

An excerpt:

Until a few years ago, I had controlled my depression and anxiety through decades of counseling. I was reluctant to try medications because the medical understanding of them seemed vague…We also can’t explain why some people benefit from S.S.R.I.s and others do not. Because of this, many people still believe those who take them don’t really need them. I also believed that, if I was strong enough, I didn’t need medication…

I was wrong to doubt. It’s had a remarkable effect on my mood, and almost everyone around me noticed the difference. I was more optimistic, friendlier and more engaging. I was forced to reconsider why I had avoided taking the medication for so long. I think it’s because — even though I realize this isn’t true — taking it felt like an admission of failure…

I’ve recently faced a similar scenario with new drugs for obesity. I’ve struggled with my weight for most of my life. I’ve always been overweight, and in the last few years, I’ve slipped into obesity, according to my body mass index. I exercise regularly and carry the weight well, but it bothers me immensely. It especially troubles me because I have a fair amount of self-discipline and eat quite healthfully…

Despite all the advances in science, we don’t know why some people, even when they try desperately, can’t seem to lose weight. Because of that, we often assume it must be a lack of willpower…

These drugs are expensive, but I was determined to see what would happen if I took one. It is hard to explain what life is like on this medication to people who don’t have trouble controlling their weight. I’m not hungry all the time. I’m not thinking about food incessantly. I’m not obsessing about what I wish I could eat and what I can’t. My mental health, and even my temperament, improved so much that my whole family rejoiced…

Before writing this essay, I had told just a few people I’m on the drug. I think it’s because, on some level, I still feel shame. I felt the same when I finally started taking an antidepressant…

Medical treatments should not be dismissed just because we don’t fully grasp their mechanisms; people who use them are not cheating.

Related blog posts:

Photos from Washington DC