Why We Are Not Making Progress with Probiotics

A recent commentary A Khoruts et al. Gastroenterol 2020; 159: 409-413. Full text: Probiotics: Promise, Evidence, and Hope

Despite the fact that the probiotic industry has ample money which is projected to reach $70 billion yearly, there is very little high quality research.

Key points:

  • Probiotics are regulated by the Food and Drug Administration (FDA) and the Federal Trade Commission (FTC). The FDA, unlike the FTC, regulates products by category (eg, foods, drugs, dietary supplements, medical devices, and cosmetics)…Foods and dietary supplements, unlike drugs, do not require FDA premarket approval. By law, probiotic foods and dietary supplements must be safe. However, food manufacturers are permitted to make a self-determination of whether their product meets the “generally recognized as safe” (GRAS) designation, typically based on history of prior use”
  • Probiotic food and dietary supplement manufacturers do not have to specify on their product labels the strains they use in probiotic products or specify the number of live microbes of each strain that the product delivers through the end of its shelf life; and, although they are required to have validation of label claims, they are not required to submit it to the FDA
  • Dietary supplements can make structure/function claims, even though they cannot claim to treat any specific disease. These claims can sound very promising and consumers may be hard pressed to distinguish between a statement that a product “improves digestion,” a structure/function claim that is so vague that it is literally untestable
  • Rational selection of donor microbiota should be possible based on microbiome-based diagnostics, as well as in vitro technologies that interrogate the functional potential of complex microbial communities. There are parallel, intensive efforts to develop defined microbial communities. A common theme among these different approaches is deployment of complex assemblages of microorganisms rather than single strains. Such complex consortia are likely to have more consistent and predictable effects.
  • The emergence of microbial therapeutics requires development of a new branch of pharmacology. The challenges of formulation, pharmacokinetics, and pharmacodynamics are very distinct from those of small molecule therapeutics or protein biologics.

My take: “These next-generation probiotics will need to be tested for safety and efficacy in well-designed and properly powered clinical trials.”  Probably the only way that will happen is to empower regulatory agencies to insist that these products are treated like medications.  Given the fact that probiotics are so profitable now with little evidence of efficacy for most strains, I am not optimistic about any changes in the near future.

Related blog posts:

Best Screening For Celiac At All Ages

Another study (MR Khan et al. J Pediatr 2020; 224: 158-61. The Utility of IgA-Based Serologic Markers in Diagnosing Celiac Disease in Children 24 Months of Age or Younger) shows that tissue transglutaminase (TTG) IgA is the best first test, even in children less than 2 years of age.

This was a multicenter retrospective study with 150 children, mean age was 18 months.

Key findings:

  • ~98% of children <2 years of age with celiac disease had an elevated TTG IgA
  • “These findings are consistent with recently published European guidelines, which endorse TTG IgA…as the initial screening test regardless of age.”
  • IgG-based test should be reserved for IgA-deficient children, which was noted in 5.5% of this cohort.
  • Endomysial antibody (EMA) had excellent specificity in this study but was less sensitive; it was negative in 13 of 66 (19.7%) of children with celiac disease (positive in 80%).

My take: TTG IgA is a good first step; based on clinical presentation, further testing (eg. endoscopy) could be warranted in highly-selected cases with negative results.

Related blog posts:

Leading Medical Journals Condemn U.S. Pandemic Response

Multiple prestigious journals have weighed in on the U.S. pandemic response.


From Science Editor-in-Chief
From Nature
Also, from Nature

From The Lancet:

“If logic and justice prevail in the next presidential
administration, universal health coverage, a fairer society,
stronger health institutions, more energetic global
engagement, and a robust research agenda will be the
foundations for America’s renewal. We all have a stake in
America’s success.”

Transanal Irrigation Device -Pediatric Experience

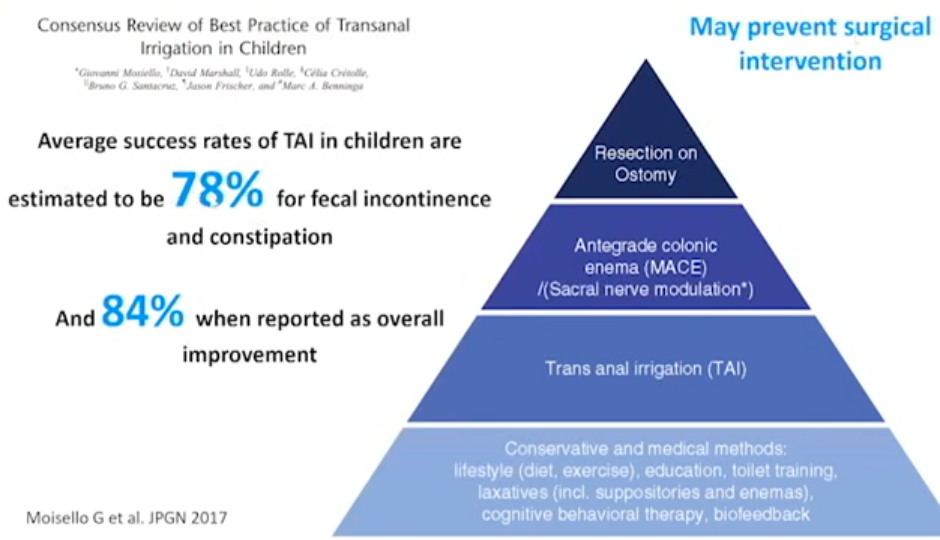
A recent retrospective study (S Patel et al. JPGN 2020; 71: 292-297. Impact of Transanal Irrigation Device in the Management of Children With Fecal Incontinence and Constipation) provides some useful experience in the management of constipation related to bowel dysfunction (n=147), including patients with neurogenic bowel dysfunction (NBD) related to spinal cord defects (NBD, n=85), refractory constipation (RC, n=43), or anorectal malformations (ARMs, n=19).

The authors elaborate on their protocol which includes flushing with warm tap water (on average) 15 mL/kg, generally once a day.  They note that the device is contraindicated in patients <2 years of age and/or within 3 months of anal/colorectal surgery.  The Peristeen device has been FDA approved since 2012.

Key findings:

  • For all patient groups, there was significant improvement in symptoms of fecal incontinence and constipation (P ≤ 0.001).
  • Abdominal pain was improved in the NBD and RC group, but not significantly in the ARM group.

My take: As with other treatment options for these problems, the key to success is adequate upfront training.  The authors note that their training sessions typically last 1-2 hours. A limiting factor with this treatment can be cost.

Useful link: Peristeen Bowel Management

Related blog entries:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition


ANMS Virtual Symposia on Constipation

For those wanting a state-of-the-art review on constipation:

YouTube (1:01) ANMS Virtual Symposia on Constipation

Dr. Jose Garza (one of my partners) gives the first lecture focused on pediatrics -first 18 minutes.

A few points:

  • Miralax is safe (time: 13:45)
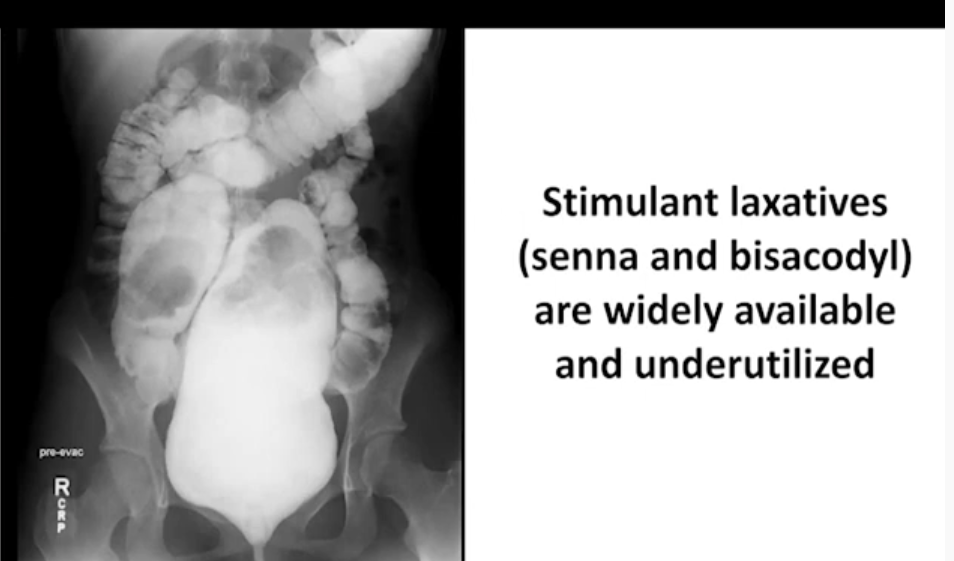
  • Senna and bisacodyl are safe and have not been shown to cause dependence (time 14:55)

Study: No Increased Cancer Risk with Ranitidine

Despite theoretical concerns that impurities with N-nitrosodimethylamine (NMDA) identified in samples of ranitidine (trade name: Zantac) could increase the risk of cancer, a recent study (N Mohyuddin et al. DDW 2020; Abstract#152. RISK OF CANCER WITH USE OF RANITIDINE: RESULTS OF A COHORT STUDY OF 65 MILLION US ADULTS) did not find any evidence of this.

Methods: The authors utilized the Explorys database (IBM, New York) which is a source of longitudinal real world deidentified data collected from electronic medical records from over 40 health systems nationwide (65 million) from 1999-2019.

Key findings:

  • 1.62 million users of ranitidine were identified, 3.37 million users of famotidine, and 59.63 million individuals who did not use either H2 blocker.
  • Users of ranitidine and famotidine when compared to the general population, and users of famotidine when compared to ranitidine, were older (p<0.001), smokers (p<0.001), obese (p<0.001), had liver cirrhosis (p<0.001), a history of alcohol use (p<0.001), and a family history of cancer (p<0.001).
  • Ranitidine users had a numerically lower risk for GI cancers (liver, stomach, esophageal, colorectal, and pancreatic cancers) compared to famotidine. Among subjects without risk factors including smoking, obesity, alcohol use, family history, cirrhosis and GERD, the risk of all cancers (excluding non-melanoma skin cancers) was identical for ranitidine and famotidine (OR=1, CI=1.01-1.02, p=0.001).

My take: This large database did NOT identify an increased risk of malignancy with ranitidine over a 20 year span.  Despite this, I don’t expect that the FDA will reverse its recall.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Missing Care Due to COVID-19

When analyzing health care expenditures, it has been well-recognized that many patients/families cut back on both necessary and unnecessary care when faced with increased costs; that is, individuals are not very good at selecting care that is truly essential.  This is one reason why many health care policy advisors are opposed to  high copays and deductibles as a way of reducing health care costs.

I have seen the same type of problem amidst the pandemic.  Due to fears of contracting SARS-CoV-2 (rather than mainly cost), individuals/families are deferring routine medical care.  This is leading to delays in diagnosis of many serious illnesses and missing opportunities to prevent illnesses (eg. vaccines).  A recent study has shown some of the impact with regard to cancer that happened early in the pandemic (and may be ongoing).

HW Kaufman et al. JAMA Netw Open. 2020;3(8):e2017267. doi:10.1001/jamanetworkopen.2020.17267. Full text: Changes in the Number of US Patients With Newly Identified Cancer Before and During the Coronavirus Disease 2019 (COVID-19) Pandemic

Introduction/Background:  In this study, we analyzed weekly changes in the number of patients with newly identified cancer before and during the COVID-19 pandemic.

Methods: This cross-sectional study included patients across the United States who received testing for any cause by Quest Diagnostic; data was compared between baseline period (January 6, 2019, to February 29, 2020) and the COVID-19 period (March 1 to April 18, 2020). n=278 778 patients. Study evaluated  breast cancer,  colorectal cancer, lung cancer,  pancreatic cancer, gastric cancer, and esophageal cancer.

Key findings:

  • During the pandemic period, the weekly number fell 46.4% (from 4310 to 2310) for the 6 cancers combined, with significant declines in all cancer types, ranging from 24.7% for pancreatic cancer (from 271 to 204; P = .01) to 51.8% for breast cancer (from 2208 to 1064; P < .001)

The authors noted a similar problem has been reported with cardiovascular disease.  A study from 9 high-volume US cardiac catheterization laboratories found a 38% decrease in patients treated for ST-elevation myocardial infarction, considered a life-threatening condition.

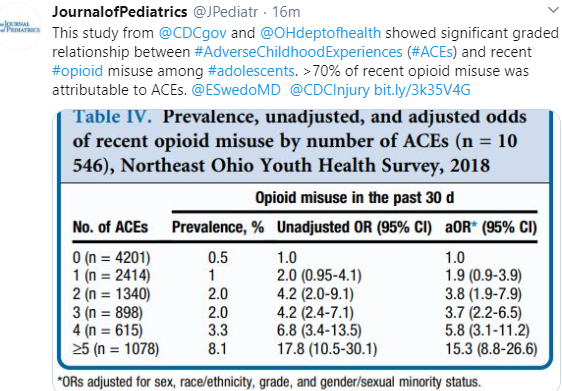
My take: It is difficult to calculate the actual toll of this pandemic which includes a great deal of secondary problems: delays in diagnosis of life-threatening conditions, mental health/suicides, death from poverty, setbacks in the opioid crisis & overdose deaths, and enormous setbacks in global health projects.

Related blog posts:

Elevated Ferritin Evaluation (in adults)

This is a useful article in evaluation of elevated ferritin levels in adults.  This approach is NOT applicable in young children but may have some use in adolescents.  In young children, other considerations include HLH and macrophage activation. In newborns, elevation of ferritin (along with liver dysfunction) may be indicative of GALD (gestational alloimmune liver disease).

W. Palmer et al. AJG 2020; 115: 1353-55. How I Approach Patients With Elevated Serum Ferritin

Image from ACG Twitter Link


Autoimmune Hepatitis -Early Response Associated with Remission

Briefly noted: S Pape et al .Clin Gastroenterol Hepatol 2020; 18: 1609-1617. Full Text: Rapid Response to Treatment of Autoimmune Hepatitis Associated With Remission at 6 and 12 Months

Methods: This was a retrospective cohort study, collecting data from 2 independent cohorts of adults (each with n=370) with AIH from 12 centers in 7 countries in Europe.

Key findings:

  • The authors found that a significant decrease in level of AST after 8 weeks of treatment was significantly associated with normalization of transaminase levels at 26 and 52 weeks (P < .001)
  • In both cohorts, rapid responders (≥80% decrease in level of AST after 8 weeks) were more likely to achieve normalization of transaminases at 26 and 52 weeks when compared to non-rapid responders
  • Rapid responders in the discovery cohort had lower risk of liver-related death or transplantation (adjusted hazard ratio 0.18)
  • Slow responders (without normalization of transaminases after 1 year) had the highest risk of liver transplantation or liver-related death.

My take: It is no surprise that patients who respond rapidly to treatment would fare better.  This study establishes a target of >80% improvement in AST at 8 weeks.

Related blog posts:

New Data on Bisacodyl for Pediatric Constipation

A recent retrospective study (S Bonilla et al. JPGN 2020; 71: 288-291. Long-term Use of Bisacodyl in Pediatric Functional Constipation Refractory to Conventional Therapy) provides some reassuring information about the use of bisacodyl for pediatric constipation, n=164.  Bisacodyl’s mechanism of action is due to its ability to cause mucosal secretion and a prokinetic effect on colonic mucosa.

Key findings:

  • Bisacodyl median dose was 5 mg/day, median duration of treatment was 14 months
  • Median number of BM/wk doubled after initiation of bisacodyl from 2 to 4 bm/w (P < 0.001)
  • Approximately 57% of patients had successful response. At long-term follow-up 55% of patients were successfully weaned off bisacodyl (median time of 18 months)
  • Side effects: 8 patients reported abdominal pain, 4 had diarrhea, and 1 had nausea
  • Limitations: open-label study, retrospective study, lack of a placebo-control

My take (from authors): “We observed no long-term complications with its long-term use in children.” Prospective studies are needed.

Related blog posts: