Nutrition Week (Day 4) Trophic Hormone for Pediatric Short Bowel Syndrome

A recent study (BA Carter et al. J Pediatr 2017; 181: 102-11) provides some preliminary data on the use of glucagon-like peptide-2 (GLP-2) (Teduglutide) for pediatric short bowel syndrome (SBS).

This was a 12-week, open-label study in patients aged 1-17 years with intestinal failure (IF) associated with SBS. Prior to the study, patients had shown little to minimal advance in enteral nutrition for at least 3 months. Three doses of GLP-2 (0.0125 mg/kg/d, 0.025 mg/kg/day, and 0.05 mg/kg/day).

Key findings:

  • All treated patients (37) experienced mild or moderate adverse effects, including vomiting, pyrexia, catheter-related complications, and upper respiratory tract infections. No serious adverse events were identified. In the 5 patients who received standard care, adverse effects were recorded as well, including upper respiratory tract infections in 2 (40%) which was similar to the other groups.
  • By week 12, parenteral nutrition (PN) volume and calories were reduced in the higher dosed groups.  In the 0.025 mg/kg/day group, PN volume dropped by 41% and calories by 45%.  In the 0.05 mg/kg/day group, PN volume dropped by 25% and calories by 52%. Virtually no change in these parameters occurred in the lowest dose (0.0125 mg/kg/day) with no change in volume and 6% drop in calories.
  • Enteral feeding volume occurred in all groups: 22%, 32%, and 40% in the groups and was directly related to the GLP-2 dosing.
  • Citrulline levels (a biomarker of enteral autonomy) were monitored “but the results were clouded by wide variability of baseline values.”  In adult studies, citrulline levels increased significantly.

My take: This open-label study has many limitations; further studies are planned (ClinicalTrials.gov, NCT02682381). Nevertheless, this study indicates that GLP-2 holds promise as a therapy for SBS/IF.

Another slide in a recent lecture on PNALD (slide derived from Conrad Cole lecture in Octobler 2015 -available at Pediatric Nutritionist Blog, slide 49):

screenshot-109

Related blog posts:

Predicting Short Bowel Syndrome Enteral Autonomy: Small Bowel Diameter

In a small retrospective single-center study (GC Ives et al. J Pediatr 2016; 178: 275-7), the authors found that small bowel diameter, as measured on calibrated luminal contrast studies was predictive of enteral autonomy.

Measurements of >35 mm of bowel lumen was considered dilated.  29 patients had adequate imaging for the study.  Necrotizing enterocolitis was the most common etiology of short bowel syndrome in this study.  16 (55%) of the intestinal failure group achieved enteral autonomy in an average of 1.3 years.  11 (38%) of patients underwent an intestinal lengthening procedure.

Key findings:

  • Small bowel diameter correlated negatively with residual small bowel length
  • Larger small bowel diameter predicted failure to achieve enteral autonomy.  In fact, only one patient in this study with a dilated small bowel diameter achieved enteral autonomy.

My take: Bigger (diameter) is not better.

Related blog posts:

Lighthouse in Rockland

Lighthouse in Rockland

World Congress 2016 Postgraduate Course

I’ve attached (with permission) the syllabus from the World Congress 2016 Postgraduate Course: 2016-world-congress-postgraduate-course-syllabus

screen-shot-2016-10-14-at-11-45-54-am

screen-shot-2016-10-14-at-11-46-04-am

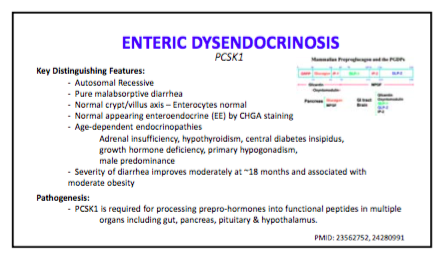
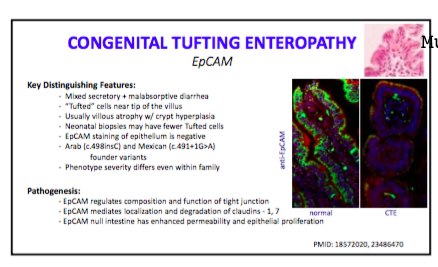
One lecture that I will highlight with a few slides is from Dr. Martin Martin (pg 53-62) which emphasizes a new model for evaluating neonatal intestinal failure/congenital diarrhea by using whole exome sequencing –see slides below.

Other pointers:

  • Pg 82.  Breastmilk associated with shorter duration of TPN dependence in short bowel syndrome
  • Pg 137. Look for vasculopathy (MRI/MRA) and renal disease in Alagille syndrome
  • Pg 152. Lactated ringer’s likely better in acute pancreatitis than normal saline.
  • Pg 171. If constipation at less than 1 year is untreated, >60% have issues with constipation at age 3.

screen-shot-2016-10-14-at-11-37-07-am screen-shot-2016-10-14-at-11-37-00-am screen-shot-2016-10-14-at-11-36-44-am screen-shot-2016-10-14-at-11-36-34-am screen-shot-2016-10-14-at-11-35-40-am


Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Eosinophilic Disease in Children with Intestinal Failure

Last week, this blog posted an abstract regarding the use of “real foods” for short gut kids.  This post looks into whether certain foods may provoke an allergic response.

A large (n=105) single center retrospective study (C Duggan et al. JPGN 2016; 63: 336-39) examined the histology from 208 endoscopic procedures to determine the frequency of eosinophilic disease in children with intestinal failure.

Key findings:

  • 37% of patients had evidence of eosinophilic inflammation in at least one section of the GI tract.
  • Most common sites for eosinophilic disease: colon/rectosigmoid 18/68 (26%), esophagus 17/83 (20%), ileum 9/54 (17%) and duodenum 4/83 (5%)
  • Both peripheral eosinophilia and hematochezia correlated with eosinophilic colitis
  • The authors state that “a strict elemental diet for 3 months before endoscopy was not associated with a decreased frequency of eosinophilic inflammation.”

While a strict elemental diet was not shown to be effective in this study, the limitations of the study design (eg. retrospective, small number on amino acid diet) preclude a definitive answer about the utility of these diets.  Other confounders, including ongoing parenteral nutrition support, also ‘muddy’ the picture.  A prospective study would be able to determine more conclusively how effective elemental diets are at minimizing eosinophilic inflammation and to allow for a more uniform definition of abnormal tissue eosinophilia.

Given the frequency of elemental diets early in life along with prior GI insults, the propensity to eosinophilic disease may have its origins well before this study period.  In healthy children, the LEAP, LEAP-ON, and EAT studies indicated that earlier exposure to allergens reduces the risk of allergic disease.

My take: This study shows a high prevalence of GI eosinophilic inflammation among children with intestinal failure.  Thus, in children with hematochezia and intestinal failure, eosinophilic colitis needs to be considered.

Related blog posts:

Grinnell Glacier, Glacier Natl Park

Glacier Natl Park

Real Foods in Short Gut Kids

Screen Shot 2016-08-17 at 7.31.27 AM

 Reference from Kipp Ellsworth:

Transition to a Tube Feeding Formula With Real Food Ingredients in Pediatric Patients With Intestinal Failure K Samela et al. NCP: Published online before print August 4, 2016, doi:10.1177/0884533616661011

Abstract: Due to concerns related primarily to allergic response and malabsorption, enteral nutrition therapy has traditionally relied on the use of elemental formulas in children with intestinal failure (IF). Blended food diets via a gastrostomy tube have been reported to improve feeding tolerance in pediatric populations receiving long-term enteral nutrition therapy. Complex macronutrients have been shown to stimulate intestinal adaptation in animal models. We report on our experience in children with IF who had an overall improvement in stool output when transitioned from an elemental formula to a tube feeding formula with real food ingredients (TFRF). Data were collected in a retrospective chart review of children with IF, >1 year of age, who were receiving enteral nutrition via continuous infusion, bolus feeding, or both. Indications for the TFRF trial were diarrhea or inconsistent stooling patterns. Ten children with a mean small bowel length of 48.3 cm were trialed on TFRF. Nine of 10 (90%) children tolerated the transition to 100% TFRF, of which 7 of 9 (78%) had their entire colon in continuity. The average age at successful transition was 29.2 months, and the average length of time to transition to 100% TFRF was 67.3 days. TFRF is well tolerated in children >1 year of age with IF; it also improves their stooling patterns. A commercially available TFRF is a cost-effective and nutritionally adequate means of providing nutrition to this patient population.


Nutrition Support for Intestinal Failure

A recent blog post by Kipp Ellsworth (The Pediatric Nutritionist) highlights a recent lecture by Conrad Cole that provides several useful points.  The post includes a link (embedded talk) to 76 slides. Here are a few:

  • Iodine deficiency: Dr. Cole “typically orders a TSH level every six months, also ordering a spot urine iodine if a significant TSH uptrend emerges.”
  • Lipids: “Dr. Cole reviewed evidence revealing the restriction of soy-based lipids to 0.5 gm/kg/day as nearly efficacious as the use of fish-oil infusion (Omegaven) in preventing PNALD.” Daily use of 0.5-1 gm/kg/day is less error-prone than using lipids 3-4 times/week.
  • Formula: “breastmilk constitutes the touchstone of enteral nutrition choices for the intestinal rehab patient, conferring a host of benefits beyond those associated with formula alone… the medium-chain triglyceride component of many oligomeric and monomeric formulas constitutes a therapeutically valuable source of nutrition, increasing the proportion of calories absorbed.”
  • Formula for toddlers: “Dr. Cole continues transitioning his patients to oligomeric and monomeric formulas such as Elecare Junior, Pediasure Peptide, and Peptamen Junior upon reaching toddlerhood.”
  • Fiber: “Dr. Cole recommended the use of a sc-FOS product such as NutraFloraas optimal for the short bowel syndrome population.  Dr. Cole initially doses soluble fiber at 1 gm/100 mL of formula and advances as tolerated to a maximum of 2 gm/100 mL formula.  He typically does not use supplemental fiber to control ostomy output in patients without a colon in continuity”
  • Enteral fish oil: “Dr. Cole remains unconvinced of the therapeutic value of enteral fish oil supplementation pending further research studies on the subject.”

Funding for his talk was provided by Abbott Nutrition.

Related blog posts:


Identifying Anastomotic Ulcers with Capsule Endoscopy

A retrospective review (LM Bass et al. JPGN 2015; 61: 215-9) showed that capsule endoscopy (CE) can be helpful in identifying anastomotic ulcers among patients with short bowel syndrome and chronic GI blood loss.

This study of 4 patients (& 6 CE procedures) indicated that two of these patients underwent surgery after identifying anastomotic ulcers.  The other common treatment was antibiotics. In the suggested evaluation CE was used after upper/lower endoscopy. The recommended role for patency capsule/small bowel imaging is not clearly spelled out, but should be carefully considered due to the risk of strictures.

“The decision to perform CE is made in conjunction with medical and surgical teams so that, although every effort is made to avoid a situation that may result in a retained capsule, both parents and care teams are prepared.”

Related blog posts:

Enteral Autonomy in Pediatric Intestinal Failure

A recent study (FA Khan et al. J Pediatr 2015; 167: 29-34 -thanks to Mike Hart for forwarding this reference) provides data from a multicenter retrospective cohort of 272 infants.  These infants had of IF were defined by requiring >60 days of PN; they were enrolled in the Pediatric Intestinal Failure Consortium.  The median followup was 33.5 months.  The most common etiologies of IF were necrotizing enterocolitis (NEC), gastroschisis, small bowel atresia, and volvulus. Key findings:

  • 43% achieved enteral autonomy (EA), defined as freedom from PN for >3 months, 13% remained dependent on PN, and 43% had died, undergone intestinal transplantation, or both.
  • Infants with EA were more likely to have had NEC, preserved ileocecal valve, longer preserved small bowel length, and care at a non-transplant center (with retrospective study, high likelihood of a selection bias).

The associated editorial by Valeria Cohran (pages 6-8) notes that pediatric intestinal transplants peaked in frequency in 2007, but in 2014 there only 56 performed.  She also notes that the care of these children with short bowel syndrome in the first year of life is approximately $500,000 ± $250,000!  The improved survival is attributed to minimizing cholestasis with new lipid strategies, minimizing blood stream infections with better care and ethanol locks, and the use of autologous bowel reconstruction surgery. Bottomline: This study and several others show that meticulous care and advances in the treatment of intestinal failure improve the likelihood of survival without the need for intestinal transplantation. FULL CITATION: Khan FA et al. Predictors of enteral autonomy in children with intestinal failure: A multicenter cohort study. J Pediatr 2015 Jul; 167:29-34. [Free full-text J Pediatr article PDF | PubMed® abstract] Related blog posts:

These windows were huge -Grand Tetons in background

These windows were huge -Grand Tetons in background


Stick with the (intestinal) rehab program?

More data on the progress of treatment of short bowel syndrome (SBS) programs:

  • Avitzur J, et al. JPGN 2015; 61: 18-23

In this study, the researchers from Toronto and the Group for Improvement of Intestinal Function and Treatment (GIFT) retrospectively examine 84 patients over 3 time periods: 1999-2002, 2003-2005, and 2006-2009.

Key points:

  • Across those time periods, the authors find fewer SBS patients that needed to be listed for transplantation despite similar baseline characteristics.  In addition, many more patients in the late period were removed from the transplant waiting list due to clinical improvement.
  • Another important finding was a drop in mortality (15% vs >60%) and a shift from previous causes like liver failure and sepsis to death from other comorbid conditions.
  • “Since 2009, we have performed only 1 IT [intestinal transplant].”  They note this is a worldwide trend with ~50% reduction in pediatric IT since 2008.
  • Even with ultrashort bowel (small bowel length <30 cm), there are reports that “50% of these patients achieved PN independence within 2 years.”  As such, this is a declining indication for IT listing. In this study, ultrashort bowel was the reason for listing in 11% in the last period compared 21% in the first time period.

Why is this happening?

The authors credit the intestinal rehab program (IRP) for this impact along with specific management changes including new lipid emulsions/lipid minimization to reduce IFALD, use of ethanol locks to reduce bloodstream infections, and bowel reconstructive procedures (e.g. STEP).

Briefly noted: Merras-Salmio L, Pakarinen MP. JPGN 2015; 61: 24-9. This second retrospective study (n=48) from Finland reinforces the view of improvements in cholestasis  and prognosis from 1988-2014.  Similar strategies, as noted above, were implemented in SBS management protocols.

Bottomline: The outlook has improved for SBS.  While this is good news, at the same time, there will be less pediatric gastroenterologists with extensive intestinal transplantation experience.

In Wyoming often there are stretches of nearly deserted highways

In Wyoming often there are stretches of nearly deserted highways

Related blog posts:

Iron Deficiency Common in Patients Requiring Long-Term Parenteral Nutrition

A recent study (JPEN J Parenter Enteral Nutr May 13, 2015 0148607115587329) demonstates a high rate of iron deficiency anemia in patients requiring home parenteral nutrition (Thanks to Kipp Ellsworth for reference).

From Abstract:

Methods: Medical records of patients receiving HPN at the Mayo Clinic from 1977 to 2010 were reviewed. Diagnoses, time to IDA development, and hemoglobin, ferritin, and mean corpuscular volume (MCV) values were extracted. Response of iron indices to intravenous iron replacement was investigated.

Results: Of 185 patients (122 women), 60 (32.4%) were iron deficient…Of 93 patients who had sufficient iron storage, 37 had IDA development after a mean of 27.2 months (range, 2–149 months) of therapy. Iron was replaced by adding maintenance iron dextran to PN or by therapeutic iron infusion. Patients with both replacement methods had significant improvement in iron status. With intravenous iron replacement, mean ferritin increased from 10.9 to 107.6 mcg/L (P < .0001); mean hemoglobin increased from 11.0 to 12.5 g/dL (P = .0001); and mean MCV increased from 84.5 to 89.0 fL (P = .007).

Conclusions: Patients receiving HPN are susceptible to IDA. Iron supplementation should be addressed for patients who rely on PN.

Zoo Atlanta

Zoo Atlanta