I am a pediatric gastroenterologist at GI Care for Kids (previously called CCDHC) in Atlanta, Georgia. The goal of my blog is to share some of my reading in my field more broadly. In addition, I wanted to provide my voice to a wide range of topics that often have inaccurate or incomplete information.
Before starting this blog in 2011, I would tear out articles from journals and/or keep notes in a palm pilot. This blog helps provide an updated source of information that is easy to access and search, along with links to useful multimedia sources.
I was born and raised in Chattanooga. After graduating from the University of Virginia, I attended Baylor College of Medicine. I completed residency and fellowship training at the University of Cincinnati at the Children’s Hospital Medical Center. I received funding from the National Institutes of Health for molecular biology research of the gastrointestinal tract.
During my fellowship, I had the opportunity to work with some of the most amazing pediatric gastroenterologists and mentors. Some of these individuals included Mitchell Cohen, William Balistreri, James Heubi, Jorge Bezerra, Colin Rudolph, John Bucuvalas, and Michael Farrell. I am grateful for their teaching and their friendship. During my training with their help, I received a nationwide award for the best research by a GI fellow.
I have authored numerous publications/presentations including original research, case reports, review articles, and textbook chapters on various pediatric gastrointestinal problems. In addition, I have been recognized by Atlanta Magazine as a "Top Doctor" in my field multiple times.
Currently, I am the vice chair of the section of nutrition for the Georgia Chapter of the American Academy of Pediatrics. In addition, I am an adjunct Associate Clinical Professor of Pediatrics at Emory University School of Medicine. Other society memberships have included the North American Society for Pediatric Gastroenterology Hepatology and Nutrition (NASPGHAN), American Academy of Pediatrics, the Food Allergy Network, the American Gastroenterology Association, the American Association for the Study of Liver Diseases, and the Crohn’s and Colitis Foundation.
As part of a national pediatric GI organization called NASPGHAN (and its affiliated website GIKids), I have helped develop educational materials on a wide-range of gastrointestinal and liver diseases which are used across the country. Also, I have been an invited speaker for national campaigns to improve the evaluation and treatment of gastroesophageal reflux disease, celiac disease, eosinophilic esophagitis, hepatitis C, and inflammatory bowel disease (IBD). Some information on these topics has been posted at my work website, www.gicareforkids.com, which has links to multiple other useful resources.
I am fortunate to work at GI Care For Kids. Our group has 17 terrific physicians with a wide range of subspecialization, including liver diseases, feeding disorders, eosinophilic diseases, inflammatory bowel disease, cystic fibrosis, DiGeorge/22q, celiac disease, and motility disorders. Many of our physicians are recognized nationally for their achievements. Our group of physicians have worked closely together for many years. None of the physicians in our group have ever left to join other groups. I have also worked with the same nurse (Bernadette) since I moved to Atlanta in 1997.
For many families, more practical matters about our office include the following:
– 14 office/satellite locations
– physicians who speak Spanish
– cutting edge research
– on-site nutritionists
– on-site psychology support for abdominal pain and feeding disorders
– participation in ImproveCareNow to better the outcomes for children with inflammatory bowel disease
– office endoscopy suite (lower costs and easier scheduling)
– office infusion center (lower costs and easier for families)
– easy access to nursing advice (each physician has at least one nurse)
I am married and have two sons (both adults). I like to read, walk/hike, bike, swim, and play tennis with my free time.
I do not have any financial relationships with pharmaceutical companies or other financial relationships to disclose. I have helped enroll patients in industry-sponsored research studies.
“Rejecting the advice of its scientific advisers, the federal government has released new dietary recommendations that sound a familiar nutritional refrain, advising Americans to “make every bite count” but dismissing experts’ specific recommendations to set new low targets for consumption of sugar and alcoholic beverages...
The dietary guidelines have an impact on Americans’ eating habits, influencing food stamp policies and school lunch menus and indirectly affecting how food manufacturers formulate their products…
The new guidelines do say for the first time that children under 2 should avoid consuming any added sugars, which are found in many cereals and beverages.”
I have a deep admiration and fondness for Jorge. When I first did a gastroenterology rotation during my pediatric residency, he was the first person who handed me an endoscope and showed me how to handle it. During my training as a resident and as a fellow (1991-1997), I had the opportunity to get to know Jorge; for some of that time, he was completing his training as he started his GI fellowship in 1990.
I really enjoyed reading this introduction to learn a lot more about Jorge, because I don’t remember Jorge speaking about himself. Of course, he has been part of some very important advances in pediatric hepatology including the very useful MMP-7 assay, the ‘Jaundice chip’ and the START study.
The article delves into some personal attributes including the description of Jorge being ‘the Pele of pediatric hepatology’ (per Dr. Ronald Sokol). It also describes his family and some characteristics. “He has inspired us with his calm demeanor, decency, humor, positivity, and kindness.”
It is a personal thrill for me to read about one of my heroes in our field.
I want to thank all of you who take an interest in my blog, particularly those who give suggestions, references, and encouragement. The following posts were the most popular from the past year.
Full Text: All About COVID-19 Vaccines (Thanks to Seth Marcus for the reference). This article explains how the vaccines work, who essential workers are, and the effectiveness of the vaccines.
Methods: Single course of oral encapsulated fecal microbiome from 4 healthy lean donors or saline placebo.
Key findings:
In this randomized, double-masked, placebo-controlled trial of 87 adolescents with obesity, FMT alone did not lead to weight loss at 6 weeks.
There were no observed effects on insulin sensitivity, liver function, lipid profile, inflammatory markers, blood pressure, total body fat percentage, gut health, and health-related quality of life
In post-hoc exploratory analyses among participants with metabolic syndrome at baseline, FMT led to greater resolution of this condition (18 to 4) compared with placebo (13 to 10) by 26 weeks (adjusted odds ratio, 0.06; 95% CI, 0.01-0.45; P = .007)
This study looked at 105 patients receiving combination therapy; the a median duration of combination therapy was 2.1 years, with infliximab and either methotrexate (53) or azathioprine (52). 89 patients had Crohn’s disease.
Key findings:
11 (10.5%) patients experienced a clinical relapse over a median duration of follow-up of 12.0 months after stopping the immunomodulator.
In the patients who did not relapse, the median IFX trough level at IM discontinuation was 6.2; the IFX trough level was 3.8 μg/mL in those who relapsed.
In their discussion, the authors urge caution in discontinuation of immunomodulators in those with clinically-severe Crohn’s disease and those with low infliximab levels.
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition
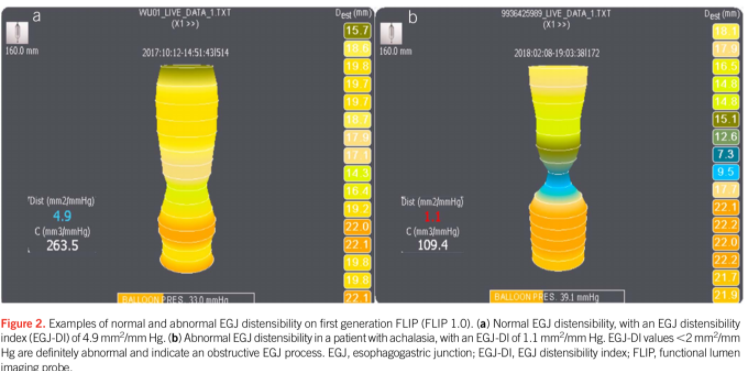
A recent review article (E Sararino et al. Am J Gastroenterol 2020; 115: 1786-06. Use of the Functional Lumen Imaging Probe in Clinical Esophagology) is a terrific article for understanding Functional Lumen Imaging Probe (FLIP) techonology and uses. Thanks to Ben Gold for this reference.
The FLIP “measures luminal cross sectional area (CSA) and pressure in the esophagus using impedance planimetry and serves as an adjunct to existing esophageal investigative tests. A distensible balloon encasing a catheter with multiple pairs of impedance electrodes is used, and the balloon is distended with fluid of known conductivity and volume.”
FLIP can be done at time of endoscopy.
Distensibility index (DI). This is the ratio of EGJ cross sectional area to intraballoon pressure is generally considered the most useful FLIP metric. Normal DI values in adults range from 3.1 to 9.0 m3/mm Hg. Lower values indicated reduced EGJ opening.
FLIP can complement the diagnosis of achalasia when manometry and barium studies are inconclusive or negative in patients with typical symptoms.
FLIP can be used to assess fibrostenotic remodeling of the esophagus in eosinophilic esophagitis.
Lumen diameter measured using FLIP in complex strictures can potentially guide management.
This review has several helpful figures to illustrate the type of visual data available. It also provides a standard protocol for using FLIP. The current limitations for FLIP include the lack of real-time software analysis of the data which hinders reporting, and limited data supporting use.
The Nutrition4Kids website (developed by my partner Stan Cohen) has a lot of useful information for families. Here is a link to a recent addition: 5 Signs Your Child Needs a Feeding Tube
An excerpt:
Reasons for needing a feeding tube…
Medical necessity, where the child can’t meet their calorie needs due to a medical condition (like, say, a heart defect, neurologic and neuromuscular disorders, or a digestive disorder.)
Failure to thrive, often because of food aversions…
Trouble learning to suck, swallow, and breathe
Here are some of the most common signs your child may benefit from a feeding tube.
Sign #1: Your Physician Brings It Up
Sign #2: You’ve Noticed Development Delays
Sign #3: They’re Malnourished or Chronically Dehydrated
Sign #4: You’ve Tried Other Options Without Success
Sign #5: You’re Feeling Helpless as the Caregiver
If your child does end up needing enteral nutrition, understand that it doesn’t always mean it’s a forever situation.
www.feedingtubeawareness.com This site contains a terrific PDF download which explains enteral tubes in an easy to understand style along with good graphics. “What You Need to Know Now, A Parent’s Introduction to Tube Feeding is the guidebook that every parent wished they had when they were first introduced to feeding tubes.”