High Relapse Rates with Anti-TNF Withdrawal Even with Endoscopic Remission

R Mahmoud et al. Clin Gastroenterol Hepatol 2023; 21: 750-760. Open Access! Complete Endoscopic Healing Is Associated With Lower Relapse Risk After Anti-TNF Withdrawal in Inflammatory Bowel Disease

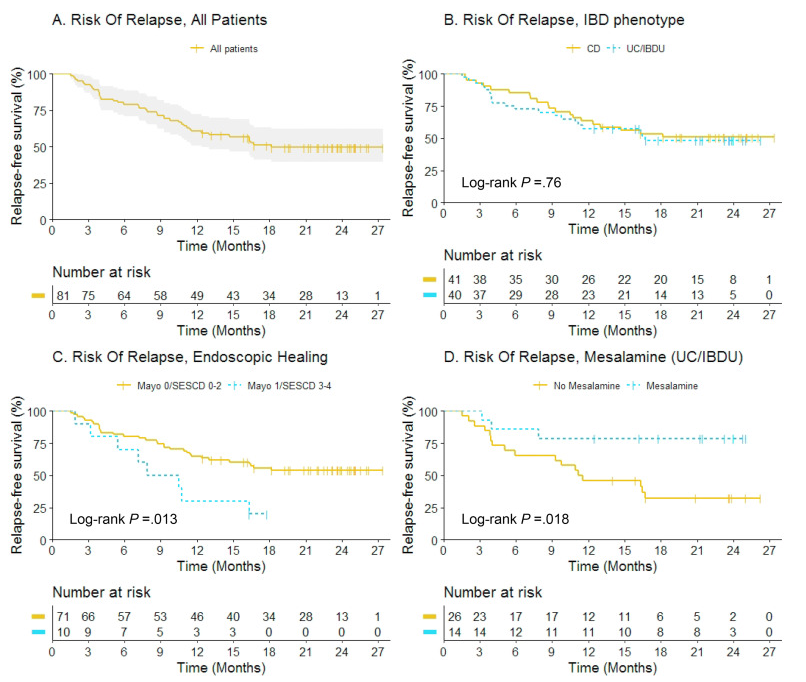
This was a prospective observational study (n=81). In order to participate, patients (all adults) had to be in confirmed baseline steroid-free clinical remission (for at least 6 months) and endoscopic healing;  endoscopic healing was defined as endoscopic Mayo score <2 or Simple Endoscopic Score for CD (SES-CD) <5 without large ulcers. Endoscopic healing was subclassified as complete endoscopic healing (Mayo 0/SES-CD 0–2) versus partial endoscopic healing (Mayo 1/SES-CD 3–4).

Key findings:

  • At 12 months, 70% (7 of 10) versus 35% (25 of 71) of patients with partial versus complete endoscopic healing relapsed, respectively (adjusted hazard rate [aHR], 3.28; 95% confidence interval [CI], 1.43–7.50)
  • Mesalamine use was associated with fewer relapses in UC/IBDU patients (aHR, 0.08; 95% CI, 0.01–0.67)
  • Thirty patients restarted anti-TNF, and clinical remission was regained in 73% at 3 months.

The authors highlight the lower relapse rate between those with complete endoscopic healing and those with partial healing. They acknowledge that those eligible for anti-TNF de-escalation are highly selected (~7% in a prior study) and “few patients with an unfavorable IBD phenotype, such as stricturing or penetrating CD, anti-TNF for perianal fistulizing CD, young age at diagnosis, or prior biological failure, were included in this study. Therefore, our findings may not be generalizable to patients with a more severe IBD phenotype.

My take: Even in those with complete endoscopic healing, there is a high rate of relapse. In addition, stopping anti-TNF therapy likely increases risk of not responding to anti-TNF therapy when it is restarted. This study does show that transitioning from anti-TNF therapy to mesalamine therapy in those with ulcerative colitis (or IBDU) could be a reasonable consideration.
Related blog posts:


Targeting Calprotectin Levels Below 80 for Ulcerative Colitis Plus Obesity Medication Pushback

K Kawashima et al. Inflamm Bowel Dis 2023; 29: 359-366. Low Fecal Calprotectin Predicts Histological Healing in Patients with Ulcerative Colitis with Endoscopic Remission and Leads to Prolonged Clinical Remission

In this prospective study (n=76), patients with UC in clinical and endoscopic remission, defined as a partial Mayo score (PMS) ≤ 2 points and a Mayo endoscopic subscore 0–1, were enrolled and followed for 2 years or until relapse, defined as a PMS > 2 or medication escalation.

Key findings:

  • The median fecal calprotectin (FC) value in patients with histologic healing (HH) (n = 40) was 56.2 µg/g, significantly lower than that in those with histological activity (118.1 µg/g; P < .01)
  • The optimal FC cutoff value to predict prolonged CR was 84.6 µg/g (72% sensitivity; 85% specificity; P < .01)

My take: Even among ulcerative colitis in clinical & endoscopic remission, fecal calprotectin levels are an objective way to identify histologic healing and to stratifying likelihood of prolonged remission.

Related blog posts:

Sendero Esperanza Trail, Saguaro National Park, Tucson AZ

It is good to see some skepticism regarding the new obesity medications. 4/2/23 USA Today: Why experts worry the ‘magic’ in new weight loss medications carries a dark side

Cold vs Hot Polypectomy for Small Polyps

L-C Chang et al. Ann Intern Med. [Epub 21 February 2023]. doi:10.7326/M22-2189. Cold Versus Hot Snare Polypectomy for Small Colorectal Polyps

In this multicenter randomized open-label, single-blind trial of patients (n=4270) 40 years or older (mean age 62 years) with polyps of 4 to 10 mm, cold snare polypectomy (CSP) was compared with hot snare polypectomy (HSP).

Key findings:

  • Eight patients (0.4%) in the CSP group and 31 (1.5%) in the HSP group had delayed bleeding (w/in 14 days) (risk difference, −1.1% [95% CI, −1.7% to −0.5%]).
  • Severe delayed bleeding (drop in Hgb of 2 g/dL) was also lower in the CSP group (1 [0.05%] vs. 8 [0.4%] events; risk difference, −0.3% [CI, −0.6% to −0.05%])
  • The CSP group had fewer emergency service visits than the HSP group (4 [0.2%] vs. 13 [0.6%] visits
  • Polyp type (in Table 2): 70% were adenomas, 5% were sessile polyps, and 23% were nonneoplastic which includes hyperplastic polyps, inflammatory polyps, and nonsignificant lesions. ~56% had a “polypoid morphology” and ~ 44% had a “nonpolypoid morphology.”
  • “Besides an improved safety profile, another advantage of CSP is its high efficiency. This study’s results showed that the time required for polypectomy is reduced by 26.9% with CSP (difference in mean, -44.0 seconds)”

Why is CSP safer?

“The shallower resection depth in CSP is one of the factors contributing to the lower bleeding risk. Besides the tearing force, electrocautery also applies more energy to the soft tissue… (28). Profound submucosal destruction may occur in 60% of cases, and the muscularis propria may be damaged in 20% of patients receiving HSP; however, all cold resections are limited to the shallow submucosa. Because larger vessels are usually located in the deeper submucosa, the shallow resection depth of CSP causes less arterial injury, thereby reducing the risk for delayed bleeding (29).”

My take: It would be helpful to replicate these findings in children mainly due to differences in polyp types that are found. Nevertheless, this study suggests that it is likely more risky to use cautery for small polyps (“including persons using antiplatelet agents or anticoagulants”).

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

The Eosinophilic Esophagitis Diagnostic Cup is Half Empty with the Esophageal Sponge

JA Alexander et al. Clin Gastroenterol Hepatol 2023; 21: 299-306. Open Access! Use of the Esophageal Sponge in Directing Food Reintroduction in Eosinophilic Esophagitis

Methods: In this prospective non-blinded trial, 22 responders to 6-food elimination diets underwent sequential food reintroduction guided by esophageal sponge cytology

Key findings:

  • At the post food reintroduction evaluation, sponge cytology and biopsy histology were in agreement in 59% (13/22) of cases using a cutoff of <15 eos/hpf and 68% (15/22) of cases using a cutoff of <6 eos/hpf. With the cutoff of <15 eos/hpf, the median absolute difference was 38 eos/hpf.
  • Interestingly, the authors noted a high rate (23%) of dietary responders who had dietary reintroduction without a dietary trigger being identified; this is possibly related in part to lower sponge sensitivity, and possibly due to a short food reintroduction period of 2 weeks prior to testing.

The authors in their discussion note that it is unclear whether the values from the sponge or from the biopsy is more reliable.

My take: This is a disappointment for those of us waiting for a reliable non-invasive measure of EoE activity. Those with abnormal sponge results are fairly likely to have abnormal endoscopy; however, many of those with normal values with sponge testing are likely to have active EoE.

Related blog posts:

Briefly Noted: Kiwi for IBS-C

R Gearry et al. AJG 2022. DOI: 10.14309/ajg.0000000000002124.Open Access! Consumption of 2 Green Kiwifruits Daily Improves Constipation and Abdominal Comfort—Results of an International Multicenter Randomized Controlled Trial

Participants included healthy controls (n = 63), patients with functional constipation (FC, n = 60), and patients with constipation-predominant irritable bowel syndrome (IBS-C, n = 61). Mean age 35 years.

Key findings: Consumption of green kiwifruit was associated with a clinically relevant increase of ≥ 1.5 CSBM (complete spontaneous bowel movement) per week (Functional constipation; 1.53, P < 0.0001, IBS-C; 1.73, P = 0.0003) and significantly improved measures of GI comfort (GI symptom rating scale total score) in constipated participants (FC, P < 0.0001; IBS-C, P < 0.0001)

Related blog post: Small Study: Kiwi For Constipation

Tofacitinib Outperformed Vedolizumab in Anti-TNF-experienced Ulcerative Colitis

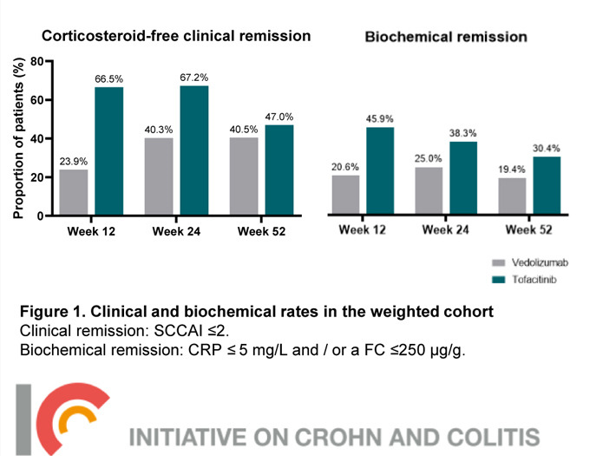
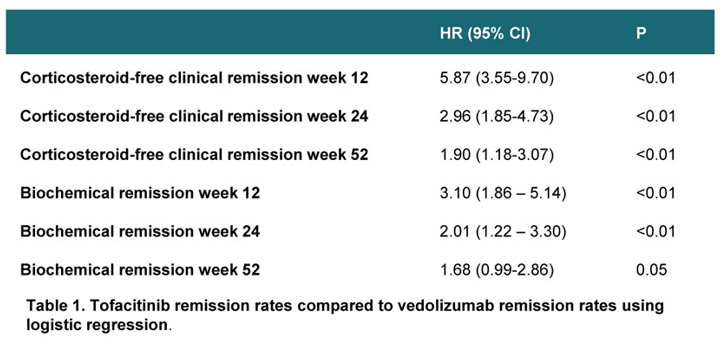
T Straamijer et al. Clin Gastroenterol Hepatol 2023; 21: 182-191. Open Access! Superior Effectiveness of Tofacitinib Compared to Vedolizumab in Anti-TNF-experienced Ulcerative Colitis Patients: A Nationwide Dutch Registry Study

Methods: Adults with ulcerative colitis (UC) previously who failed anti-TNF treatment and initiated vedolizumab (n=83) or tofacitinib (n=65) treatment were identified in the Initiative on Crohn and Colitis Registry in the Netherlands.

Key findings (Vedolizumab is in gray):

  • There was no difference in infection rate or severe adverse events.

My take: Coupled with more recent reassuring safety data on JAK inhibitors, this study makes a strong case for positioning Tofacitinib (or other JAK inhibitor) earlier in patients with moderate-to-severe ulcerative colitis. Given that vedolizumab outperformed adalimumab in a head-to-head study, this indicates that tofacitinib is a very effective therapy.

Related article: B Chen et al. Gastroenterology 2022; 163: 1555-1568. Efficacy and Safety of Ivarmacitinib in Patients With Moderate-to-Severe, Active, Ulcerative Colitis: A Phase II Study This phase 2 study with 146 patients examined the effectiveness of the selective JAK inhibitor Ivarmacitinib found a week 8 clinical response in 46% of those receiving 8 mg per day. The week 8 clinical remission rate was 22%-24% in the treatment groups compared to 5% in the placebo group.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Safety Net for Celiac Disease?

JA Murray, JA Syage et al.Gastroenterol 2022; 163: 1510-1521. Open access! Latiglutenase Protects the Mucosa and Attenuates Symptom Severity in Patients With Celiac Disease Exposed to a Gluten Challenge

Background: Latiglutenase (IMGX003) is an investigational dual-enzyme drug candidate that acts to degrade gluten in vivo when consumed with a meal. The authors note that “despite strict adherence to a GFD, about half of CD patients show evidence of persistent small intestinal mucosal injury (Marsh grades II–III);’ thus, there is a need to improve treatment with other measures in addition to diet.

Methods: 43 patients (IMGX003, n = 21; placebo, n = 22) completed this double blind and placebo controlled study which assessed the efficacy and safety of a 1200-mg dose of IMGX003 in patients with celiac disease (CD) exposed to 2 g of gluten per day for 6 weeks study

Key findings:

  • In IMGX003-treated patients, there was less damage to mucosa. The mean change in the ratio of villus height to crypt depth (primary endpoint) for IMGX003 vs placebo was –0.04 vs –0.35 (P = .057). The mean change in the density of intraepithelial lymphocytes (secondary endpoint) for IMGX003 vs placebo was 9.8 vs 24.8 cells/mm epithelium (P = .018). 
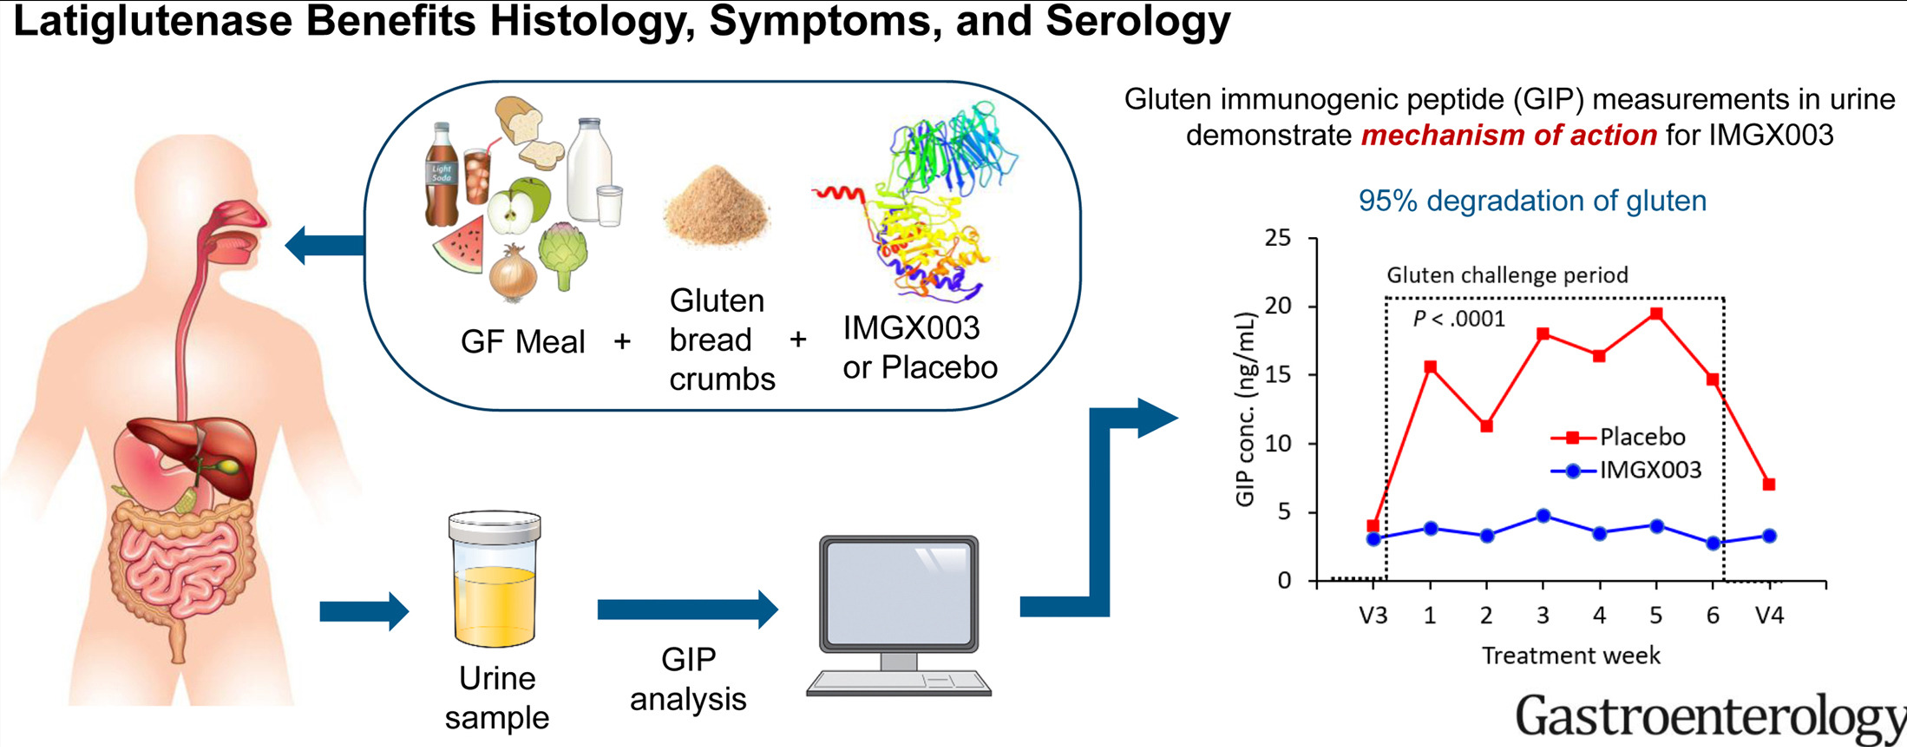
  • Measurements of gluten-immunogenic peptides (GIP) in urine indicated 95% gluten degradation in the stomach by latiglutenase.

The 2 g dose per meal of gluten allowed used in the study, “would likely substantially exceed that accidently occurring while on a GFD, 4 supporting such an approach for management for gluten-triggered symptoms in treated patients.”

Graphical abstract:

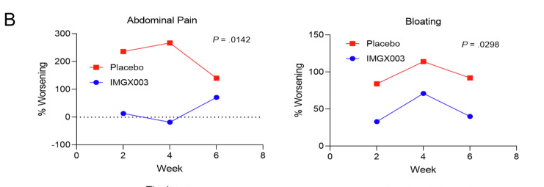
In both the placebo and IMGX003 groups, there was an increases in symptoms, but this was blunted in the treated group–Figure 2:

My take: This study shows the potential for latiglutenase to act as a ‘safety net’ to protect from CD from accidental gluten exposure. The findings reinforce the idea that this agent is not likely to be effective in the absence of gluten restriction. As an aside, I would be interested in finding out whether patients with presumed non-celiac gluten sensitivity would improve on this therapy.

Related blog posts:

2023 ACG Celiac Guidelines for Adult and Children

A Rubio-Tapia et al. Am J Gastroenterol 2023;118:59–76. Open Access! American College of Gastroenterology Guidelines Update: Diagnosis and Management of Celiac Disease Thanks to Ben Gold for this reference.

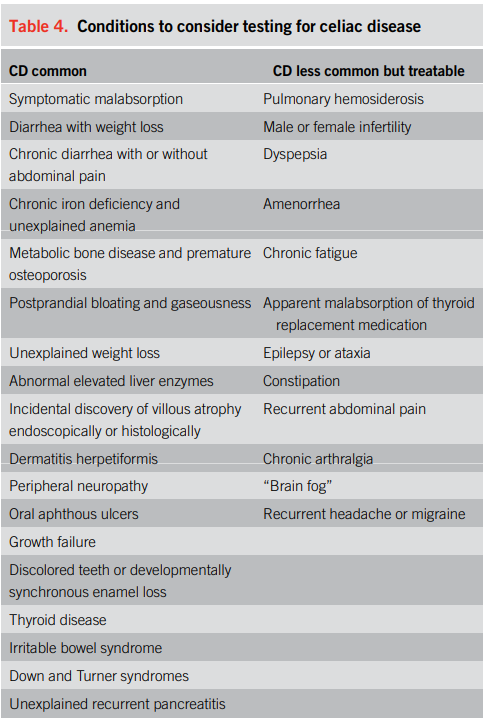
Here are some of the recommendations from updated ACG Celiac Guidelines:

Comments: The authors favor a non-biopsy approach for Celiac diagnosis in children with very elevated serology but not in adults. In adults, they cite a paucity of literature. “One multicenter international study of adults found that a 10-fold elevation of TTG IgA had a positive predictive value of 95% for CD (50). Given the life-long treatment implications of a GFD, this may be unacceptably low.”

The authors suggest assessing for mucosal healing after 2 years of treatment in all patients though they indicate a low quality of evidence for this recommendation. In those undergoing endoscopy, biopsies of the duodenal bulb along with at least 4 post-bulbar biopsies are recommended.

Figure 3 provides an algorithm for non-responsive celiac disease.

Related blog posts:

Picking Apart the SERENE-CD Study & Constipation Vibrating Capsule FDA Approved

Several recent letters to the editor provide some insight into some of the shortcomings of the SERENE-CD study which reported that higher adalimumab induction dosing and proactive therapeutic drug monitoring (TDM) were not associated with improved outcomes.

“The rerandomization design of SERENE CD, which selectively enrolled patients with clinical response at week 12 to the TDM vs CA part of the study, may have resulted in the exclusion of those who would have benefited the most from early adjustment of their anti-tumor necrosis factor (TNF) dose. The rerandomization design and the late adaptation of the proactive strategy at week 12 were 2 significant aspects of the design that may have led to the negative results. On the other hand, PAILOT, which showed beneficial effects of proactive TDM, randomized patients as early as week 4 and assessed the outcome at week 72. This is distinct from the 1-year time frame used in most other studies, including SERENE CD.8 A properly designed, adequately powered clinical trial is needed before we can make a judgement on the use of proactive TDM in patients with inflammatory bowel disease. Until then, the jury remains out.”

“The study design only allowed patients in the TDM group with adalimumab concentrations of ≥5 and ≤10 μg/mL to be escalated to 40 mg every week if their CD activity index was ≥220 or their high-sensitivity C-reactive protein level was ≥10 mg/L.. The goal of proactive TDM is to attain a threshold concentration regardless of disease activity. This design probably led the 2 groups to have similar drug concentrations at week 56…

Second, a rather low targeted drug concentration of 5 μg/mL was used, although previous studies have suggested that higher concentrations are more appropriate.5, 6, 7, 8 A study from Ungar et al5 showed that adalimumab concentrations of 8–12 μg/mL are required to achieve mucosal healing in 80%–90% of patients with IBD, and the prospective PANTS (The Personalised Anti-TNF Therapy in Crohn’s Disease Study) study identified an adalimumab concentration of 12 μg/mL at week 14 associated with remission at both week 14 and week 54.8..

Third, dose escalation for the TDM group could only happen at weeks 14, 28, or 42 (and not earlier and more often). In the PAILOT RCT, proactive TDM based on adalimumab concentration evaluations started as early as week 4 followed by week 8 and every 8 weeks thereafter until the end of the follow-up at week 72.3 Fourth, there was a rather short follow-up of the patients (44 weeks).”

” Even with the assumption of a 30% benefit of proactive TDM and that 20% of patients would have low drug levels in the absence of symptoms, the sample size for 80% power would range from 1228 to 2170. Thus, although SERENE CD1 and other clinical trials3,4 have suggested a lack of benefit of proactive TDM in adults with inflammatory bowel disease, all were likely substantially underpowered to do so.”

My take: While the SERENE-CD results have suggested that a strategy of proactive TDM may not be helpful, there are a lot of reasons to disregard these findings. Achieving a therapeutic level is a fundamental principle and proactive TDM, particularly in pediatrics, is well-supported by other studies.

Related blog posts:

Also noted: