One If By Colon and Two If By Capsule For Clostridioides difficile

Well, this study is not exactly Paul Revere territory; nevertheless, the blog title seemed better than “Eat Shit for C diff.”

BP Vaughn et al. Clin Gastroenterol Hepatol 2023; 21: 1330-1337. Effectiveness and Safety of Colonic and Capsule Fecal Microbiota Transplantation for Recurrent Clostridioides difficile Infection

Methods: Clinical outcomes and adverse events after FMT performed for rCDI at 6 sites (n=269) were captured in a prospective registry. FMT was performed using either freeze-dried/encapsulated or frozen-thawed/liquid.  

The authors note that the cohort with a mix of academic and private practices reflects real-world use of FMT. Since the study products were free of charge, providers and patients selected treatment based on their preference (65% selected oral capsule).

Key findings:

  • At 1 month, rCDI cure rate was 91% for FMT-colonoscopy and 84% for FMT-capsule (no significant difference, p=0.12)
  • At 2 months, rCDI were 83% and 81% for FMT-colonoscopy and FMT-capsule respectively
  • Use of non-CDI antibiotics increased failure rates: 28% at 2 months compared to 10% who did not receive antibiotics
  • One serious adverse event was related to colonoscopy (aspiration pneumonia), otherwise no new safety signals were identified

My take: This study indicates similar effectiveness of FMT-capsule to FMT-colonoscopy. FMT-capsule is easier and avoids risks associated with colonoscopy. But, it does require patients to eat (encapsulated) feces

Related blog posts:

More Pics from Tucson -above picture near Wasson Peak

When Will Intestinal Ultrasound for IBD Become Practical?

M Allocca et al. Gastroenterol 2023; 164: 851-855. Open Access! Intestinal Ultrasound in the Assessment and Management of Inflammatory Bowel Disease: Is It Ready for Standard Practice?

This short article outlines the indications, availability, technical skills, cost-effectiveness and potential value of intestinal ultrasound (IUS). Some key points:

  • Goal: “IUS is used as a first-line investigation and can avoid or delay the need for more invasive and expensive testing (CT, MRI, or colonoscopy). Thus, costs are minimized and patient convenience is optimized”
  • Availability: “IUS is quite widespread in many European countries, but its uptake has been significantly less in other parts of the world, including the United States. Limitations to its use include the absence of standardized and reproducible protocols, lack of local expertise, and the perception that IUS is an operator-dependent tool, feasible only by highly experienced operators. In reality, however,…. studies specifically addressing sonographer variability demonstrate substantial agreement for color Doppler signals and almost perfect agreement for bowel-wall thickness, as the most relevant IUS parameter.”
  • Expertise: Trainees “have to perform at least 300 supervised ultrasound examinations in Italy and 400 in Germany to achieve full competency…It is believed that learners can achieve competency in IUS after approximately 200 supervised examinations, but it is important to acknowledge that a formal learning curve and the criteria for competency assessment have not yet been fully defined”

My take: Despite all the interest in this useful point-of-care tool, for IUS to become more widespread in the U.S. it will need to be incorporated in training programs. The threshold for competency is not achievable with a weekend seminar. It will be interesting to see how this test affects cost, management, and outcomes. Will it reduce or increase other cross sectional imaging testing? Is the information from IUS more useful than a calprotectin (stool biomarker) which could also be a point-of-care test?

Related blog posts:

The Oro Valley/Tucson Loop shared use bike path extends over 130 car free miles throughout unincorporated Pima County, Marana, Oro Valley, and Tucson.

Landmark Study: Oral Biologic for Crohn’s –Upadacitinib

EV Loftus et al. N Engl J Med 2023; 388:1966-1980. Upadacitinib Induction and Maintenance Therapy for Crohn’s Disease

This study is the basis for the FDA’s approval of updacitnib (Rinvoq) for Crohn’s disease in adults: New FDA Rinvoq (upadacitinib) Indication: Oral Treatment For Crohn’s

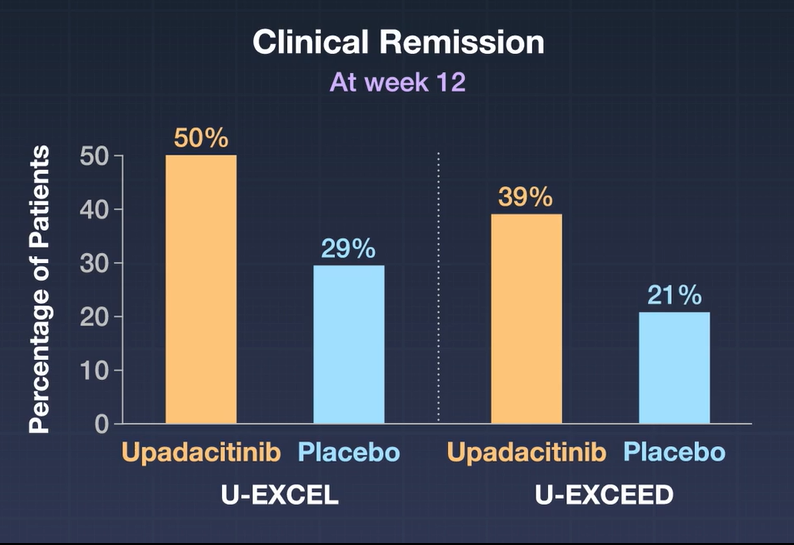
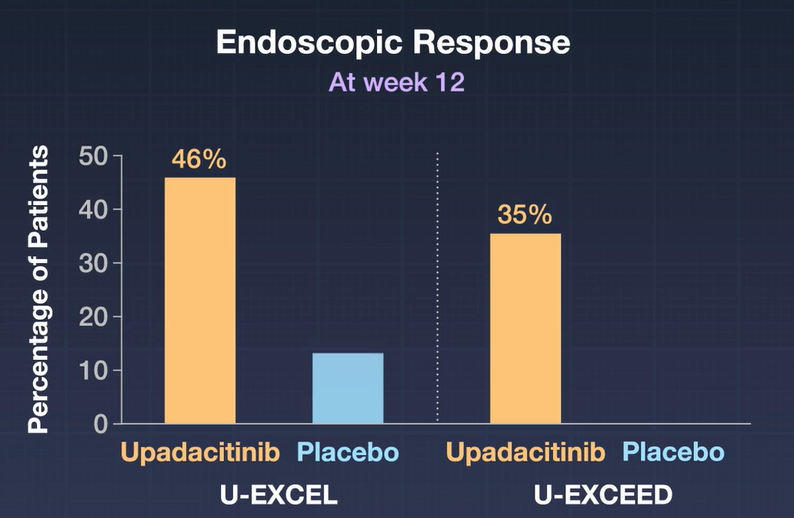
This publication describes the results of two multicenter, double-blind, randomized, placebo-controlled induction trials (n=1021 adults,U-EXCEL, U-ECEED) and one maintenance trial (n=502, U-ENDURE) with Upadacitinib (Rinvoq). The induction trials involved an early mandatory glucocorticoid taper.

Key findings:

  • A significantly higher percentage of patients who received 45-mg upadacitinib than those who received placebo had clinical remission (in U-EXCEL, 49.5% vs. 29.1%; in U-EXCEED, 38.9% vs. 21.1%) and an endoscopic response (in U-EXCEL, 45.5% vs. 13.1%; in U-EXCEED, 34.6% vs. 3.5%) (P<0.001 for all comparisons).
  • There was a rapid onset of action with a difference in clinical response compared to placebo at 2 weeks
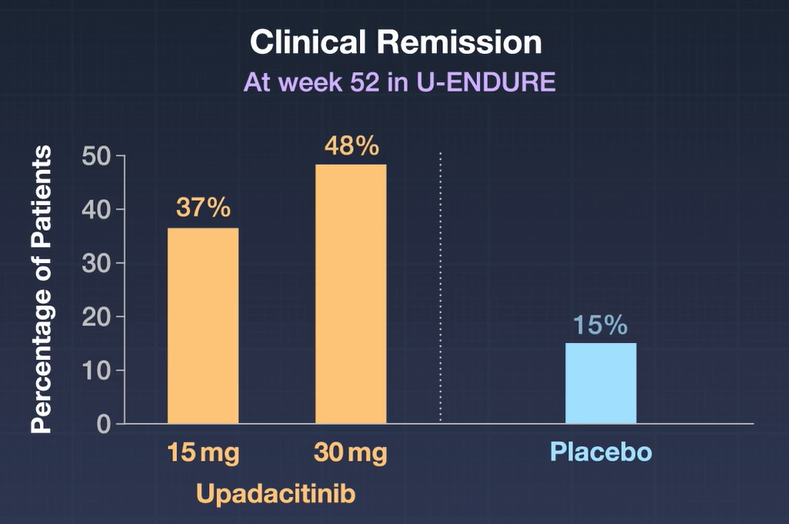
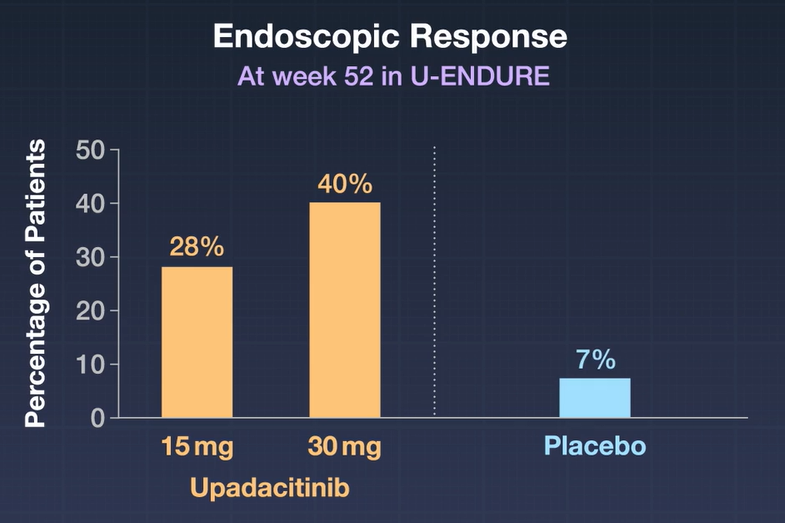
  • Maintenance Trial of clinical responders: At week 52 in U-ENDURE, a higher percentage of patients had clinical remission with 15-mg upadacitinib (37.3%) or 30-mg upadacitinib (47.6%) than with placebo (15.1%), and a higher percentage had an endoscopic response with 15-mg upadacitinib (27.6%) or 30-mg upadacitinib (40.1%) than with placebo (7.3%) (P<0.001 for all comparisons).
  • Adverse effects included gastrointestinal perforations (6 in study medication, 1 in placebo), neutropenia in up to 2.6%, and increased Herpes Zoster infections in patients receiving study medication (1.5% to 3%).

A good commentary of this study is in the same issue: M Abreu. N Engl J Med 2023; 388:2005-2009. It is noted that upadacitinib showed a good response even though a different JAK inhibitor, tofacitinib, had disappointing results for patients with Crohn’s disease. Other points:

  • “It is hard to compare findings across studies because of differences in the characteristics of patients and end points. That being said, the incidences of clinical remission observed by Loftus et al. were greater than those observed in most studies of biologic drugs to treat Crohn’s disease. Moreover, upadacitinib was more likely than placebo to resolve extraintestinal manifestations.”
  • “They did not find evidence of cardiovascular or thromboembolic complications, which were previously observed in patients with rheumatoid arthritis treated with tofacitinib and which led to a black-box warning.10 However, the treatment of greater numbers of patients for a longer duration will be required to determine whether upadacitinib is asssociated with a risk of such complications.”
  • “Among the most common upadacitinib-specific adverse events were anemia [6.9%] and acne [6.3%]. The increase in anemia may be due to off-target effects of upadacitinib on erythropoietin signaling through JAK2.”

My take: This is great news for patients with Crohn’s disease. In addition to having a new option for refractory disease, this option does not require IV administration. When will pediatric data be available?

New FDA Rinvoq (upadacitinib) Indication: Oral Treatment For Crohn’s

5/18/23: FDA approves first oral treatment for moderately to severely active Crohn’s disease

“Patients should start with 45 mg of Rinvoq once daily for 12 weeks. Following the 12-week period, the recommended maintenance dosage is 15 mg once a day. A maintenance dosage of 30 mg once daily can be considered for patients with refractory, severe, or extensive Crohn’s disease.”

“The most common side effects of Rinvoq as indicated for Crohn’s disease are upper respiratory tract infections, anemia, fever, acne, herpes zoster, and headache…. Serious infections, mortality, malignancy, major adverse cardiovascular events, and thrombosis have occurred with JAK inhibitors such as Rinvoq.”

Tucson Botanical Gardens

How Does Bowel Ultrasound Stack Up to MRE for Crohn’s Disease?

A Rispo et al. Inflamm Bowel Dis 2023; 29: 563-569. David Against Goliath: Direct Comparison of Handheld Bowel Sonography and Magnetic Resonance Enterography for Diagnosis of Crohn’s Disease

Lately, there has been a lot of ‘buzz’ about the potential use of point-of-care bowel sonography (aka intestinal ultrasound). This study (2019-2021) prospectively enrolled patients with a high likelihood of Crohn’s disease (CD) and compared handheld bowel sonography (HHBS), MRE (all patients, n=85, had ileocolonoscopy)

Key findings:

  • Sensitivity, specificity, positive predictive values, and negative predictive values for CD diagnosis were 87.50%, 91.89%, 93.33%, and 85% for HHBS; and 91.67%, 94.59%, 95.65%, and 89.74% for MRE, without significant differences in terms of diagnostic accuracy (89.41% for HHBS vs 92.94% for MRE, P = NS)
  • Magnetic resonance enterography was superior to HHBS in defining CD extension (r = 0.67; P < .01) with a better diagnostic performance than HHBS for detecting location (k = 0.81; P < .01), strictures (k = 0.75; P < .01), abscesses (k = 0.68; P < .01), and fistulas (k = 0.65; P < .01).

My take: In this study, MRE was clearly superior at defining CD complications. This study suggests that HHBS could be an effective screening tool but is not likely a definitive imaging study. In terms of bedside monitoring, it would be helpful to see how clinical monitoring with HBSS compares with a highly sensitive marker like a calprotectin. I also worry that HBSS could perform more poorly with more widespread application due to potential increase in operator error.

If a Gastroparesis Medication Works in the Forest But No One Sees It, Did It Really Work?

MR Ingrosso et al. Gastroenterol 2023; 164: 642-654. Open Access! Efficacy and Safety of Drugs for Gastroparesis: Systematic Review and Network Meta-analysis

The authors examined  29 RCTs (3772 patients). Key findings:

  • Only two medications (neither available in U.S.) were identified as being more effective than placebo for global symptoms of gastroparesis: clebopride (RR, 0.30) followed by domperidone (RR, 0.68) 
  • Oral metoclopramide ranked first for nausea (RR 0.46), fullness (RR 0.67), and bloating. Though, use may result extrapyramidal adverse effects

In the associated editorial (pg 522-524, Drug Treatments for Gastroparesis—Why Is the Cupboard So Bare?), the authors note that the label “gastroparesis” applies to a heterogeneous population.

Key points:

  • I tend to abide by the recommendation proposed by Masaoka and Tack10 some years ago that one should use the term gastroparesis only “when persistently and severely delayed gastric emptying is found in the absence of mechanical obstruction.” 
  • An obsession with gastroparesis as the basic issue among patients with “gastroparesis-like” symptoms has translated into a therapeutic fixation on the acceleration of gastric emptying. This too has led to frustration and disappointment. As already mentioned, symptoms are a poor predictor of the rate of gastric emptying, and a normalization of delayed emptying has not consistently correlated with symptom responses and vice versa.11,12
  • Oblivious to research illustrating how upper gastrointestinal symptoms can result from several other derangements in foregut physiology, such as impaired accommodation of the upper stomach, visceral hypersensitivity, and antropyloric distensibility and dysmotility,13, 14, 15, 16

My take: Currently, pharmaceutical agents geared towards symptoms like nausea and sensory disorders are much more promising than prokinetic agents for gastroparesis

Related blog posts:

Sunset in Tucson, AZ at Tumamoc Hill

Synergistic Dangers: Helicobacter Pylori and Cancer Genes

Y Usui et al. NEJM 2023; 388: 1181-1190. Helicobacter pylori, Homologous-Recombination Genes, and Gastric Cancer

Background: Gastric cancer is the fifth most common neoplasm and the fourth leading cause of death from cancer worldwide.1 Helicobacter pylori has been classified as a group I carcinogen and is an environmental risk factor for gastric cancer.2 Although H. pylori infection affects more than half the world population

Methods: This study evaluated the association between germline pathogenic variants in 27 cancer-predisposing genes and the risk of gastric cancer in a sample of 10,426 patients with gastric cancer and 38,153 controls from BioBank Japan. This retrospective study also assessed the combined effect of pathogenic variants and H. pylori infection status on the risk of gastric cancer and calculated the cumulative risk in 1433 patients with gastric cancer and 5997 controls from the Hospital-based Epidemiologic Research Program at Aichi Cancer Center (HERPACC).

Key findings:

  • Germline pathogenic variants in nine genes: (APC, ATM, BRCA1, BRCA2, CDH1, MLH1, MSH2, MSH6, and PALB2) were associated with the risk of gastric cancer.
  • At 85 years of age, persons with H. pylori infection and a pathogenic variant had a higher cumulative risk of gastric cancer than noncarriers infected with H. pylori (45.5% vs. 14.4%).
  • Limitation: The study population was from East Asia and thus, the findings may be different in other populations.

My take: H. pylori infection has a synergistic effect in increasing the risk of gastric cancer in individuals with germline pathogenic variants in homologous-recombination genes. To minimize the risk of gastric cancer, H pylori eradication is important; however, it is especially in those with cancer-predisposing variants.

From NEJM Twitter Feed

Related blog posts:

Vedolizumab for Chronic Pouchitis

S Travis et al. NEJM 2023; 388: 1191-1200. Vedolizumab for the Treatment of Chronic Pouchitis

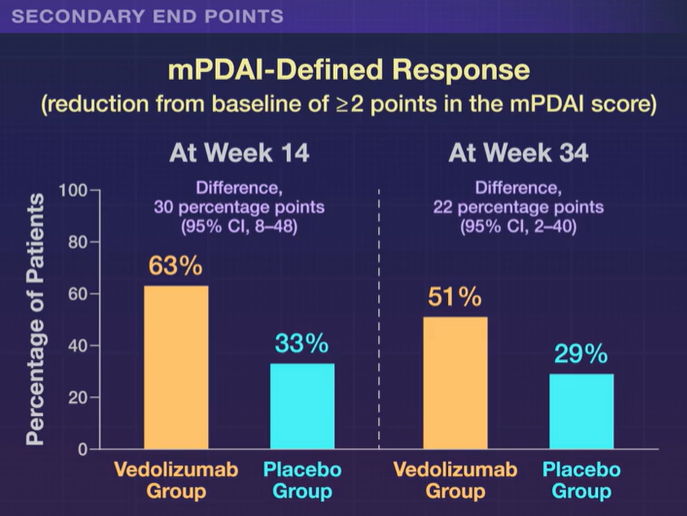
Methods: This was a a phase 4, double-blind, randomized trial (n=102 adults,EARNEST trial) to evaluate vedolizumab in adult patients in whom chronic pouchitis had developed after undergoing IPAA for ulcerative colitis.All patients received 4 weeks of ciprofloxacin and the treatment group received standard vedolizumab dosing. The primary end point was modified Pouchitis Disease Activity Index (mPDAI)–defined remission (an mPDAI score of ≤4 and a reduction from baseline of ≥2 points in the mPDAI total score; scores range from 0 to 12, with higher scores indicating more severe pouchitis) at week 14. The mPDAI is based on clinical symptoms and endoscopic findings.

Key findings:

  • The incidence of mPDAI-defined remission at week 14 was 31% (16 of 51 patients) with vedolizumab and 10% (5 of 51 patients) with placebo
  • Differences in favor of vedolizumab over placebo were also seen with respect to mPDAI-defined remission at week 34 (difference, 17 percentage points, 35% vs 18%)

My take: Vedolizumab is an effective treatment for chronic pouchitis.

This figure is from NEJM Twitter Feed

Related blog posts:

AGA Practice Update: Acute Hepatic Porphyrias

B Wang et al. Gastroenterol 2023; 164: 484-491. Open Access! AGA Clinical Practice Update on Diagnosis and Management of Acute Hepatic Porphyrias: Expert Review

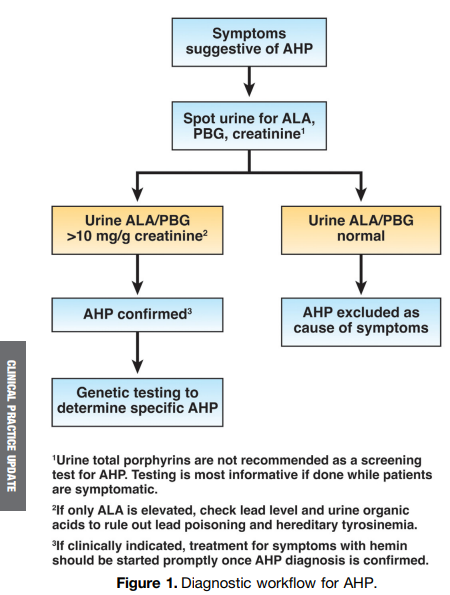
Overall, acute hepatic porphyrias (AHP) are rare disorders. “Acute intermittent porphyria is the most common type of AHP, with an estimated prevalence of patients with symptoms of
approximately 1 in 100,000. The major clinical presentation involves attacks of severe pain, usually abdominal and generalized, without peritoneal signs or abnormalities on cross-sectional imaging…The screening tests of choice include random urine porphobilinogen and d-aminolevulinic acid corrected to creatinine.”

“All patients with elevations in urinary porphobilinogen and/or d-aminolevulinic acid should initially be presumed to have AHP. The cornerstones of management include discontinuation of porphyrinogenic drugs and chemicals, administration of oral or intravenous dextrose and
intravenous hemin, and use of analgesics and antiemetics. Diagnosis of AHP type can be confirmed after initial treatment by genetic testing for pathogenic variants in HMBS, CPOX, PPOX, and ALAD genes.”

Some of the best practice advice:

  • Women aged 15–50 years with unexplained, recurrent severe abdominal pain without a clear etiology after an initial workup should be considered for screening for an AHP.
  • Initial diagnosis of AHP should be made by biochemical testing measuring d-aminolevulinic acid, porphobilinogen, and creatinine on a random urine sample.
  • Genetic testing should be used to confirm the diagnosis of AHP in patients with positive
    biochemical testing.
  • Acute attacks of AHP that are severe enough to require hospital admission should
    be treated with intravenous hemin, given daily, preferably into a high-flow central vein

Related blog posts:

Guideline: Biomarker Use for Ulcerative Colitis

S Singh et al. Gastroenterol 2023; 164: 344-372. Open Access! AGA Clinical Practice Guideline on the Role of Biomarkers for the Management of Ulcerative Colitis Clinical Decision support tool (pg 373-374), Spotlight (pg 375).

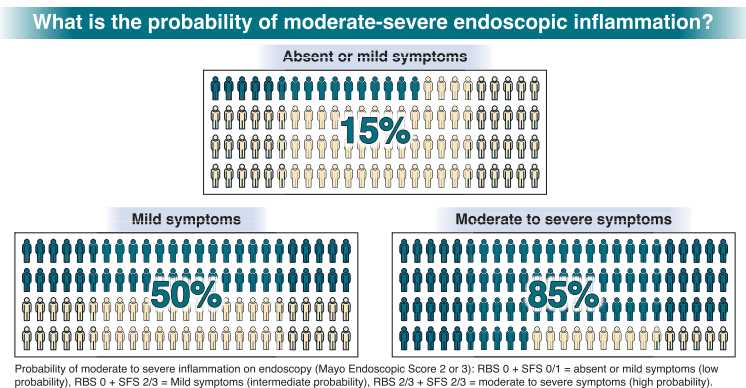
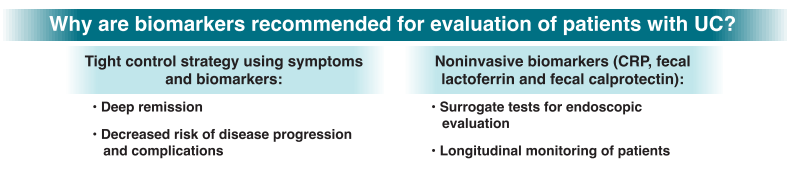
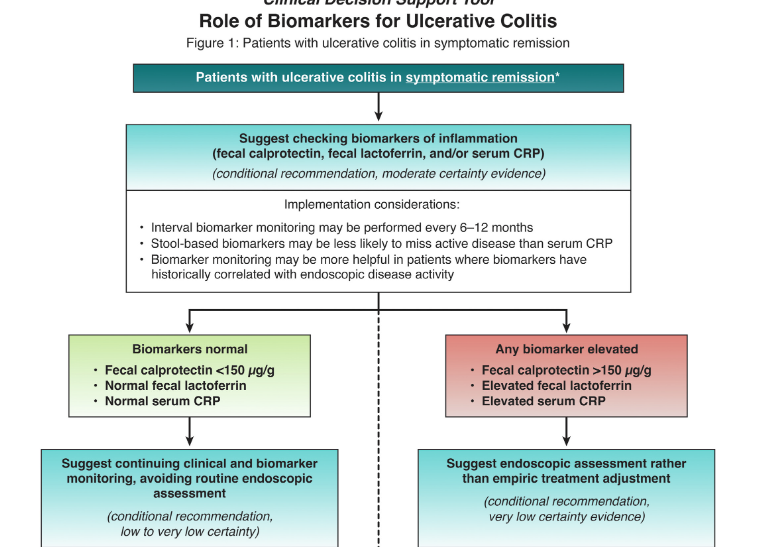
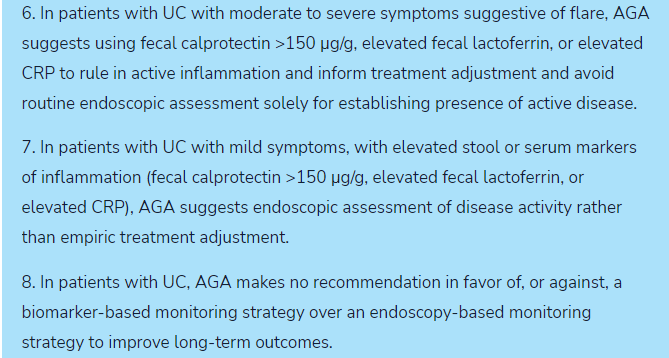
The full access links to the article and related articles provide extensive information and rationale for AGA’s biomarker recommendations in ulcerative colitis (UC). For me, the recommendations highlight the important role of biomarkers (especially fecal calprotectin (FC)) when things are going very well or very poorly. Key points:

  • In asymptomatic patients with normal biomarkers (FC <150, normal lactoferrin, normal CRP), the recommendations suggest continued monitoring without endoscopic assessment.
  • In patients with moderate-to-severe symptoms and with elevated biomarkers, the authors, likewise, advocate for treatment adjustment without endoscopic assessment.
  • For asymptomatic patients with elevated biomarkers and symptomatic patients with normal biomarkers, the authors recommend endoscopic assessment.
From Spotlight Material

My take: By combining biomarkers with symptoms, this improves utility of more invasive testing.

Related blog posts: