Esophagitis in Pediatric Esophageal Atresia

A recent study (JL Yasuda et al. JPGN 2019; 69: 163-70) shows that esophagitis is common with and without proton pump inhibitor (PPI) therapy in children with esophageal atresia (EA).

Background: This study encompassed 310 patients (34% long gap EA) and 576 endoscopies (median age 3.7 years)

Key findings:

  • Erosive esophagitis was found in 8.7% of patients.
  • 15.2% of patients had esophagitis with >15 eos/hpf; 49% of patients had ≥1 eos/hpf (histologic eosinophilia)
  • 87% of endoscopies were preceded by acid suppression therapy; being on acid suppression reduced the odds for abnormal esophageal biopsy (P=0.011).
  • Histologic esophagitis was “highly prevalent even with high rates of acid suppressive medications use.”
  • For example, among those receiving PPI monotherapy, 150 had normal biopsy and 136 had abnormal biopsy.  Among those off all acid suppression, 30 had normal biopsy and 45 had abnormal biopsy.
  • For erosive esophagitis, this occurred in 12 on PPI and was not present in 274 on PPI therapy. Among those off all acid suppression, 4 had erosive esophagitis and 70 did not.
  • Presence or integrity of fundoplication was not significantly associated with esophagitis.

While this is a large study, the findings have several limitations. This is a single center retrospective study and this center attracts highly complex cases of EA.

My take: In addition to fairly high rates of erosive esophagitis and eosinophilic esophagitis, this study shows a high incidence of microscopic esophagitis, the significance of this is unclear.   This study supports the current recommendations of 3 endoscopies in childhood and perhaps more frequent surveillance in those with more complex EA.

Related blog posts:

Sign in Hood River, OR


Integrating Mental Health into Pediatric IBD Care

WE Bennett, MD Pfefferkorn. JAMA Pediatr. Published online August 19, 2019. doi:10.1001/jamapediatrics.2019.2669

Full Link: Editorial: “Mental Health Screening as the Standard of Care in Pediatric Inflammatory Bowel Disease” Thanks to Ben Gold for this reference.

An excerpt:

Butwicka and colleagues1 have published a fascinating, landmark cohort study in this issue of JAMA Pediatricsassessing the prevalence of psychiatric diagnoses and symptoms among children with inflammatory bowel disease (IBD) in Sweden. The authors used a rigorous design that compared a cohort of more than 6000 pediatric patients with IBD with hundreds of thousands of healthy controls, as well as a separate cohort comprising the patients’ own siblings who did not have IBD. Butwicka et al1 computed hazard ratios for any psychiatric disorder, as well as for multiple specific disorders, and found a hazard ratio of 1.6 for any psychiatric diagnosis when comparing children with IBD with healthy controls. The statistical analysis is stellar and represents the best data we currently have on the intersection of pediatric IBD and mental health. Their study highlights a substantial risk in a vulnerable population and should trigger revision of guidelines and allocation of resources to support widespread screening and treatment for these dangerous conditions.

Related Article:

A Butwicka et al. JAMA Pediatr. Published online August 19, 2019. doi:10.1001/jamapediatrics.2019.2662 

Full Text Link: Association of Childhood-Onset Inflammatory Bowel Disease With Risk of Psychiatric Disorders and Suicide Attempt

Related blog posts:

Crater Lake, OR

Briefly noted: Psoriasis due to Infliximab

O Courbette et al. JPGN 2019; 69: 189-93. Infliximab Paradoxical Psoriasis in a Cohort of Children With Inflammatory Bowel Disease

From Abstract:

Results: One hundred and twenty-three CD patients and 24 UC patients were treated with IFX. Twenty patients (13.6%) experienced a paradoxical psoriasis. All of them were affected by CD. Perianal CD was more frequent in the psoriasis group (P = 0.033). Fourteen patients (70%) were in remission when skin lesions occurred. Paradoxical psoriasis was diagnosed 355 days (median, interquartile range [IQR] 239; 532) after the initiation of IFX corresponding to the eighth injection (median, IQR: 6; 15). Psoriasis lesions were controlled by local steroids in all cases and no patients discontinued IFX therapy.

Conclusions: 13.6% of our IBD patients treated with IFX developed psoriasis during a median follow-up of 23.9 months (IQR: 11.6; 36.5). Crohn disease patients with perianal disease were at a higher risk to develop this common side effect.

Combination Therapy Associated with Treatment Persistence

Another large retrospective ‘real-world’ study (C Chen et al. Inflamm Bowel Dis 2019; 1417-27) examined persistence profiles of biologic therapies in newly diagnosed IBD patients.  This study, based on Truven Health MarketScan data (2008-2015) included 5612 patients with Crohn’s disease (CD) and 3533 with ulcerative colitis (UC). There were 1156 persons (20.6%) in the pediatric age range (0-18)

Key findings:

  • Less than half of the patients continued using their initial biologic treatment after 1 year (48.5% of CD cohort and 44.8% of UC cohort).
  • For infliximab (IFX) in the CD cohort, the 1 year continued rate was 47.6% and the 5 year rate was 20.0%. In the UC cohort, the rates were 44.9% and 15.7% respectively.
  • For adalimumab (ADA) in the CD cohort, the 1 year continued rate was 50.9% and the 5 year rate was 9.1%. In the UC cohort, the rates were 45.4% and 7.7% respectively.
  • Combination therapy with immunomodulators (IMM) significantly decreased the risk of discontinuation, especially if IMM was started more than 30 days before the biologic agent (HR 0.22).  Simultaneous starting had HR of 0.32.
  • The major predictors for noncompliance included infection and hospitalization.

Why did combination therapy result in higher medication persistence rates?

  • Potential reasons included improved efficacy by direct inflammatory effects and reduced drug antibodies to TNF antagonists.  It is possible that patients receiving combination therapy had more severe disease and thus less likely to discontinue therapy.

Limitation: This study may overestimate drug discontinuation as some patients may simply have had a dosing delay.

My take: This study shows a higher-than-expected rate of drug discontinuation indicating dissatisfaction related to efficacy, cost or complications. Those receiving immunomodulators (combination therapy) were much less likely to discontinue treatment.

Related blog posts:

Wizard Island, Crater Lake, OR

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition

Combination Therapy Still Works for Inflammatory Bowel Disease (Part 1)

There is speculation that the use of therapeutic drug monitoring (TDM) may obviate the advantages of combination therapy. However, there is plenty of data supporting combination therapy including a recent retrospective population-based study (LE Targownik et al. Clin Gastroenterol Hepatol 2019; 17: 1788-98).

This ‘real-world’ study (2001-2016) utilized the Manitoba IBD database and included 852 persons with Crohn’s disease (CD) and 303 with ulcerative colitis (UC).

Key findings: 

  • In persons with CD, combination therapy (immunomodulator with a TNF antagonist) was associated with lower treatment ineffectiveness with an adjusted hazard ratio (aHR) for ineffectiveness at 0.62.  The ineffectiveness in UC persons was lower at 0.82 but did not reach statistical significance.
  • When looking at specific time frames, among patients with CD, at 1 year, combination therapy the rate of ineffectiveness-free treatment was 74.2% for combination therapy compared to 68.6% for monotherapy; at 2 years, the rates were 64.0% and 54.5% respectively.
  • Combination therapy in CD was associated with increased time to first IBD-related hospitalization with aHR of 0.53 and with lower rates of switching anti-TNF agents (aHR 0.63).  Lower rate of surgery (aHR 0.76) did not reach statistical significance.
  • The choice of immunomodulator (6-MP/AZA vs MTX) and the choice of anti-TNF agent (IFX or ADA) did not significantly influence the overall benefit of combination therapy.  Though, AZA was the main concomitant treatment (92%).
  • 90% of the patients in the study who received combination therapy had received immunomodulator therapy prior to combination therapy.  This is in contrast to the SONIC study in which patients were naive to both agents.
  • 57% of IFX users and 43% of ADA users received concomitant therapy.

My take: Combination therapy has been associated with higher response rates to IBD therapy.  This advantage has to be weighed against potential adverse effects.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Wizard Island. Crater Lake, OR

SMOFlipid vs. Intralipid for Intestinal Failure Patients

A recent study (C Belza et al. JPEN 2019; https://doi.org/10.1002/jpen.1692) showed that SMOFlipid reduced the frequency of cholestasis in intestinal failure patients. Thanks to Kipp Ellsworth for reference.

An Observational Study of Smoflipid vs Intralipid on the Evolution of Intestinal Failure–Associated Liver Disease in Infants With Intestinal Failure. From Abstract:

Methods

This was a retrospective cohort study of infants with IF with a minimum follow‐up of 12 months in 2008–2016. Patients were stratified into 2 groups: group 1 received SMOFlipid; group 2 was a historical cohort who received Intralipid. The primary outcome was liver function evaluated using conjugated bilirubin (CB) levels…

Results

Thirty‐seven patients were evaluated (17 = SMOFlipid, 20 = Intralipid). SMOFlipid patients were less likely to reach CB of 34 (24% vs 55%, P = 0.05), 50 µmol/L (11.8% vs 45%; P = 0.028), and did not require Omegaven (0% vs 30%; P = 0.014). CB level at 3 months after initiation of parenteral nutrition (PN) was lower in patients receiving SMOFlipid (0 vs 36 µmol/L; P = 0.01). Weight z‐scores were improved for patients receiving SMOFlipid at 3 months (−0.932 vs −2.092; P = 0.028) and 6 months (−0.633 vs −1.614; P = 0.018).

Related blog posts:

Crater Lake, OR

Modeling Trough Levels to Predict Optimal Infliximab Dosing

A recent study for optimizing infliximab  dosing: LE Bauman et al.  2019 Jul 9. pii: izz143. doi: 10.1093/ibd/izz143. [Epub ahead of print]

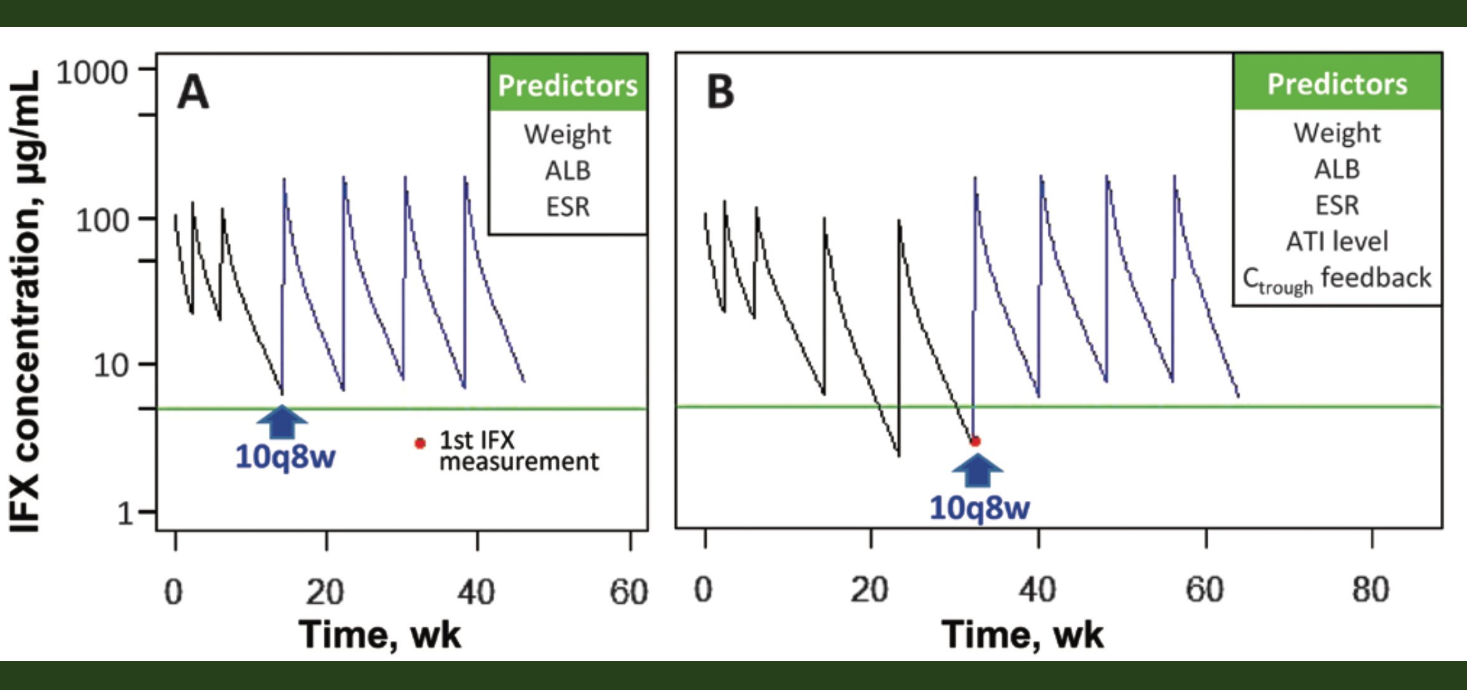
The authors identified 228 pediatric patients with IBD and developed a pharmocokinetic model using weight, albumin, sedimentation rate and antibodies to infliximab (ATI) to help predict infliximab dosing that would achieve a therapeutic trough level (>5 mcg/mL).

In their study, they also simulated 1000 patients and found that only 24% of patients receiving 5 mg/kg q8weeks achieved a therapeutic level; this increased to 56% for 10 mg/kg q8weeks.  Shortening dose interval more reliably achieved therapeutic levels: 5 mg/kg q4 weeks had a target level in 84% and 10 mg/kg q6 weeks had a target level in 80%.

The image above corresponds to Figure 5 in the manuscript.  This figure shows the difference between proactive and reactive dosing strategy.  In the first panel, a higher initial dose prevents suboptimal dosing whereas the second panel shows suboptimal troughs until adjustment of dose after identifying a low trough.  Avoiding low troughs may reduce the likelihood of developing antibodies to infliximab and therapeutic failure

My take: This study and several others indicate that most pediatric patients need either more frequent inflixmab dosing or higher initial doses to achieve therapeutic levels and to improve outcomes.

Study: Soda (even diet soda) May Increase Mortality

From Reuters –Link: Soft drinks – sugared or low-calorie – may raise the risk of early death

Link to abstract: Association Between Soft Drinks Consumption and Mortality in 10 European Countries

Excerpt:

In a study that followed more than 400,000 European adults for more than 16 years, the risk of premature death was heightened in those who consumed 2 or more glasses per day of soft drinks, according to the report published in JAMA Internal Medicine…

The new findings don’t mean that soft drinks cause early death, because “in these types of studies (observational epidemiology) there are other factors which may be behind the association we observed,” Murphy added in an email. “For instance, high soft drink consumption may be a marker of overall unhealthy diet”…

Participants who consumed two or more glasses of soft drinks per day were 17% more likely to die early compared to those who drank less than a single serving of soft drinks per month…

Those who consumed two or more glasses of artificially sweetened soft drinks a day were 26% more likely to die prematurely compared to those who drank less than a glass per month.

My take: Whether drinking soda directly impacts one’s health or is a marker for an unhealthy lifestyle is not settled by this study.  Yet, I feel confident that preferentially drinking water is a healthy habit.

Related blog posts:

Proactive Therapeutic Drug Monitoring -Different Time Points

Yesterday’s post outlined expert recommendations for proactive therapeutic drug monitoring (pTDM).  Today’s post reviews a study (NV Casteele et al. Clin Gastroenterol Hepatol 2019; 17: 1814-21) which identifies optimal levels at earlier time points. The authors note that “higher infliximab (IFX) concentrations during induction therapy  are correlated with long-term relapse-free and colectomy-free survival.”

The authors analyzed data from 484 patients with active ulcerative colitis (UC) from two double-blind, placebo-controlled, parallel group studies: ACT-1 and ACT-2.

Key findings:

  • IFX levels ≥18.6 mcg/mL at week 2, ≥10.6 mcg/mL at week 6, and ≥34.9 mcg/mL at week 8 were associated with Mayo endoscopic scores (MES) of ≤1 at week 8.
  • IFX level of ≥5.1 mcg/mL at week 14 was associated with MES of ≤1 at week 30
  • IFX level of ≥6.7 mcg/mL at week 14 was associated with MES of 0 at week 30

My take: In pediatric patients receiving monotherapy with an anti-TNF agent, checking earlier levels (week 6, week 8, or week 10) may help avoid low troughs which are associated with a higher likelihood of treatment failure.  This study provides guidance on target levels at earlier time points.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Crater Lake, OR. The blue color is amazing !


Toronto Consensus Guidelines for Luminal Crohn’s Disease

The recommendations from the Canadian Association of Gastroenterology for luminal Crohn’s Disease in adults were published in two journals.  R Panaccione et al. Clin Gastroenterol Hepatol 2019; 17: 1680-1713 and R Panaccione et al . 2019 Aug; 2(3): e1–e34.

Full text link : Canadian Association of Gastroenterology Clinical Practice Guideline for the Management of Luminal Crohn’s Disease

A few of the 41 statement recommendations:

  • 6. In patients with mild to moderate ileal and/or right colonic Crohn’s disease, we suggest oral budesonide beginning at 9 mg/day as first-line therapy to induce complete remission. GRADE: Conditional recommendation, low-quality evidence
  • 20. In patients with moderate to severe luminal Crohn’s disease with risk factors of poor prognosis, we recommend anti-TNF therapy (infliximab, adalimumab) as first-line therapy to induce complete remission. GRADE: Strong recommendation, moderate-quality evidence
  • 23. In patients with active Crohn’s disease, when starting anti-TNF therapy, we suggest it be combined with a thiopurine or methotrexate over monotherapy to improve pharmacokinetic parameters. GRADE: Conditional recommendation, very low-quality evidence for infliximab, very low-quality evidence for adalimumab
  • 29. We suggest against switching between anti-TNF therapies in patients who are doing well on anti-TNF therapy. GRADE: Conditional recommendation, low-quality evidence
  • 30. In patients with moderate to severe Crohn’s disease who fail to achieve complete remission with any of corticosteroids, thiopurines, methotrexate, or anti-TNF therapy, we recommend vedolizumab to induce complete remission. GRADE: Strong recommendation, moderate-quality evidence
  • 34. In patients with moderate to severe Crohn’s disease who fail to achieve complete remission with any of corticosteroids, thiopurines, methotrexate, or anti-TNF therapy, we recommend ustekinumab to induce complete remission. GRADE: Strong recommendation, moderate-quality evidence
  • 37-41: Authors against the use of probiotics, omega-3 fatty acids, marijuana, naltrexone and enteral nutrition/diet therapies.

Crater Lake and Wizard Island