How Helpful is Endoscopic Pancreatic Testing in Pediatrics?

A recent study (P Hopson et al. JPGN 2019; 68: 854-60) reports a high rate of isolated amylase deficiency of 10.1% in their cohort. Is this really accurate? I am skeptical.

  • This is a retrospective study and the authors undertook endoscopic pancreatic function testing (ePFT) in a large number of patients, 712 over a 6 year period.  The authors state “whenever there is clinical indication for esophagogastroduodenoscopy (EGD) we usually obtain” ePFT collections.
  • To determine the amylase levels, the authors relied upon their in-house laboratory.  Before accepting widespread deficiencies in amylase production, it would be useful to have specimens checked in more than one laboratory. At the same time, given the normalcy of the other pancreatic enzymes, it is likely that the specimens were of good quality.
  • 59 of the 72 (82%) patients with isolated amylase deficiency were younger than 2 years. It is notable that in the same issue, some of the same authors in a review article describe the technique for ePFT (JPGN 2019; 68: 768-76) and note that amylase activity is undetectable at 1 month of age and is normal at 2 years of age.  “Data are lacking as to when it is expected that most children have normal pancreatic amylase activity before 2 years of age.”
  • The authors note that 48 patients (67%) with isolated amylase deficiency had failure to thrive or poor growth.

Amylase Levels:

  • Looking at the authors’ Figure 1, they do provide their mean amylase levels; they considered a level below 10.3 micromol/min/mL to be deficient.  Is this the right cutoff? Is there evidence that levels below this result in a disease state?
  • Particularly in the first year of life, the amylase activities are much lower: approximately 2 micromol/min/mL for age 0-6 months and 12 micromol/min/mL for 6-12 months.
  • In their cohort of 72 with abnormal amylase levels, 35 (approximately half) are less than 1 year of age.  Thus, given how low the mean levels are, it is not surprising that nearly half of the patients (35/82) in this age group had abnormal ePFT.
  • Even in the 1-1.5 year olds, the mean amylase activity is lower than the older group (approximately 24 micromol/min/mL compared to more than 40 micromol/min/mL for patients older than 6 years).  The authors found 25% of the ePFT testing in this age group (1-15. yr olds) to have isolated amylase deficiency; again, this seems implausible.
  • It is notable that there is not a control population.  How often in healthy patients less than 2 years of age is the amylase level below their cutoff? In fact, the authors state that 10 of their patients with isolated amylase deficiency had constipation, and 5 had reflux which would be quite atypical presenting indications.

The technique for obtaining ePFT is detailed in the review (JPGN 2019; 68: 768-76) and includes the following:

  • Before endoscopic intubation, “a bolus of secretin (0.2 mcg/kg to max of 16 mcg) is administered” (or alternatively synthetic CCK octapeptide in a dose of 0.02 or 0.04 mcg/kg).
  • Initial fluid in stomach and duodenum is aspirated and discarded
  • Using an aspiration catheter (or thru biopsy channel if scope too small), collect 3 to 4 aliquots of fluid between 3-10 minutes after injection of secretin (should be completed within 10 minutes of secretin)
  • Place immediately on ice or dry ice
  • Samples with low pH may be contaminated
  • Avoid trauma to mucosa as bleeding can give erroneous results

I would suggest a more selective approach in utilizing endoscopy to check for both pancreatic function as well as disaccharidases.  The sensitivity, specificity, positive predictive value and negative predictive value of a test is highly dependent on the study population. In those at low risk, the results of the testing is highly suspect.

My take: The reference to the review article is worth keeping as it gives a clear description of endoscopic pancreatic function testing.  The study describing a 10% rate of amylase deficiency among a large cohort of pediatric patients requires careful interpretation, particularly as more than 80% of the deficiency group were less than 2 years of age. Clearly, a prospective study is needed.  In those with possible isolated amylase deficiency at a young age (<2 years), a double-blind randomized trial may be needed to determine if enzyme supplementation is beneficial.

Related blog posts: Transient Exocrine Pancreatic Insufficiency or Misleading Tests?

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.


Camille Passaro, Rue Saint-Honore por la Tarde. Efecto de lluvia.  Thyssen-Bornemisza Museum; https://www.museothyssen.org/en/collection/artists/pissarro-camille/rue-saint-honore-afternoon-effect-rain



Backwash Ileitis Plus One

Briefly Noted:

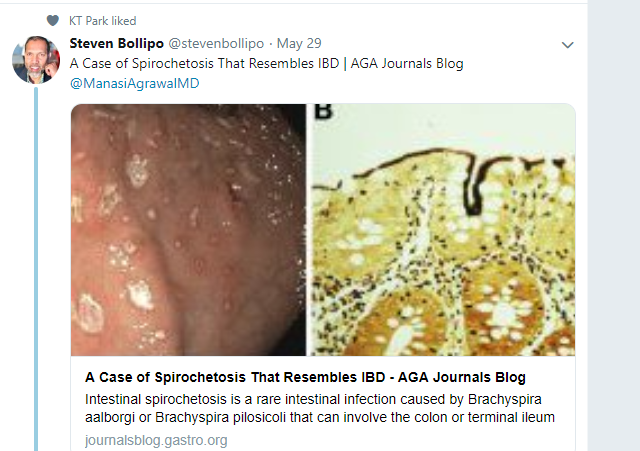
RM Najarian et al. JPGN 2019; 68: 835-40.  This retrospective study found microscopic/’backwash’ ileitis in 16% (17/105) of patients with new-onset ulcerative colitis. This occurred predominantly in patients with pancolitis (82%). The authors note that the term “backwash ileitis” was derived from an unproven hypothesis that the inflammation was related to retrograde contact with inflammatory substances, though some now consider ileal involvement as a secondary involvement “akin to the upper tract inflammation that can be seen in a subset of patients with UC.” The authors recommend that isolated histologic inflammation of the ileum should “not be construed as being diagnostic of either ‘indeterminant colitis’ or CD [Crohn’s disease].”

K van Hoeve et al. JPGN 2019; 68: 847-53. This retrospective study of 35 children found that higher infliximab levels during induction was associated with higher rates of clinical and biologic remission at 52 weeks. Groups at risk for lower troughs included patients with a lower weight and/or lower hemoglobin level.

Rafaela Flores Calderon by Antonio Maria Esquivel, Museo del Prado (Image in Public Domain)

Detergent Pod Ingestions -Is an Endoscopy Needed?

A recent study (A Singh et al. JPGN 2019; 68: 824-8) provides a descriptive retrospective review of a single center experience with detergent pods (a.k.a. laundry pods or dishwater pods). There is very little published in this area and no clear consensus on management.

For me, the most interesting finding in the study is the discrepancy between the ENT service which only did a direct laryngoscopy-bronchoscopy (DLB) in 6 of 23 (26%) ingestions compared with 21 of 23 (91%) EGD rate among patients who presented to the GI service.

Key findings:

  • Of those undergoing an EGD, 76% were normal; abnormal findings (edema, erythema or ulceration) were present in 24% (though figure 4 suggests erythema in 28%). Ulceration was noted in 14%.
  • In the DLB cohort (n=6), 33% were normal and 67% were abnormal.

Unfortunately, this report has a lot of limitations:

  • It did not provide any information regarding long-term effects (if any were present)
  • It did not provide much guidance in determining whether an EGD is worthwhile. The authors did note that patients with oral injuries were more likely to have an abnormal EGD. 80% of patients with positive oropharyngeal findings had an abnormal EGD compared with 20% with a normal oropharyngeal exam.
  • In the discussion, the authors reference a study which reported esophageal injury in only 0.1% of cases (Davis et al.  2016 May;137(5). pii: e20154529. doi: 10.1542/peds.2015-4529. Pediatric Exposures to Laundry and Dishwasher Detergents in the United States: 2013-2014). There were two deaths in this study.

My take: This would have been a good report to have an associated commentary/expert opinion.  Even if an EGD is abnormal, this does not mean that the EGD was needed.  The bigger question is how often an EGD would improve management.  Given the lack of specific treatments, it is likely that an EGD should be reserved for severe cases –which could include the following:

  • intentional ingestions
  • significant oropharyngeal burns
  • food refusal
  • drooling/difficulty managing secretions
  • stridor

Related blog post: New caustic danger from detergent pods

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Detergent Pods -Still an Issue -This Tweet is from June 5, 2019

William Meyers

Yesterday I attended the Inaugural William Meyers Lecture and intended for this post to be a summary of that.  Sadly, he passed away last night.

Billy, a partner in our GI group, had been fighting brain cancer for the past year. This lecture was established to honor him. Jose Garza gave a lecture which highlighted the important work of the neurogastroenterology service, established in large measure by Billy.

Also, Billy served on numerous hospital committees.  Much of his efforts were ‘behind the scenes’ and usually the type of work that many of us seek to avoid.  In addition to working on these hospital committees, Billy remained a busy clinician.  In the past year, I’ve had the opportunity to interact with many of his patients and families.  Uniformly I have heard how compassionate and patient he was, even with the most complex situations.  In the 22 years that I had the opportunity to work with Billy, I cannot seem to recall him ever being flustered.  He was a truly wonderful person, physician, and mentor..   I will miss his kindness and friendship.


Capsaicin for Cannaboid Hyperemesis Syndrome

Capsaicin is the stuff in chili peppers that makes your mouth feel hot. But it also has some medical purposes. It’s a key ingredient in creams and patches that has been used for pain relief (e.g. joint, muscle, headaches).

From our recent hospital PNT meeting –information on using Capsaicin for Cannaboid Hyperemesis Syndrome (CHS).

What is cannabinoid hyperemesis syndrome (CHS)?

  • Clinical syndrome in which marijuana users develop nausea, cyclic vomiting, and abdominal pain that improves with a hot water bath or cannabis cessation
  • Often refractory to standard treatment for nausea/vomiting
  • No laboratory or diagnostic tests for CHS

Capsaicin Mechanism for CHS

  • Transient receptor potential vanilloid subtype 1 (TRPV1) receptor is expressed in the brain, along enteric and vagal nerves, and on cutaneous receptors in the skin
  • Chronic cannabis use results in inactivation of TRPV1 receptor leading to  nausea & emesis
  • Nociceptive heat, such as topical capsaicin, acts as a TRPV1 agonist restoring gastric motility
  • Activation of TRPV1 receptor results in potent anti-emetic effects
  • Capsaicin exposure results in subsequent desensitization of the sensory axons and inhibition of pain transmission initiation.

Topical Capsaicin

  • Product: Capsaicin cream 0.025% (Generic)
  • Dosing: Apply thin film to affected area not more than 3 to 4 times/day
  • Benefits:
    • Less adverse effects than unconventional antiemetics (e.g., haloperidol)
    • Cost-effective
  • Adverse effects: “burning sensation” on skin
  • Average wholesale price: $10 per 60 gram tube

Supporting literature

  • Graham J, et al.
    • Case series in which capsaicin was successfully used to treat CHS in two pediatric patients presenting to the emergency department (ED).
    • In a 16 yo & 20 yo, each with two ED visits, on the 2nd visit: due to history of cannabis use, CHS became working diagnosis, patients agreed to try capsaicin cream (0.025%, 1 mm-thick coating) applied to the abdomen. Thirty minutes after capsaicin application, patients pain decreased to a 3 out of 10 and her nausea resolved

References:

  1. Moon AM, Buckley SA, Mark NM. Successful treatment of cannabinoid hyperemesis syndrome with topical capsaicin. ACG Case Rep J. 2018 Jan 3;5:e3.
  2. Graham J, Barberio M, Wang GS. Capsaicin cream for treatment of cannabinoid hyperemesis syndrome in adolescents: A case series. 2017 Dec;140(6): e20163795.

My take: Capsaicin use for CHS is supported by case reports.

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

From Barcelona chocolate museum –everything is chocolate

Aprepitant for CVS

Last year at NASPGHAN meeting (NASPGHAN Highlights and Tweets), there was data presented on aprepitant for cyclic vomiting syndrome (CVS).  This came up at a recent hospital PNT meeting as well.

  • Aprepitant (Emend) is an anti-emetic that works by blocking the NK1 receptor.
  • It has FDA approval for prevention of nausea and vomiting in moderate and highly emetogenic chemotherapy (adults and pediatrics) and prevention of post-operative nausea and vomiting (adult only).

Supporting Data for use of Aprepitant

An abstract published in 2006 reported on the use of aprepitant in 11 children (3-16 years)2.   Patients were refractory to/had poor response to pizotifen (not available in US – serotonin and histamine antagonist), propranol, and ondansetron.  Aprepitant was dosed at 80 mg/m2 up to twice weekly in combination with ondansetron.  Nine out of 11 patients had reduction in cycle frequency, duration of vomiting episodes and intensity of vomiting.  Three patients achieved complete cycle abolishment.

Cristoferi et al retrospectively reviewed 41 patients (age range 4-16.5 years, median 8 years) treated acutely or prophylactically with aprepitant.3  The primary outcome was decrease in frequency and intensity of CVS episodes.  The follow up period was 18-60 months.  The majority of patients failed cyproheptadine/pizotiphen, ondansetron, and amitriptyline as prophylactic medications.

Dosing regimens utilized in Cristoferi paper:

Prophylactic regimen (oral):

  • < 40 kg, 40 mg twice/week = $220/week (average wholesale price)
  • >40 kg to < 60 kg, 80 mg twice/week = $408/week
  • > 60 kg, 125 mg twice/week = $612/week

Acute regimen (oral):

  • >20 kg, 125 mg x 1 followed by 80 mg on day 2 and day 3 = $714
  • 15-<20 kg, 80 mg x 3 days = $612
  • < 15 kg, 80 mg x 1 followed by 40 mg on day 2 and day 3 = $424

Response rates:

  • With the prophylactic regimen, the authors reported a complete response in 3/16 (19%) and a partial response 10/16 (62%) [partial response was considered if there was ≥50% decrease in CVS episode frequency and intensity].
  • With the acute regimen, the authors reported 19/25 (76%) with a complete response and 3/25 (12%) with a partial response.

My take: Aprepitant appears promising as an agent for children who fail first-line therapies like periactin, tricyclic antidepressants, and ondansetron.

References

  1. Bhandari S and Venkatesan T.  Novel treatments for cyclic vomiting syndrome:  beyond ondansetron and amitriptyline.  Curr Treat Options Gastro 2016;14:495-506.
  2. Russell RK, et al. NK1 receptor antagonism ameliorates nausea and emesis in typical and atypical variants of treatment refractory cyclical vomiting syndrome.  J Pediatr Gastroenterol Nutr 2006;42:E13.
  3. Cristoferi F, et al. Efficacy of the neurokin-1 receptor antagonist aprepitant in children with cyclical vomiting syndrome.  Aliment Pharmacol Ther 2014;40:309-17.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Highest Reported Prevalence Rates for Eosinophilic Esophagits

A recent retrospective study (J Robson et al. Clin Gastroenterol Hepatol 2019; 17: 107-14) utilized a pathology database encompassing the vast majority of Utah pediatric cases to determine the incidence and prevalence of eosinophilic esophagitis (EoE) from 2011 to 2016.

The authors determined cases of EoE by looking for symptomatic children with isolated esophageal eosinophilia (more that 14 eos/hpf) in the absence of other comorbid conditions.

Key findings:

  • 1060 children met the criteria for a new diagnosis of EoE
  • Average annual incidence of EoE was 24 per 100,000 children; this is nearly double the previously reported rate 12.8 per 100,000 from Hamilton County, Ohio in 2003.
  • Prevalence of EoE was 118 per 100,000 children

The authors speculate on several factors that produced this increased incidence rate –all related to EoE risk factors:

  • Predominant non-Hispanic White population
  • High rates of atopy
  • Increased capture rate of their database
  • Also, the authors did NOT exclude PPI-responsive esophageal eosinophilia (which is a subtype of EoE and not a different disease

The authors note that “there is reason to believe that this [high incidence rate] is a conservative estimate:”

  • ~2% of pathology reports had 10-14 eos/hpf.  Further review of these cases would likely have identified some which have exceeded the >14 threshold
  • Some pediatric EoE cases are diagnosed by adult gastroenterologists who did not use the pathology databases

My take: This study shows high rates of EoE but comes as no surprise.  And, there are likely a large number of individuals with mild EoE which has not been diagnosed.  In my experience, families and physicians often overlook altered eating habits as related solely to behavior.  Useful questions to uncover dysphagia include the following: how long does it take your child to eat? does your child have to drink a lot of liquids when eating? does food get stuck frequently?

Related blog posts: