Can We Learn to Live With Germs Again?

Correction made on blog post on 5/12/21 Humira Dosing Guidelines. For Crohn’s induction >/= 40kg, there is not an 80mg dose on day 8, just 160mg day 1 and 80mg day 15. Blog post: Ustekinumab for Refractory Pediatric Ulcerative Colitis and Updated Adalimumab Dosing

————————————————————————

NY Times: Can We Learn to Live With Germs Again? (4/23/21)

An excerpt:

Almost everything we know about the microbiome is uncertain, including how our activities and environments influence its makeup...

Despite the now consensus recognition that air transmission, …we continue to annihilate every microbe in our midst, even though most are harmless…

Excessive hygiene practices, inappropriate antibiotic use and lifestyle changes such as distancing may weaken those [microbial] communities going forward in ways that promote sickness and imperil our immune systems. By sterilizing our bodies and spaces, they argue, we may be doing more harm than good…

Dr. Graham Rook, an emeritus professor of medical microbiology at University College London, likens the immune system to a computer. He says that the microbes we encounter in daily life — on other people and in our spaces — are the data that the immune system relies on to program and regulate its operations.

Deprived of these exposures, especially at the start of life, the immune system is prone to malfunction. The result can be allergies, asthma, autoimmune disorders, obesity, Type 2 diabetes and other chronic medical conditions...

 “Even before the pandemic, we know that half of antibiotic use was inappropriate.”…

For those who aren’t yet able to mix and mingle — and right now, that’s most of us — there are other ways to support microbial health. “If you want to do something proactive right now, I would put eating a healthy diet high on your list,” says Dr. Emeran Mayer… plant foods (legumes, greens, whole fruits, a variety of vegetables), as well as fermented foods, support the richness and diversity of the gut microbiome. So, too, does limiting one’s intake of processed and fast foods, especially those that contain added sugar…

Before the pandemic, only one of the top 10 causes of death in America — influenza — was attributable to an infectious disease that someone could “catch.” Nearly all the rest, such as heart disease and stroke, cancer, brain disease and diabetes, are associated with poor microbiome health or dysfunction.

Related blog posts:

World Obesity Day was March 4, 2021

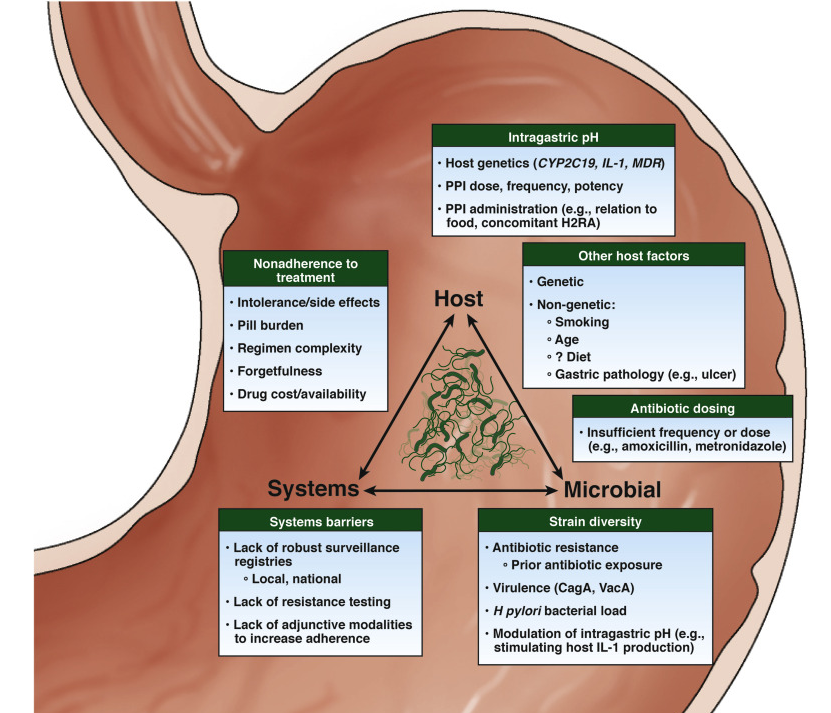
AGA: Best Practice Advice for Refractory H pylori

SC Shah et al. Gastroenterol 2021;  160: 1831-1841. Full text: AGA Clinical Practice Update on the Management of Refractory Helicobacter pylori Infection: Expert Review

Key recommendations:

  • Best Practice Advice 4: If bismuth quadruple therapy failed as a first-line treatment, shared decision making between providers and patients should guide selection between (a) levofloxacin- or rifabutin-based triple-therapy regimens with high-dose dual proton pump inhibitor (PPI) and amoxicillin, and (b) an alternative bismuth-containing quadruple therapy, as second-line options
  • Best Practice Advice 5: When using metronidazole-containing regimens, providers should consider adequate dosing of metronidazole (1.5–2 g daily in divided doses) with concomitant bismuth therapy, because this may improve eradication success rates irrespective of observed in vitro metronidazole resistance.
  • Best Practice Advice 6: In the absence of a history of anaphylaxis, penicillin allergy testing should be considered in a patient labeled as having this allergy in order to delist penicillin as an allergy and potentially enable its use. Amoxicillin should be used at a daily dose of at least 2 g divided 3 times per day or 4 times per day to avoid low trough levels.
  • Best Practice Advice 8:Longer treatment durations provide higher eradication success rates compared with shorter durations (eg, 14 days vs 7 days). Whenever appropriate, longer treatment durations should be selected for treating refractory H pylori infection.
  • Best Practice Advice 10: After 2 failed therapies with confirmed patient adherence, H pylori susceptibility testing should be considered to guide the selection of subsequent regimens.
  • Table 1 in report details specific regimens

Related blog posts:

Ustekinumab for Refractory Pediatric Ulcerative Colitis and Updated Adalimumab Dosing

As noted in previous blog posts (see below), adult guidelines for ulcerative colitis favor ustekinumab over vedolizumab for ulcerative colitis patients who have had anti-TNF therapy; recent pediatric guidelines appeared to do the opposite, possibly due to limited data with ustekinumab.

A recent study (J Dhaliwal et al. AP&T 2021; https://doi.org/10.1111/apt.16388. One‐year outcomes with ustekinumab therapy in infliximab‐refractory paediatric ulcerative colitis: a multicentre prospective study) provides prospective data on ustekinumab effectiveness when given to children with UC refractory to other biologics; n=25. Thanks to Ben Gold for this reference.

Key findings:

  •  All patients had failed prior infliximab therapy, and 12 (48%) also had failed vedolizumab.  Five patients discontinued ustekinumab after IV induction (four undergoing colectomy).
  • On intent to treat basis, 44% (n=11) achieved the primary endpoint of steroid‐free remission at week 52, including nine (69%) of 13 who previously treated with anti‐TNF only vs two (17%) of 12 who previously failed also by vedolizumab. Seven of 11 remitters met the criteria for endoscopic improvement.
  • Higher trough levels were not associated with a superior rate of clinical remission; the median (IQR) trough levels (μg/mL) were greater with q4 vs q8 weekly dosing (8.7 [4.6‐9.9] vs 3.8 [12.7‐4.8]) P = 0.02.
  • No adverse events were associated with therapy.

My take: Ustekinumab is a good option for pediatric patients with ulcerative colitis who are refractory to anti-TNF agents. More data are needed to help in positioning therapies.

Also, Humira (adalimumab) is now FDA-approved for children as young as 5 years with ulcerative colitis: FDA Approves Adalimumab as Treatment for Children With Ulcerative Colitis (2/25/21). “This approval is based on results from the phase 3, randomized, double-blind, multicenter ENVISION I (NCT02065557) study.” Abbvie has now updated their Humira dosing recommendations (Reference:  https://www.rxabbvie.com/pdf/humira.pdf). Thanks to Clair Talmadge for this update.

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

No Benefit of Combination Therapy with Ustekinumab or Vedolizumab

C Yzet et al. Clin Gastroenerol Hepatol 2021; 19: 668-679. Full Text: No Benefit of Concomitant Immunomodulator Therapy on Efficacy of Biologics That Are Not Tumor Necrosis Factor Antagonists in Patients With Inflammatory Bowel Diseases: A Meta-analysis

In a systematic review, key findings:

  • Combination therapy was not associated with better clinical outcomes in patients receiving vedolizumab (16 studies: OR, 0.84; 95% CI, 0.68–1.05; I2=13.9%; Q test P = .17); n= 933 and n=2378 with combination therapy and monotherapy, respectively
  • Combination therapy was not associated with better clinical outcomes in patients receiving ustekinumab (15 studies: OR, 1.1; 95% CI, 0.87–1.38; I2 = 11%; Q test P = .28); n=856 and n=1926 patients with combination therapy and monotherapy, respectively

Why don’t immunomodulators seem to help? “Unlike anti-TNF, prospective studies as well as post hoc analysis of randomized controlled trial consistently reported a low immunogenicity [with ustekinumab and vedolizumab]…all the prospective studies available to date have shown no impact of immunomodulator on the trough serum level of vedolizumab or ustekinumab.”

Limitation: patients treated with combination therapy in the included studies could be more severe

My take: “This meta-analysis found that overall the use of combination therapy in patients treated with vedolizumab or ustekinumab was not associated with a clinical benefit in comparison with the use of monotherapy.”

————————————————————————————————————————–

What Happens With Double Switches of Infliximab Products

N Trystram et al. Alimentary Pharmacology & Therapeutics, 01 Mar 2021, 53(8):887-899 Outcomes after double switching from originator Infliximab to biosimilar CT-P13 and biosimilar SB2 in patients with inflammatory bowel disease: a 12-month prospective cohort study.

Key findings:

  • Drug persistence was high (94.9%) after 54 weeks in cohort of 158 patients
  • Double switching from the originator Infliximab to CT-P13 and then to SB2 was associated with continued effectiveness; this study did not identify issues related to immunogenicity or safety of anti-TNF therapy after 54 weeks of follow-up.

My take: There is very limited data on repeated infliximab product changes; this small study did not identify any problems. Due to mandates from insurance, more frequent switching is likely to be more widespread and more definitive outcome data will emerge.

Abstract:

Related blog posts:

Combating Anti-Drug Antibodies with Immunomodulators in Pediatric IBD

RJ Colman et al. Inflamm Bowel Dis 2021; 27: 507-515. Favorable Outcomes and Anti-TNF Durability After Addition of an Immunomodulator for Anti-Drug Antibodies in Pediatric IBD Patients

In this retrospective review with 89 patients who developed antidrug antibodies (ADAs), the authors identified 30 who started an immunomodulator (IM) within 3 months of developing an ADA and compared with 59 who did not start an IM. The main IM used was methotrexate (n= 28, 93%)

Key findings:

  • 61 of the 89 patients (69%) had quiescent disease based on physician global assessment at their previous clinic visit
  • The initial anti-TNF was stopped shortly after ADA detection in 36% of the No-IM patients vs none of the IM patients. Thus, anti-TNF agents durability was prolonged in the IM group.
  • Dose intensification was also undertaken at the time of ADA detection: 25 (83%) of IM group and 28 (48%) of non-IM group.
  • At 12 months, steroid-free clinical and biochemical remission on the same anti-TNF occurred in 53.9% of the IM group vs 26.8% in the No-IM group (P = 0.025).
  • Drug levels rose higher (P = 0.003) and ADA levels fell farther (P = 0.037) in the IM group than in the No-IM group
  • Lower ADAs often improved without IM: An ADA level <329 ng/mL had a 76.2% sensitivity and an 83.3% specificity for ADA reversal without IM.

My take: If a patient develops a significantly elevated anti-drug antibody, addition of methotrexate/immunomodulator along with dose intensification increases the likelihood that the anti-TNF agent will continue to be effective.

Related blog posts:

Seeing More MALS Publications

Anecdotally, I’ve seen more publications recently regarding median arcuate ligament syndrome (MALS). A recent study (JP Moak et al. J Pediatr 2021; 231: 141-147. Median Arcuate Ligament Syndrome with Orthostatic Intolerance: Intermediate-Term Outcomes following Surgical Intervention) prospectively examines the outcomes in patients with MALS and with orthostatic intolerance (OI).

Background: MALS is generally considered after other more common conditions. Typical symptoms include abdominal pain after eating or exercise and often weight loss due to fear of eating. The pain is often positional and may improve with leaning forward. The diagnostic finding of celiac artery compression may be identified in many healthy individuals (10-24% of population); thus, only severe compression, which is seen in a small number, can result in symptomatic MALS.

In this study, the key findings:

  • 31 patients with both MALS and OI were identified from 2014-2019. Median f/u after surgery was 22 months.
  • Based on questionnaires, gastrointestinal symptoms of abdominal pain, nausea, and vomiting improved in 63% (P = .007), 53% (P = .040), and 62% (P = .014) of patients, respectively. 
  • Based on questionnaires, cardiovascular symptoms of dizziness, syncope, chest pain, and palpitations improved in 45% (P = not significant), 50% (P = not significant), 54% (P = .043), and 54% (P = .037) of patients, respectively.
  • Importantly, the authors could not demonstrate a “statistical relationship between a postoperative decrease in celiac artery Doppler velocity and improvement in clinical symptoms.”
  • In an effort to gauge for a potential post-surgical placebo effect, the authors determined the degree of improvement in musculoskeletal symptoms. There was a 24% improvement which was much less than the improvement in GI symptoms.

One useful feature of this article is that the authors explicitly state how they arrive at the diagnosis of MALS. They start with an abdominal ultrasound with doppler. Criteria for suspected MALS include supine celiac artery peak systolic velocity of >300 cm/s, celiac artery/aoritic peak systolic ratio of >3:1, neutral position celiac artery peak systolic velocity of >200 cm/s, and a change in the celiac artery deflection angle of >50 degrees between inspiration and expiration. If ultrasound is abnormal, the authors obtained an enhanced CT to image inspiratory and expiratory changes in the celiac artery deflection angle, the area of stenosis, poststenotic dilation, and the collateral blood vessels. If there are discrepancies between U/S and CT, a celiac arterial angiogram is obtained.

The authors conclude that there “were minimal improvements in neurologic or psychological symptoms after MALS surgery, despite their common occurrence among patients with POTS.”

My take: This study, in agreement with others, showed that about 60% had improvement in GI symptoms including pain, nausea and vomiting. In those with OI, most continued with impaired health. Overall, MALS as a clinical entity remains a ‘needle in a haystack.’

Related blog posts

“Let Food Be Thy Medicine” and Microbial Nourishment

‘Let food be thy medicine’ has been to Hippocrates.

A recent study (RY Chen et al. NEJM 2021; 384: 1517-1528. Full text A Microbiota-Directed Food Intervention for Undernourished Children) shows that foods that benefit the microbiome can help reverse malnutrition.

Background: “Children with these levels of malnutrition have defects in the development of their gut microbiota, which leaves them with microbial communities that appear to be younger than those of their healthy counterparts”

Methods: After completing studies in mice and piglets, the authors developed several microbiota-directed complementary food (MDCF) prototypes. They compared three of these formulations with an existing ready-to-use supplementary food (RUSF) in a 1-month-long, randomized, controlled trial involving children between the ages of 12 months and 18 months with moderate acute malnutrition who were living in an urban slum known as Mirpur, located in Dhaka, Bangladesh. A total of 118 children (59 in each study group) completed the intervention.

Key findings:

  • The rates of change in the weight-for-length and weight-for-age z scores are consistent with a benefit of MDCF-2 on growth over the course of the study, including the 1-month follow-up.
  • Receipt of MDCF-2 was linked to the magnitude of change in levels of 70 plasma proteins and of 21 associated bacterial taxa that were positively correlated with the weight-for-length z score (P<0.001 for comparisons of both protein and bacterial taxa). These proteins included mediators of bone growth and neurodevelopment.
  • The mean weekly change in the weight-for-length z score was 0.021 (95% confidence interval [CI], 0.014 to 0.029) in the MDCF-2 group and 0.010 (95% CI, 0.003 to 0.017) in the RUSF group, for a between-group difference of 0.011 (95% CI, 0.001 to 0.021).
  • The mean weekly change in the weight-for-age z score was 0.017 (95% CI, 0.012 to 0.022) in the MDCF-2 group and 0.010 (95% CI, 0.004 to 0.015) in the RUSF group, for a between-group difference of 0.008 (95% CI, 0.001 to 0.015).

My take: This study supports the notion that alterations in the microbiome need to be restored for healthy growth and development. Further studies are needed regarding the durability of the improvements induced by the MDCF and long-term outcomes.

4-14-4 Rule: More Biopsies Needed For Eosinophilic Esophagitis

Briefly noted: AL Krarup et al. Endoscopy. 2021 Jan;53(1):15-24. doi: 10.1055/a-1206-0852. Implementation of a biopsy protocol to improve detection of esophageal eosinophilia: a Danish registry-based study

In 2011, leaders of regional endoscopy units in Northern Denmark reached a consensus on a protocol to take eight biopsy samples in dysphagia patients (four biopsies from 4 cm and 14 cm above the esophagogastric junction-“4-14-4 rule”) regardless of the macroscopic appearance.

Key finding:  The number of patients with esophageal eosinophilia detected per year increased 50-fold after the protocol was implemented in 2011 (median of 1 [interquartile range 0-3] vs. 52 [47-56]; P < 0.001), and the number of biopsy samples per patient doubled (median 4 [4-5] vs. 8 [6-9]; P < 0.04). In total, there were 309 with esophageal eosinophilia identified from 2007-2017.

My take: This study provides more data that more biopsies help identify more cases of eosinophilic esophagitis.

Related blog posts:

  • Best Approach for Identifying Eosinophilic Esophagitis Prior studies have shown higher yield when taking 5 or 6 biopsies rather than fewer biopsies; thus, the location of biopsies may not be as important as the number of specimens. Also, prior studies have shown that having another pathologist review the slides can increase the yield by ~20%; this indicates that careful review of specimens by itself is helpful.  Perhaps, more specimen containers will increase the time that a pathologist reviews the biopsies.
  • Looking Twice for Eosinophilic Esophagitis

Real-World Experience with Proactive Therapeutic Drug Monitoring in Inflammatory Bowel Disease

A recent large retrospective pediatric study provides further evidence that therapeutic drug monitoring (TDM) in inflammatory bowel disease (IBD) results in better clinical outcomes. One of my partners, Chelly Dykes, is a coauthor and leads our ImproveCareNow team.

JL Lyles et al. Inflamm Bowel Dis 2021; 27: 482-492. Effect of a Practice-wide Anti-TNF Proactive Therapeutic Drug Monitoring Program on Outcomes in Pediatric Patients with Inflammatory Bowel Disease

This single center implemented a practice wide TDM approach in 2014. This study compared a historical pre-TDM group (n=108) to the TDM group (n=206). The primary outcome was sustained clinical remission (SCR22-52), defined as physician global assessment (PGA) of inactive from 22 to 52 weeks and off corticosteroids at 52 weeks. Key findings:

  • The SCR22-52 was achieved in 42% of pre-TDM and 59% of TDM patients (risk difference, 17.6%; 95% CI, 5.4–29%; P = 0.004)
  • The TDM group had an increased adjusted odds of achieving SCR22-52 (odds ratio, 2.03; 95% CI, 1.27–3.26; P = 0.003)
  • The adjusted risk of developing high titer antidrug antibodies (ADAs) was lower in the post-TDM group (hazard ratio, 0.18; 95% CI, 0.09–0.35; P < 0.001)
  • The SCBR22-52 (which was defined by normal CRP along with SCR22-52) was 24.7% in pre-TDM and 42.7% in the TDM group
  • The authors did not identify a significantly higher rate of anti-TNF cessation in either group
  • Only 12% of patients in their practice were receiving combination therapy

In the discussion, the authors review three pivotal studies which also support proactive TDM: TAXIT, TAILORIX, and PAILOT.

My take: While this was an observational study with historical controls, the findings are convincing that proactive TDM is helpful, particularly in patients who are not receiving combination therapy.

Related blog posts:

March 31, 2021