Postoperative Outcomes with Tofacitinib Following Colectomy for ASUC and Real-World Outcomes for Upadacitinib in Crohn’s Disease

C Larson et al. Clin Gastroenterol Hepatol 2025; 23: 2263-2271. Postoperative Outcomes in Tofacitinib-Treated Patients With Acute Severe Ulcerative Colitis Undergoing Colectomy

This  was a multicenter, retrospective, case-control study of patients hospitalized with ASUC who underwent colectomy, comparing patients treated with tofacitinib (n=41) prior to colectomy with infliximab-treated controls (n=68).

Key findings:

  • Compared with tofacitinib-treated patients, infliximab-treated patients had higher overall rates of overall (44 [64.7%] vs 13 [31.7%]; P = .002) and serious (19 [27.9%] vs 3 [12%]; P = .019) postoperative complications

My take: This study supports the safety of JAK inhibitor therapy for ASUC. It showed a significantly lower rate of overall postoperative complications in ASUC patients treated with tofacitinib compared with infliximab; the authors note that “these findings can likely be extrapolated to upadacitinib, a selective JAK inhibitor, given its similar mechanism of action.”

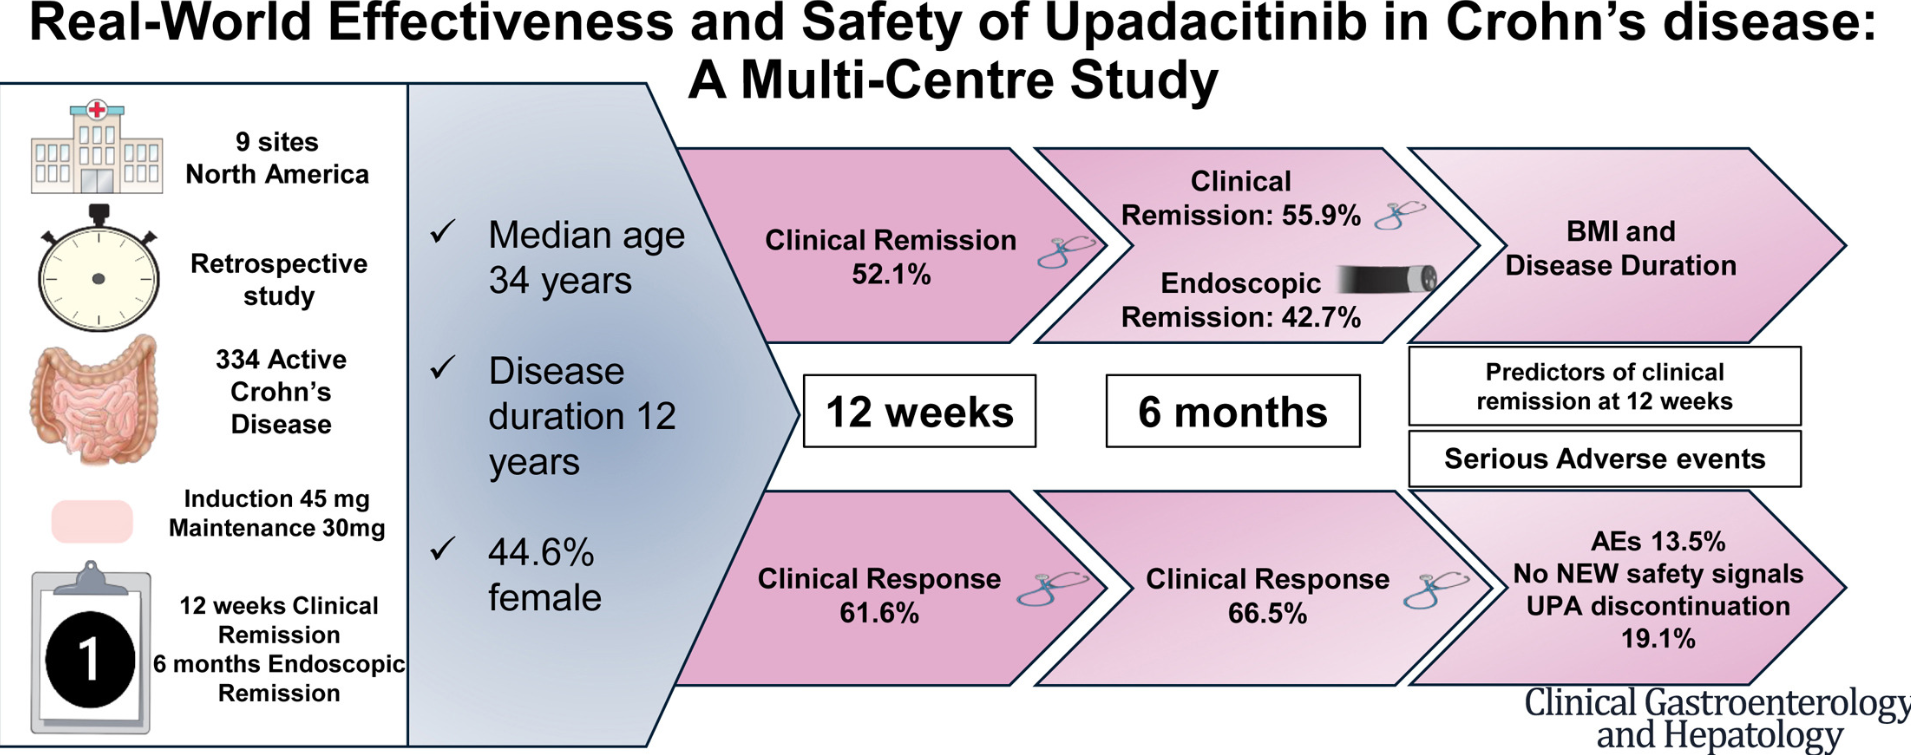
J Devi et al. Clin Gastroenterol Hepatol 2025; 23: 2281-2291. Open Access! Real-World Effectiveness and Safety of Upadacitinib in Crohn’s Disease: A Multicenter Study
Related blog posts:

Likelihood of Celiac Disease with Conflicting Serology Results

R Mandile et al. J Pediatr Gastroenterol Nutr. 2025;81:1482–1487. Advantages of anti-endomysial evaluation in children with low titers of anti-transglutaminase antibodies: A retrospective study

This was a single center retrospective study examining children (n=202) undergoing EGD (2022-2024) to evaluate for celiac. Among those with low anti-TTG IgA titers, Group 1 (n=25) was EMA negative and Group 2 (n=100) was EMA positive.

Key findings:

  • The finding of discordant serology (anti-transglutaminase [anti-TG] positive and EMA negative) is infrequent (12% cases, 25 out of 202), and all patients with discordant serology had anti-TG positive at low titer (<4 times the upper limit of normality).
  • Group 1 (N = 25) had a mean anti-TG titer of 1.86× ULN and villous atrophy (VA) in only 8% (2/25). Group 2 (N = 100) had VA in 35% (35/100)
Percentage of patients with villous atrophy between EMA positive and EMA negative children.

Discussion Points:

  • The diagnosis of CD still requires performing an EGD in at least half of the cases
  • This “study suggests that patients with low levels of anti-TG but EMA positive antibodies should anyway receive an EGDS in the next 6 months, since in around one-third of the cases a duodenal atrophy will be detected”
  • In those with low anti-TG but EMA negative, ” it could be reasonable to initially follow-up patients over time with clinical and serological monitoring (in particular of anti-TG titer), postponing the EGDS to a later stage, when the disease is more advanced and the chance of finding a concomitant VA (and thus the need to start a GFD) is higher”

My take: In patients with minimal symptoms and low level anti-TG, my strategy has been to follow with serological monitoring and if repeatedly abnormal, proceed with endoscopy. This study suggests that obtaining EMA early may influence choice to proceed earlier with endoscopy.

Related blog posts

How Procedure Volume Affects Pediatric Colonoscopy Success Rates

J Huang et al. J Pediatr Gastroenterol Nutr. 2025;81:1488–1495. Open Access! Numbers matter: How pediatric endoscopy quality varies with annual procedural volume

In this retrospective study with 985 ileocolonoscopies (2021-2024):

Methods:  “Quality indicators were compared across groups using Kruskal–Wallis analyses. Multivariate modeling was performed to identify variables predicting terminal ileal intubation and TIIR ≥ 85%.”

Key findings:

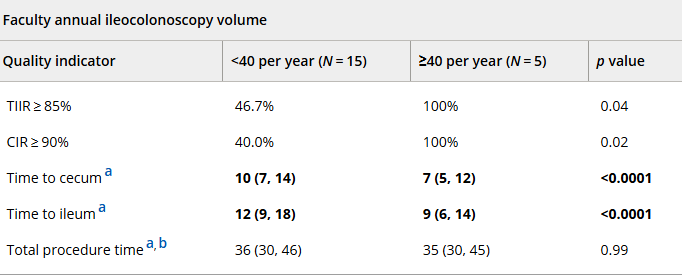
  • Overall ileal intubation rate (TIIR) and cecal intubation rate (CIR) were 86.3% and 91.6%, respectively
  • Annual procedure volume ( APV ≥ 40) was identified as predictive for TIIR ≥ 85% (p < 0.01)
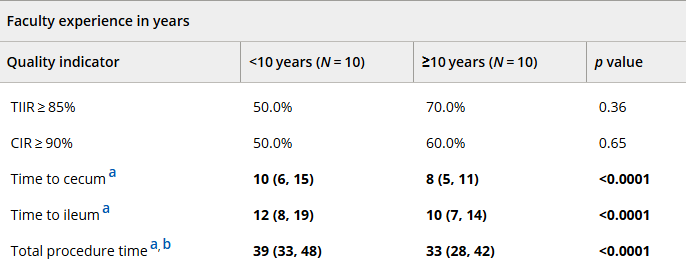
  • Faculty years’ experience (≥10 vs. <10 years) predicted shorter procedure duration (adjusted hazard ratio [confidence interval]: 1.40)
  • Adequate bowel prep was associated with higher TIIR (901% vs 76.7%), CIR (93.8% vs 86.0%) and shorter duration procedures (34 min vs 41 min)
a Presented as median (IQR) in minutes. b Includes only 967 combined esophagogastroduodenoscopy/ileocolonoscopy procedures without multiservice involvement.
Bolded text and numbers reflect results demonstrating statistical significance

My take (borrowed in part from the authors): The authors state that “our findings suggest that a threshold of 40 annual procedures [ileocolonoscopies] is necessary to maintain high pediatric endoscopic quality.” While I agree that adequate procedural volume is helpful, there is a great deal of individual variation/ability. Particularly if the endoscopist has a lower procedural volume, metrics like ileal intubation rate can be useful to assure good quality.

Related blog posts:

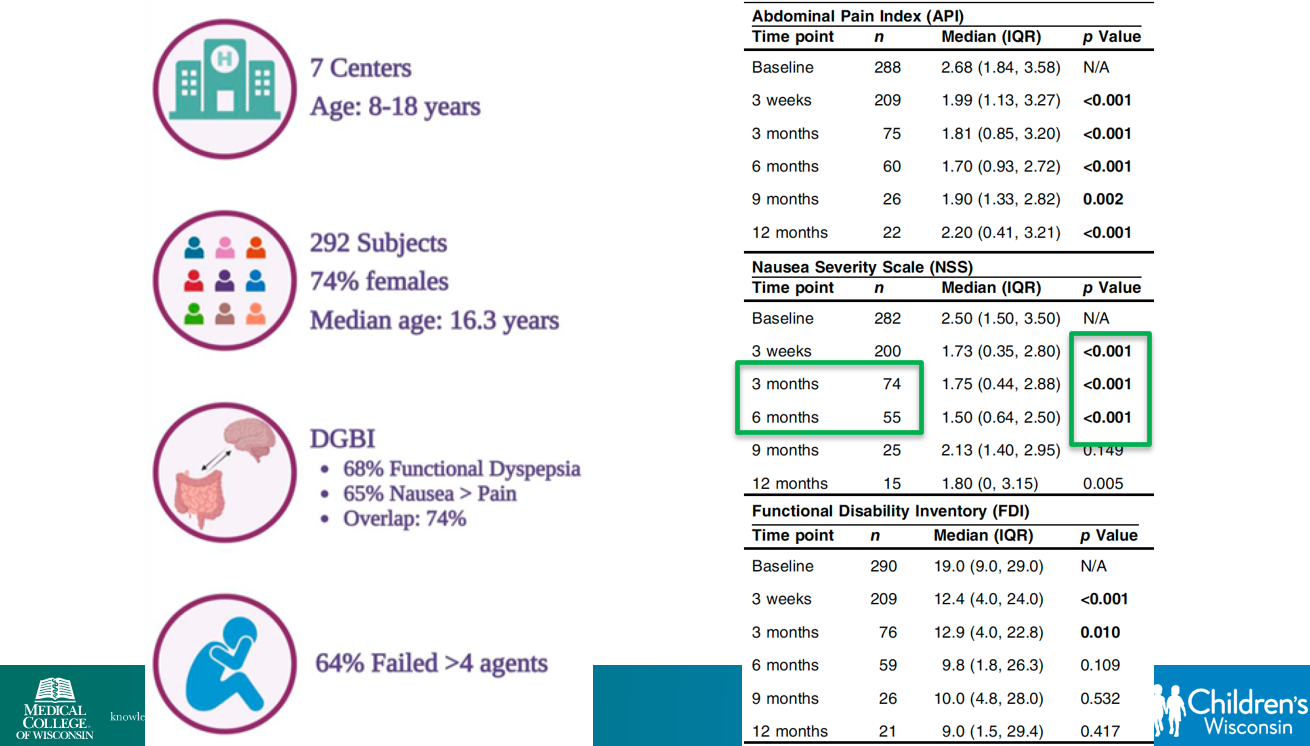
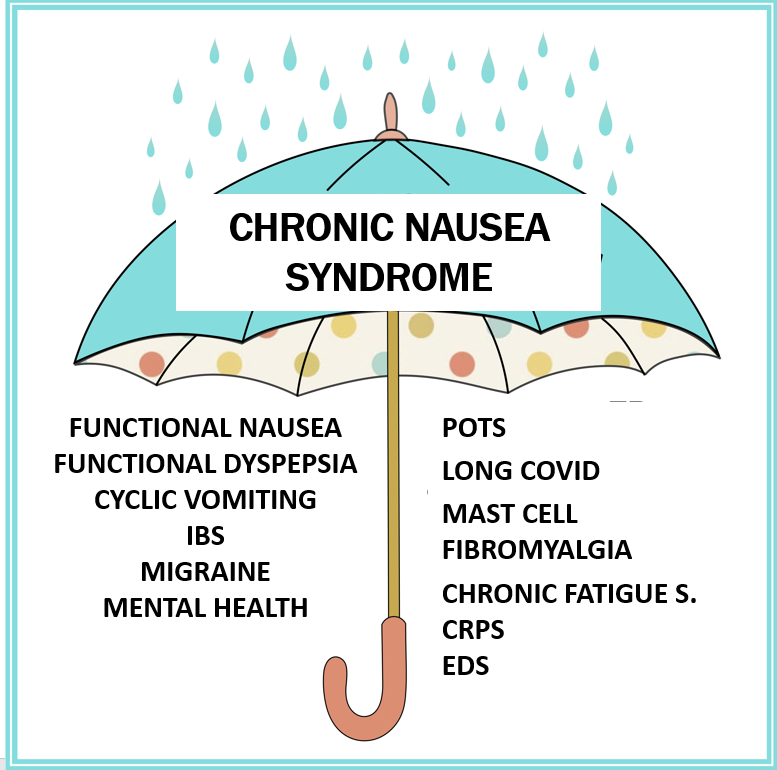
Dr. Katja Karrento: Chronic Nausea — Evidence of a Complex Syndrome

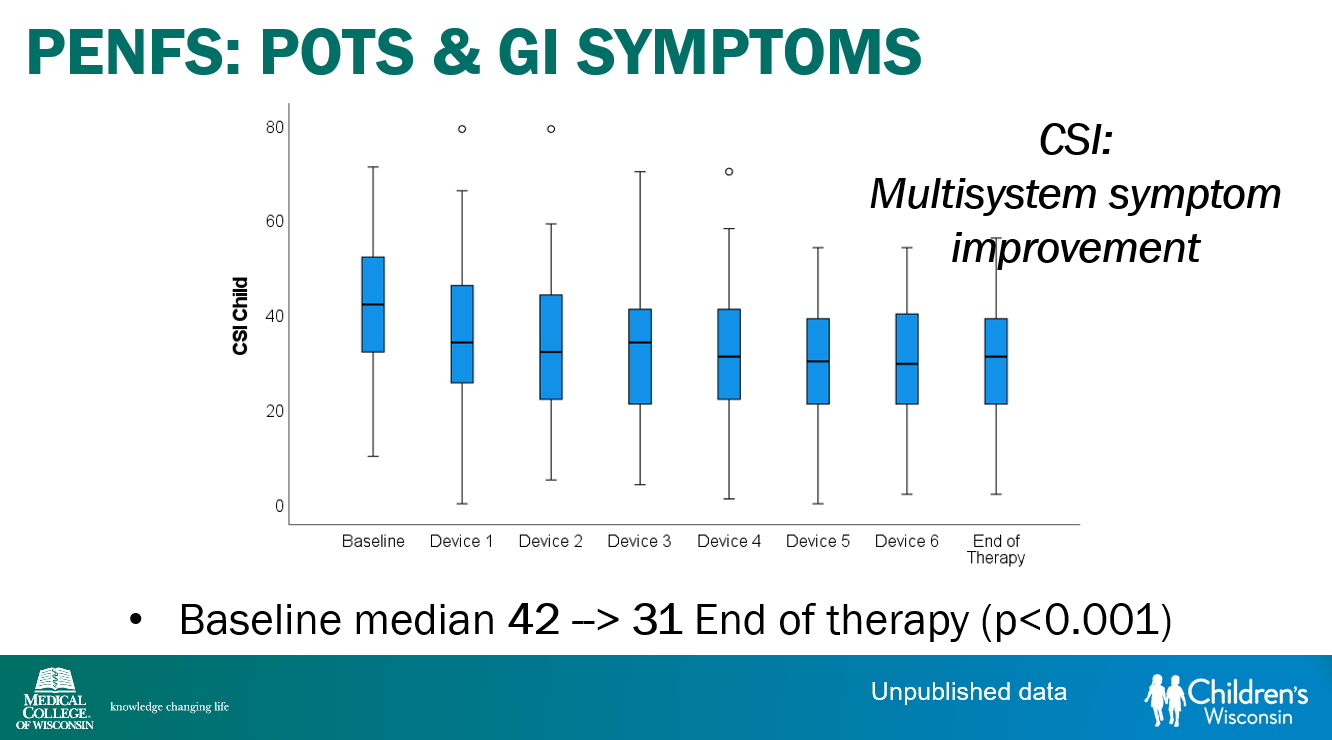
Recently, Dr. Katja Karrento gave our group a great update on chronic nausea.  My notes below may contain errors in transcription and in omission. Along with my notes, I have included many of her slides.

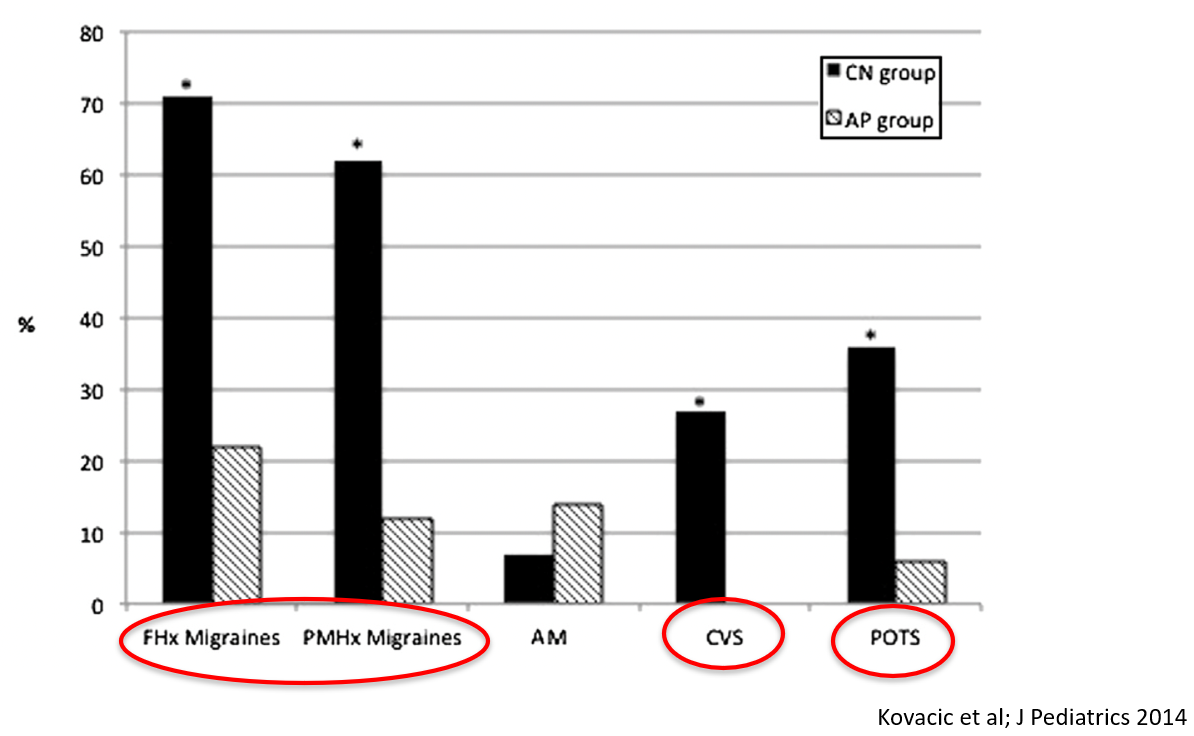
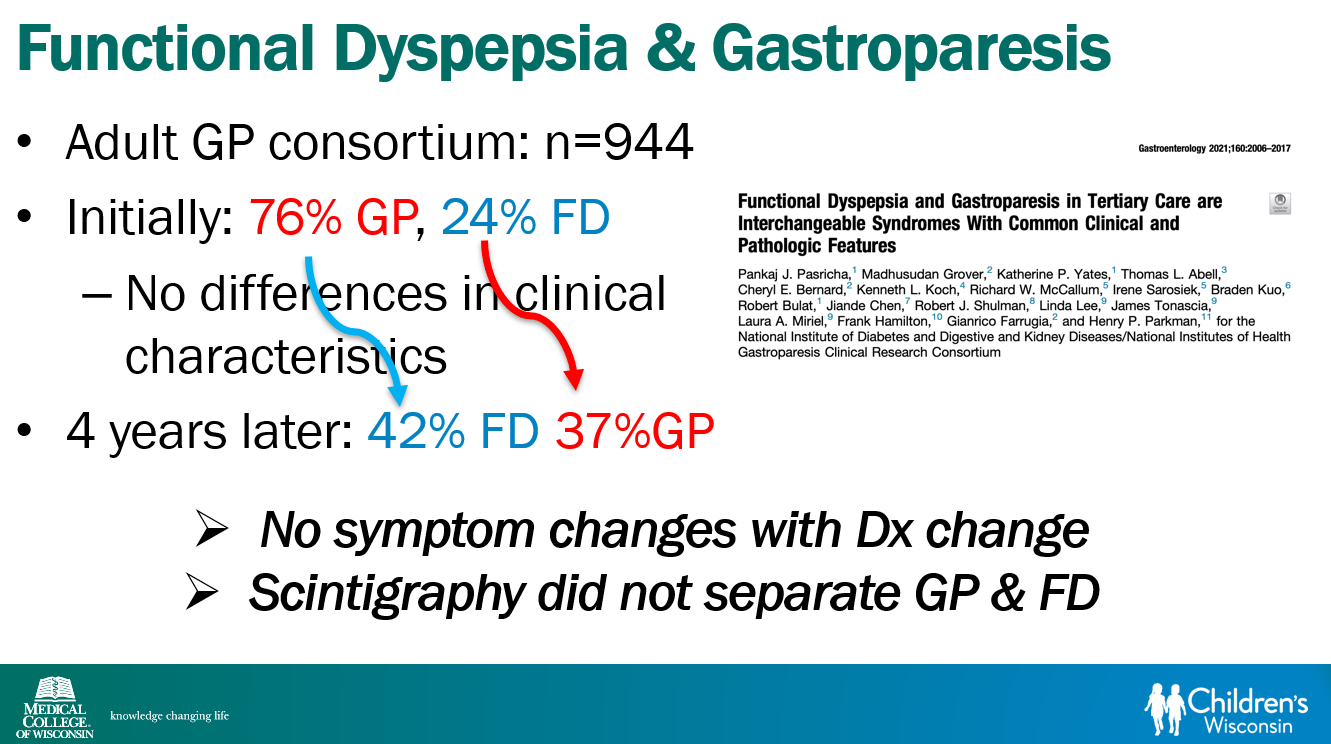
  • Recent research suggests that functional nausea overlaps with other DGBIs including functional dyspepsia, IBS and even gastroparesis 
  • Delayed gastric emptying is found in a subset of patients who meet criteria for functional nausea (though there are limitations of GE studies) 
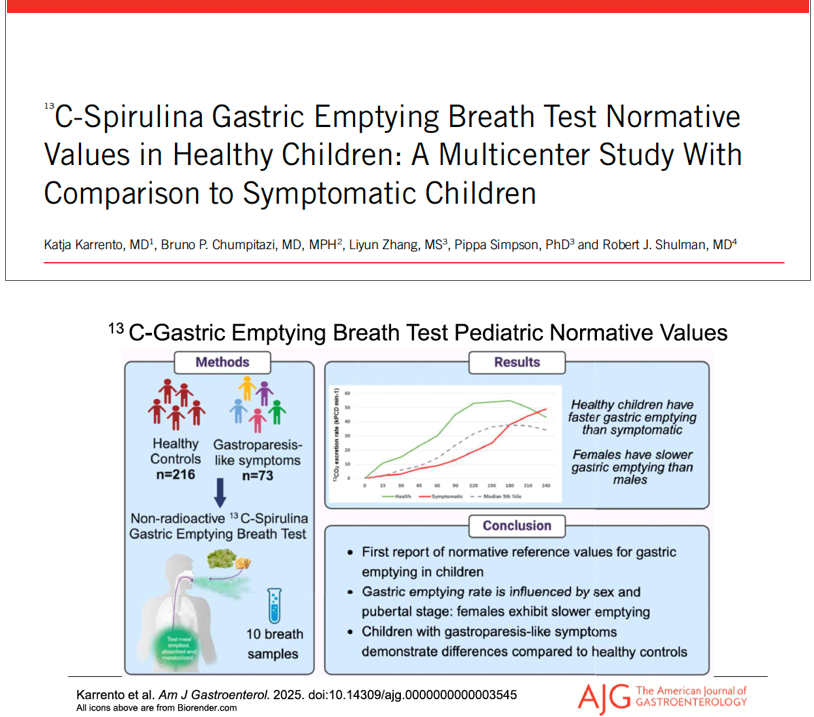
  • Emerging research on use of C13-Spirulina breath test to assess gastric emptying
  • Nausea is linked to disability more than stomach pain
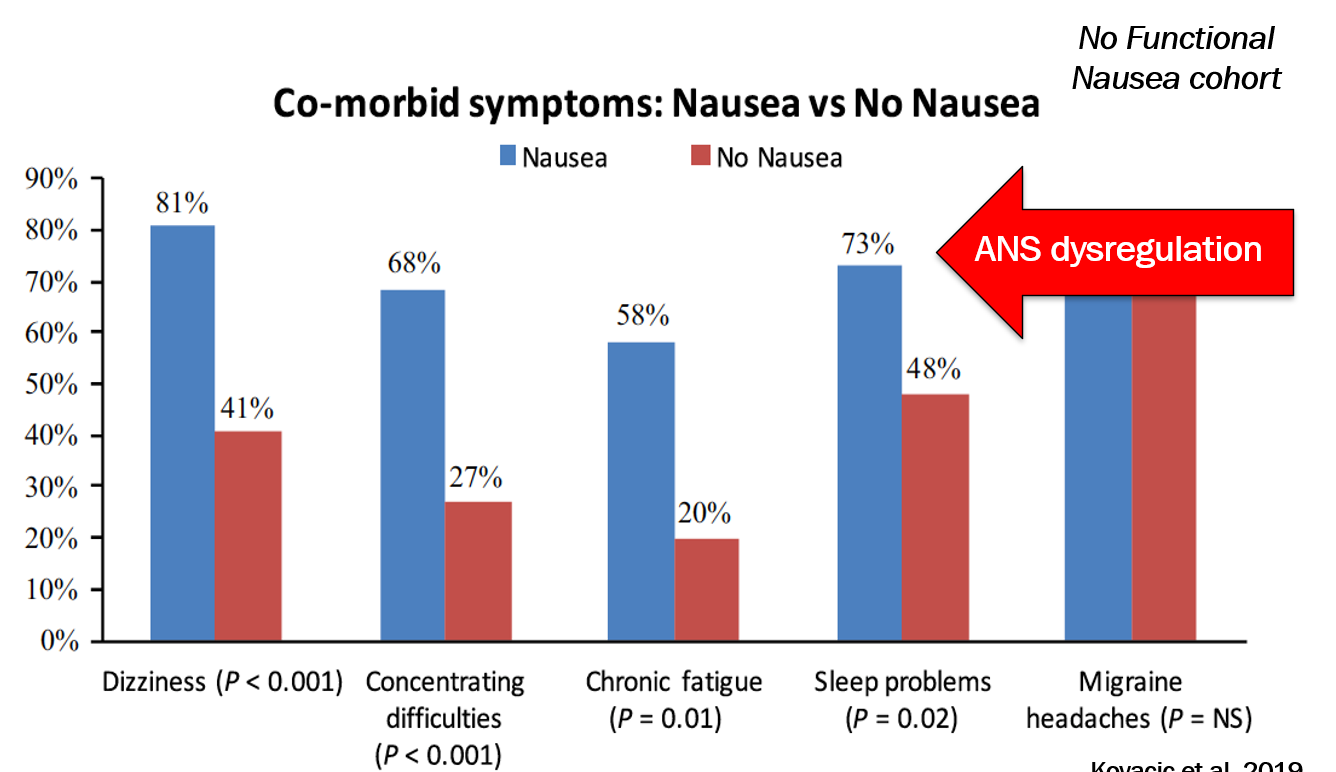
Among patients with DGBI, the presence of nausea was associated with increased comorbidities
  • Functional dyspepsia and gastroparesis overlap and may be part of same disorder
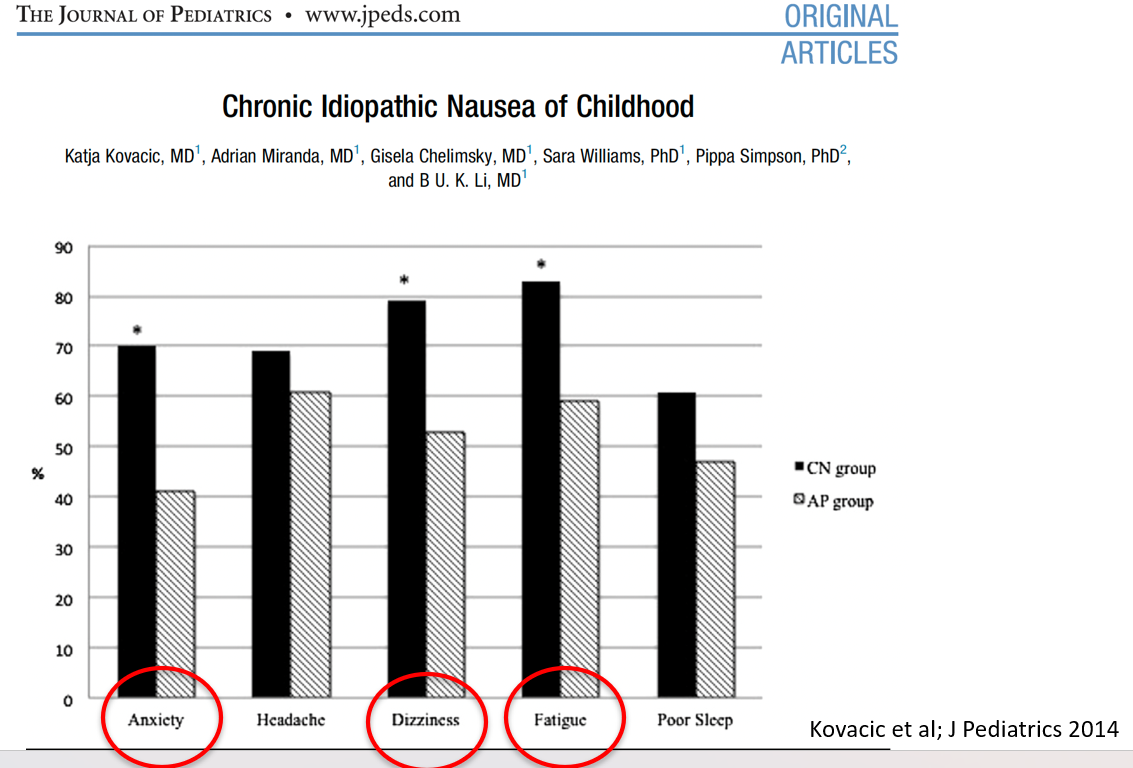
  • Nausea is associated with numerous extraintestinal comorbidities symptoms
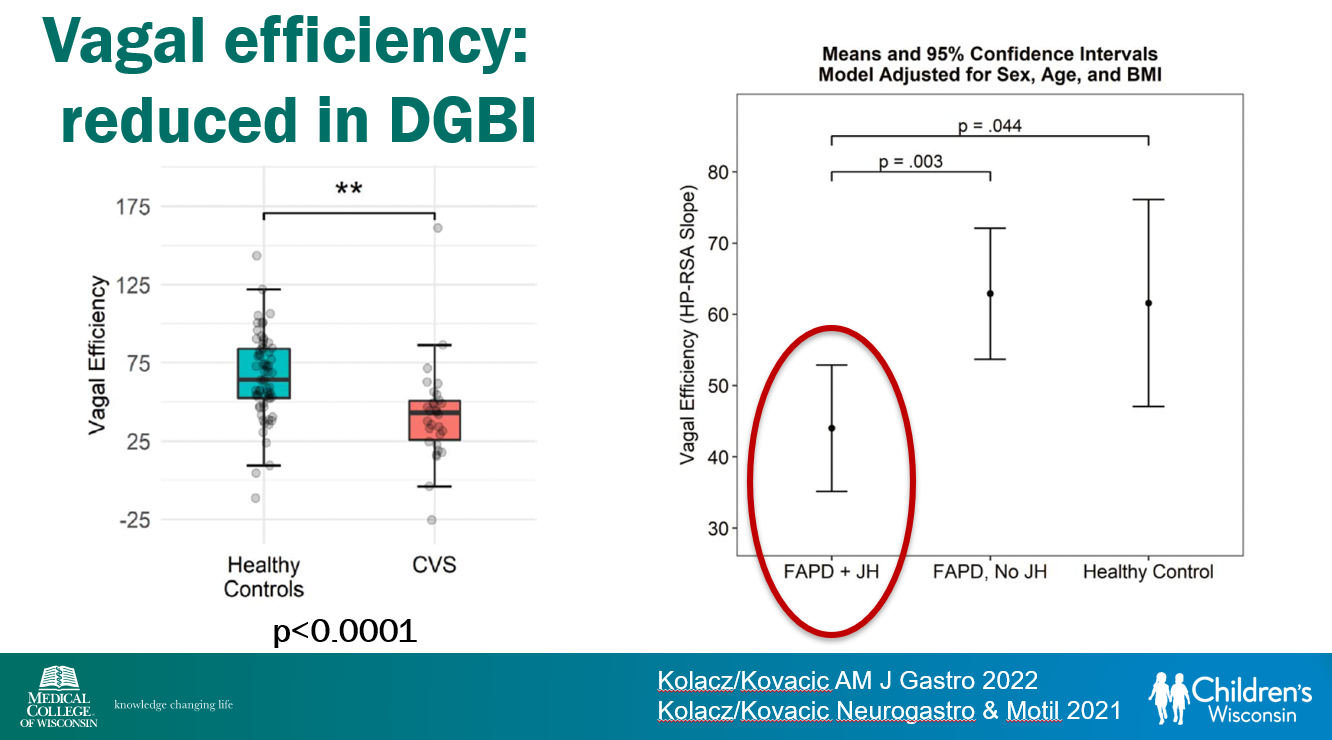
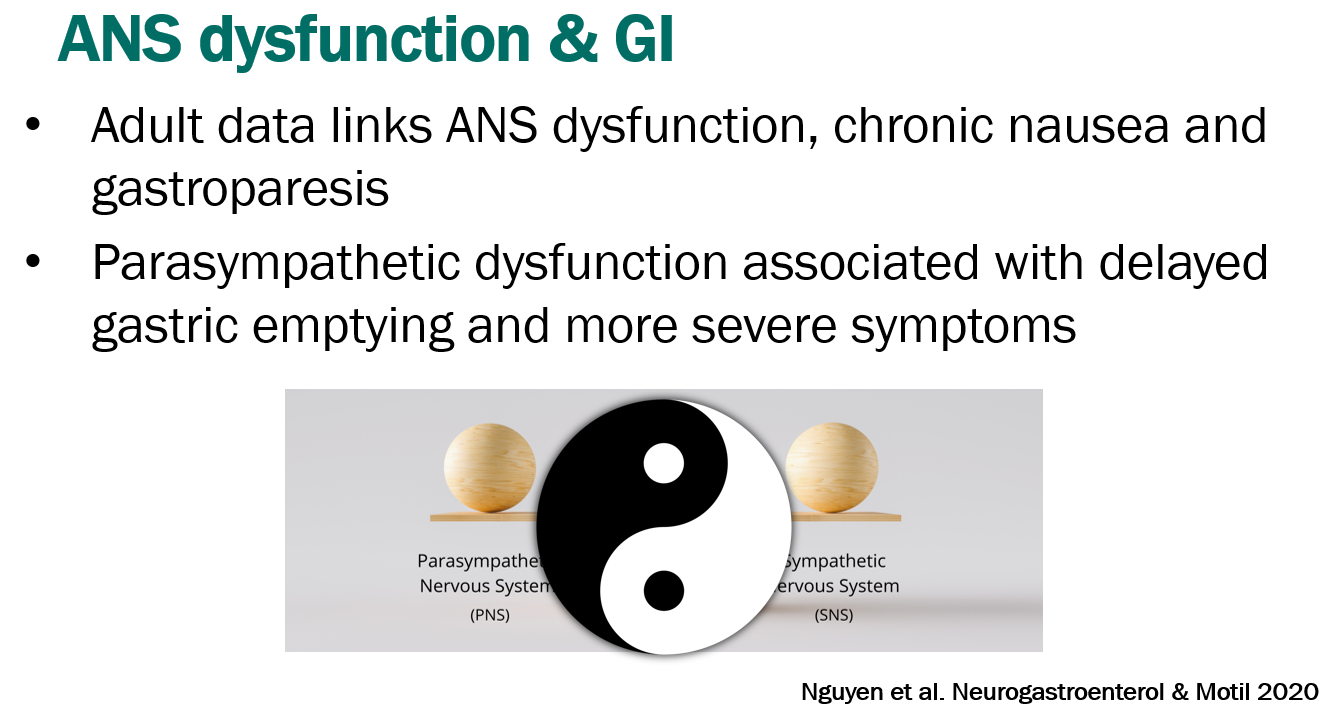
  • DGBIs are associated with abnormal autonomic nervous system signaling
  • Morning nausea, associated with being upright, is characteristic of dysautonomia. Other symptoms include ; palpitations, anxiety, sweating
  • POTS defined by increased HR >40 within 10 minutes with tilt test along with symptoms. In adults, increased HR>30 with symptoms.
  • A small (n=10) functional MRI study showed abnormal brain network organization in patients with nausea and orthostatic intolerance
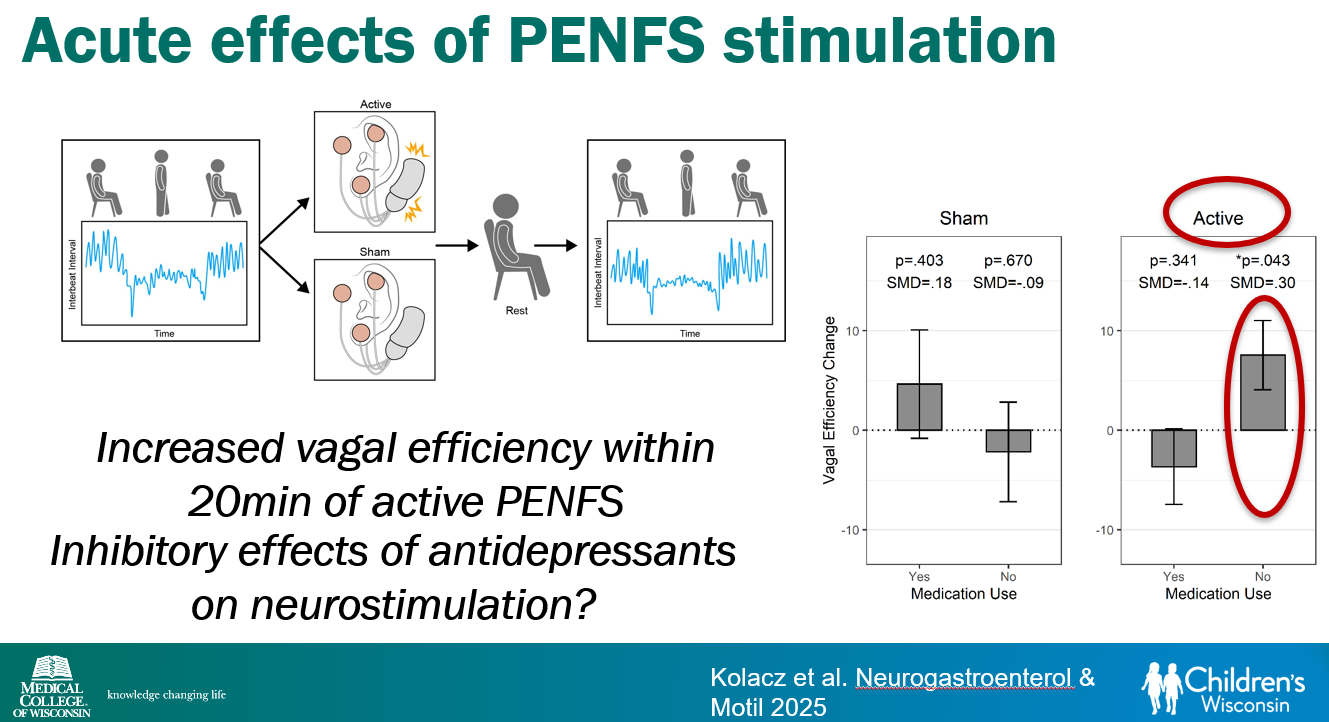
  • Vagal efficiency, which is decreased in subsets of DGBI, is a measure of the heart’s regulation of sympathetically-elicited tachycardia (or ‘..heart’s regulation of postural tachycardia’)
  • Cyclic vomiting is associated with autonomic nervous system alterations. In adolescence, the disorder often changes to chronic symptoms
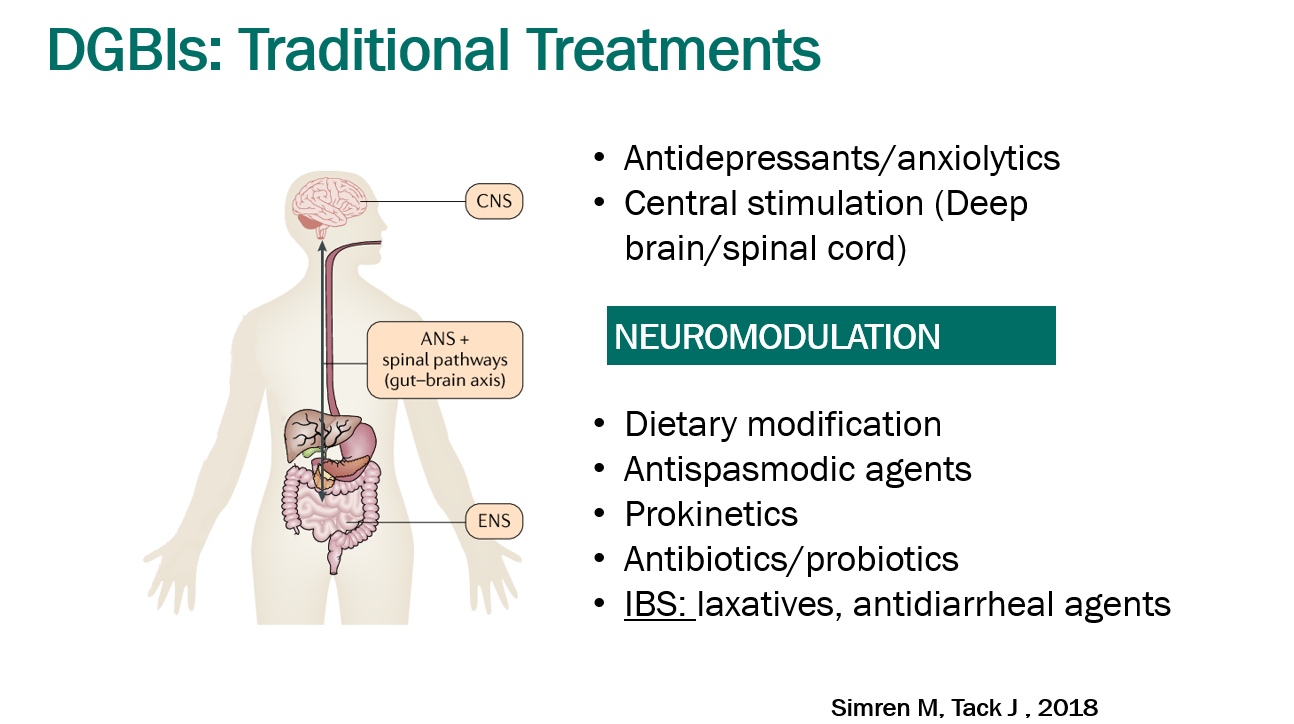
  • Treatment Advice: Explain early on the difficulty in treating these symptoms. Usually there is not a quick fix medicine. Lifestyle changes and coping are integral parts. Neuromodulation is likely more effective than other approaches
  • Dr. Karrento recommends The Dysautonomia Project to doctors and patients
  • Exercise is helpful for DGBIs
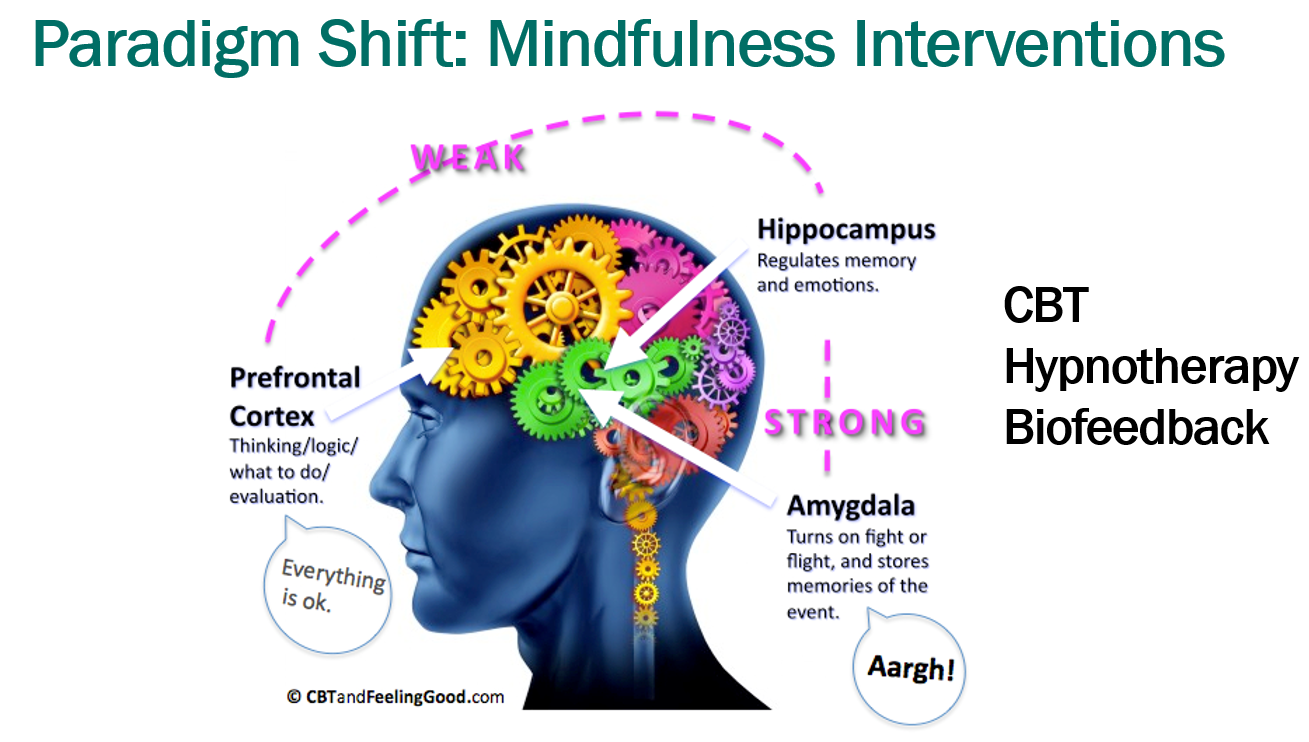
  • Mindfulness training may help: CBT, Hypnotherapy, Biofeedback
  • Potential treatments for autonomic dysfunction: Lifestyle changes, Neuromodulation, pharmacology: fludrocortisone, propranolol, pyridostigmine, midodrine
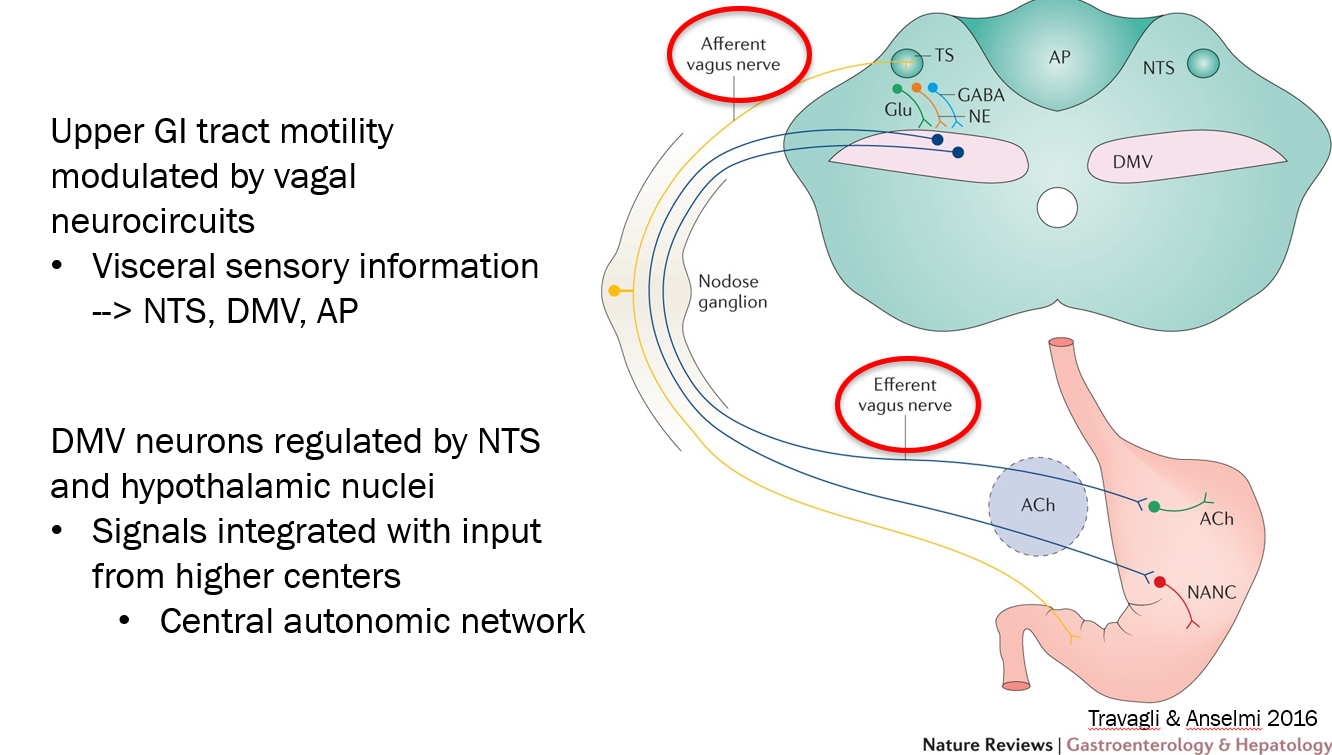
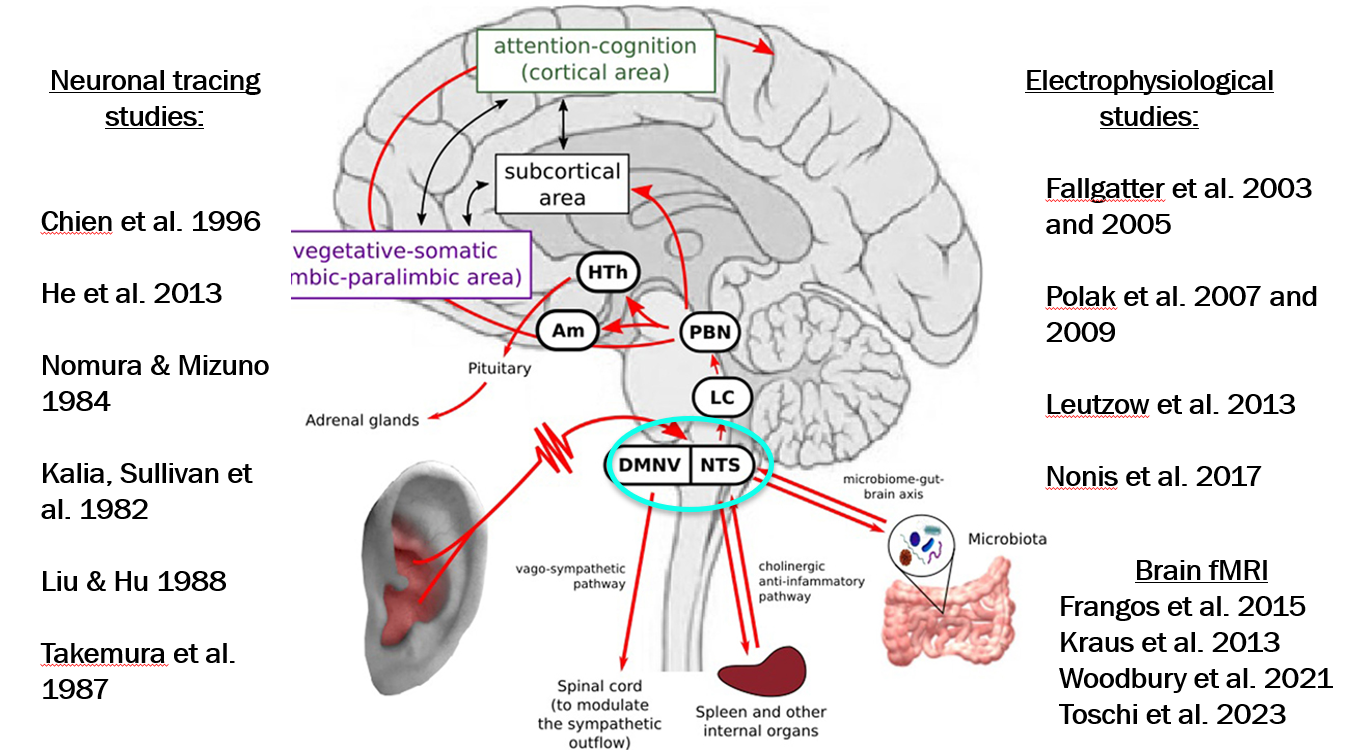
The auricular branch of the vagus projects to brainstem NTS. 95% of vagal afferent projections end up in NTS which in turn is directly and indirectly connected to a network of higher brain regions of the central
autonomic network
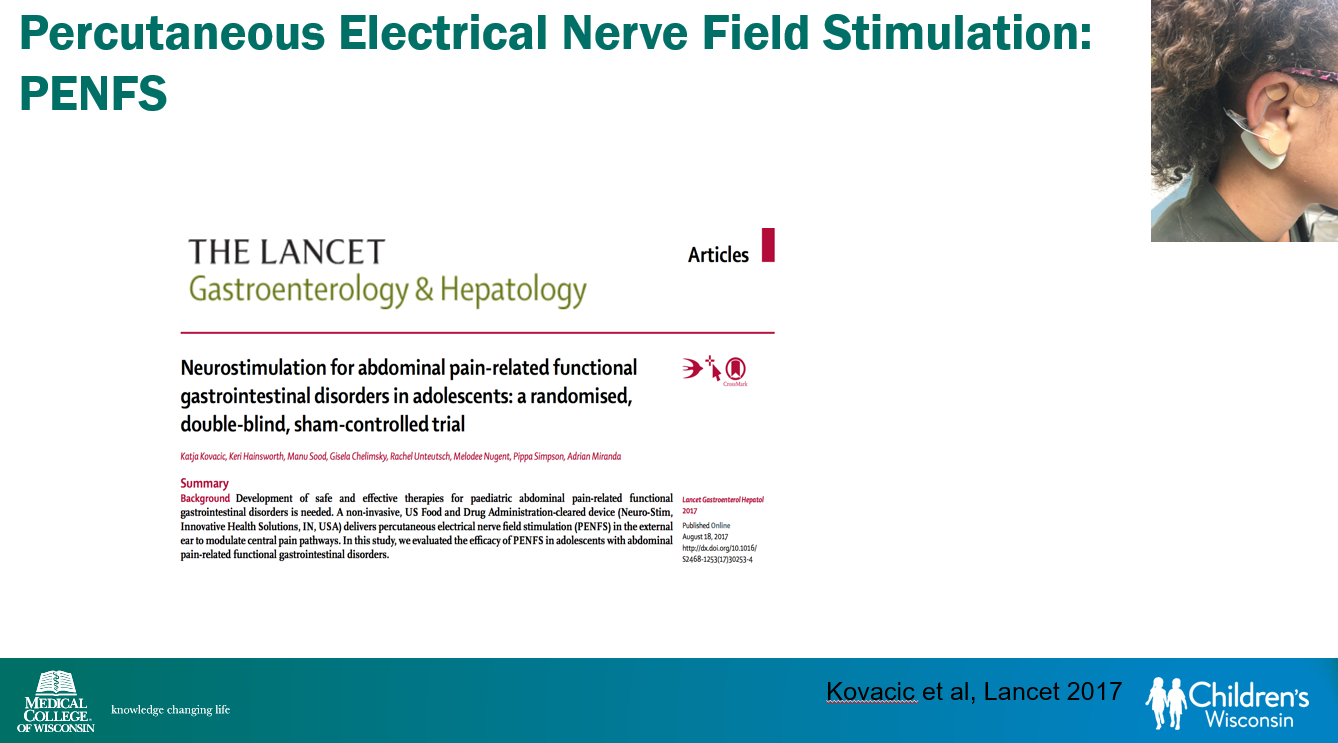
  • Percutaneous electrical nerve field stimulation (PENFS) can be useful in functional nausea and many DGBIs

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

COVID-19 Vaccine Effectiveness in Children 2024-2025

A Bendix et al. NBC News, 12/11/25: CDC study says Covid shots continue to protect healthy kids from severe illness

CDC Study: “From late August 2024 to early September 2025, the vaccines reduced the risk of Covid-related emergency room and urgent care visits by 76% among children ages 9 months to 4 years, and by 56% among children ages 5-17, according to the study”

Citation: Irving SA, Rowley EA, Chickery S, et al. Effectiveness of 2024–2025 COVID-19 Vaccines in Children in the United States — VISION, August 29, 2024–September 2, 2025. MMWR Morb Mortal Wkly Rep 2025;74:607–614. DOI: http://dx.doi.org/10.15585/mmwr.mm7440a1

Open Access! Effectiveness of 2024–2025 COVID-19 Vaccines in Children in the United States — VISION, August 29, 2024–September 2, 2025

Effects of NIH Funding Cuts on Clinical Trials

PBS News 11/17/25: NIH cuts affected over 74,000 patients enrolled in experiments, report finds

An excerpt:

Between the end of February and mid-August, funding ceased for 383 studies that were testing treatments for conditions including cancer, heart disease and brain disease. The cuts disproportionately impacted efforts to tackle infectious diseases like the flu, pneumonia and COVID-19, researchers found…

More broadly, the lost research harms patients who could have benefited from a possible new treatment, researchers said in the report published Monday in the journal JAMA Internal Medicine…

“The whole purpose of these clinical trials is to generate evidence on what works and doesn’t work in medicine,” said study co-author Anupam B. Jena with Harvard Medical School. Researchers counted 11,008 NIH-funded studies during the study period. Of those, 1 in 30 lost funding.

Related blog posts:

Outcomes of Hematopoietic Stem Cell Transplant in Monogenic Inflammatory Bowel Disease

A Baccarella et al. Clinical Gastroenterology and Hepatology; 2025; 23: 2242 – 2252. Open Access! Outcomes of Allogeneic Hematopoietic Stem Cell Transplant in Monogenic Inflammatory Bowel Disease

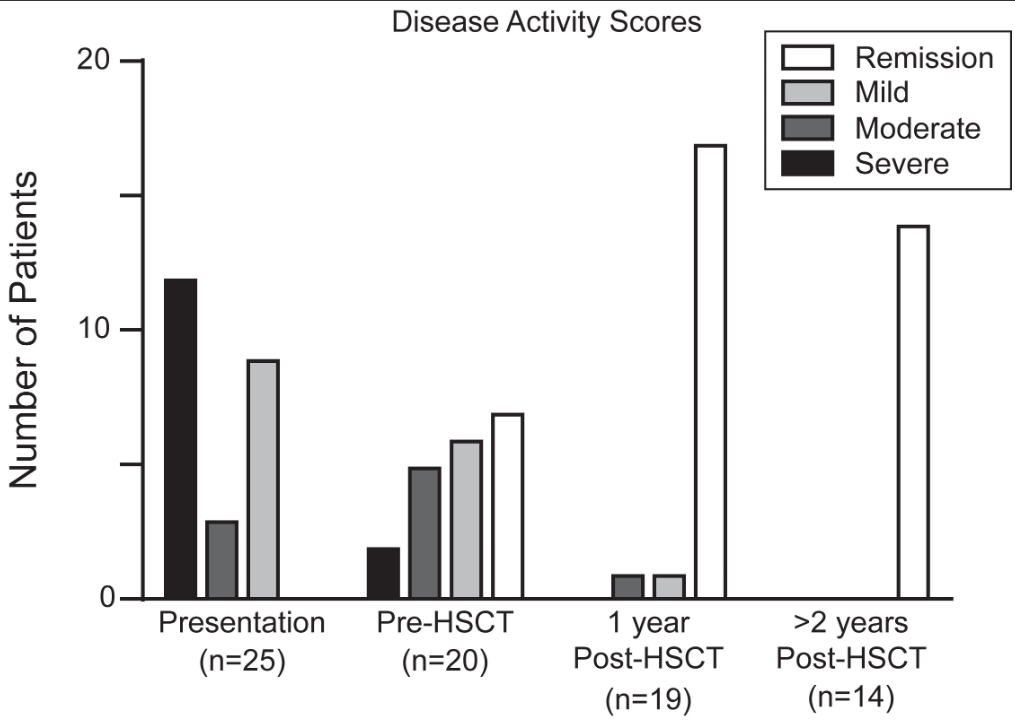
This was a retrospective single-center (CHOP) study of 25 children with monogenic IBD who underwent Hematopoietic Stem Cell Transplant (HSCT) (2012-2022).

Key findings:

  • Seventy-two percent of patients had Crohn’s Disease, and 28% were classified as IBD-unspecified. Ninety-two percent of patients had VEO-IBD, 56% presenting under age 1
  • At most recent follow-up, 92% of patients achieved sustained medication-free remission of IBD and 60% with prior ostomy underwent re-anastomosis. There was 100% survival at a median follow-up of 3 years
  • There was significant improvement in growth, hospital days, and severe infections
Disease activity scores at the time of IBD presentation, immediately prior to transplant, 1-year post-transplant, and at most recent follow up if ≥2 years since transplant.

Discussion points:

  • “Delay of HSCT with the goal of obtaining remission of IBD prior to transplant may prove to be determinantal, as outcomes of HSCT are in general improved for younger patients,20 and medical remission is often unattainable for more severe forms of monogenic IBD. Within our cohort, 32% of patients had moderate or severe disease at the time of transplant despite medical optimization. None of these patients developed intestinal GVHD, which was a rare event in our total cohort”
  • “HSCT is not without risk, and complications occurred in our cohort, at rates typical of other IEI cohorts”
  • “The selection of patients who would benefit from HSCT requires multidisciplinary discussion.”

With regard to patient selection, one item that was not included in the discussion was the one patient excluded from their analysis who had a TTC7A gene defect. In the results section, it was explained that the patient with “TTC7A was subsequently excluded as transplant was performed for the indication of SCID alone, rather than treatment of intestinal disease.” More discussion on this point is merited as many centers would NOT have a patient with TTC7A undergo HCST specifically because it cannot correct the underlying bowel disease.

Also, it was noted that one patient with CTLA4 deficiency had undergone HSCT prior to the discovery of the genetic defect. With the more widespread use of genetic testing available now, this discovery may have obviated the need for HSCT as treatment with abatacept is typically effective.

My take: Overall, the authors present impressive results for HSCT for monogenic IBD and strengthen the need for genetic testing in those with early onset disease and those refractory to treatment.

Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Long-Term Treatment of Eosinophilic Esophagitis with Budesonide

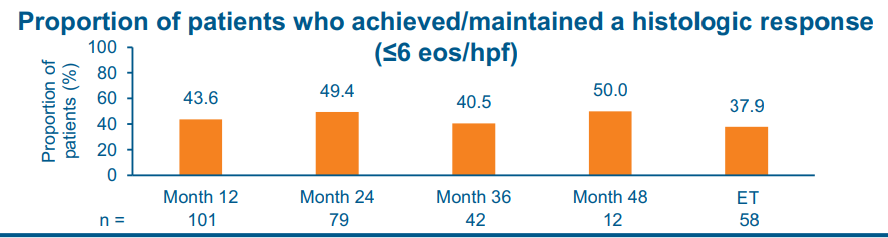
The study by Dellon et al was a 4-year, phase 3, open-label study in patients with EoE who completed up to 52 weeks of BOS therapy (Budesonide oral suspension 2 mg 2/day) in 2 preceding phase 3 studies.

Key findings:

  • At month 48 of treatment, 50.0% and 58.3% of patients achieved/maintained a histologic response (< or =6 and <15 eosinophils per high-power field, respectively)

Safety:

  • Treatment-emergent adverse events (TEAEs) occurred in 76.3% of patients; most were mild/moderate in severity and unrelated to study drug.
  • The most frequently reported BOS-related TEAEs included abnormal adrenocorticotropic hormone stimulation test results (8.4%, 11/131; number of events [m] [ 12) and adrenal insufficiency (2.3%, 3/131; m [ 3). Esophageal candidiasis occurred in 3.1% of patients (4/131)

The study by Biedermann et al explored the use of an orodipsersible tablet for EoE up to 3 years in patients who achieved remission during a 12-week induction. This tablet is not available in the U.S.

Key findings:

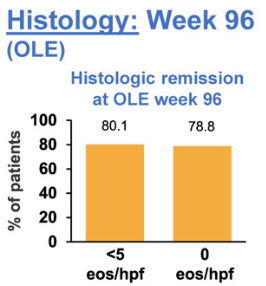
  • At week 96, 80.1% of patients were in histologic remission, defined as peak eosinophils per high-power field of <5, at week 96 vs 91.8% at open label extension baseline
  • No new safety concerns were observed across 96 weeks of treatment. Suspected symptomatic candidiasis occurred at similar rates to prior BOT studies and was predominantly mild and resolved with treatment

My take: The pharmaceutical budesonide suspension, Eohilia, is labelled by the FDA for use as a 12 week treatment course. Since EoE is a chronic disease, 12 weeks is insufficient. These long-term studies provide data that may address this shortcoming.

Related blog posts:

How to Best Use Steroids for Inflammatory Bowel Disease

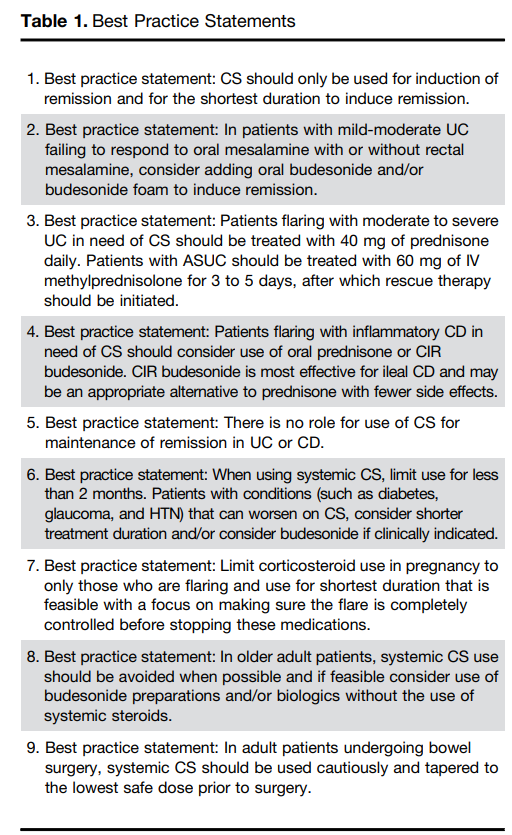
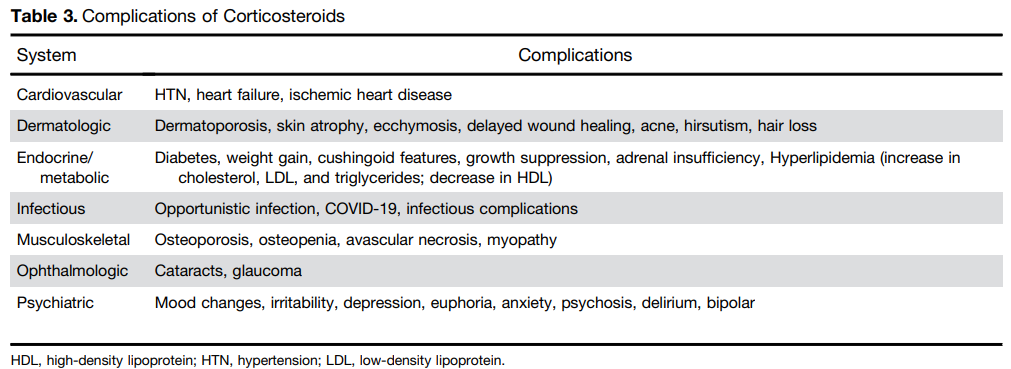
JD Feuerstein et al. Clin Gastroenterol Hepatol 2025; 23: 2068-2082. Open Access! Appropriate Use and Complications of Corticosteroids in Inflammatory Bowel Disease: A Comprehensive Review

Steroids are commonly used and misused for inflammatory bowel disease. This article reviews best practices, steroid formulations/dosing, and potential complications.

  • For moderate to severe ulcerative colitis (in adults), the authors recommend treatment with 40 mg of prednisone daily. Patients with ASUC (acute severe ulcerative colitis) should be treated with 60 mg of IV methylprednisolone for 3 to 5 days, after which rescue therapy should be initiated
  • Use of budesonide is recommended as an option for many clinical situations to minimize steroid adverse effects. These situations include mild-moderate UC failing to respond to mesalamine, ileal CD and older patients
  • Postoperative complications: “In the postoperative period, patients treated with CS had a higher risk of both infectious complications (aOR, 3.69; 95% CI, 1.24–10.97) and major infectious complications (aOR, 5.54; 95% CI, 1.12–27.26) [Abrerra et al].135  Subramanian pooled data from 7 studies showing that preoperative CS use is associated with increased postoperative complications (OR, 1.41; 95% CI, 1.07–1.87) as well as infectious complications.

The authors note that corticosteroids “remain widely available and are an effective short-term option for induction of remission in patients with active UC or inflammatory CD. However, their well-described and significant safety profile warrants proactive strategies to limit their use through non-systemic formulations, short-term exposures, steroid-sparing maintenance options, and most recently, complete steroid avoidance strategies.”

My take: Continuing steroids when they are not effective prior to potential surgery (eg. ASUC) remains a frequent problem. Sometimes, it is difficult to know it they are helping some.

An Esophageal Coin with Moth Eaten Appearance

M Hook et al. JPGN 2025; DOI: 10.1002/jpn3.70221. Esophageal coin with moth eaten appearance: A cause for caution

This case report describes a penny ingestion by a 10 yo with autism that likely happened nine months before attempted retrieval. The coin was not able to be retrieved due to stricturing but was advanced into the stomach (the authors note advancement into duodenum would be better); in addition, there was an esophageal diverticulum that was identified likely secondary to the caustic damage.

In the discussion, the authors note that “the ‘moth eaten’ appearance is a rare finding that indicates prolonged foreign body retention and unforeseen mucosal injury…It is specific to post-1982 pennies, composed of 97.5% zinc.4 Hydrochloric acid exposure dissolves zinc, forming caustic zinc chloride.”

My take: Future generations will not see this radiologic finding. For now, if this finding is seen, it likely indicates a more difficult foreign body removal.

Related blog posts:

Ref: https://www.pbs.org/newshour/nation/u-s-mint-in-philadelphia-to-press-final-penny-as-the-1-cent-coin-gets-canceled