This retrospective cohort included 270 adolescents/young adults who attended an intensive, interdisciplinary pain treatment program, including 135 youth with functional abdominal pain (FAP) and an age- and gender-matched control group with a primary pain diagnosis of chronic headache.
Key findings:
Limitation of this study: The population attending this intensive pain program is NOT representative of typical outpatient setting
A history of an eating disorder was more common with FAP than in those with chronic headache (15.4% vs. 5.9%)
In this cohort, patients with FAP compared to patients with chronic headache had higher rates of prior exclusion diets to manage their symptoms (46% vs. 22%, p = 0.007), and prior requirement enteral or parenteral feeds (18% vs. 1.5%, p = 0.001)
The study found a significant association between a history of exclusion diets and meeting criteria for ARFID. “With regard to ARFID, the prevalence of patients in both groups who met diagnostic criteria (FAP: 50%; chronic headache: 36%) was also significantly higher than estimates from the general school-aged population (3%)”
Patients with FAP were also more likely than patients with chronic headache to be diagnosed with postural orthostatic tachycardia syndrome ([POTS]; 46% vs. 30%) and have a history of food allergies or intolerances (43% vs. 25%)
Significantly more adolescents with FAP (n = 68) than chronic headache (n = 45) had lost 4.5 kg or more, p = 0.004
My take: Most treatments for FAP, including dietary treatment, have some inherent risks. In patients placed on dietary therapies, screening and/or discussing the risk of dietary restriction need to be considered.
Background: “A subset of patients with SNI may not tolerate enteral feeding due to gastrointestinal (GI) issues, resulting in pain, feeding intolerance, and malnutrition, despite the absence of primary digestive disorders.3–5 In these cases, home parenteral nutrition (HPN) can be considered…The decision to initiate HPN in children with SNI is challenging. The lack of evidence, absence of definitive etiologies for GI symptoms, known complications, and psychosocial burden of HPN create ethical hurdles for clinicians when partnering with caregivers in this decision.12, 18, 20“
Methods: This was a retrospective review from Canada’s largest tertiary care pediatric hospital of all children with severe neurologic impairment (SNI, n=18) and primary digestive disorders (n=187), where home parenteral nutrition (HPN) was initiated between January 2010 and September 2023.
Key findings:
Compared with the primary digestive disorders group, children with SNI with non-primary digestive disorders were less likely to achieve enteral autonomy (p < 0.0001).
There was a higher mortality rate were observed in the SNI cohort, though this did not reach statistical significance (22% in SNI group vs. 8% those primary digestive disorders; p = 0.09). Only one death in the SNI group was attributed to HPN-related complications.
“CRBSI rate of 1.7 per 1000 catheter days among the SNI and non-primary digestive disorder population on HPN indicates no increased risk in this population. Similarly, our observed rate for catheter-related mechanical problems (occlusion, leakage, dislodgement) of 4.3 per 1000 catheter days is similar to the report of 3.4 per 1000 catheter-days in children with intestinal failure on HPN.28 “
In the discussion, the authors note that “HPN initiation was found to not influence utilization acute care hospital resources, with no difference in ED visits, hospitalizations, ICU admissions or days in hospital in the year before initiating HPN, compared to the following year…the high usage of acute care that is characteristic of this population persisted, suggesting that HPN also did not meaningfully decrease health care use for these children.”
My take: HPN may improve symptoms and nutrition in some children with SNI. This comes with a substantial burden. Prior to starting PN, careful exploration of long-term goals is essential. The decision to use of PN is fraught with ethical issues in children with SNI and could be considered a ‘heroic’ measure; some families will opt for palliative care.
Using the ImproveCareNow prospective registry, the authors analyzed a total of 285,913 visits from 32,497 patients aged ≤ 21 years.
Key findings:
The occurrence of erythema nodousm (EN) was 1.57% and the occurrence of pyoderma gangrenosum (PG) was 0.90%. Co-occurrence of EN and PG was reported in 0.30% patients.
Both EN and PG were associated (p < 0.0001) with worse intestinal disease, lower remission, higher inflammatory markers, and extraintestinal manifestations (EIMs) arthritis and uveitis.
Limitations: “imperfect and incomplete data entry that may introduce bias. However, due to the extensive longitudinal data, we expect any bias to be minimal.”
My take: This study clarifies how common these dermatologic findings occur in pediatric patients with IBD. Prompt recognition of these disorders is important. Recently, our group cared for a 20 yo patient with inadequately-treated PG by multiple internal medicine physicians; this led to prolonged hospitalization.
This retrospective review of 24 children with tethered cord syndrome (TCS) (50% female) who had ARM testing (median age at ARM 6.0 years). 19 children had prior TCS repair.
Key findings:
No significant differences in ARM parameters were found between children who had detethering surgery before ARM and children with functional constipation (FC). The children with TCS did have lower resting pressures though this was attributed to most having their ARM while under GA for concurrent procedures. The resting pressures were still normal.
Among the 14 children who also had a colonic manometry (CM) performed (13/14 after detethering surgery), there were no significant differences in colonic motility were found between children with a history of TCS and children with FC.
My take: The vast majority of children with a history of TCS (following detethering) should be treated akin to children with functional constipation.
Impression, Sunrise by Claude Monet at National Gallery of Art (Washington, D.C.)
A D’Agrosa et al. J Pediatr 2024; 273; DOI: 10.1016/j.jpeds.2024.114129. Cefdinir Stool
This 5 month old infant was brought to ED due to diarrhea and dark stools for 2 weeks. She had completed cefdinir for a UTI.
Cefdinir may cause red or maroon stools when administered with iron or products that contain iron, such as infant formula. This typically occurs within two days of antibiotic administration.
My take: Familiarity with this reaction is helpful to avoid extensive evaluations. Also, it is worthwhile to keep in mind that false-positive testing with guaiac testing is common (up to 34% in healthy infants).
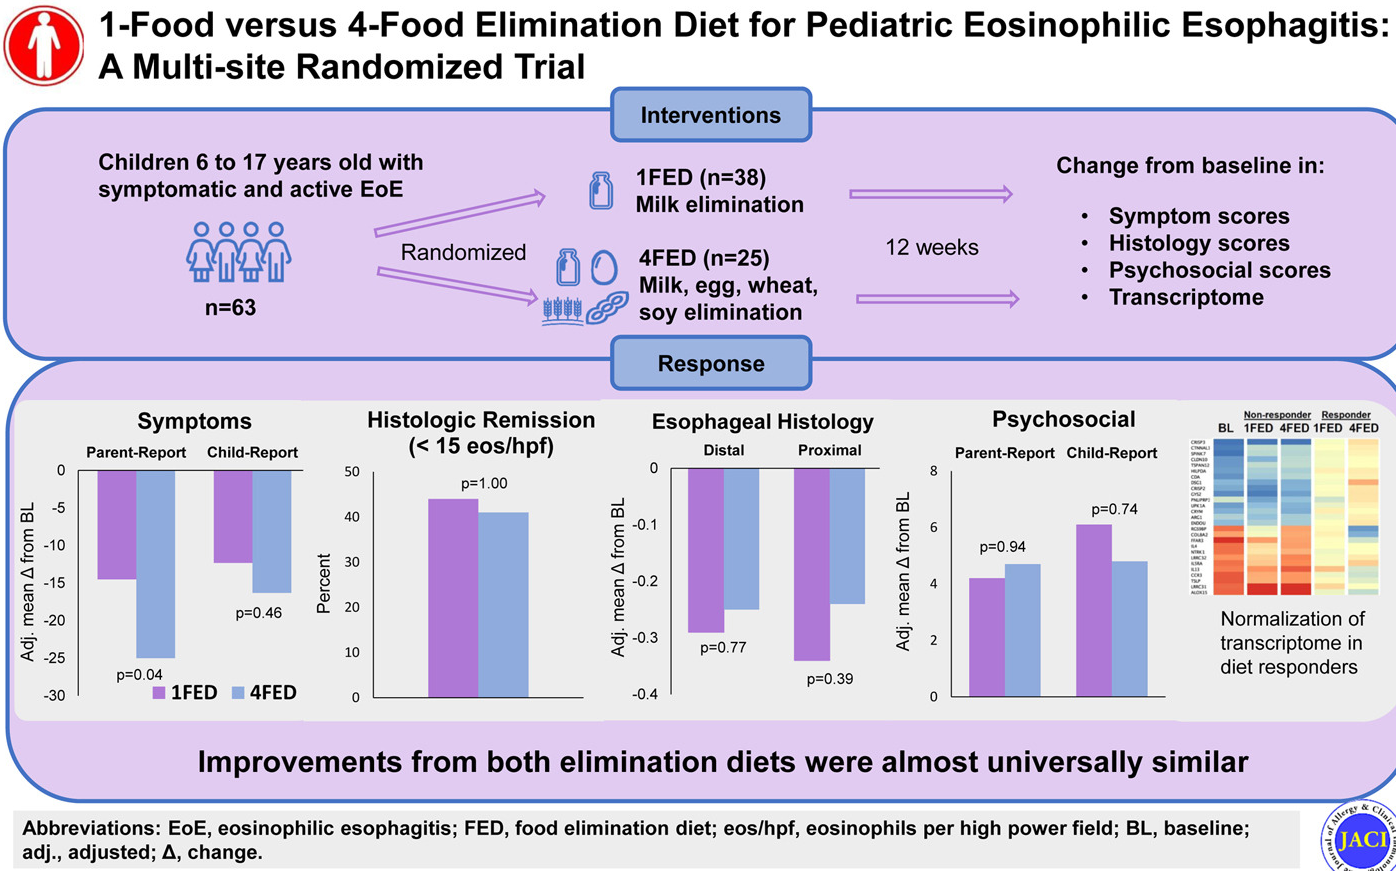
Methods: This was a multisite, randomized comparative efficacy trial of a 1-food (milk) elimination diet (1FED) versus 4-food (milk, egg, wheat, soy) elimination diet (4FED) in pediatric EoE. The 12-week study enrolled 63 patients (6-17 yrs). Primary end point was symptom improvement by Pediatric Eosinophilic Esophagitis Symptom Score (PEESS).
Key findings:
1FED vs 4FED: The mean PEESS improved −25.0 versus −14.5 (P = .04), but remission rates (41% vs 44%; P = 1.00), histology scoring system (−0.25 vs −0.29; P = .77), endoscopic reference score (−1.10 vs −0.58; P = .47), and QoL scores were similar between groups.
The 4FED withdrawal rate (32%) exceeded that of 1FED (11%) (P = .0496).
My take: A 4FED diet is difficult to maintain. In this 12 week study, more than 30% of patients withdrew from the 4FED diet. In addition, dairy elimination alone resulted in similar response rates.
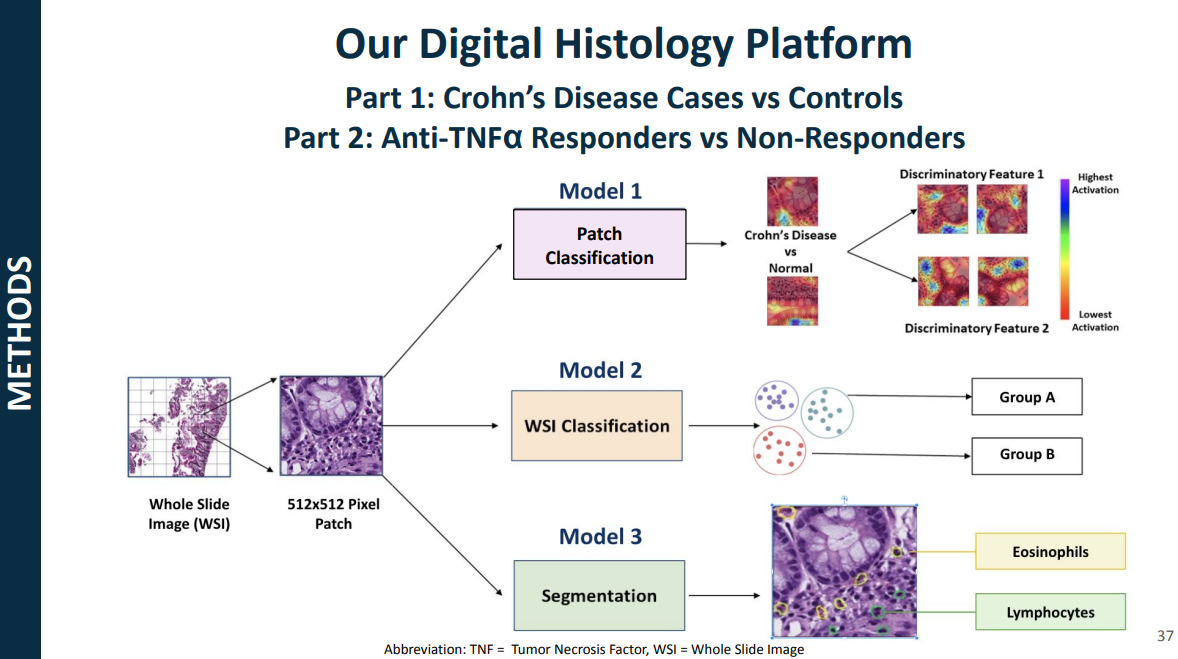
Recently, Dr. Sana Syed gave Children’s Healthcare of Atlanta Grand Rounds. She provided an excellent update on the development of artificial intelligence (AI) to select targeted therapies for pediatric gastroenterology diseases. My notes below may contain errors in transcription and in omission. Along with my notes, I have included many of her slides.
Key points:
One of the goals of using AI is to identify the right therapy at the time of diagnosis. Currently, diseases like eosinophilic esophagitis (EoE) and Crohn’s disease have multiple treatment options. However, many patients do not respond to first-line treatments; many develop complications due to not responding to treatment.
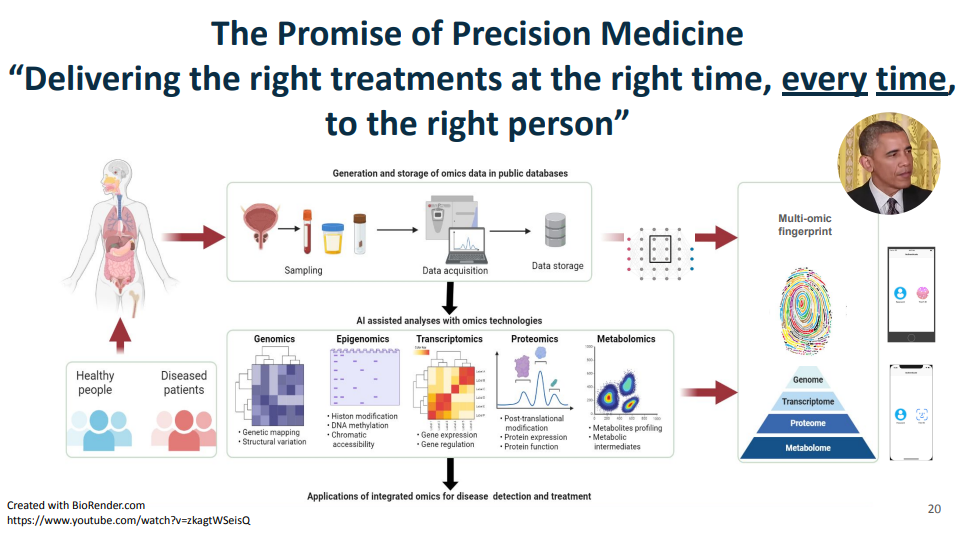
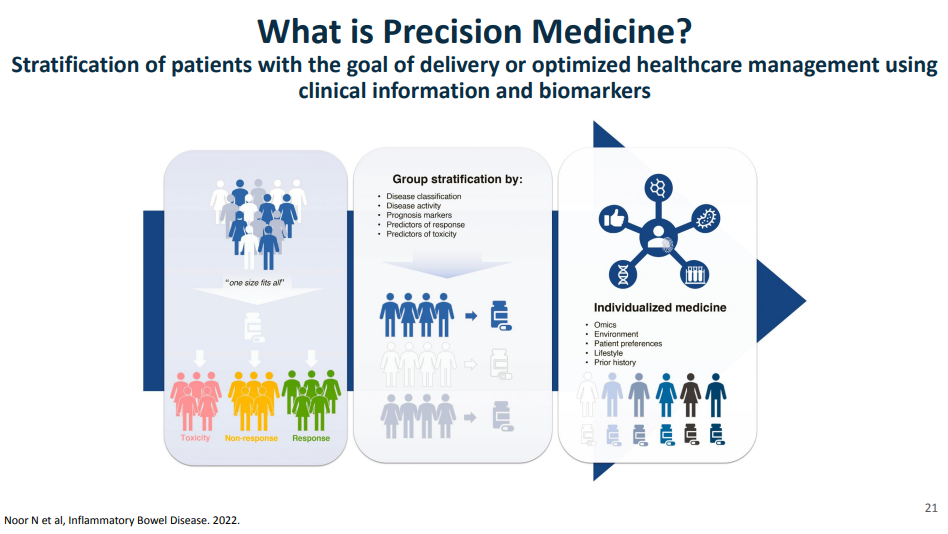
Currently we are lacking adequate biomarkers for individualized therapy. AI has the potential to sort through massive amounts of data (histologic, genetic, pharmacokinetics, transcriptome, metabolomics, etc) to allow for precision therapy.
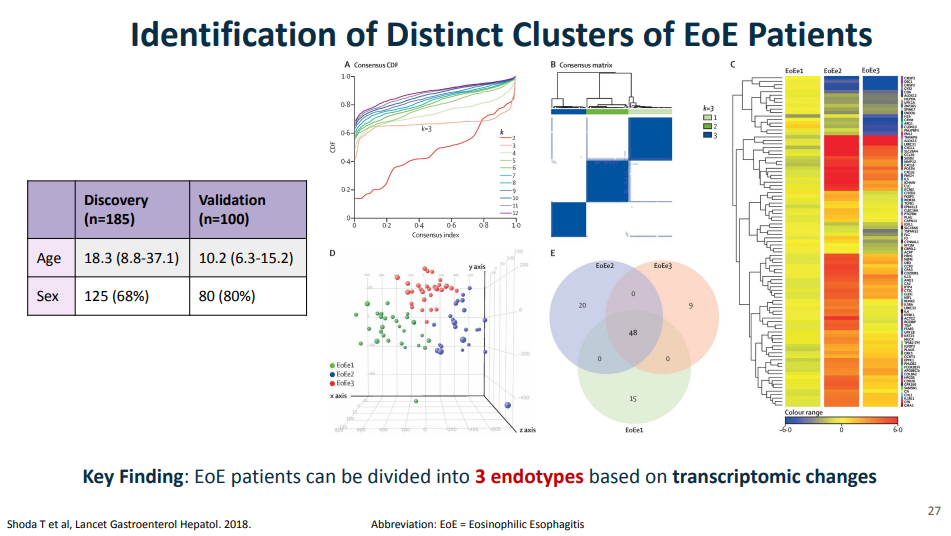
For EoE, machine-learning has already identified three subtypes that may affect clinical management. EoE1 is associated with a normal-appearing esophagus. EoE2 is associated with being steroid refractory. EoE3, when compared to the other two endotypes, is associated with adult-onset and narrow-caliber esophagus or stricturing.
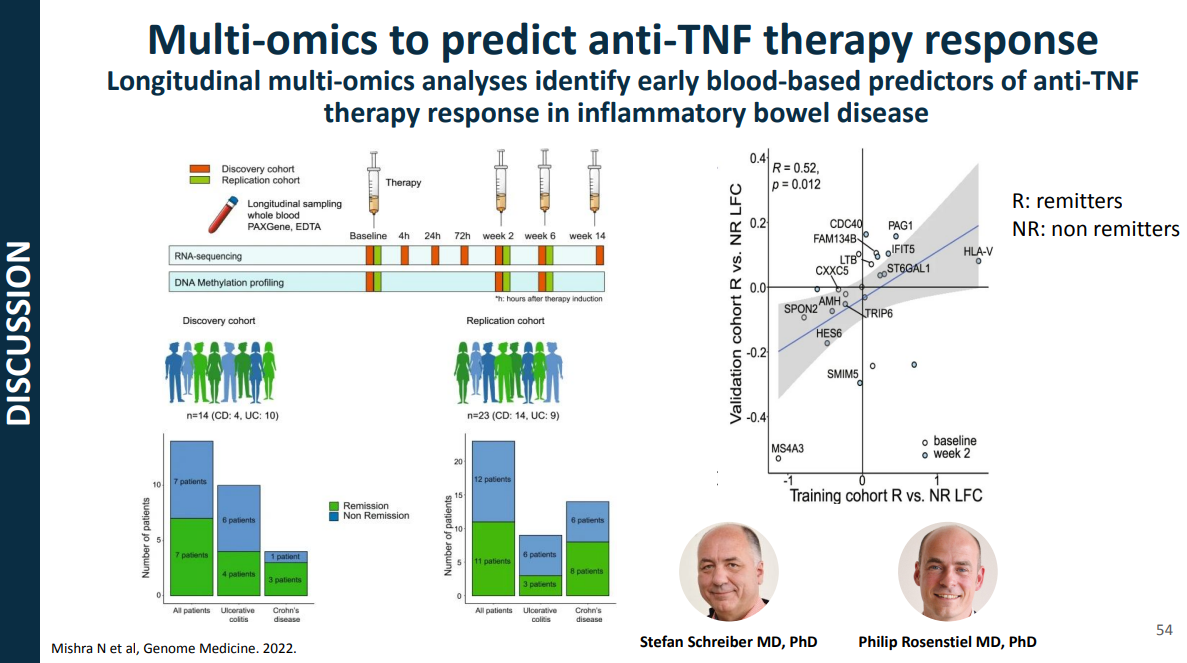
For Crohn’s disease, research has shown that younger age has been associated with an increased risk of not responding to anti-TNF therapy
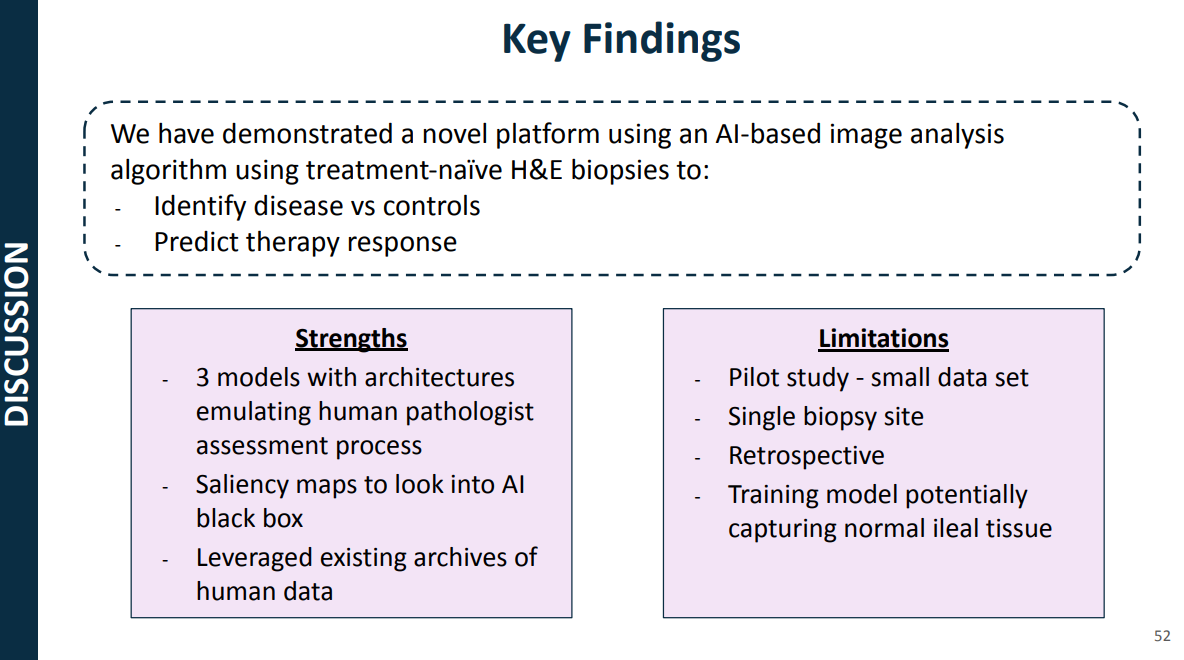
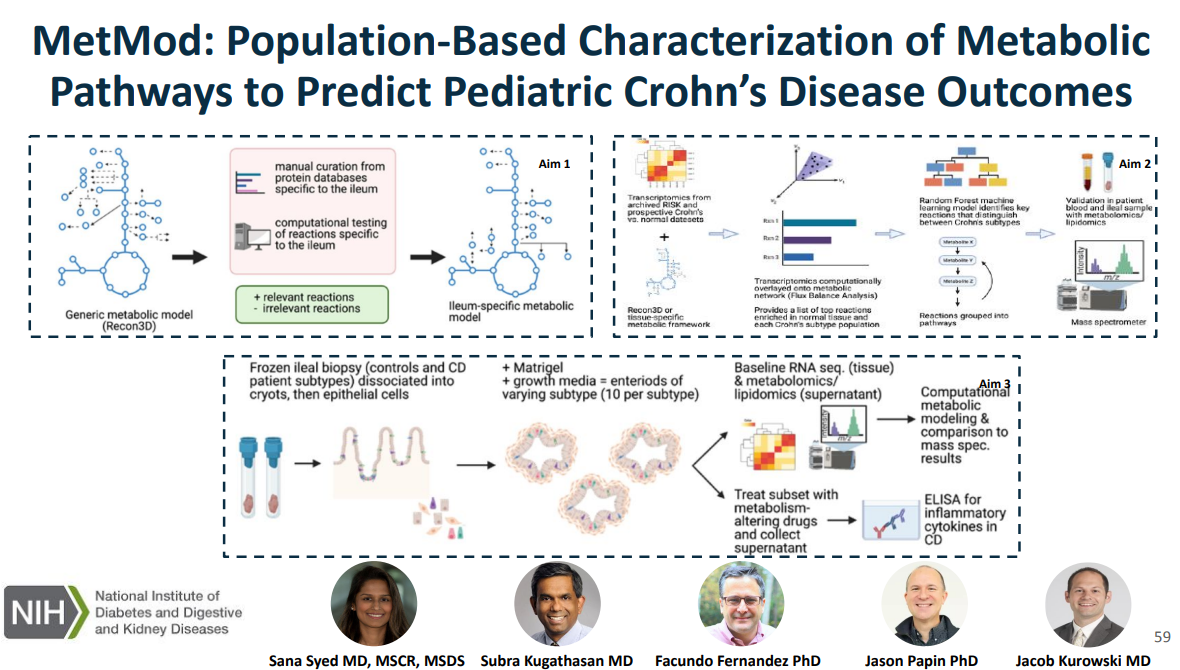
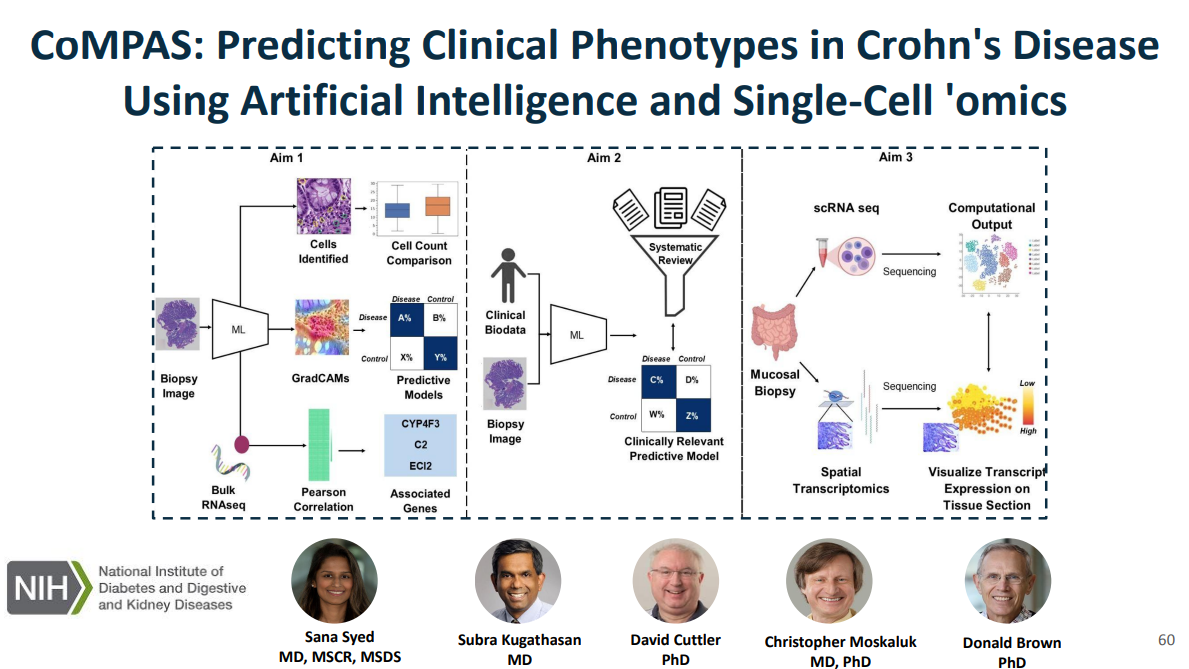
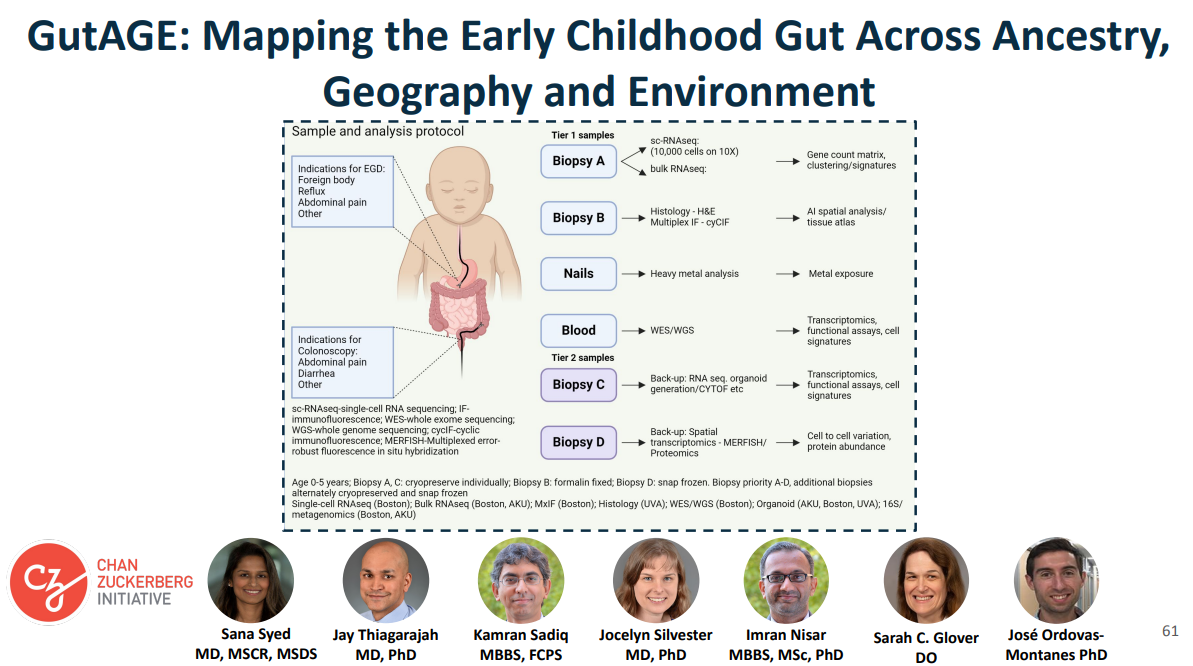
This is a quote from President Obama when his administration announced massive funding toward precision medicine in January of 2015, that the promise of precision medicine is ”delivering the right treatments at the right time, every time to the right person.” This figure illustrates some of the kinds of data that Dr. Syed had access to as faculty at UVA, including genomics, epigenome, transcriptomics, proteomics, metabolomics, etc.Shoda and colleagues, used a combination of histology data, endoscopic features, histologic and endoscopic scoring indices, and transcripts that make up the eosinophilic esophagitis diagnostic panel, a quantitative PCR assay with 96 EoE representative genes. The key message from all of those visualizations is that they found that EoE can be divided into three distinct endotypes after analyzing transcriptomics changes via partition-around-medoid clustering, a machine-learning method.In this project, the researcher intend to curate a novel metabolic network specific to the ileum, which is relevant to Crohn’s disease, link metabolic processes with Crohn’s disease phenotypes using in silico metabolic network modeling and ‘omics and characterize and target metabolic pathways in an organoid model generated from patient-derived Crohn’s disease tissue.In CoMPAS, the researchers aim to leverage artificial intelligence methods (AI) methods to build predictive models for CD using histology slides and single-cell RNA sequencing, allowing for risk stratification of B1 patients who will respond to anti-TNF therapyThe goal of our project is to create a multi-omics reference dataset with scRNA-seq data coupled with contextual data on tissue morphology, ancestry, social determinants of health, and the environment. The cohort for this study is enrolling patients who have clinical indications for endoscopy like foreign body removal, reflux, abdominal pain
My take: This work is necessary to identify the right treatments for each patient and will lead to better outcomes. We are already seeing the early stages of machine-learning’s impact on clinical care. In many other fields, AI work is much further along (especially in oncology). A recent study in Nature identified JAK inhibitors as potential life-saving therapy with toxic epidermal necrolysis (TEN).
Reference: Nordmann, T.M., Anderton, H., Hasegawa, A. et al. Spatial proteomics identifies JAKi as treatment for a lethal skin disease. Nature (2024). https://doi.org/10.1038/s41586-024-08061-0
Summary from Eric Topol (Ground Truths) focusing on spatial omics: Thierry Nordmann, Matthias Mann and their international consortium, used deep visual proteomics from 3μm PPFE sections of skin biopsies in patients affected by TEN…
More than 5,000 proteins were quantified from single cells—keratinocyte and immune cells—using mass spec, for the 4 different skin conditions (proteome cluster in Figure below, left panel). This led to the finding that the TEN patients had marked increased in Type 1 and 2 interferon signaling and activation of phosphorylated STAT1, which invoked the janus kinase (JAK/STAT) pathway. Subsequent steps were to test JAK inhibitors in cell culture (with live cell imaging) and in two different mouse models, all showing highly potent, dose-dependent impact on inhibition of the intense inflammatory process and disease severity…
They went on to treat seven patients at Fuian Medical University, the course of one patient shown below, treated with a JAKi on day 4 after diagnosis, and manifesting a marked response starting within 48 hours. All 7 patients fully resolved, with no side effects…
For spatial medicine, there are multiple analytical challenges that invoke the need for machine learning and A.I., including segmentation of cell types, automated capture of cells of microdissection, extracting useful information from the >5,000 proteins quantified per cell, and ultimately, as we’ll see more in the future, A.I. powering the construction of high-resolution 3D maps.
In this multicenter retrospective review with 183 patients, the adalimumab (ADM) levels were examined with respect to healing of perianal fistulas. Most patients (82%) had complex perianal fistulizing CD.
Key findings:
87 patients (48%) received intensified dosing at the time of therapeutic drug monitoring (TDM)
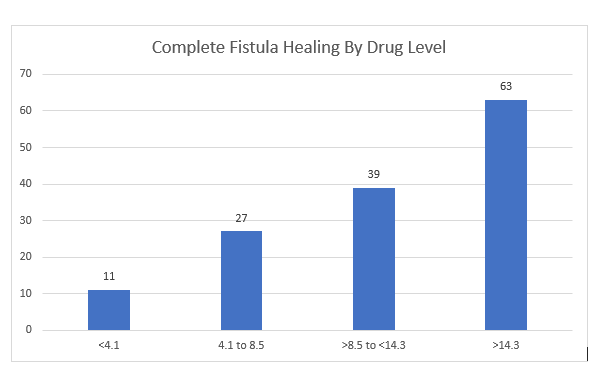
Patients with complete fistula healing (CFH) had higher median ADM levels: 12.9 compared to 6.1 for those witout CFH
“Optimal ADM concentration associated with CFH was 12.2 mcg/mL” which had positive predictive value of 64% and negative predictive value of 80%. Among those with ADM >12.1, CFH was achieved in 64% compared to 20.5% in those with concentrations <12.1 (Odds ratio, 5.7). “Even higher drug levels may be needed.”
There were 46 patients in each drug level category
My take: There is a lot of data supporting TDM, including proactive TDM, with anti-TNF agents like adalimumab and infliximab. This study shows that with fistulizing disease higher drug levels are needed to achieve better outcomes.
From Caitlyn Rivers Newsletter, Force of Infection 11/4/24:
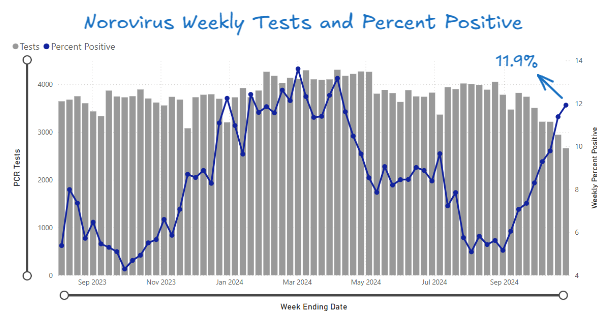
Norovirus is high and increasing right now. Nationally, test positivity is at nearly 12%. To put this in context, the peak last year was 13.6%. Rates are particularly high in the Southern region.
A reminder as cases increase: norovirus causes stomach pains, diarrhea, and vomiting. It is extremely transmissible via bodily fluids and through contaminated surfaces, food, and water.
To reduce your odds of getting sick, remember to wash your hands frequently with soap and water for at least 30 seconds (norovirus is able to withstand hand sanitizer).
If you or someone in your household becomes sick, wash hard surfaces with soap and water or a diluted bleach mixture, and wash soiled clothing and linens in hot water and then dry on high heat.
Norovirus is still highly transmissible for several days after symptoms improve or go away. As such, insofar as is possible, avoid preparing food for others for at least 72 hours after symptoms end. Longer is better: it can spread up to two weeks after symptoms end, though it is most transmissible during those first few days of illness and after symptoms resolve.
In this observational prospective cohort with 114 children (after excluding 6), outcomes following the first episode of acute pancreatitis (AP) were determined. In addition, pancreatitis risk genes (CASR, CEL, CFTR, CLDN2, CPA1, CTRC, PRSS1, SBDS, SPINK1, and UBR1) were sequenced. A genetic risk score was derived from all genes with univariable P < .15.
Pre-DM was defined as follows: fasting blood glucose ≥100 mg/dL and <126 mg/dL, or hemoglobin A1C ≥5.7% and <6.5%
Key findings:
95/114 (83%) remained normoglycemic and 19/114 (17%) developed endocrine insufficiency (4 DM, 15 pre-DM) 12 months after the first episode of AP
Sixty-three subjects (52.5%) had at least 1 reportable variant identified
Severe AP (58% vs 20%; P = .001) and at least 1 gene affected (79% vs 47%; P = .01) were enriched among the endocrine-insufficient group
CFTR (53%), SPINK1 (13%), PRSS1 (10%), and UBR1 (9%) accounted for the majority of variants identified
My take: 3.5% of this cohort developed diabetes and 13% developed prediabetes. The risk is increased in those with severe acute pancreatitis and underlying genetic variants. As noted recently with Dr. Freeman’s lecture (summarized on prior blog posts), it is worthwhile for patients to follow-up after an episode of acute pancreatitis.










 gutsandgrowth
