Related blog posts:
- ACG Clostridium Difficile Guidelines Plus One (2021)
- Secondary Prophylaxis of Clostridiodes difficile Infection (this is alluded to in the 3rd slide of this post)
From Emory Gastroenterology and Hepatology Twitter Feed:


Related blog posts:
From Emory Gastroenterology and Hepatology Twitter Feed:
EW Lopes et al. Clin Gastroenterol Hepatol 2022; 20: 303-313.Open Access: Dietary Gluten Intake Is Not Associated With Risk of Inflammatory Bowel Disease in US Adults Without Celiac Disease
Key finding: In 3 large adult US prospective cohorts (n=208,280), gluten intake was not associated with risk of CD or UC in 5,115,265 person-years of follow-up evaluation.
My take (from authors): These ” findings are reassuring at a time when consumption of gluten has been increasingly perceived as a trigger for chronic gastrointestinal diseases.”
Related blog posts:

From GeneralSurgeryNews.com: Open Access: Novel Device Uses Mechanotransduction To Treat Small Bowel Syndrome
An excerpt:
“The basic concept is similar to distraction osteogenesis, which orthopedic surgeons have used for years, applying distraction force to broken bone that will grow up to a millimeter a day,” said Andre Bessette, the CEO and a co-founder of Eclipse Regenesis, Inc…
To regenerate small-bowel tissue, a surgeon inserts the device, which looks like a small, compressed coil, inside the small intestine and secures both ends with plication sutures applied to the outside of the intestine. Over two to three weeks, the device slowly expands to its uncompressed state, stimulating new tissue growth—ultimately two to three times the segment’s original length, about 4 cm...[thus] they’ll need more than one device applied or more than one procedure.
Once this process is complete, the chromic sutures dissolve over about a month, allowing the device to pass through the body to be excreted...
[The researchers] expect to start these [human] trials in the first half of 2022, and they have identified two primary investigator sites: Boston Children’s Hospital and Cincinnati Children’s Hospital
Preclinical studies: Eclipse’s website at www.eclipseregenesis.com/ publications.

Like many clinicians, I would very much like to tell insurance companies how I really feel about their prior authorization policies, and peer-to-peer processes to get approvals needed for treating our patients.
Most of the time I resent the imposition on my time to craft detailed letters explaining my rationale for treatment. Some obstructionist tactics are particularly aggravating. For example, when I am asked to do a peer-to-peer call and find out on the call that the person on the other end is neither a peer (often a pharmacist) and more importantly that this person is not authorized to remedy the situation but only to arrange another call. Another tactic of asking me to write multiple letters at different stages of the authorization process is extremely annoying. All told, these authorization requests are becoming more frequent and further impinging on my free time.
Now it turns out a study has shown the harmful effects of these maneuvers for our patients:
Constant BD, de Zoeten EF, Stahl MG, et al. Delays Related to Prior Authorization in Inflammatory Bowel Disease. Pediatrics. 2022;149(3):e2021052501 (Thanks to Ben Gold for this reference)
In this retrospective study of 190 pediatric patients ((median age 14.5 years) with IBD initiating biologics at a tertiary care hospital, key findings:
In their discussion, the authors note that “in a recent survey conducted by the American
Medical Association, 94% of physicians reported that prior authorizations delay access to
necessary care, 90% perceived a negative impact on clinical outcomes, and 30% reported that a prior authorization led to a serious adverse event for a patient in their care.”
My take: Prior authorization policies usually delay needed care unnecessarily and lead to complications in children with IBD.
Related blog posts:

In 2014, one of the posts on this blog addressed stopping anti-TNF therapy: Marriage, Divorce and Separation with Anti-TNF Therapy. My take at that time was “most patients are better off staying married to their anti-TNF therapy.”
Despite changes in therapeutic options, a recent study and editorial come to the same conclusion in 2022:
In the retrospective study, 78 patients with CD and 56 patients with UC underwent endoscopic reassessment. Key findings:
In the commentary, the authors note the high rate of relapse in other studies with anti-TNF withdrawal (eg. STORI trial) and high rate of surgery in patients with perianal CD who stopped therapy. In the STORI trial, “the best outcomes [for infliximab withdrawal] were those with subtherapeutic infliximab trough levels, ie, those for whom infliximab was not responsible for maintaining their remission.”
The data are less certain for UC. The editorial notes that 85% of the 21 patients in the Scarallo study had limited left-sided colitis and only 17 were followed for at least 1 year. In adult studies on anti-TNF discontinuation with UC (Kennedy et al. Aliment Pharm Ther 2016; 43: 910-23 and Molander et al. Inflamm Bowel Dis 2014; 20: 1021-28), 42% and 35% relapsed within 12 months, whereas another small study (Farkas et al. World J Gastroenterol 2014; 20: 2995-3001) found 100% of patients on combination therapy who stopped anti-TNF agent had to restart anti-TNF therapy.
My take (from editorial): “The totality of the currently available evidence suggests that discontinuing anti-TNF medications in children with IBD is associated with a greatly increased risk of disease exacerbation, especially if the anti-TNF trough level was therapeutic.”

O Baghdadi et al. JPGN 2022; 74: 221-226. Predictors and Outcomes of Fully Covered Stent Treatment for Anastomotic Esophageal Strictures in Esophageal Atresia
This retrospective review of 45 patients (n=92 stents) examine the effectiveness of esophageal stenting in patients with esophageal atresia (EA). All patients had multiple dilatations prior to stenting and/or had a stricture diameter that rapidly narrowed within 2 weeks of dilatation to a diameter that was the same or smaller to predilatation. Patients were observed in the hospital after stent placement and outpatient management was considered if oral nutrition was tolerated for at least 3 days.
Key findings:
My take: Complications were frequent; thus, stenting for refractory strictures requires highly-specialized technical expertise.
Related blog posts:

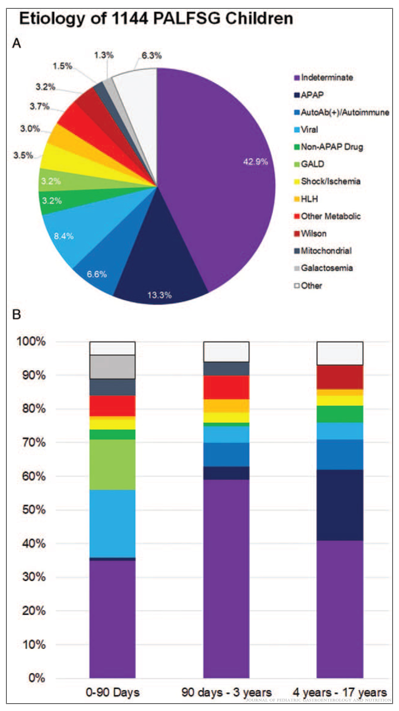
JE Squires et al. JPGN 2022 – Volume 74 – Issue 1 – p 138-158. doi: 10.1097/MPG.0000000000003268. Open Access: North American Society for Pediatric Gastroenterology, Hepatology, and Nutrition Position Paper on the Diagnosis and Management of Pediatric Acute Liver Failure
This article provides a terrific summary of the most urgent issues with regard to caring for children with PALF; this article provides helpful information for diagnosis, and management, as well as information on pathophysiology, and associated outcomes.
PDF version: PALF in Children Position Paper
The article makes a number of recommendations for testing/treatment -here are a few of them:
Related blog posts:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.
AF Peery et al. Gastroenterol 2022: 162: 621-644. Burden and Cost of Gastrointestinal, Liver, and Pancreatic Diseases in the United States: Update 2021
Using several national surveys (2016-2018), the authors provide data on GI diagnoses and expenditures for adults and children
Key findings:
This article is loaded with statistical details
During my training, we reported a case of Menetrier’s disease in a pediatric patient associated with CMV infection (Open Access PDF: Diagnosis of Cytomegalovirus Infection in Pediatric Menetrier’s Disease by In Situ Hybridization).
Recently, JPGN’s twitter feed shared the images below from a recent report (SJ Pathak et al. JPGN January 2022 – Volume 74 – Issue 1 – p e16doi: 10.1097/MPG.0000000000003276. Menetrier Disease in a Pediatric Patient With Ulcerative Colitis and Primary Sclerosing Cholangitis)
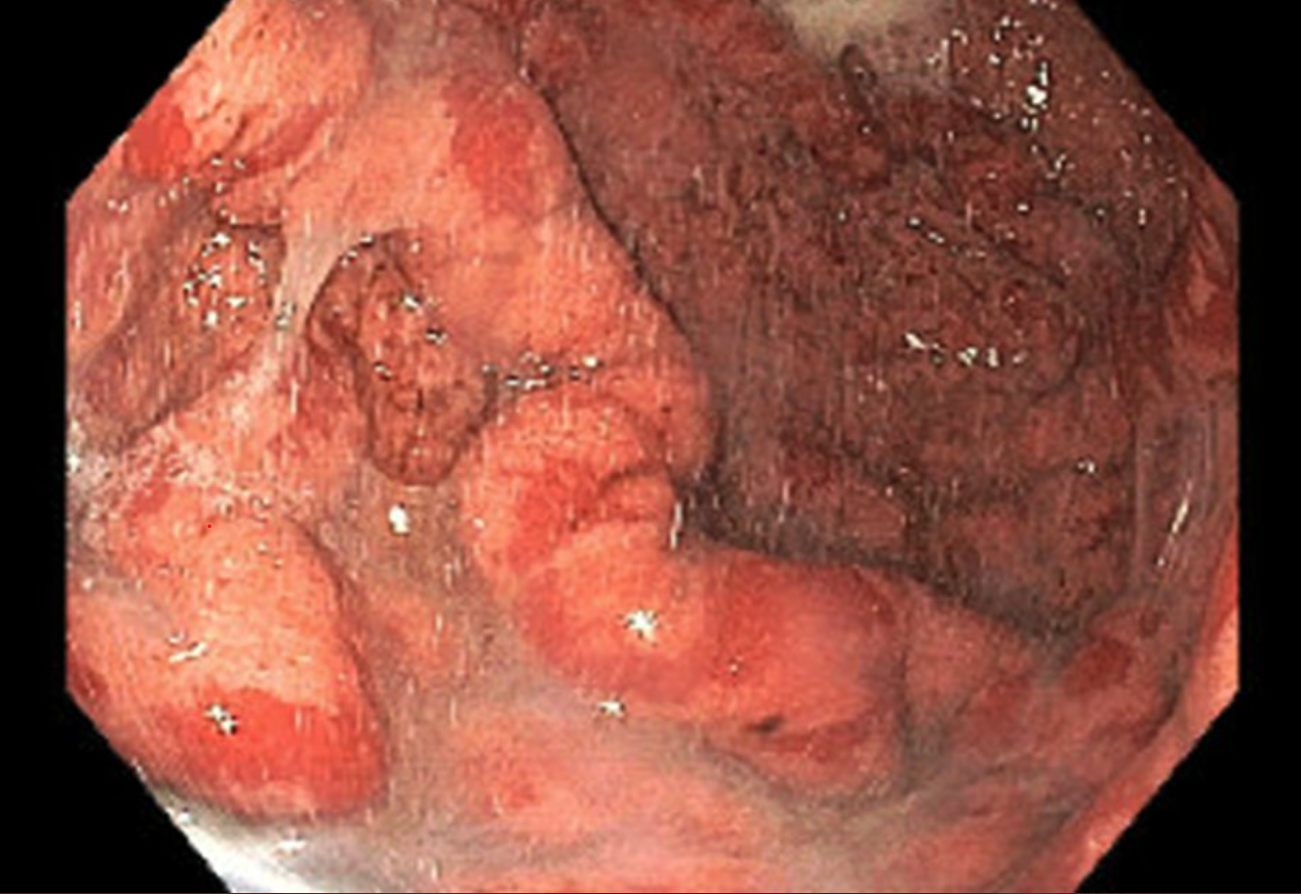
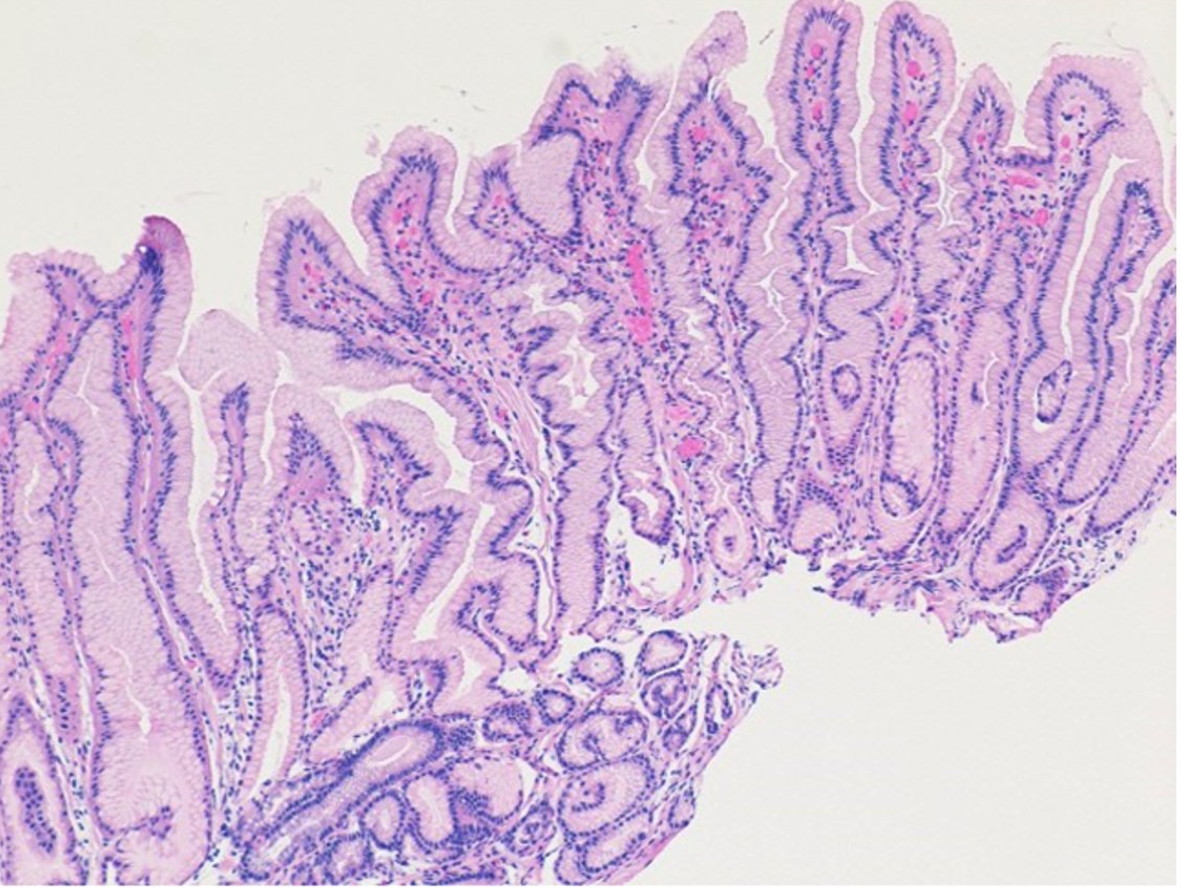

Related blog post: Image Only: Pediatric Menetrier’s Disease
LC Shipley et al. Clin Gastroenterol Hepatol 2022; 20: 455-457. Vedolizumab Therapy in Refractory Microscopic Colitis: A Single Center Case Series
In this report, the authors describe nine patients with refractory microscopic colitis (median age 55 years) who were treated with vedolizumab.
Key findings:
My take: Given vedolizumab’s favorable safety profile, further studies (with endoscopic endpoints) of vedolizumab are needed to define its efficacy for microscopic colitis.
Another study with vedolizumab: J Kirchgesner et al. Clin Gastroenterol Hepatol 2022; 20: 314-324. Risk of Serious Infections With Vedolizumab Versus Tumor Necrosis Factor Antagonists in Patients With Inflammatory Bowel Disease
Key finding: The risk of serious infections was not different between vedolizumab and anti-TNF in the overall IBD cohort (HR, 0.95; 95% CI, 0·79-1.13), while the risk was decreased for vedolizumab users in patients with UC (HR, 0.68; 95% CI, 0.50-0.93), but not CD (HR, 1.10; 95% CI, 0.87-1.38)
Related blog post/related article:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

