From David Rubin, MD

From David Rubin, MD
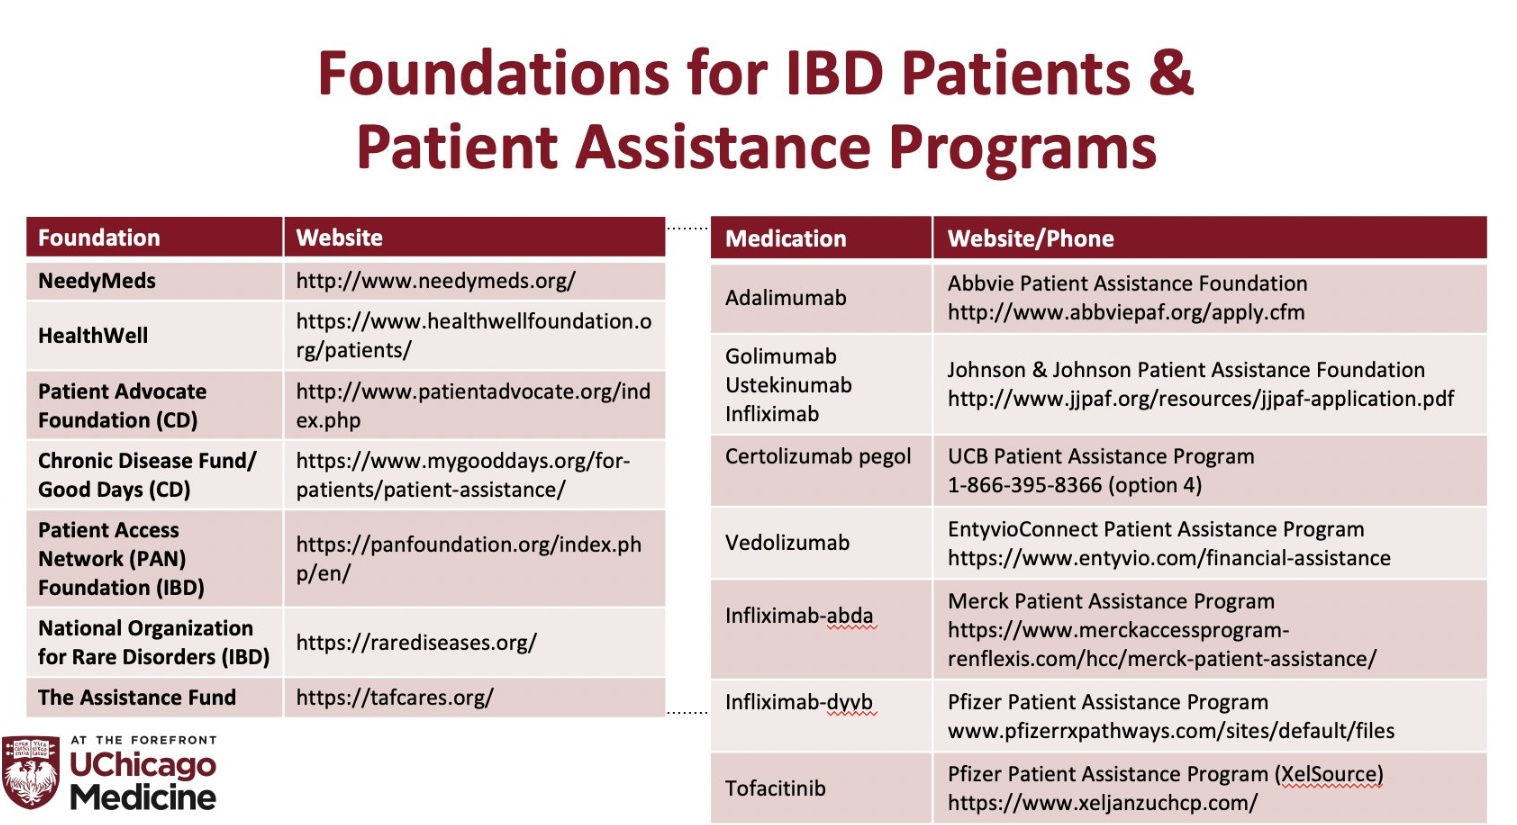
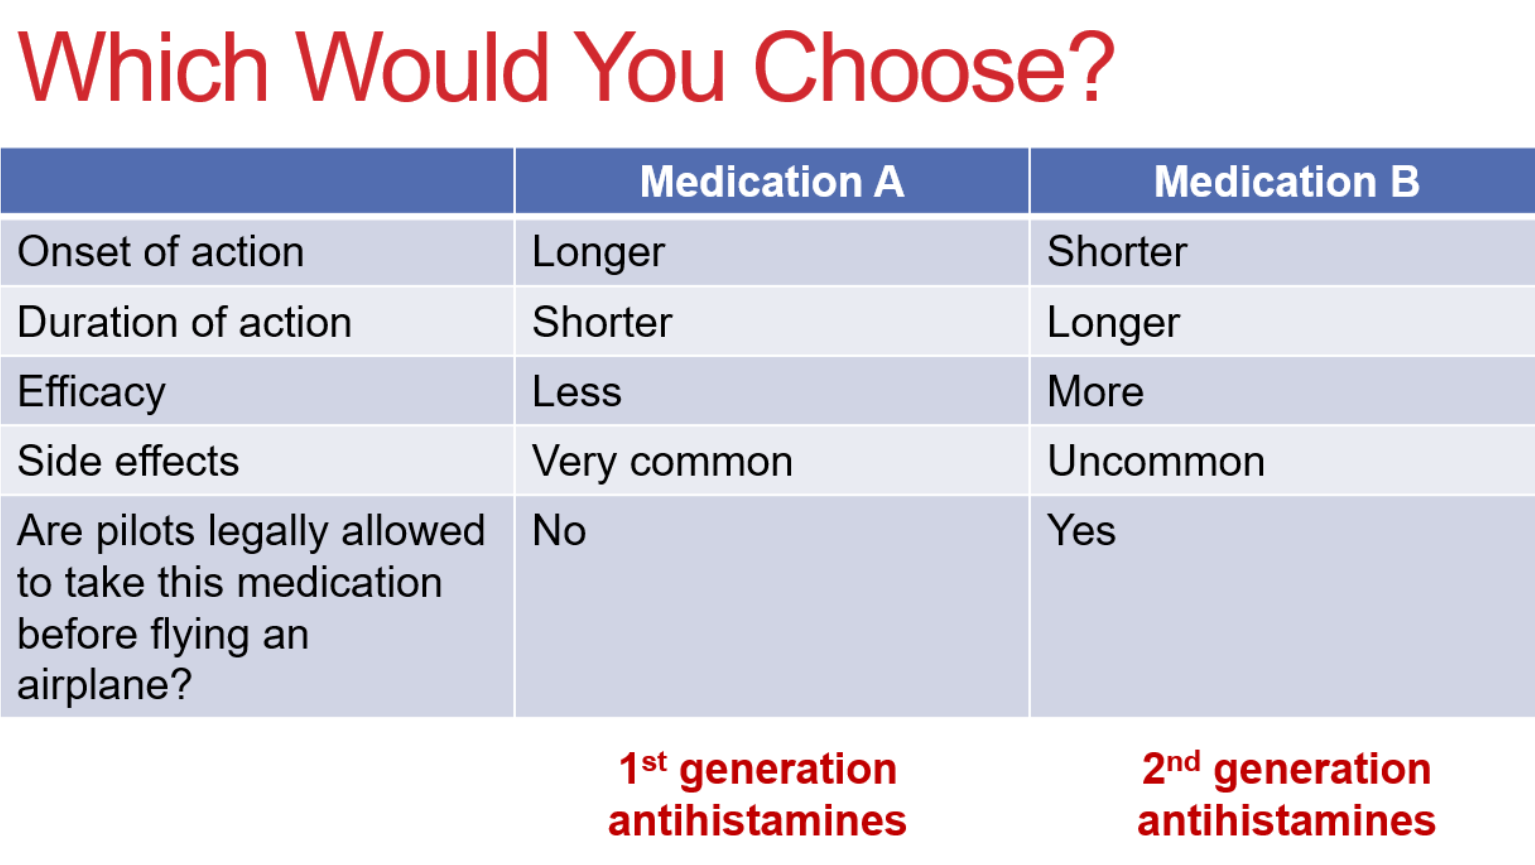
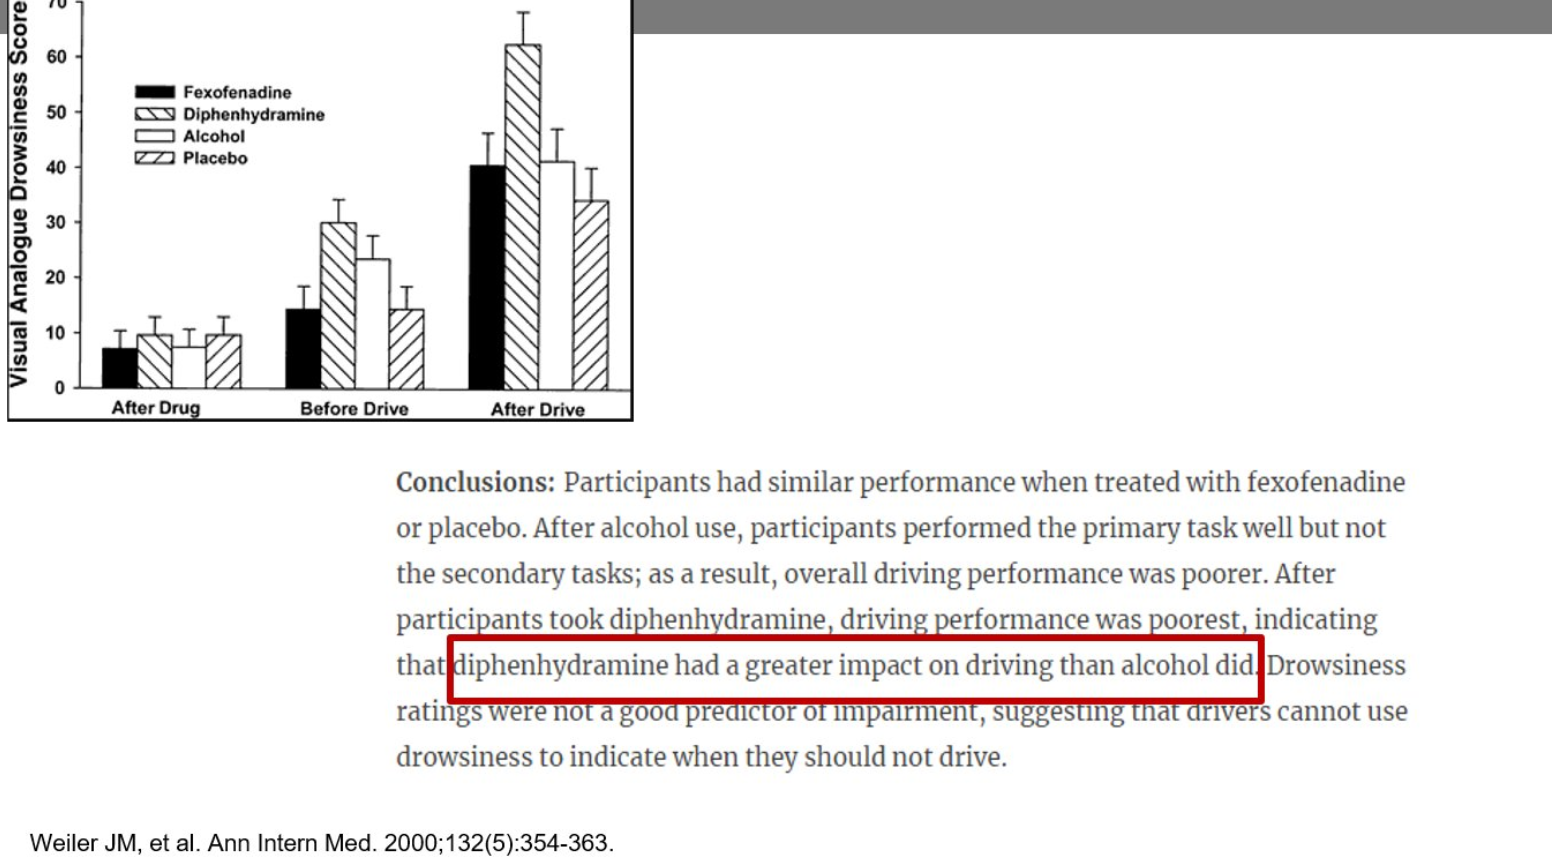
Dr. Dave Stutkus shared some slides (on twitter) recently based on a lecture at Nationwide Children’s. Since I see children everyday who are undergoing poorly-conceived allergy testing, I wanted to share some of them.
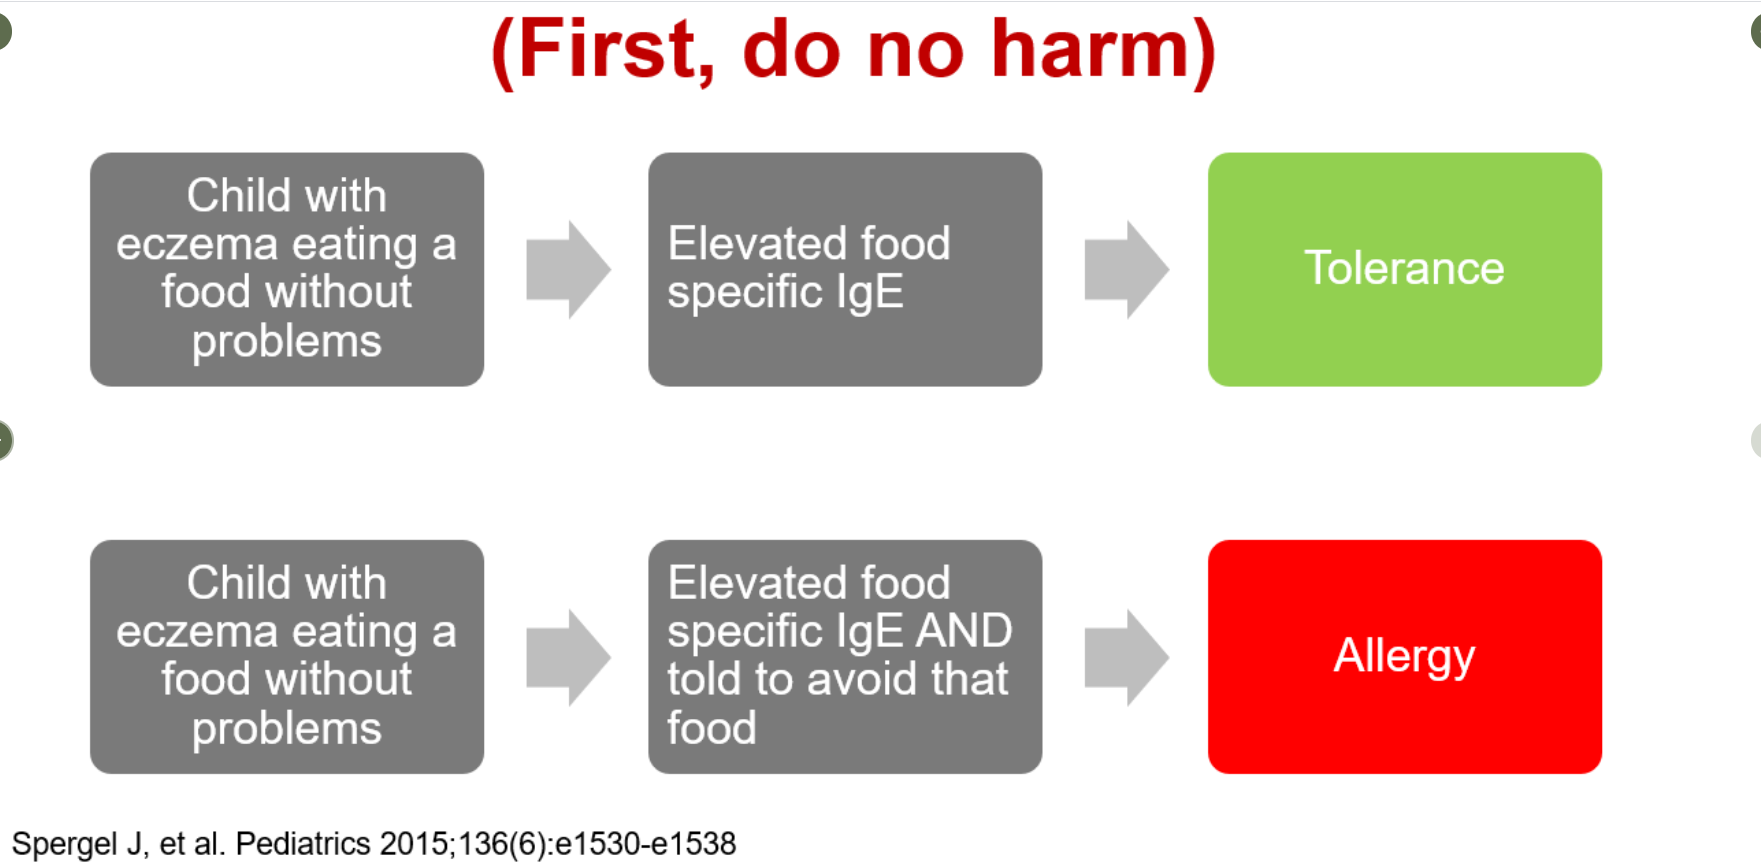







Also, link to AAP guidelines on breastfeeding & eczema and introduction of foods to minimize development of allergies: The Effects of Early Nutritional Interventions on the Development of Atopic Disease in Infants and Children: The Role of Maternal Dietary
Restriction, Breastfeeding, Hydrolyzed Formulas, and Timing of Introduction of Allergenic Complementary Foods
Related blog posts:
Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician. Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure. This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition
From NPR: More Pizza And Fries? USDA Proposes To ‘Simplify’ Obama-Era School Lunch Rules
An excerpt:
The U.S. Department of Agriculture has proposed new rules for school meals aimed at giving administrators more flexibility in what they serve in school cafeterias around the country each day.
For instance, instead of being required to offer higher quantities of nutrient-dense red and orange vegetables such as carrots, peppers and buttternut squash, schools would have more discretion over the varieties of vegetables they offer each day. In addition, students will be allowed to purchase more entree items as a la carte selections…
Critics say the proposed changes from the Trump administration amount to further rollbacks of the nutrition standards put in place during the Obama administration following the passage of the Healthy, Hunger-Free Kids Act of 2010…
“In practice, if finalized, this would create a huge loophole in school nutrition guidelines, paving the way for children to choose pizza, burgers, French fries, and other foods high in calories, saturated fat or sodium in place of balanced school meals every day,” The proposal follows a spate of rule changes announced by Perdue in 2018 that weakened the whole grain requirements and gave school administrators more leeway to serve up white breads and biscuits.
My take: School lunch standards do not need to be rolled back. While improving nutrition at schools will not solve the epidemic of obesity, it needs to be at least one piece of a much bigger puzzle.
Related blog posts:

There have been some recent terrific advances in pharmacology –a few that come to mind:
The one common feature is that these are all very expensive; there are many other expensive medications with less benefit. Given the rise in costs of these medications, there is a need to do a better job in getting good value in our drug costs. A potential path forward is outlined in a recent commentaries (SB Dusetzina, J Oberlander. NEJM 2019; 381: 2081-4; PB Bach. NEJM 2019; 381: 2084-6).
In the first commentary, the authors review the Elijah E Cummings Lower Drug Costs Now Act of 2019 (HR 3).
In the second commentary, Dr. Bach notes that drugs that have too little evidence to support full approval and those that are ‘too late in their life cycle’ both should have their pricing negotiated by the government. This would side step some of the arguments about undermining the incentive for new drug development.
“Too little”
“Too late”
My take: While current partisanship makes reaching agreement difficult, targeting soaring pharmaceutical costs is one area in which I predict common ground can be found. While many are going to benefit from the therapeutic advances listed above, there are other medications which are overpriced and should be negotiated like in other high-income countries.
Related blog posts:

Bathroom mural for bicycle enthusiasts (at a stop on the Petit Train du Nord Linear Park)

The NEJM has made the information it has on the emerging coronavirus open access. Here are the links:
An excerpt from the editorial:
For the third time in as many decades, a zoonotic coronavirus has crossed species to infect human populations. This virus, provisionally called 2019-nCoV, was first identified in Wuhan, China, in persons exposed to a seafood or wet market. The rapid response of the Chinese public health, clinical, and scientific communities facilitated recognition of the clinical disease and initial understanding of the epidemiology of the infection. First reports indicated that human-to-human transmission was limited or nonexistent, but we now know that such transmission occurs, although to what extent remains unknown. Like outbreaks caused by two other pathogenic human respiratory coronaviruses (severe acute respiratory syndrome coronavirus [SARS-CoV] and Middle East respiratory syndrome coronavirus [MERS-CoV]), 2019-nCoV causes respiratory disease that is often severe.1 As of January 24, 2020, there were more than 800 reported cases, with a mortality rate of 3%…
Both SARS-CoV and MERS-CoV infect intrapulmonary epithelial cells more than cells of the upper airways.4,6 Consequently, transmission occurs primarily from patients with recognized illness and not from patients with mild, nonspecific signs. It appears that 2019-nCoV uses the same cellular receptor as SARS-CoV (human angiotensin-converting enzyme 2 [hACE2]),3 so transmission is expected only after signs of lower respiratory tract disease develop…
It is likely that 2019-nCoV will behave more like SARS-CoV and further adapt to the human host, with enhanced binding to hACE2.


A recent prospective cohort study (M Hadjivassiliou et al. Clin Gastroenterol Hepatol 2019; 17: 2678-86) shows an alarmingly-high level of neurologic deficits in 100 consecutive adults (mean age 43 years) with a new diagnosis of celiac disease.
Key findings:
Some neurologic findings improve on a gluten-free diet (GFD). In previous studies of patients with CD and headaches, 75-80% improved or subsided after a year of strict adherence to a GFD.
My take: This study indicates that early diagnosis of celiac disease along with strict adherence to a gluten-free diet is likely to prevent permanent neurologic disability.
Related blog posts:

Several recent articles regarding reforming our current healthcare system have been published in Annals of Internal Medicine (Jan 2020) and are open access. Highlighted text in images below by Eric Topol, MD.
In this position paper, the American College of Physicians (ACP) proposes strategies to address social determinants of health and reduce barriers to care in order to achieve ACP’s vision for a better U.S. health care system for all. The ACP’s vision, outlined in an accompanying call to action (1), includes 10 vision statements, 4 of which are particularly relevant to the policies discussed in this paper (Figure). The companion position papers address improving payment and delivery systems (2) and coverage and cost of care (3). Together, these papers provide a policy framework to achieve ACP’s vision for a better U.S. health care system.

Link: Envisioning a Better U.S. Health Care System for All: Coverage and Cost of Care

Link: The American College of Physician’s Endorsement of Single-Payor Reform
An excerpt:

Link: “Original Sin” and U.S. Health Care
An excerpt:
This series of articles describes a vision and makes important recommendations to improve coverage and control costs; reform health care delivery and payment to promote person-centered; high-value primary care; and address social and environmental determinants of health…
Seen through the lens of the American College of Physicians’ recommendations, how might addressing an original sin of failure to directly finance universal coverage in the United States facilitate progress on other recommendations?…
Implementation of the American College of Physicians’ recommendations, with an emphasis on promoting transparent, direct financing of universal access, holds great promise for replacing the current system of opaque and distorting subsidies with one that better serves all Americans.
Link: A New Vision for Quality and Equity
Link: Health is More Than Health Care

Link: The U.S. Health Care System Is Ill and Needs a Bold New Prescription


NPR: U.S. Alcohol-Related Deaths Have Doubled, Study Says
An excerpt:
Death certificates spanning 2017 indicate nearly 73,000 people died in the U.S because of liver disease and other alcohol-related illnesses. That is up from just under 36,000 deaths in 1999…
Overall, researchers found men died at a higher rate than women. But when analyzing annual increases in deaths, the largest increase was among white women…
Only cigarettes are deadlier than alcohol: More than 480,000 people die each year in the U.S. because of smoking-related illnesses.
Related blog post:



A recent “Grand Rounds” review of venous thrombosis (VT) in pediatric inflammatory bowel disease (E Mitchel, T Diamond, L Albenberg. J Pediatr 2020; 216: 213-7) provides some practical advice in an area in need of more clarity.
Risk factors for VT:
Key points:
My take: In adolescents hospitalized with IBD, this article suggests that almost all should receive mechanical prophylaxis for VT and a subset at increased risk may benefit from pharmaccologic prophylaxis.
Related blog posts:

From a visit to Montreal

