Here’s Why Biologic Therapy for Crohn’s Helps Adolescents Grow

It is well-recognized that Crohn’s disease is associated with delays in the onset and progression of puberty with the potential for stunted growth, impaired bone accrual, and diminished quality of life.

Now, a study (MD DeBoer et al. J Pediatr 2016; 171: 146-52) shows that initiation of anti-tumor necrosis factor α (anti-TNFα) treatment results in a rapid increase in sex hormone and gonadotropin levels.

In 72 adolescents, this observational study followed levels of sex hormones, gonadotropin levels, dual-energy x-ray absorptiometry, along with cytokine/inflammatory markers at initiation of anti-TNFα therapy, at 10 weeks and at 12 months.

Key findings:

  • By week 10 , testosterone z scores in males increased from a median of -0.36 to 0.40 (P<0.05)
  • By week 10 , estradiol z scores in females increased from a median of -0.35 to -0.02 (P<0.01)

My take (from the authors): This study suggests that “systemic inflammation suppresses gonadotropin-stimulated production of sex hormones” and that treatment of this inflammation with anti-TNFα agents allows rapid resumption normal production.

Related blog posts:

Law Quad, Univeristy of Michigan

Law Quad, Univeristy of Michigan

Anti-TNF therapy and Pregnancy -More Data

G Broms et al (Clin Gastroenterol Hepatol 2016; 14: 234-41) provide more data on the ‘low risk of birth defects for infants whose mothers are treated with anti-tumor necrosis factor agents during pregnancy.”

From a Danish/Swedish cohort of 1,272,424 live births (2004-2012), the authors found the following (in comparison to healthy infants):

  • Birth defects were increased in chronic inflammatory bowel disease: 4.8% vs. 4.2%
  • 43 (6.3%) of the infants born to women with IBD who received anti-TNF therapy (683) had birth defects.  The OR for any defect was 1.32 (CI 0.93-1.82).  The types of defects were generally similar, including VSD, ASD, hypospadias, and hydronephrosis

Limitations:

  • In infants of mothers with chronic diseases, it is possible that more careful screening identified some less apparent defects.
  • Study did not examine rates of stillborn or abortions

My take: Overall there is a slightly but not significantly increased risk in birth defects based on the use of anti-TNF therapy.  Stopping anti-TNF therapy is likely to be more detrimental.

Briefly noted: P Wils et al. Clin Gastroenterol Hepatol 2016; 14: 242-50.  This retrospective study of 122 patients showed that 65% had a clinical benefit within 3 months of receiving ustekinumab for Crohn’s disease refractory to anti-TNF therapy.  Concomitant immunosuppressant therapy was associated with an increased likelihood of benefit (OR 5.43)

Related blog posts:

More on Hidradenitis Suppurativa and Inflammatory Bowel Disease

In a population-based inception cohort study (S Yada et al. Clin Gastroenterol Hepatol 2016; 14: 65-70) of 679 patients with inflammatory bowel disease (IBD) followed for a median of more than 19.8 years, it was determined that patients with IBD were ~9 times more likely to develop hidradenitis suppurativa (HS) compared with general population. 8 of 679 patients developed HS; only one had HS prior to IBD.

Other findings:

  • Most Crohn’s disease patients with HS had perianal disease.  Most ulcerative colitis patients developed HS after colectomy.
  • Female sex and obesity were risk factors for HS.

In a second retrospective study (N Kamal et al. Clin Gastroenterol Hepatol 2016; 14: 71-9), the authors identified 15 patients with CD and HS.  10 patients had perianal disease.  In this population, “both diseases were characterized by their severity, requirement of systemic medical therapies including anti-TNF and high operative rate.” this article contained some very helpful pictures.

Unrelated article: F Wang, JL Kaplan, BD Gold et al. Cell Reports; 2016: 14: 945-55.  This highly technical study used two independent cohorts of patients with Crohn’s disease and non-IBD controls.  One cohort, RISK, had over 700 patients and ~30,000 mean number of reads per sample; the other cohort, PIBD-CC, and 87 patients and ~3000 mean number of reads per sample.  Overall, the study showed associations between Crohn’s disease and bacteria in the lumen and the study helps provide an information-based method to depict dysbiosis.

Related blog post: Add it to the list

San Juan

San Juan

“Good Job Making the Diagnosis”

Briefly noted: JA Leon et al. Gastroenterol 2015; 149: 1697-99.  Case report of Job syndrome (Autosomal-Dominant Hyper-IgE syndrome) mimicking Crohn’s disease in a 37 yo with perianal fistula, and weight loss. Clues to the diagnosis: “Recurrent skin abscesses and respiratory infections, eczema, marked elevation of serum IgE, eosinophilia, and mucocutaneous candidiasis are the hallmark of the infectious and immunologic features…Boils and furuncles almost always occur and characteristically lack of the usual inflammatory findings…”cold” abscesses…associated with markedly increase IgE or eosinophil levels, should always raise a suspicion for AD-HIES.”

Related blog post: Add it to the list | gutsandgrowth

Optimism for New Treatment in Inflammatory Bowel Disease: AJM300

Yesterday’s post on “Eternal Nutrition” had a link to podcasts on enteral nutrition as therapy for Crohn’s disease.  I listened to the podcasts and they were helpful (Enteral Therapy as Primary Therapy for Crohn’s Disease Podcast).  A few points that were made included the following:

  1. Try to have the right person teach/place the nasogastric feeding tube.  If the first experience is bad, this may make further attempts quite difficult.  At CHOP, their facility has an education center and they schedule 3-hour learning session for enteral feeds.  Teaching the teen to place the NG tube is preferred.
  2. Many pediatric gastroenterologists in U.S. are not informing their patients that enteral feedings are a treatment option.
  3. In most parts of the world, induction with enteral nutrition involves virtually 100% of diet as enteral nutrition for ~8-12 weeks.  CHOP modification involves 80-90% of calories delivered enterally, typically over an overnight drip.  If someone is not responding to enteral feeds, CHOP may increase calories delivered enterally.
  4. For maintenance with CHOP modification, gradually reduction from 7 days per week to 5 days per week is attempted.  At CHOP, they prefer hydrolysate for enteral tube feedings and think more rapid gastric emptying could be helpful.  However, the podcast state that specific formulas have not been shown to be superior in trials to date.  At CHOP, if formula is taken orally, then an intact protein formula is selected.
  5. If someone uses enteral formula for maintenance, then consideration of a gastrostomy tube (after 3 months) is reasonable.  They have not had local issues at sites due to Crohn’s disease.
  6. Resources include the Oley.org website and the Crohn’s Survival Guide.
  7. Enteral therapy seems to work in small bowel as well as colonic disease, despite early reports suggesting less efficacy with colonic disease.

———————

A recent phase II study (N Yoshimura et al. Gastroenterol 2015; 149: 1775-83) indicates that an oral antagonist of α4 integrin may be quite useful for ulcerative colitis.

This double-blind, placebo-controlled trial with 102 patients found the following:

  • A clinical response rate at 8 weeks of 62.7% in the treatment group and 25.5% for placebo)
  • Rates of remission were 23.5% in the treatment group  compared with 3.9% in the placebo group.
  • Mucosal healing were 58.8%% in the treatment group  compared with 29.4% in the placebo group.
  • No serious adverse events were noted.

In the commentary by  BG Levesque and S Ghosh (pg 1669-72), it is noted that subsequent oral integrins will be compared to vedolizumab and similar safety concerns exist; that is making sure that there are no cases of progressive multifocal leukoencephalopathy (PML) which has been associated with natalizumab therapy.  For vedolizumab, the RAMP safety monitoring program has NOT identified PML in 2884 IBD patients.

The commentary (in blue) discusses several integrins as potential therapeutic targets and outlines future therapies.

Nontargeted therapies:

  • A) Induction: corticosteroids, 5- aminosalicylates, cyclosporin, and tacrolimus
  • B) Maintenance: thiopurines, methotrexate, 5-aminosalicylates, and tacrolimus.

Targeted therapies (those in development phase in italics)

  • A) Monoclonal antibodies (induction and maintenance): tumor necrosis factor inhibitors, vedolizumab, other integrin/adhesion molecule inhibitors, interleukin-12/23 inhibitors, and interleukin-6 inhibitors.
  • B) Oral synthetic (induction and maintenance or stop and start): Jakinibs, integrin blockers, sphingosine-1-phosphate (s1P) regulators, and SMAD7 antisense oligonucleotide.

“The results of AJM300 demonstrate feasibility of such an approach, and we anticipate a proliferation of such approaches given the robust evidence supporting integrins as a target, especially if the drug can be targeted or delivered in a gut-specific manner.”

My take: There are a number of therapies being developed that are likely to transform the treatment of inflammatory bowel disease; future treatments will be more precise, more effective and have many more options.

Related blog posts:

Banning Mills

Banning Mills


Using Ustekinumab for Crohn’s Disease

From GI & Hepatology News: New targeted Crohn’s therapy performs well in phase III trial.

This study of Ustekinumab (aka Stelara) was different than previous studies (see previous gutsandgrowth blog from 2012: Ustekinumab for Crohn’s disease) in that this study targeted patients who were NOT ant-TNF failures; however, about 80% of patients had failed corticosteroids.

An excerpt:

Ustekinumab, a monoclonal antibody targeted against interleukins 12 and 23 (IL-12 and IL-23)…

 The trial, called UNITI-2, enrolled patients with moderate to severe Crohn’s disease who had failed traditional therapies but were naive to or at least had not failed a tumor necrosis factor (TNF) inhibitor…

In UNITI-2, 628 patients were randomized to placebo, 130 mg of ustekinumab in a fixed subcutaneous dose of 130 mg, or a weight-based dose of 6 mg/kg of subcutaneous ustekinumab…The primary endpoint was a CDAI reduction of at least 100 points at 6 weeks. Clinical remission at 8 weeks, defined as CDAI less than 150, was a secondary endpoint.

The primary endpoint was reached by 28.7% randomized to placebo, 51.7% of those randomized to the fixed dose of ustekinumab, and 55.5% of those randomized to weight-based dosing. The advantage for the active treatment arms was statistically significant (both P less than .001). For the secondary endpoint of clinical remission at 8 weeks, the rates were 19.6% for placebo, 30.6% (P = .009 vs. placebo) for fixed-dose ustekinumab, and 40.2% (P less than .001 vs. placebo) for the weight-based dose…

Ustekinumab was well tolerated with similar rates and types of adverse events reported in the active treatment and placebo groups.

My take: This study indicates that ustekinumab is likely to be another treatment option for patients with Crohn’s disease.

Nutrition Symposium Georgia AAP (Part 1)

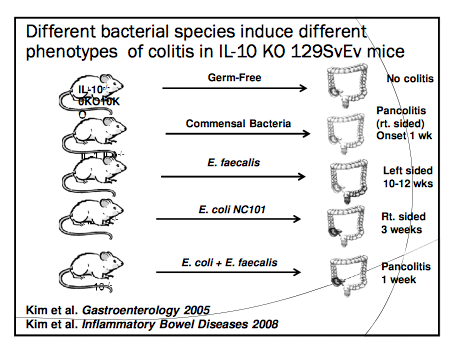
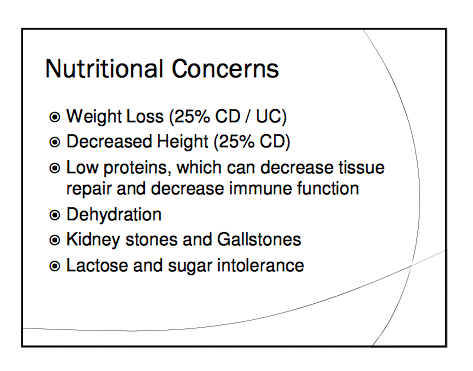
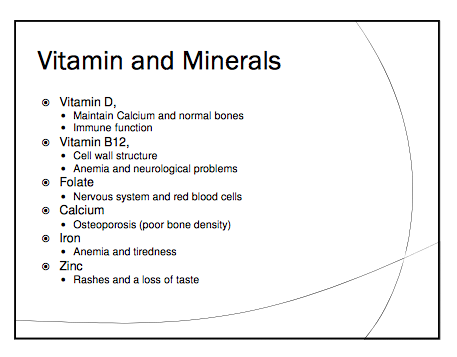
At this year’s nutrition symposium, Dr. Stan Cohen presented the latest information on nutrition and inflammatory bowel disease.  His entire presentation will be on the Nutrition4Kids website.  While I took a few pictures, my notes from his presentation were minimal, mainly because I had to give a talk afterwards.  He reviewed how the microbiome can be influenced by diet and that this in turn can result in phenotypic changes.  Specific complications from poor diet/nutrient deficiencies were discussed.  In addition, data from exclusive enteral nutrition and the specific carbohydrate diet were presented. Here are some slides from his lecture (also available at Georgia AAP Symposium Website):

Screen Shot 2015-11-13 at 5.55.55 PM

Screen Shot 2015-11-13 at 5.57.12 PM

Screen Shot 2015-11-13 at 5.57.27 PM

Screen Shot 2015-11-13 at 6.01.10 PM

Related blog posts:


Why the Genetics of Inflammatory Bowel Diseases Matter Now

A terrific update on the genetics of inflammatory bowel diseases (DPB McGovern, S Kugathasan, JH Cho. Gastroenterol 2015; 149: 1163-76) explains why and how this information matters right now.  The article is a little difficult to read due to its review of highly technical material.

Here’s what I think were the key points:

  • Big advances in understanding the genetics started with the first genome-wide association studies (GWAS) using genome-wide single nucleotide polymorphisms (SNP) chips in 2005.  “The conceptual basis of GWAS is that most complex (ie, not single-gene Mendelian) genetic disorders are polygenic, being driven by multiple common genetic polymorphisms.”
  • “Early GWAS identified the most significant loci.”  Now, more than 200 loci associated with IBD have been identified with GWAS and Immunochip data. Table 1 lists these loci over 4 pages.  About 2/3rds of these are associated with Crohn’s disease (CD) and ulcerative colitis (UC) whereas the remaining 1/3rd are unique to either CD or UC.
  • These loci provide insight into disease mechanisms. NOD2 mutations result in “impaired activation of NF-κB” This supported “the general concept that deficiencies of innate immune cell function represent a central factor in Crohn’s disease, distinguishing it from ulcerative colitis.”
  • ATG16L1 gene mutation “establish the fact that the CD risk allele is correlated with impaired autophagy.”  This is leading directly into treatment efforts.
  • IL23R.  “The most significant association is Arg381Gln…confers a 2- to 3-fold protection against development of IBD.”  The protective effect is thought to be due to “decreased numbers of interleukin (IL)-23 dependent CD4+ Th17 and CD8+ Tc17 cells…decreasing IL-23 signaling, such as through monoclonal antibody blockade of anti-p40 or anit-p19 may be beneficial.”
  • FUT2 mutations.  These mutations affect the mucus layer in Crohn’s disease.
  • Studies in non-Caucasians highlight other susceptibility regions.
  • “Currently, sequencing of the whole exome has become not only a practical method but also a cost-effective option to identify functionally relevant variants in the protein encoding regions of the genome.”

Very Early Onset IBD:

  • Whole exome sequencing (WES) identified XIAP (X-linked inhibitor of apoptosis) in a case of boy with very early onset (VEO) IBD.  XIAP is a positive regulator of NOD2 function.  WES has also identified FOXP3, and IL10RB genes.
  • “The VEO group experiences a more severe disease course and more frequently shows a positive family history for IBD in support of higher genetic load.”  Table 2 lists ~40 genes associated with VEO.  These genes are involved in epithelial barrier function, neutropenia/defects in phagocyte function, hype-and autoinflammation, and  regulatory T cells and immune regulation.

Genetic Testing Will Impact Current Therapies and Help Explain Extraintestinal Manifestations:

  • Currently testing for TPMT variations is recommended prior to use of thiopurines due to concerns of toxicity in individuals with decreased metabolism of these medications.  However, genetic testing can identify other individuals with propensity to leukopenia (eg. NUDT15 polymorphism) and those with increase risk for pancreatitis (eg. HAL-DQA1-HLA-DRB1)
  • Primary Sclerosing Cholangitis (PSC) is associated with numerous genetic loci as well. PSC “genetically is more similar to UC than to CD.” Most other extraintestinal manifestation studies have been underpowered.
  • IBD share more genetic similarity to spondyloarthropathy (SpA) than any other immune-mediated diseases.  “The vast majority of shared susceptibility loci are concordant between IBD and SpA.”
  • With regard to psoriasis, the genetic relationship to IBD is complex.  Anti-TNF agents can cause psoriaform lesions in IBD patients.  In addition, anti-IL17a therapy, “so successful in psoriasis, appears to worsen Crohn’s disease” but not in those with a TNFSF15 variant.  Specific genotyping may help identify which patients with CD are susceptible to psoriaform lesions and those who may improve with therapy typically given for psoriasis.

My take: This article shows how understanding genetics of IBD is providing insight into pathophysiology and more personalized treatment approaches.

Briefly noted: EM Stoffel, CR Boland. Gastroenterol 2015; 149: 1191-1203. Excellent review of the genetics and genetic testing for Hereditary Colorectal Cancer.  The review includes polyposis syndromes and Lynch syndrome.

Atlanta Botanical Gardens

Atlanta Botanical Gardens

What is Your Infliximab Adherence Rate?

I started thinking about this question after a recent study (DS Vitale, et al. JPGN 2015; 61: 408-10) examined adherence at a single pediatric center (2010-2012). Adherence indicated “those who attended >80% of scheduled infusions.” Key findings:

  • 91.4% adherence rate of patients (n=151 with >4 infusions)
  • Adherent patients (n=138) attended an average of 98% of their infusions. Nonadherent patients attended, on average, 76% of their infusions.
  • The study provided some preliminary evidence that there was greater acute care use in nonadherent patients.
  • There were no demographic features that could predict adherence pattern.

My take: One of the key advantages of infusion therapy is improved and documented adherence.  Infusions also provide opportunities to assess patient in a scheduled manner. This study shows that subsets of patients with scheduled infusions have suboptimal adherence  — another target for quality improvement!

Atlanta Botanical Gardens, Bruce Munro Exhibit

Atlanta Botanical Gardens, Bruce Munro Exhibit


Be Aggressive! Treating Anemia Associated with Inflammatory Bowel Disease

A number of recent publications have made the point that anemia is a biomarker for severe inflammatory bowel disease and undertreatment affects quality of life. Reading one of the more recent studies (IE Koutroubakis et al. Clin Gastroenterol Hepatol 2015; 13: 1760-66) brought to mind the high school football cheer: Be Aggressive!

This particular retrospective study involved 410 patients (245 with Crohn’s disease, 165 with ulcerative colitis) from 2009-2013.  This study is from the same group that published data on a somewhat smaller cohort and showed that IBD treatment alone often will not resolve anemia (Koutroubakis, IE et al. Inflamm Bowel Dis 2015; 21: 1587-93–see previous blog links).

Key findings:

  • Prevalence of anemia: 37.2% in 2009 and 33.2% in 2013
  • Anemia was associated with increased hospitalizations (P<.01), clinic visits (P<.001), telephone calls (P<.004), surgeries for IBD (P=.001), and lower quality of life scores (P<.03)

The associated editorial (pgs 1767-69) suggests that IBD-related anemia, if mild (w/in 1 g/L below normal) to treat with oral iron replacement and if moderate-to-severe, then to replace intravenously (using Ganzoni’s formula calculator). In addition, if anemia is not improving, looking for alternative explanations (e.g. vitamin B12 or folate deficiency) is recommended.

Ganzoni Equation: Total Iron Deficit = Weight {kg} x (Target Hb – Actual Hb) {g/l} x 2.4 + Iron stores {mg}.   Iron stores: { 500 if W > 35kg } & { 15 mg/kg if W < 35kg }

My take: Anemia is a biomarker for severe disease.  While treating the underlying inflammatory bowel disease, don’t forget to make sure the patient’s anemia is addressed.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Central Park

Central Park