Spice It Up? Curcumin for Ulcerative Colitis

This past week I’ve been on call and had not finished a few articles.  One article that was on the to do list: A Lang et al. Clinical Gastroenter Hepatol 2015; 13: 1444-9.

I’ve read it now.  However, even before finishing the article, I read a few good summaries of this article, including one from my colleague Stan Cohen/Nutrition4Kids: Curcumin Helps (A Lot) in Ulcerative Colitis

Here’s an excerpt:

The cover of a prestigious medical journal shows a pile of curcumin and over it, the announcement reads: Curcumin Helps Induce Remission in Mild-to-Moderate Ulcerative Colitis.  That’s big news for a lot of reasons: first, this Indian spice (derived from tumeric) is inexpensive and well-tolerated; second, in a well-designed scientific study, curcumin showed that it was more effective than some medicines; and third, it showed, again, that careful trials of long-used herbs can be done with important results being shown.  Again, because an earlier study (H Hanai, Clinical Gastroenterology 2006, pages 1502-6) had previously shown that curcumin can help keep ulcerative colitis (UC) patients from flaring for up to 12 months. 

This new study (A Lang, Clinical Gastroenterology 2015, pages 1444-9) compared curcumin to a placebo in patients who were not doing well on the standard therapy (mesalamine) for mild to moderate UC.  With a single daily dose of 3 grams of curcumin in capsule form, 65% responded (compared to 12% with a placebo) and 54% actually went into remission, having essentially no symptoms.  Perhaps even, more importantly, 38% of those taking the curcumin showed improvement in the intestinal tissue when a colonoscopy was performed.  That’s comparable or better than some of the medications that are being used.

A few other details: The researchers used a product called Cur-Cure from Bara Herbs Inc (Yokneam, Israel).  Also, the associated commentary in the same journal by CN Bernstein (pages 1450-52) suggests that the study may have targeted mild ulcerative colitis (rather than moderate ulcerative colitis). He comments that the increasing rates of ulcerative colitis among Indian immigrants could be related to including less curcumin in their now more westernized diets.  He also notes, as did Dr. Cohen, that there were previous promising studies dating back to 2006.  Why has it taken nine years for this report?

My Take: This is probably an article worth reading.  Although curcumin appears promising, I worry that a lack of financial incentive may hamper research efforts to better define its place as an agent for treatment of ulcerative colitis.

Related blog posts:

Curcumin

This has been a sad week in our office.  Here are links to two poems that come to mind:

Not Using and Stopping Therapy in IBD

Two recent articles show that a lot of patients are not receiving much therapy in inflammatory bowel disease.

  • Moreno-Rincon E et al. Inflamm Bowel Dis 2015; 21: 1564-71.
  • Melesse DY et al. Inflamm Bowel Dis 2015; 21: 1615-22.

In the first article, a multicenter retrospective study of 102 patients, the authors examined the relapse rates of patients with ulcerative colitis who had withdrawal of thiopurines.  They defined “significant clinical relapse” (SCR) as “the occurrence of UC typical signs or symptoms requiring a rescue therapy such as oral or intravenous corticosteroids, biological therapy, immunosuppressant drugs, recapture with TP [thiopurine] or surgery.”

Key findings:

  • Overall SCR was 32.35%.
  • Predictors of relapse included pancolitis (HR 5.01) and duration of treatment with thiopurines (HR 0.15).

Among those without relapse, the mean duration of remission prior to withdrawal of thiopurines was 54 months compared with 34 months in those who relapsed. In figure 2, the authors note that the rate of relapse was 19.2% for those who received >48 months of thiopurine treatment compared with a 45% rate of relapse for those who received treatment for 13-47 months.  The authors note that several studies have shown higher relapse rates than reported in this cohort and that interruption of therapy is associated with a considerable risk of relapse.

Limitations: small retrospective study and the expectation that their SCR would capture the true relapse rate.

The second study, using a Manitoba database, shows a strikingly-high rate of nonuse of medical therapy. Between 1996-2012, 3902 patients with IBD were identified; 47% with Crohn’s disease (CD) and 53% with ulcerative colitis (UC).  While only 11.7% of IBD patients did not have medication dispensed in the first year after diagnosis, beyond this period, “roughly half of all patients with IBD have not used IBD-specific medications in the previous year.”  The authors are not certain how much nonuse is due to nonadherence or nonprescription. They note that there was higher nonuse in patients with CD, possibly due to use of surgical treatment.  However, they note that multiple medications have been shown to reduce postsurgical relapse in CD.

My take: There are a lot of patients off therapy, both due to withdrawal of therapy when doing well and others due to nonadherence or nonprescription.  With or without overt symptoms, these studies make one wonder whether undertreatment will lead to long-term complications or whether there could be a significant number of patients who are overtreated.  Either way, it remains quite difficult to predict which patients will do well off medical therapy.

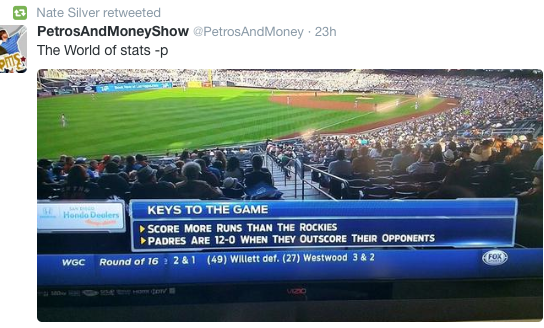
Broadcasters Really Know the Key Points to Winning!

Broadcasters Really Know the Key Points to Winning!

Is It Right? Anti-TNF Therapy Does Not Fix IBD-Related Anemia

A surprising study (Koutroubakis, IE et al. Inflamm Bowel Dis 2015; 21: 1587-93) of prospectively-collected data from 430 patients with inflammatory bowel disease (IBD) showed that the rate of anemia did not change after 1 year in patients treated with anti-tumor necrosis factor (anti-TNF) therapy and oral iron.

The data was derived from 2010-2012 and included 324 patients with Crohn’s disease (51.6% females) with a median age of 41 years.  Anemia was defined as hemoglobin (Hb) <13 g/dL in men and <12 g/dL in women.  Patients with Hb <10 g/dL were considered to have severe anemia. Key findings:

  • Prevalence of anemia in IBD patients treated with anti-TNF was 38.1% at baseline and then 36.6% at 1 year.
  • Severe anemia was identified in 10% at baseline and 9.9% at 1 year.
  • A hematopoietic response with a Hb ≥2 g/dL was observed in 33.6% (n=45 of 134 anemic patients) and 14 (40%) of those with severe anemia.
  • There were 45 new anemic patients at 1 year; 64.4% were nonresponders to anti-TNF treatment.
  • Using multivariate logistic regression analysis, the author noted that use of immunomodulators was associated with an odds ratio of 2.56 of improvement in hemoglobin levels.

The authors state that anemia is the most common extra intestinal manifestation of IBD and remains underappreciated.  Anemia in IBD correlates with the extent of intestinal disease and activity.

Bottomline: “Use of anti-TNF therapy had only a modest effect on patients’ Hb level.”

From related post: IBD Update January 2015 (Part 2)

Inflamm Bowel Dis 2014; 20: 2266-70.  This study with 749 patients from Sweden showed that a large number of inflammatory bowel disease patients did not receive with iron supplementation: “Only 46% of patients with anemia were treated with iron supplementation or blood transfusion.”  This study showed frequent persistence of anemia one year after diagnosis, especially in children. At time of diagnosis, 55% of children and 27% of adults had anemia and 28% and 16% at one year followup, respectively.

My take: Treatment of the underlying IBD, often helps anemia.  However, in some patients treating the anemia with iron may help improve symptoms as much or more than other aspects of treatment.

Related blog post: Microcytic Anemia Review | gutsandgrowth

Sandy Springs, Georgia

Sandy Springs, Georgia


Ulcerative Colitis with Questionable Response to Fecal Transplant

Fecal microbiota transplantation (FMT) is not going to be a “magic bullet” for most patients with inflammatory bowel disease. So far, it is unclear whether FMT works at all.  A recent study (full text link: Rossen NG et al. Gastroenterol 2015; 145: 110-8) with only 37 patients echo that experience. Here is the abstract:

Background & Aims

Several case series have reported the effects of fecal microbiota transplantation (FMT) for ulcerative colitis (UC). We assessed the efficacy and safety of FMT for patients with UC in a double-blind randomized trial.

Methods

Patients with mild to moderately active UC (n = 50) were assigned to groups that underwent FMT with feces from healthy donors or were given autologous fecal microbiota (control); each transplant was administered via nasoduodenal tube at the start of the study and 3 weeks later. The study was performed at the Academic Medical Center in Amsterdam from June 2011 through May 2014.

The composite primary end point was clinical remission (simple clinical colitis activity index scores ≤2) combined with ≥1-point decrease in the Mayo endoscopic score at week 12. Secondary end points were safety and microbiota composition by phylogenetic microarray in fecal samples.

Results

Thirty-seven patients completed the primary end point assessment. In the intention-to-treat analysis, 7 of 23 patients who received fecal transplants from healthy donors (30.4%) and 5 of 25 controls (20.0%) achieved the primary end point (P = .51). In the per-protocol analysis, 7 of 17 patients who received fecal transplants from healthy donors (41.2%) and 5 of 20 controls (25.0%) achieved the primary end point (P = .29). Serious adverse events occurred in 4 patients (2 in the FMT group), but these were not considered to be related to the FMT. At 12 weeks, the microbiota of responders in the FMT group was similar to that of their healthy donors; remission was associated with proportions of Clostridium clusters IV and XIVa.

Conclusions

In this phase 2 trial, there was no statistically significant difference in clinical and endoscopic remission between patients with UC who received fecal transplants from healthy donors and those who received their own fecal microbiota, which may be due to limited numbers. However, the microbiota of responders had distinct features from that of nonresponders, warranting further study. ClinicalTrials.gov Number: NCT01650038.

Related blog posts:

Cumberland Island

Cumberland Island


Will Infliximab Worsen Flare-ups Associated with Cytomegalovirus Infection?

Another look (Pillet S, et al. Inflamm Bowel Dis 2015; 21: 1580-86) at Cytomegalovirus (CMV) infection in patients with ulcerative colitis (UC) examines 109 flareups in 73 patients who were receiving maintenance therapy with anti-TNF therapy.

This was a single-center prospective observational study.  CMV load was determined with PCR based on a pair of biopsies. DNA load was either undetectable, mild (10-250 copies/mg of tissue) or high (>250 copies/mg of tissue). 69 patients with anti-TNF therapy were compared with 40 patients receiving azathioprine. Key findings:

  • CMV reactivation was noted in 35% of anti-TNF therapy patients and 38% in azathioprine patients.
  • Among 45 patients requiring infliximab optimization, clinical remission was not significantly impacted by the presence of CMV reactivation.
  • 17 of 20 who had repeat biopsies 8 weeks later had stable or decreased CMV load.

Bottomline: This prospective, small study shows that “in patients with moderate-to-severe UC, treatment with anti-TNF mab does not increase the risk of colonic CMV infection.”  In addition, “no adverse influence of CMV colonic infection was observed in patients with flare-up treated by anti-TNF mabs.”

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Zoo Atlanta

Zoo Atlanta

Utility of Antiviral Therapy for Cytomegalovirus in the Setting of Inflammatory Bowel Disease

According to a recent study (Jones A et al. Clin Gastroenterol Hepatol 2015; 13: 949-55), the tissue density of cytomegalovirus (CMV) is an important determinant of antiviral response in patients with inflammatory bowel disease (IBD).

In this case-control study, the authors identified 68 samples from 1111 patients with IBD that were found to contain CMV.  Adequate data was available for 50, including 16 with high-grade CMV (all treated) and 34 with low-grade CMV (20 treated).  High-grade CMV was defined as biopsies with 5 or more inclusions.  Treatment included ganciclovir, valganciclovir or both; 33 of 36 treated patients received at least 21 days of therapy.

Key findings:

  • Patients with high-grade CMV showed significant benefit from treatment: they had the best outcomes with “only 33% undergoing surgery by 1 year after biopsy.”
  • All patients with low-grade CMV, treated or not, were more likely to undergo surgery than those with high-grade CMV, with HR of 2.13.  However, the treated low-grade CMV had a lower risk of surgery (HR 0.39) compared with the untreated group.  73% of the untreated low-grade CMV group had undergone resection by 1 year after biopsy.

The authors note the many limitations of the study.  Requests to rule out CMV were not done uniformly but “usually reflected refractoriness of steroids or failure to respond to escalation of therapy.”

Bottomline: In those with high-grade CMV, the likelihood of responding to antiviral therapy was much higher than in patients with low-grade CMV; however, treatment in all patients with CMV inclusions was associated with improved outcomes.

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Bird in Flowers

Money Matters in Pediatric Inflammatory Bowel Disease

A very pragmatic article (Sin AT et al. Inflamm Bowel Dis 2015; 21: 1368-77) describes the out-of-pocket cost burden in pediatric inflammatory bowel disease (IBD). For anyone who lives on planet earth, how much a procedure or treatment costs weighs very heavily on many decisions.  This is particularly relevant in pediatric IBD.

In a cross-sectional cohort analysis, the researches collected data with surveys from 150 parents of children with IBD (67 Crohn’s disease, 83 Ulcerative colitis).  The median patient age was 14 years.

Findings:

  • Annually, out-of-pocket expenses were >$5000 in 5.3%, >$1000 in 28.6%, and >%500 in 63.6%.
  • Increased expenditures were derived from the following: emergency department visits with 36% having had an ED visit in past year, procedures/testing with 20% who spent >$2000, and from treatments (medications/diet).  10.7% reported missing medications due to cost.
  • “Families with household incomes between $50,000-100,000 had a statistically-significant probability (80.6%) of higher annual OOP costs than families with lower income…or higher income.”
  • Not surprisingly, patients with IBD “who have relapsing or uncontrolled IBD states are particularly at risk to require acute care services, which represent high OOP costs for families.”
  • The authors also describe missed workdays and lost wages as another financial burden.

Take-home message: This study helps quantitate the out-of-pocket expenses and financial burden that families face when they have a child with IBD.  In some patients, improved control of IBD will lower these expenses by decreasing costs from emergency department visits, office visits, and hospitalizations.

Cumberland Island

Cumberland Island

Cancers Complicating Inflammatory Bowel Disease

In several prior posts, the issue of cancer and inflammatory bowel disease (IBD) has been discussed.  In my view, even the word “cancer” is so scary that it can make people make bad choices (related: Facts, “Misfearing” and Women’s Health | gutsandgrowth).  An up-to-date succinct summary (Laurent Beaugerie, M.D., Ph.D., and Steven H. Itzkowitz, M.D. N Engl J Med 2015; 372:1441-1452) provides a fairly good overview of “Cancers Complicating Inflammatory Bowel Disease.”

Key points:

  • “Smokers are overrepresented among the patients with Crohn’s disease…results in an excess rate of smoking related cancers.” (Smoking also is associated with more aggressive Crohn’s)
  • Colorectal cancers risk factors (Table 1), specific to IBD, include coexisting primary sclerosing cholangitis (PSC), and increasing duration & extent of colonic IBD.
  • A “progressive decrease in the excess risk of colorectal cancer in patients with IBD has been noted over time.”  This may be due to better control of inflammation, surveillance, and colectomy.  Still, the risk of colorectal cancer in patients with IBD is 1.5 to 2 times greater than the general population risk.
  • Small-bowel adenocarcinoma –risk is 20-30 times that of the general population, typically arises more than 8 years after diagnosis.  Absolute risk in those with disease more than 8 years is estimated at “0.5 per 1000 patient-years.”
  • Intestinal lymphomas –absolute risk is about 0.1 per 1000 patient-years.
  • Cholangiocarcinoma (CCA)–absolute risk is approximately “0.08 per 1000 patient-years.” CCA is mainly evident in patients with PSC who have a risk ~160 times the general population and lifelong risk of 5-10%.
  • Non-Hodgkin’s lymphoma –“whether TNF-alpha antagonists promote lymphomas by themselves in patients with IBD is difficult to assess…” A recent study found no excess risk in patients receiving TNF-alpha antagonists after adjustments for cotreatments.
  • Skin Cancers –nonmelanoma skin cancer, though not life-threatening, occur more often in those with current thiopurine usage.
  • HPV-Related Cervical Cancer –“it is still unclear whether the risk of HPV-related cervical cancer is intrinsically increased in woman with IBD or independently worsened by exposure to an immunosuppressant.”
  • Thiopurines: “after adjustment for confounders, current use of thiopurines for IBD has been shown to be associated with an overall relative risk of cancer of 1.3 to 1.7.”
  • TNF-alpha antagonists: “There is no overall excess risk of cancer in patients treated with TNF-alpha antagonists for IBD.”  However, more long-term data are needed.

Recommendations:

  • Figure 2 provides recommendations for colorectal cancer surveillance based on the American Gastroenterological Association (AGA), British Society of Gastroenterology (BSG) and European Crohn’s and Colitis Organisation (ECCO) recommendations. Typically, 8-10 years after diagnosis of colitis, starting surveillance (with chromoendoscopy if available) is recommended.  In patients with Crohn’s disease, “the excess risk appears when more than 30 to 50% of the colonic surface is ever involved.” However, with PSC, the excess risk of colorectal cancer is significant at the time of diagnosis.
  • For cholangiocarcinoma screening in those with PSC, “most experts recommend noninvasive annual imaging of the biliary tract (MRCP or ultrasound) and serum CA 19-9.”
  • For HPV, vaccination is recommended and regular Papanicolaou tests

Take-home message: Some cancers are increased in association with IBD.  However, the medications, particularly immunosuppressants, may reduce the incidence of inflammation-related cancers…or promote immunosuppression-related cancers.

Related blog posts:

Sandy Springs

Sandy Springs

Working on Transition Readiness

A recent study (Gray WN, et al. Inflamm Bowel Dis 2015; 21: 1125-31) examines preparedness of patients with inflammatory bowel disease (IBD) on the verge of transitioning to adult gastroenterologists from pediatric gastroenterologists.

Using a population of 195 patients (16-25 years), the authors used the Transition Readiness Assessment Questionnaire (TRAQ).  Scoring system:

  • 5= Yes, I always do this when I need to
  • 4= Yes, I have started doing this
  • 3= No, but I am learning to do this
  • 2= No, but I want to learn
  • 1= No, I do not know how

Specific Readiness Skills & Mean Scores (more complete data listed in Table 3):

  • Taking medicines correctly and on own 4.66
  • Arranging for ride to medical appointment 4.39
  • Managing money and budgeting 3.69
  • Calling doctor about unusual change in health 3.64
  • Reordering and getting refills on time 3.60
  • Calling doctor’s office to schedule an appointment 3.09
  • Getting financial help with school or work 2.92
  • Knowing what health insurance covers 2.60
  • Applying for health insurance if coverage lost 2.44

Key finding: “Only 5.6% older adolescents/young adults …met our institutional benchmark.”

To help with transition readiness the authors recommend the CDHNF/NASPGHAN Transition Checklist for parents and starting on transition issues between 12-15 years of age.  Transition checklist available here: Transitioning a Patient With IBD From Pediatric to Adult Care –this is a simple 2-page handout!

Conclusion: Most patients need more work on transition readiness.  If patients are not prepared, it is more likely that this will lead to medical setbacks.

Briefly noted:

“Exercise Decreases Risk of Future Active Disease in Patients with Inflammatory Bowel Disease in Remission” Inflammatory Bowel Dis 2015; 21: 1063-71. This prospective study used the CCFA’s Partners’ internet-based cohort. 227 of 1308 (17.4%) Crohn’s disease (CD) patients and 135 of 549 (24.6%) Ulcerative colitis/indeterminate colitis (UC/IC) patients developed active disease after 6 months.  Key finding: Higher exercise level was associated with decreased risk of active disease for CD (adjusted relative risk 0.72) and UC/IC (adjusted relative risk 0.78).  Take-home point: While there are several limitations to this study, it does seem likely that regular physical exercise is a good idea (not just in patients with IBD).  In this population, subjective markers of disease activity (sCDAI and SCCAI) improved in those who exercised more.

Zoo Atlanta

Zoo Atlanta

Increasing Inflammatory Bowel Disease Among U.S. Patients From India

An interesting epidemiology study (Malhotra R, et al. Clin Gastroenterol Hepatol 2015; 13: 683-89) shows a high prevalence of inflammatory bowel disease among U.S. residents with Indian Ancestry.

Using a national pathology database on 1,027,977 subjects who had ileocolonic biopsies from 2008-2013, the authors identified 30,812 patients who were diagnosed with inflammatory bowel disease (IBD): 20,308 with ulcerative colitis (UC), 7706 with Crohn’s disease (CD), and 2798 with indeterminate colitis (IC).

Key findings:

  • Among patients with Indian ancestry, the overall prevalence of IBD was 9.1% (n=197 compared with 1960 controls) compared with 4.3% for those of Jewish ethnicity, 2.4% for hispanic ethnicity, and 1.4% for East Asian ethnicity.  The adjusted odds ratio for patients with Indian ancestry was 2.5.
  • In addition, UC was predominant, accounting for 153 of the 197 cases; 26 were diagnosed with CD and 18 were IC.  IBD and UC were highest in subjects with roots in Gujarat.

Take-home point (from authors): “Considering the reported relatively low prevalence of IBD in India, these findings suggest that genetic factors may interact with new environmental conditions to trigger the expression of disease.”

Related blog post: Emigration -One Way to Acquire IBD

Briefly Noted:

Rungoe C, et al. “Inflammatory Bowel Disease and Cervical Neoplasia: A Population-Based Nationwide Cohort Study” Clin Gastroenterol Hepatol 2015; 13: 693-700. Using a Dutch national cohort with more than 27,000 patients, the authors showed a “2-way association between IBD, notably CD, and neoplastic lesions of the uterine cervix.” Overall the risk was mildly increased; for CD, the incidence rate ratio of cervical cancer was 1.53 (CI 1.04-2.27).

Reinisch W, et al. “Factors Associated with Poor Outcomes in Adults with Newly Diagnosed Ulcerative Colitis” Clin Gastroenterol Hepatol 2015; 13: 635-42. The tables in this article summarize clinical characteristics, biologic markers, and treatment factors associated with poor outcomes.  For clinical factors, younger age at diagnosis and age >65 years increase the risk for more severe disease. For biomarkers, increased CRP, ESR, and cal protection were associated with higher risk of progressing to colectomy. For treatment factors, not surprisingly, failing to respond to therapy and absence of mucosal healing were associated with higher risk of progressing to colectomy.

Chattahoochee River National Recreation Area

Chattahoochee River National Recreation Area