Ozanimod for Ulcerative Colitis

The results of a phase 2 trial for Ozanimod have been published: WJ Sandborn et al. NEJM 2016; 374; 1754-62.

Ozanimod (RPC1063) is “an oral agonist of the sphingosine-1-phosphate receptor subtypes 1 and 5 that induces peripheral lymphocyte sequestration, potentially decreasing the number of activated lymphocytes circulating to the gastrointestinal tract.”

From the abstract:

METHODS

We conducted a double-blind, placebo-controlled phase 2 trial of ozanimod in 197 adults with moderate-to-severe ulcerative colitis. Patients were randomly assigned, in a 1:1:1 ratio, to receive ozanimod at a dose of 0.5 mg or 1 mg or placebo daily for up to 32 weeks. The Mayo Clinic score was used to measure disease activity on a scale from 0 to 12, with higher scores indicating more severe disease; subscores range from 0 to 3, with higher scores indicating more severe disease. The primary outcome was clinical remission (Mayo Clinic score ≤2, with no subscore >1) at 8 weeks.

RESULTS

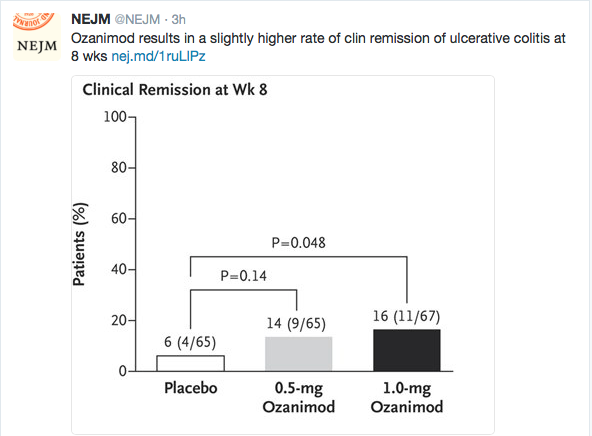
The primary outcome occurred in 16% of the patients who received 1 mg of ozanimod and in 14% of those who received 0.5 mg of ozanimod, as compared with 6% of those who received placebo (P=0.048 and P=0.14, respectively, for the comparison of the two doses of ozanimod with placebo). Differences in the primary outcome between the group that received 0.5 mg of ozanimod and the placebo group were not significant; therefore, the hierarchical testing plan deemed the analyses of secondary outcomes exploratory. Clinical response (decrease in Mayo Clinic score of ≥3 points and ≥30% and decrease in rectal-bleeding subscore of ≥1 point or a subscore ≤1) at 8 weeks occurred in 57% of those receiving 1 mg of ozanimod and 54% of those receiving 0.5 mg, as compared with 37% of those receiving placebo. At week 32, the rate of clinical remission was 21% in the group that received 1 mg of ozanimod, 26% in the group that received 0.5 mg of ozanimod, and 6% in the group that received placebo; the rate of clinical response was 51%, 35%, and 20%, respectively. At week 8, absolute lymphocyte counts declined 49% from baseline in the group that received 1 mg of ozanimod and 32% from baseline in the group that received 0.5 mg. The most common adverse events overall were anemia and headache.

CONCLUSIONS

In this preliminary trial, ozanimod at a daily dose of 1 mg resulted in a slightly higher rate of clinical remission of ulcerative colitis than placebo. The trial was not large enough or of sufficiently long duration to establish clinical efficacy or assess safety. (Funded by Receptos; TOUCHSTONE ClinicalTrials.gov number, NCT01647516.)
Ozanimod

Related blog post: CCFA Conference Notes 2016 (part 5) -Emerging Therapies …
 

More on Anti-TNF Drug Levels (part 2) and a Few Mentions

Another study (K Papamichael et al. Clin Gastroenterol Hepatol 2016; 14: 543-9) examined therapeutic drug levels with regard to infliximab induction and mucosal healing.

In this retrospective study with 101 patients with ulcerative colitis, 54 (53.4%) achieved mucosal healing between weeks 10-14, defined by a Mayo endoscopic score of 0 or 1.  97% of patients were treated with 5 mg/kg infusions.

Key finding:

  • Infliximab threshold concentrations of 28.3 mcg/mL at week 2, 15 mcg/mL at week 6, and 2.1 mcg/mL at week 14 were associated with mucosal healing.

My take: While this study provides information on what type of levels to expect at 2, 6, and 14 weeks, what is really important is figuring out which patients need higher doses of infusions from the start.

Unrelated, briefly noted:

R Yadlapati et al. Clin Gastroenterol Hepatol 2016; 14: 535-42. In this prospective blinded cohort study of 59 subjects, oropharyngeal pH testing (Restech Dx-pH) and salivary pepsin analysis was not able to distinguish between healthy volunteers and subjects with a combination of laryngeal and reflux symptoms.

M Moris et al. Clin Gastroenterol Hepatol 2016; 14: 585-93. This study reports increasing findings of small pancreatic cysts with more (and better) MRI imaging.

Y Kawamura et al. Clin Gastroenterol Hepatol 2016; 14: 597-605. This retrospective study shows, among almost 10,000 patients with fatty liver disease, that alcohol consumption of ≥40 g/day is an independent risk factor for hepatocellular carcinoma.

Strongloides

What happens when anti-TNF therapy is stopped

Another study (NA Kennedy et al. Aliment Pharmacol Ther 2016; 43: 910-23) has examined the issue of outcomes after anti-TNF therapy withdrawal among patients with inflammatory bowel disease.

This study included 166 UK patient cohort (117 with Crohn’s disease [median 31 yrs], 19 with ulcerative colitis [median 40 years]) as part of a retrospective observational study and a meta-analysis incorporating 11 further cohorts totalling 746 patients (624 with Crohn’s dissease, 122 with ulcerative colitis).

Key findings:

  • In the UK cohort, relapse rates were 36% at year and 56% at 2 years for Crohn’s disease
  • In the UK cohort, relapse rates were 42% at year and 47% at 2 years for ulcerative colitis
  • Increased relapse rates were noted for those with a diagnosis prior to age 22 years (hazard ratio (HR) 2.78), calprotectin >50 mcg/g (HR 2.95).
  • In meta-analysis, 1-year relapse rates were 39% for CD and 35% for UC/IBDU patients
  • Retreatment with anti-TNF was successful in 88% for CD and 76% of UC/IBDU patients

To understand this study, it is important to note some of the study criteria.  In the UK cohort, inclusion criteria required the patient to have had at least 12 months of ant-TNF therapy and be in corticosteroid-remission for at least 6 months.  In addition, the relapse rate is likely to be underestimated due to using a definition of relapse that required either commencement of steroids, immunomodulator or anti-TNF therapy.  The meta-anlaysis cohort studies also used clinical relapse rather than endoscopic or other objective markers.

My take: Relapse of clinical symptoms occur in about 40% after withdrawal in highly-selected groups who were doing well prior.  Significantly higher rates of endoscopic relapse are likely.  This study provides strong reasons for not interrupting therapy when it is working.

Related blog posts:

Cures Tshirt


CCFA Conference Notes 2016 (part 3) -Malignancy and IBD

This blog entry has abbreviated/summarized this terrific presentation; most of the material has been covered in this blog in prior entries but still this was a useful review. Though not intentional, some important material is likely to have been omitted; in addition, transcription errors are possible as well.

3rd Lecture: Prevention and management of malignancy in IBD –Dr. Thomas Ullman

Malignancy risk (colorectal cancer [CRC]) is present with prolonged ulcerative colitis, though more recent studies have shown lower risk than in the past –not much higher than the general population.

Screen Shot 2016-04-17 at 12.02.04 PM

  • CRC surveillance–colonoscopy monitoring after 8-10 years. Typically colonoscopy every other year for most patients, every year in higher risk patients (eg. PSC).

Screen Shot 2016-04-17 at 12.01.37 PM

  • Unclear if chemoprevention is effective (5-ASA, thiopurines, others).
  • Chromoendoscopy “has not been consensus on its use in our field (yet).” It is time consuming and expensive and unclear if it will improve outcome.

Does medical therapy for IBD predispose to developing cancer?

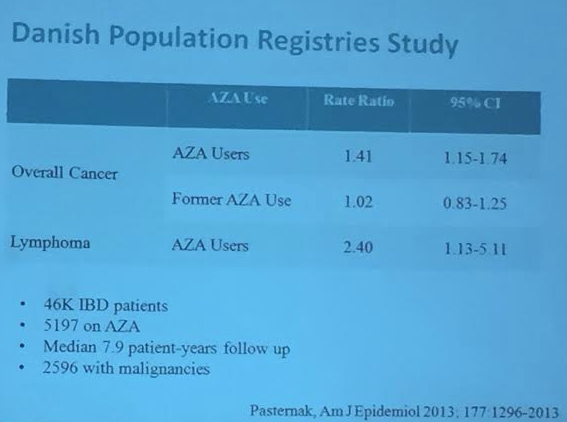
  • Thiopurines increase the risk of malignancy. (Pasternak et al) though the risk returns to near baseline when stopped according to study below.

Screen Shot 2016-04-17 at 12.03.27 PM

  • No overall increased risk with anti-TNF agents with RCTs (may not follow patients long enough) but also not seen in Danish registry either (JAMA study)
With Anti-TNFs

No increased risk of malignancy in this study with Anti-TNFs

  • Lymphoma risks: age, immunodeficiency, EBV
  • EBV negative are at risk for HLH with thiopurines
  • HTSCL ~200, >90% men and >90% <35 years. NOT EBV-related. Has not been identified in anti-TNF monotherapy.

Screen Shot 2016-04-17 at 12.02.55 PM

  • Skin cancer –main concern is in non-melanoma skin cancer (possibly melanoma too). Skin cancer increase has not been noted with methotrexate. Prevention: Skin care, and annual dermatology visits.
  • Cervical cancer—likely increased risk in IBD, probably due to thiopurine exposure and reduced immune surveillance. Prevention: HPV vaccination, Pap testing.
  • Urinary Tract cancers –especially in those >65 years with thiopurine exposure


Should Methotrexate Be Used For Ulcerative Colitis?

A recent study (F Carbonnel et al. Gastroenterol http://dx.doi.org/10.1053/j.gastro.2015.10.050, article in press; thanks to KT Park twitter feed for reference) with 111 patients provides more questions than answers.  It appears that methotrexate improved clinical remission but the overall difference is fairly small; the abstract is below.

My initial impression: Immunomodulators (including methotrexate and thiopurines) have some efficacy as monotherapy agents in patients with inflammatory bowel disease. Their role as part of combination therapy (with anti-TNF agents) has been associated with improved outcomes but how long to use combination therapy and at what dosage is still being worked out.

Here’s the abstract and a link: Methotrexate is not Superior to Placebo in Inducing Steroid-free Remission, but Induces Steroid-free Clinical Remission in a Larger Proportion of Patients with Ulcerative Colitis

Background & Aims

Parenteral methotrexate is an effective treatment for patients with Crohn’s disease but has never been adequately evaluated in patients with ulcerative colitis (UC). We conducted a randomized controlled trial to determine its safety and efficacy in patients with steroid-dependent UC.

Methods

We performed a double-blind, placebo-controlled trial to evaluate the efficacy of parenteral methotrexate (25 mg/week) in 111 patients with corticosteroid-dependent UC at 26 medical centers in Europe, from 2007 through 2013. Patients were given prednisone (10 to 40 mg/day) when the study began, and randomly assigned to groups (1:1) given placebo or methotrexate (intramuscularly or subcutaneously, 25 mg weekly) for 24 weeks. The primary endpoint was steroid-free remission (defined as a Mayo score ≤ 2 with no item > 1 and complete withdrawal of steroids) at week 16. Secondary endpoints included clinical remission (defined as a Mayo clinical subscore ≤ 2 with no item > 1) and endoscopic healing without steroids at weeks 16 and/or 24, remission without steroids at week 24, and remission at both weeks 16 and 24.

Results

Steroid-free remission at week 16 was achieved by 19/60 patients given methotrexate (31.7%) and 10/51 patients given placebo (19.6%)—a difference of 12.1% (95% confidence interval [CI], –4.0% to 28.1%; P=.15). The proportions of patients in steroid-free clinical remission at week 16 were 41.7% in the methotrexate group and 23.5% in the placebo group, for a difference of 18.1% (95% CI, 1.1%–35.2%; P=.04). The proportions of patients with steroid-free endoscopic healing at week 16 were 35% in the methotrexate group and 25.5% in the placebo group—a difference of 9.5% (95% CI, –7.5% to 26.5%; P=.28). No differences were observed in other secondary endpoints. More patients receiving placebo discontinued the study because of adverse events (47.1%), mostly caused by UC, than patients receiving methotrexate (26.7%; P=.03). A higher proportion of patients in the methotrexate group had nausea and vomiting (21.7%) than in the placebo group (3.9%; P=.006).

Conclusions

In a randomized controlled trial, parenteral methotrexate was not superior to placebo for induction of steroid-free remission in patients with UC. However, methotrexate induced clinical remission without steroids in a significantly larger percentage of patients, resulting in fewer withdrawals from therapy due to active UC.

Related blog posts:

Banning Mills

Banning Mills

Why the Genetics of Inflammatory Bowel Diseases Matter Now

A terrific update on the genetics of inflammatory bowel diseases (DPB McGovern, S Kugathasan, JH Cho. Gastroenterol 2015; 149: 1163-76) explains why and how this information matters right now.  The article is a little difficult to read due to its review of highly technical material.

Here’s what I think were the key points:

  • Big advances in understanding the genetics started with the first genome-wide association studies (GWAS) using genome-wide single nucleotide polymorphisms (SNP) chips in 2005.  “The conceptual basis of GWAS is that most complex (ie, not single-gene Mendelian) genetic disorders are polygenic, being driven by multiple common genetic polymorphisms.”
  • “Early GWAS identified the most significant loci.”  Now, more than 200 loci associated with IBD have been identified with GWAS and Immunochip data. Table 1 lists these loci over 4 pages.  About 2/3rds of these are associated with Crohn’s disease (CD) and ulcerative colitis (UC) whereas the remaining 1/3rd are unique to either CD or UC.
  • These loci provide insight into disease mechanisms. NOD2 mutations result in “impaired activation of NF-κB” This supported “the general concept that deficiencies of innate immune cell function represent a central factor in Crohn’s disease, distinguishing it from ulcerative colitis.”
  • ATG16L1 gene mutation “establish the fact that the CD risk allele is correlated with impaired autophagy.”  This is leading directly into treatment efforts.
  • IL23R.  “The most significant association is Arg381Gln…confers a 2- to 3-fold protection against development of IBD.”  The protective effect is thought to be due to “decreased numbers of interleukin (IL)-23 dependent CD4+ Th17 and CD8+ Tc17 cells…decreasing IL-23 signaling, such as through monoclonal antibody blockade of anti-p40 or anit-p19 may be beneficial.”
  • FUT2 mutations.  These mutations affect the mucus layer in Crohn’s disease.
  • Studies in non-Caucasians highlight other susceptibility regions.
  • “Currently, sequencing of the whole exome has become not only a practical method but also a cost-effective option to identify functionally relevant variants in the protein encoding regions of the genome.”

Very Early Onset IBD:

  • Whole exome sequencing (WES) identified XIAP (X-linked inhibitor of apoptosis) in a case of boy with very early onset (VEO) IBD.  XIAP is a positive regulator of NOD2 function.  WES has also identified FOXP3, and IL10RB genes.
  • “The VEO group experiences a more severe disease course and more frequently shows a positive family history for IBD in support of higher genetic load.”  Table 2 lists ~40 genes associated with VEO.  These genes are involved in epithelial barrier function, neutropenia/defects in phagocyte function, hype-and autoinflammation, and  regulatory T cells and immune regulation.

Genetic Testing Will Impact Current Therapies and Help Explain Extraintestinal Manifestations:

  • Currently testing for TPMT variations is recommended prior to use of thiopurines due to concerns of toxicity in individuals with decreased metabolism of these medications.  However, genetic testing can identify other individuals with propensity to leukopenia (eg. NUDT15 polymorphism) and those with increase risk for pancreatitis (eg. HAL-DQA1-HLA-DRB1)
  • Primary Sclerosing Cholangitis (PSC) is associated with numerous genetic loci as well. PSC “genetically is more similar to UC than to CD.” Most other extraintestinal manifestation studies have been underpowered.
  • IBD share more genetic similarity to spondyloarthropathy (SpA) than any other immune-mediated diseases.  “The vast majority of shared susceptibility loci are concordant between IBD and SpA.”
  • With regard to psoriasis, the genetic relationship to IBD is complex.  Anti-TNF agents can cause psoriaform lesions in IBD patients.  In addition, anti-IL17a therapy, “so successful in psoriasis, appears to worsen Crohn’s disease” but not in those with a TNFSF15 variant.  Specific genotyping may help identify which patients with CD are susceptible to psoriaform lesions and those who may improve with therapy typically given for psoriasis.

My take: This article shows how understanding genetics of IBD is providing insight into pathophysiology and more personalized treatment approaches.

Briefly noted: EM Stoffel, CR Boland. Gastroenterol 2015; 149: 1191-1203. Excellent review of the genetics and genetic testing for Hereditary Colorectal Cancer.  The review includes polyposis syndromes and Lynch syndrome.

Atlanta Botanical Gardens

Atlanta Botanical Gardens

Be Aggressive! Treating Anemia Associated with Inflammatory Bowel Disease

A number of recent publications have made the point that anemia is a biomarker for severe inflammatory bowel disease and undertreatment affects quality of life. Reading one of the more recent studies (IE Koutroubakis et al. Clin Gastroenterol Hepatol 2015; 13: 1760-66) brought to mind the high school football cheer: Be Aggressive!

This particular retrospective study involved 410 patients (245 with Crohn’s disease, 165 with ulcerative colitis) from 2009-2013.  This study is from the same group that published data on a somewhat smaller cohort and showed that IBD treatment alone often will not resolve anemia (Koutroubakis, IE et al. Inflamm Bowel Dis 2015; 21: 1587-93–see previous blog links).

Key findings:

  • Prevalence of anemia: 37.2% in 2009 and 33.2% in 2013
  • Anemia was associated with increased hospitalizations (P<.01), clinic visits (P<.001), telephone calls (P<.004), surgeries for IBD (P=.001), and lower quality of life scores (P<.03)

The associated editorial (pgs 1767-69) suggests that IBD-related anemia, if mild (w/in 1 g/L below normal) to treat with oral iron replacement and if moderate-to-severe, then to replace intravenously (using Ganzoni’s formula calculator). In addition, if anemia is not improving, looking for alternative explanations (e.g. vitamin B12 or folate deficiency) is recommended.

Ganzoni Equation: Total Iron Deficit = Weight {kg} x (Target Hb – Actual Hb) {g/l} x 2.4 + Iron stores {mg}.   Iron stores: { 500 if W > 35kg } & { 15 mg/kg if W < 35kg }

My take: Anemia is a biomarker for severe disease.  While treating the underlying inflammatory bowel disease, don’t forget to make sure the patient’s anemia is addressed.

Related blog posts:

Disclaimer: These blog posts are for educational purposes only. Specific dosing of medications/diets (along with potential adverse effects) should be confirmed by prescribing physician/nutritionist.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

Central Park

Central Park

Desperate Measures in Refractory IBD

The often cited, ‘desperate times call for desperate measures,’ resonates in the setting of refractory inflammatory bowel disease (IBD).  [Of course, this saying could be used to justify about anything you want to do.]  For IBD, two recent studies point out potential remedies:

  • SA Merkley, et al. Inflamm Bowel Dis 2015; 21: 1854-59.
  • M Lazzerini, et al. Inflamm Bowel Dis 2015; 21: 1739-49, with editorial by A Bousvaros (1750-51)

In the first study, the authors retrospectively analyzed date from 24 IBD patients who were treated with intravenous immunoglobulin (IVIG) at a dose of 0.4 g/kg/day for 3 days, then 0.4 g/kg once a month. Key findings: 16 (67%) had a response and 3 (12.5%) obtained remission. Measures of improvement included CRP, ESR, Simple Endoscopic Score for Crohn’s disease, and the Harvery-Bradshaw Index. The researchers speculate that IVIG has anti-inflammatory and immunomodulator effects.  In addition, they note that IVIG can be given with concurrent infections.

In the second study, the authors studied thalidomide(1.5-2.5 mg/kg/day) in a double-blind, placebo-controlled randomized pediatric clinical trial in children with refractory active ulcerative colitis. Key findings: at week 8, clinical remission was achieved in 10/12 (83%) of thalidomide arm compared with 2/11 (19%) of control patients.  Then, among control patients who were switched, 8 of 11 (72%) reached remission as well. Peripheral neuropathy and amenorrhea were reported adverse effects. In the accompanying editorial, Dr. Bousvaros notes that there has been some data to suggest thalidomide efficacy in ulcerative colitis since 1979.  However, due to widespread bad publicity related to thalidomide-induced teratogenicity (eg. phocomelia) and side effects including neuropathy, it has not been used with much frequency. He notes that this study, as well, requires replication and speculates that “the primary focus on drug development will focus on newer small molecules and biologics, and this potentially useful medication may be left on the sidelines.” It is worth noting that the authors response (pg 1752) to this editorial was that the stigma of thalidomide is unwarranted and that teratogenicity can be avoided. “No case was observed out of 124,000 patients enrolled in the thalidomide distribution risk management program for more than 6 years.”

Bottomline: Both thalidomide and IVIG may be beneficial to desperate patients (and desperate doctors).  While small trials appear promising, larger trials are needed.  Don’t hold your breath waiting … will they ever happen?

Related blog posts:

1000th Tweet: GI Symptoms Preceding IBD Diagnosis

Another milestone for this blog: since 2012, the blog has been publicized on twitter; this is the 1000th tweet. It is also 1314th blog post over nearly 4 years.

A recent study (H Singh et al. Clin Gastroenterol Hepatol 2015; 13: 1302-09) indicates that children with inflammatory bowel disease (IBD) were more likely to have gastrointestinal symptoms in each of the 4 years before the diagnosis of IBD than children without IBD.

In this study, the researchers identified all children with IBD from a population-based Manitoba database; Manitoba had a population of 1.27 million in 2012.  651 children were matched with 5950 controls without IBD.  The study’s Table 1 & 2 indicates that children with IBD had increased clinic visits prior to diagnosis:

  • 54-66 months prior: standardized rate ratio for number of ambulatory visits 1.15; & for ≥1 visit due to GI symptoms odds ratio 1.44
  • 42-54 months prior: standardized rate ratio for number of ambulatory visits  1.22; & for ≥1 visit due to GI symptoms odds ratio 2.05
  • 30-42 months prior: standardized rate ratiofor number of ambulatory visits 1.19; & for ≥1 visit due to GI symptoms odds ratio 2.16
  • 18-30 months prior: standardized rate ratio for number of ambulatory visits 1.23; & for ≥1 visit due to GI symptoms odds ratio 2.93
  • 6-18 months prior: standardized rate ratio for number of ambulatory visits  1.15; & for ≥1 visit due to GI symptoms odds ratio 5.23

There was not a clear trend in increased symptoms between those who developed Crohn’s disease compared with Ulcerative Colitis. In addition, the study noted a trend towards decreased colectomy and resective surgery in Crohn’s in the time period 2002-2010 compared with 1987-2001.  One limitation of this study is the few number of pediatric gastroenterologists in Manitoba (only 1 before 2003); the lack of pediatric gastroenterology availability could impact timely diagnosis.

My take: This data shows that GI symptoms still predate diagnosis in many children and indicate a potential for diagnosis delay. The authors note that noninvasive tools like stool calprotectin have not been widely adopted (at least in Manitoba) and could be helpful in reducing diagnostic delays.

Estes Park, Colorado

Estes Park, Colorado

Higher Stool Infliximab Correlates with Poor Response in Severe Ulcerative Colitis

A recent study (full text link: “Loss of Infliximab into feces is associated with lack of response to therapy in patients with severe ulcerative colitis” Gastroenterol 2015; 149; 350-55.e2) provides information about patients with ulcerative colitis who do not respond well to infliximab therapy.

In this study, the authors obtained fecal samples from 30 consecutive patients with moderate to severe UC during the 1st 2 weeks of therapy.  In addition, they obtained serum infliximab levels as well as assessed clinical and endoscopic response at 2 weeks, 8 weeks, and 3 months after treatment began.

Key findings:

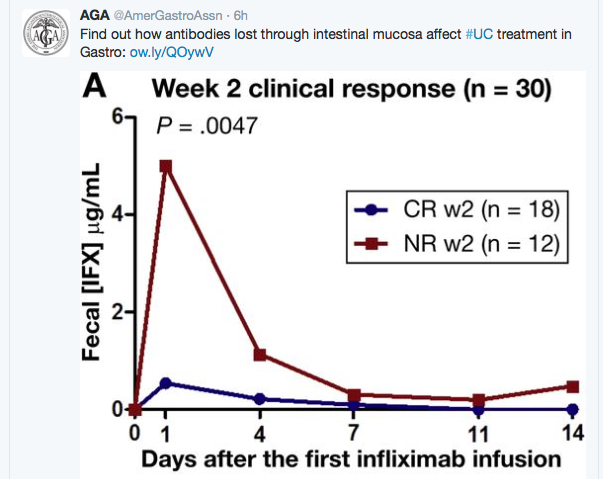
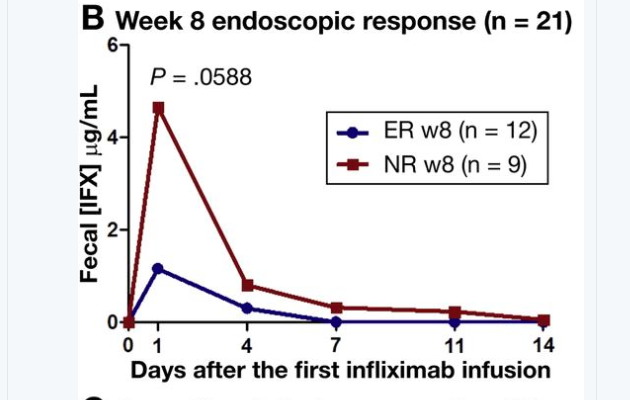
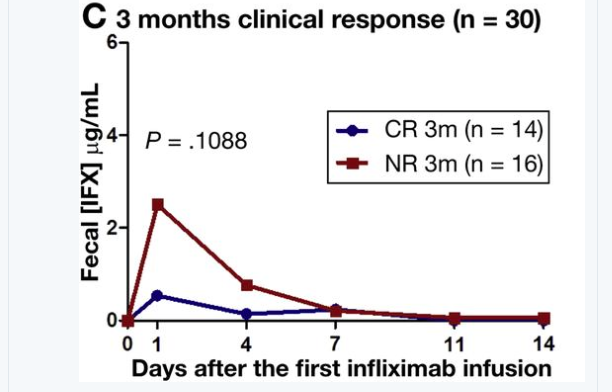
  • Fecal infliximab was detected in 129 of 195 (66%) samples.  The greatest loss was observed approximately 2 days after infusion. Low serum albumin was associated with greater infliximab levels in the stool.
  • Clinical nonresponders at week 2 had significantly higher fecal infliximab
  • The authors did not observe a correlation between fecal and serum infliximab concentrations.  However, it is possible that stool losses could indicate lower mucosal concentrations of infliximab.
From AGA twitter account

From AGA twitter account

From AGA twitter account

From AGA twitter account

From AGA twitter feed

From AGA twitter feed

Bottomline: It is not clear whether stool losses of infliximab directly contribute to drug failure or whether the loss is another biomarker of disease activity/high-risk patients.

The study authors note that “intestinal loss of IFX in moderate to severely active UC is associated with a diminished response to this treatment.  Patients with severe disease can, therefore, benefit from more intensive dosing regiments. This strategy warrants a prospective clinical trial.”

Related blog posts: