Unknown's avatar

About gutsandgrowth

I am a pediatric gastroenterologist at GI Care for Kids (previously called CCDHC) in Atlanta, Georgia. The goal of my blog is to share some of my reading in my field more broadly. In addition, I wanted to provide my voice to a wide range of topics that often have inaccurate or incomplete information. Before starting this blog in 2011, I would tear out articles from journals and/or keep notes in a palm pilot. This blog helps provide an updated source of information that is easy to access and search, along with links to useful multimedia sources. I was born and raised in Chattanooga. After graduating from the University of Virginia, I attended Baylor College of Medicine. I completed residency and fellowship training at the University of Cincinnati at the Children’s Hospital Medical Center. I received funding from the National Institutes of Health for molecular biology research of the gastrointestinal tract. During my fellowship, I had the opportunity to work with some of the most amazing pediatric gastroenterologists and mentors. Some of these individuals included Mitchell Cohen, William Balistreri, James Heubi, Jorge Bezerra, Colin Rudolph, John Bucuvalas, and Michael Farrell. I am grateful for their teaching and their friendship. During my training with their help, I received a nationwide award for the best research by a GI fellow. I have authored numerous publications/presentations including original research, case reports, review articles, and textbook chapters on various pediatric gastrointestinal problems. In addition, I have been recognized by Atlanta Magazine as a "Top Doctor" in my field multiple times. Currently, I am the vice chair of the section of nutrition for the Georgia Chapter of the American Academy of Pediatrics. In addition, I am an adjunct Associate Clinical Professor of Pediatrics at Emory University School of Medicine. Other society memberships have included the North American Society for Pediatric Gastroenterology Hepatology and Nutrition (NASPGHAN), American Academy of Pediatrics, the Food Allergy Network, the American Gastroenterology Association, the American Association for the Study of Liver Diseases, and the Crohn’s and Colitis Foundation. As part of a national pediatric GI organization called NASPGHAN (and its affiliated website GIKids), I have helped develop educational materials on a wide-range of gastrointestinal and liver diseases which are used across the country. Also, I have been an invited speaker for national campaigns to improve the evaluation and treatment of gastroesophageal reflux disease, celiac disease, eosinophilic esophagitis, hepatitis C, and inflammatory bowel disease (IBD). Some information on these topics has been posted at my work website, www.gicareforkids.com, which has links to multiple other useful resources. I am fortunate to work at GI Care For Kids. Our group has 17 terrific physicians with a wide range of subspecialization, including liver diseases, feeding disorders, eosinophilic diseases, inflammatory bowel disease, cystic fibrosis, DiGeorge/22q, celiac disease, and motility disorders. Many of our physicians are recognized nationally for their achievements. Our group of physicians have worked closely together for many years. None of the physicians in our group have ever left to join other groups. I have also worked with the same nurse (Bernadette) since I moved to Atlanta in 1997. For many families, more practical matters about our office include the following: – 14 office/satellite locations – physicians who speak Spanish – cutting edge research – on-site nutritionists – on-site psychology support for abdominal pain and feeding disorders – participation in ImproveCareNow to better the outcomes for children with inflammatory bowel disease – office endoscopy suite (lower costs and easier scheduling) – office infusion center (lower costs and easier for families) – easy access to nursing advice (each physician has at least one nurse) I am married and have two sons (both adults). I like to read, walk/hike, bike, swim, and play tennis with my free time. I do not have any financial relationships with pharmaceutical companies or other financial relationships to disclose. I have helped enroll patients in industry-sponsored research studies.

Is a Gluten-Free Diet a Healthy Diet for Those without Celiac Disease?

A helpful commentary (NR Reilly. J Pediatr 2016; 175: 206-10) on the gluten-free diet (GFD) tries to separate fact from fiction.  A few key points:

  1. There are some health problems that can occur with a GFD, particularly when the diet is started without the support of an experienced dietician. GFD foods frequently contain a greater density of fat and sugar and can contribute to obesity and metabolic syndrome.  A GFD may lead to nutrient deficiencies in B vitamins, folate, and iron.  GFD without sufficient dietary diversity may contain increase in toxin exposures (eg. arsenic, and mercury).
  2. Gluten is not toxic. “There are no data to support the theory of an intrinsically toxic property of gluten for otherwise-healthy and asymptomatic adults and children, and certain studies have specifically demonstrated a lack of toxic effects.“
  3. Most individuals with NonCeliac Gluten Sensitivity (NCGS) do not have NCGS!  First of all, many receive a GFD without proper testing to exclude celiac disease.  Secondly, most will tolerate gluten reintroduction.  In an Italian study, “only 6.6% of consecutive patients with presumed gluten sensitivity…actually had NCGS. 86% did not experience symptoms when gluten was reintroduced.”
  4. Timing of gluten introduction: “The most current understanding…in at-risk infants is that neither delaying gluten introduction from the recommended 6 months of age to 1 year, nor introducing at 4 months of age alters long-term CD risk estimates.”

My take: This is an excellent commentary.  While many people (without celiac disease) perceive benefit from a GFD, only a minority are likely  to derive better health or improved quality of life.  Those who stick with a GFD should seek the help of a well-qualified dietician.

Related blog posts:

Glacier Nat'l Park

Glacier Nat’l Park

How helpful are serologies in pediatric inflammatory bowel disease?

For quite some time, I have been unimpressed with the utility of serologies in distinguishing Crohn’s disease and Ulcerative Colitis.  While some of these tests claim some usefulness, when one excludes the obvious cases of Crohn’s disease (eg. perianal disease, fistulizing disease, small bowel disease), these claims seem quite dubious  Another study backs up my interpretation: L Birimberg-Schwartz et al. Inflamm Bowel Dis 2016; 22: 1908-14

This longitudinal report from the IBD Porto Group examined a multicenter retrospective cohort of 406 children with isolated colonic disease.  These children had a mean age of 10.5 years.  117 had Crohn’s colitis, 143 had ulcerative colitis, and 146 had IBD-unclassified (IBDU).

Key findings:

  • Among those with IBDU, the most prevalent serologic profile was pANCA neg/ASCA neg (41%).  34% had pANCA pos/ASCA neg, and 17% and pANCA neg/ASCA pos.
  • ANCA+: present in 43% of patients with IBDU, 64% of patients with UC, and 30% of patients with Crohn’s.
  • ASCA+ (IgA or IgG): present in 26% of  patients with IBDU, 6% of patients with UC, and 40% of patients with Crohn’s.
  • pANCA neg/ASCA pos did help differentiate Crohn’s colitis versus IBDU with 83% specificity, 96% positive predictive value; however the sensitivity was only 33% and the negative predictive value was only 13%.
  • pANCA neg/ASCA pos also differentiated Crohn’s colitis compared with ulcerative colitis with 97% specificity, and 90% positive predictive value however the sensitivity was only 33% and the negative predictive value was only 40%.
  • pANCA pos/ASCA neg did NOT differentiate well.  For IBDU versus UC, the specificity was 66%, the positive predictive value was 94%; the sensitivity was 65% and the negative predictive value was 38%.

In short, these tests generally have poor sensitivity.  If ASCA antibodies are present, which occurred in only 23%, the serology performs better but still usually not well-enough to help with big decisions. The presence of positive serology was associated with an increased likelihood of more severe disease.

Before you order IBD serology, you may want to consider whether you might use the money for this costly test in a better way.

My take (borrowed from authors): “Serology cannot routinely be recommended for differentiating between IBDU versus CC or UC as a sole diagnostic criterion given its low diagnostic utility.”

Related blog posts:

Trail to Iceberg Lake, Glacier Natl Park

Trail to Iceberg Lake, Glacier Natl Park

Medical Error -Overestimated as Cause of Death

A recent NY Times article provides some context to previous studies claiming that medical error could cause 100,000-250,000 deaths per year: Aaron Carroll Death by Medical Error

Here’s some excerpts:

When I started out as a doctor in 1999, the Institute of Medicine published a blockbuster report that declared that up to 98,000 people were dying in United States hospitals each year as a result of preventable medical errors. Just a few months ago, a study in the BMJ declared that number has now risen to more than 250,000, making preventable medical errors in hospitals the third-largest cause of death in the country in 2013…

There are about 2.5 million deaths each year in the United States, about 700,000 of which are hospitalized patients. This means that medical errors — in hospitals — would have to account for up to 10 percent of all deaths, or up to more than a third of hospitalized patients. That’s hard to fathom….

It’s somewhat sensationalistic to keep coming up with increasing numbers. I’m not sure it’s doing much good. After the publication of the initial report, defenders of the 98,000 number argued that even if the numbers were wrong, bringing attention to this problem would be good in itself.

Unfortunately, research doesn’t necessarily back that up. A 2010 study in The New England Journal of Medicine followed 10 North Carolina hospitals in the 10 years after the Institute of Medicine report. They found that the overall rate of harms, and the rate of preventable harms, did not significantly improve over that period.

My take: The article, in full, makes some compelling arguments that medical errors are overly-attributed as causes of death. At the same time, the article does not dismiss the importance of medical errors.  Many of the harms from medical errors do not result in death.

Screen Shot 2016-08-16 at 5.28.29 PM

Obeticholic Acid in Primary Biliary Cholangitis

While Primary Biliary Cholangitis (PBC) (previously called primary biliary cirrhosis) is seen mainly in adult hepatology practices, a new treatment may be emerging and this same medication is likely to be considered for several liver conditions.

Reference: F Nevens et al. NEJM 2016; 375: 631-43.

This 12 month, double-blind, placebo-controlled phase 3 “POISE” trial with 217 patients examined the use of obeticholic acid with or without ursodeoxycholic acid.  Surrogate markers of PBC were followed & the treatment groups improved compared to placebo.  However, adverse effects, particularly itching, were more common in the obeticholic acid groups; serious adverse effects were 11-16% in the treatment groups compared with 4% in the placebo group.

Results below:

PBC Rx

My take: It will be nice when important clinical endpoints can be assessed for this therapy like progression to cirrhosis.  For now, the cost of this treatment is ~$70,000 yearly.

Related blog post:

Breakthrough for Fatty Liver Disease? | gutsandgrowth

More advice on Proton Pump Inhibitors

L Laine, A Nagar. Am J Gastroenterol 2016; 111: 913-15.

This reference explains how these clinicians discuss the long-term use of proton-pump inhibitors with their adult patients.  Thanks to Ben Gold for this reference.  Here are a couple pointers:

  • “The recent studies about CKD (chronic kidney disease) and dementia, similar to many prior studies assessing PPI risk, are retrospective observational studies…This results in differences between PPI users and non-users in factors that may impact study outcomes and confound results.”
  • Gastroesophageal reflux disease: The authors suggest that PPIs for GERD can be stopped >2 weeks after symptoms resolve.  For infrequent symptoms, H2RAs, lifestyle modifications and intermittent PPIs often suffice.
  • Barrett’s esophagus: “observational sutdies suggest that PPIs may decrease progression to neoplastic Barrett’s esophagus”

WHAT WE TELL PATIENTS: “Because of inherent risk of bias and low effect sizes we cannot conclude that associations of PPIs and adverse outcomes such as dementia and CKD in recent observational studies are vailid…Nevertheless, we cannot conclude that risks do not exist…we need to ensure that benefits outweigh potential risk.  If PPIs are indicated, using the lowest effective dose and, if possible, intermittent rather than daily therapy..should decrease the risk of potential side effects.”

On the same topic, Paul Moayyedi (in Gastroenterology and Endoscopy News, August 2016): “Every study has shown that sicker patients tend to be prescribed PPIs…Sick patients tend to develop other illnesses so PPIs will be associated with about any disease you can imagine in a database.”  As such, he asserts that weak associations (OR <2) are usually due to cofounding factors.  “The only benefit [these studies]..have is that it is another opportunity to discuss with the patients about stopping their PPI therapy, as there are a significant proportion…on these drugs unnecessarily.”

purple flowers

Optimistic Results for Hepatitis C plus Hepatology Update

The August issue of Hepatology had several articles on Hepatitis C confirming the efficacy of newer agents:

  • LI Backus et al Hepatology 2016; 64: 405-14.  This “real-world” observational study from the VA Clinical registry with 4,365 genotype 1 treatment-naive patients who received ledipasvir/sofosbuvir showed SVR rates of 91.3% (w/o ribavirin) and 92% (w ribavirin).
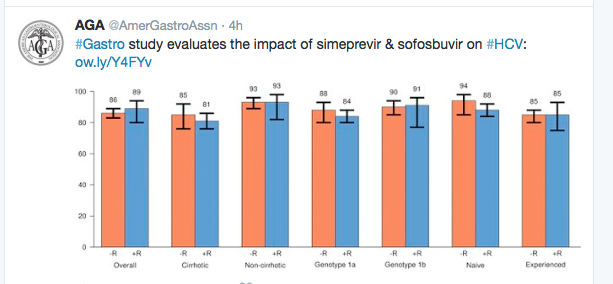
  • P Kwo et al. Hepatology 2016; 64: 370-80 (OPTIMIST-1) This study showed that 12 weeks of simeprevir+sofusbuvir for 12 weeks was highly effective (97% SVR) and that 8 weeks of this therapy was inferior (83% SVR).  N=310 with genotype 1 (w/o cirrhosis).  No patients stopped therapy due to adverse effects.
  • E Lawitz et al. Hepatology 2016; 64: 360-69 (OPTIMIST-2) This study showed that simeprevir+sofusbuvir for 12 weeks was effective in genotype 1 patients (n=103) with cirrhosis.  For treatment-naive, the SVR was 88% and for treatment-experienced patients, the SVR was 79%.

Also in Hepatology:

  • S Heibani et al Hepatology 2016; 64: 549-55. This study looked at 1-week versus 2-week intervals for endoscopic ligation.  While 1-week ligation eradicated varices more quickly, neither approach was associated with differences in number of endoscopies, complications (including rebleeding) or other clinical outcomes.
From earlier study of "real-world" treatment of Genotype 1. Gastroenterol 2016; 150: 419-29.

From earlier study of “real-world” treatment of Genotype 1. Gastroenterol 2016; 150: 419-29. (Full text link)


NPR: Children Missing Out on Hepatitis C Treatment

From NPR: Children Missing Out on Hepatitis C Treatment

An excerpt:

A study by the Philadelphia Department of Health points to what Wen and others in the medical profession see as a worrisome trend: Children with hepatitis C may be unaware of their diagnosis and the potential need for treatments down the road in order to prevent long-term liver damage.

Using city surveillance data, the study found that as many as 8 in 10 children at high risk for hepatitis C exposure in Philadelphia were never screened for the condition. More specifically, of the approximately 500 moms-to-be who were registered as having hepatitis C between 2011 and 2013, only 84 of their newborns, or about 16 percent, were tested for the virus by 20 months of age.

My take: As the article discusses, with the advent of better treatments, which will be available for children (?next 1-2 years), identifying Hepatitis C acquired prenatally is becoming important.

Related blog posts:

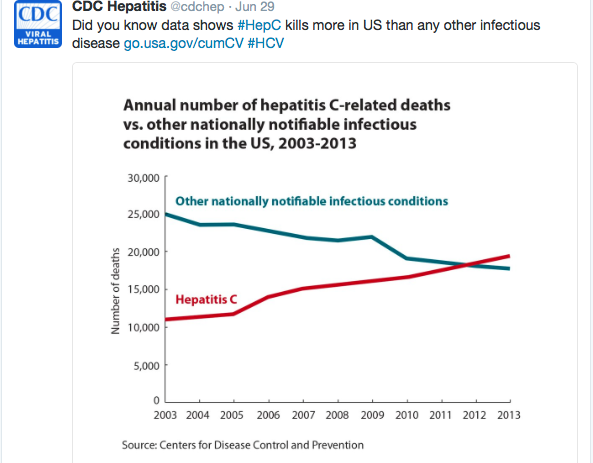
Rising HCV mortality

How Watching TV Food Commercials Affects Children’s Brains

A recent study of 23 children (8-14 yrs) correlated functional MRI results with watching commercials.

Full text: The Influence of Televised Food Commercials on Children’s Food Choices

Key finding: The ventromedial prefrontal cortex, a reward valuation brain region, showed increased activity during food choices after watching food commercials compared with after watching nonfood commercials.

Author’s conclusion: Overall, our results suggest watching food commercials before making food choices may bias children’s decisions based solely on taste, and that food marketing may systematically alter the psychological and neurobiologic mechanisms of children’s food decisions.

My take: When is the last time you saw a commercial for broccoli?  While food companies may not fully understand how their marketing affects kids’ brains, I’m certain they understand how it affects their bottom line.

Lake McDonald, Glacier Natl Park

Lake McDonald, Glacier Natl Park