Functional Dyspepsia in Clinical Practice

PJ Pascricha, NJ Talley. NEJM 2026; 394: 166-176. Functional Dyspepsia

This is a terrific, succinct review of functional dyspepsia.

Key points:

  • “The syndrome probably comprises several different and as yet incompletely characterized disorders; local microinflammation driven by an aberrant response by type 2 helper T cells may represent an important subset of cases.”
  • “Functional dyspepsia can overlap with other gastrointestinal syndromes, particularly irritable bowel syndrome and gastroesophageal reflux disorder, and persons with such overlap have more severe symptoms.”
  • “There is no approved drug therapy; treatment is empirical and directed at symptoms, consisting of acid suppressants and low-dose tricyclic antidepressants (and other neuromodulators), along with appropriate nutritional and psychological support.”

Discussion points:

  • Epidemiology: “Worldwide, functional dyspepsia is present in 7.2% of adults (10.1% in the United States), affects women 1.6 times as often as men, and is more common in persons younger than 40 years of age.”
  • Diagnostic workup: Workup depends on clinical judgement. Careful evaluation is needed in the presence of alarm symptoms like GI bleeding, anemia, weight loss, dysphagia, personal/family history of gastrointestinal cancers.

Treatments:

  • “Acid-inhibition pharmacotherapy is considered to be first-line treatment in functional dyspepsia. However, the benefits of this approach are modest at best”
  • Neuromodulators: “Tricyclic antidepressants are considered first-line therapy in this category…Results of the Functional Dyspepsia Treatment Trial showed significant superiority of low-dose amitriptyline over placebo in achieving prespecified “adequate relief” for the last 5 weeks of the 10-week trial (53% with amitriptyline vs. 40% with placebo, P=0.05). The effect appeared to be greatest in participants with epigastric pain (relative risk, 1.34; 95% CI, 1.02 to 1.59). In contrast, the response obtained with escitalopram (a selective serotonin-reuptake inhibitor) did not differ from that obtained with placebo.39 The benefit of amitriptyline was independent of changes in depression or anxiety scores…Mirtazapine (an atypical tetracyclic antidepressant that also antagonizes histamine H1 receptors and serotonin 5-hydroxytryptamine [5-HT] type 3 receptors) also has shown efficacy in functional dyspepsia and may be best suited for patients with prominent nausea and clinically significant weight loss.41“
  • Psychology: “Recognition and treatment of uncontrolled anxiety and depression are important in all cases. In refractory functional dyspepsia, it is also important to consider psychological therapies as an adjunct for helping patients cope with their symptoms and perhaps attenuate the severity of symptoms. Studies support the use of cognitive behavioral therapy, mindfulness-based stress reduction, and hypnotherapy in functional dyspepsia, and benefits may last up to 12 months.42…the evidence from these trials is considered to be very low.”
  • Diet: “Dietary advice has not been shown to be effective in studies.”The effectiveness of simple dietary advice (i.e., small low-fat meals and avoidance of carbonated drinks to limit gastric distention), although seemingly rational, has not been borne out in a randomized trial.33 Low-FODMAP (fructans, fermentable oligosaccharides, disaccharides, monosaccharides, and polyols) diets have not been shown to reduce symptoms any more than traditional dietary advice.34…” IgE-mediated (classical) food allergy is generally not mistaken for functional dyspepsia, and screening for IgG-mediated reactivity to food antigens is not recommended.25“
  • Immune-Modulating Treatment: “A randomized, controlled trial of montelukast, a cysteinyl leukotriene antagonist, in children with duodenal eosinophilia and dyspeptic symptoms showed a significant effect in reducing pain as compared with placebo (62% vs. 32%, P<0.02), and the effect appeared to be even greater (84%) in patients with more than 20 eosinophils per high-powered field.43“

My take (borrowed from the authors) “Given the limited efficacy of drugs that are recommended under national and international guidelines…, the consideration of therapies for which evidence is insufficient may be reasonable in refractory cases.”

Related blog posts:

Tango Dancing in Buenos Aires

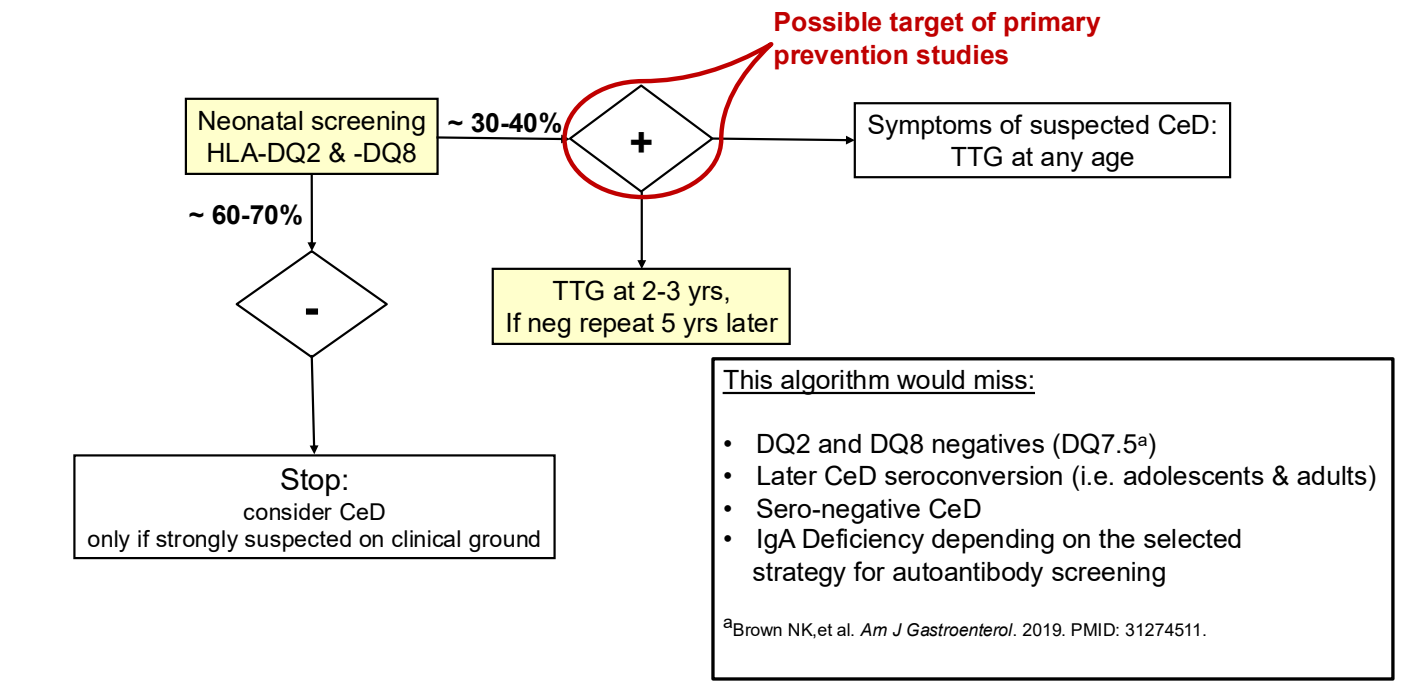
Should We Adopt Mass Screening for Celiac Disease?

MG Stahl et al. Gastroenterol 2026; 170: 240-245. Open Access! Mass Screening of Celiac Disease: A Crossing Point Between Secondary and Primary Prevention?

The authors make several good arguments for mass screening for celiac disease.

Key Points:

  • “The worldwide prevalence is high, affecting an estimated 1% to 3% of the general population…One study showed that two-thirds of children remain undiagnosed.” (Dig Liver Dis. 2023; 55:608-613). Thus, screening would identify many cases that would otherwise go undiagnosed and untreated
  • ” As one of the most HLA-restricted diseases, nearly all patients carry HLA-DQ2.5, DQ2.2, or DQ8 (and very rarely DQ7.5), and their absence makes CeD extremely unlikely. Although 30% to 40% of the general population carry these alleles, only approximately 3% will go on to develop CeD”
  • “The Environmental Determinants of Diabetes in the Young (TEDDY) study showed that although there was some early anxiety reported, there was no long-term psychological harm in disclosing genetic risk to parents of children that were tested and most parents adapted over time”
  • “Children identified as highest risk at birth through HLA-DQ typing also represent an ideal cohort to test interventions such as dietary modifications or microbiome targeted therapies during the predisease phase, during the key “window of opportunity,” ideally before seroconversion (primary prevention).” There are no currently proven primary prevention interventions.
  • Some of the drawbacks to screening: 1. “Evidence on health benefits of treating asymptomatic CeD is limited.” 2. “The potential psychosocial effects of both newborn genetic testing and a strict gluten-free diet in individuals diagnosed through screening need to be considered.” 3. “HLA-DQ typing may be cost prohibitive in some regions of the world.” 4. “Most children identified to be at risk for CeD based on HLA-DQ will not develop CeD.”

My take: I am skeptical about the benefits of screening at birth and how it would work in our current health care system. We have plenty of examples in our field in which early screening is not followed up well (eg. Hepatitis C, Biliary Atresia). If more evidence emerges on the benefits of primary prevention, then more widespread screening at birth may be worthwhile. For example, there is “a clinical trial underway in Sweden, the GRAin study (NCT04593888) that aims to investigate whether eating a gluten reduced diet (<2 g of gluten per day) may reduce the risk of CeD in children with genetic risk.”

Related blog posts:

Updated Data on PPI Effectiveness For Eosinophilic Esophagitis

AJ Lucendo et al. Clin Gastroenterol Hepatol 2025; 23: 2115-2127. Proton Pump Inhibitors for Inducing and Maintaining Remission in Eosinophilic Esophagitis: An Updated Systematic Review and Meta-Analysis

Background/Methods: This systematic review aimed to update the response/remission rates of PPI therapy for eosinophilic esophagitis. Compared to review in 2016, the current review covers a 10-fold increase in population (from 619 to 7304 patients), with a more balanced distribution between children (41%) and adults, and with a geographical representation from several continents.

Key findings:

  • PPI therapy led to clinical response in 65% (95% confidence interval [CI], 57.2–72.4)) and histological remission (<15 eos/hpf) in 45.4% (95% CI, 41.6%–49.3%) of patients, without differences between children and adults (41.4% vs 48%; P = .17)
  • Overall, 34.1% (95% CI, 27.9%–40.5%) achieved <5 eosinophils per high-power field
  • Maintenance half-doses led to sustained histological remission in 68.2% (95% CI, 63.7%–72.6%) of patients
  • Clinical and histological remission (<15 eos/hpf) was achieved in 45% of patients
  • Histological remission was significantly higher with double PPI doses compared with standard (51.7% vs 28.3%; P < .005)

In the discussion, it was noted that Japanese cohorts had a better response to PPI therapy with a histological remission (67.9%). This could be related to more favorable metabolism of PPI. “CYP2C19∗17 haplotype (related to ultrarapid and rapid PPI metabolizers), is the least prevalent (<3%) in patients with Asian ancestry.”

My take: This study reinforces previous data showing a 40-50% remission rate with PPI therapy for EoE. Twice a day PPI therapy is significantly more effective than once a day.

Related blog posts:

Increased Mortality with Achalasia

A Forss et al. Clin Gastroenterol Hepatol 2025: 23: 2468-2476. Open Access! All-cause and Cause-specific Mortality in Achalasia: A Nationwide Matched Cohort Study

Methods: This study was a nationwide, population-based, matched cohort study using the Epidemiology Strengthened by Histopathology Reports in Sweden (ESPRESSO) cohort which included all adults in Sweden with incident achalasia (n = 704; 1969–2017; follow-up until December 31, 2021) without any other prior esophageal conditions. Individuals with achalasia were matched by age, sex, birth year, and county to up to 5 reference individuals (n = 3348) from the general population. The median follow-up was 9.1 years. Medians age in the study was 60 years.
Key findings:

  • There were 270 deaths in individuals with achalasia, and 1023 in reference individuals (IR, 69.4 vs 51.9/1000 person-years)
  • Thus, there was a 42% increase in the risk of death. This translated into 1 extra death per every 6 individuals with achalasia followed for 10 years
  • Risk increases were seen for death from any cancer (aHR, 1.65), esophageal cancer (aHR, 23.19), and respiratory disease (aHR, 2.22)

Discussion point: “The sibling comparison (aHR for all-cause mortality, 1.78; 95% CI, 1.13–2.81) confirmed our findings in the main analysis (aHR, 1.42; 95% CI, 1.21–1.65). The similar risk estimates suggest that shared early-life exposures do not play any major role for mortality in achalasia. In all, we are confident that the observed elevated mortality is unlikely to be fully explained by environmental exposures or comorbidities, because the risk estimates remained largely unchanged in the sibling comparison as well as after adjustment for a wide range of comorbidities (through CCI).”

My take: This study is in agreement with others which have sown that achalasia is associated with an increased mortality risk.

Related blog posts:

Lower Expectations for Outcomes After Botox for Retrograde Cricopharyngeus Dysfunction (aka Abelchia)

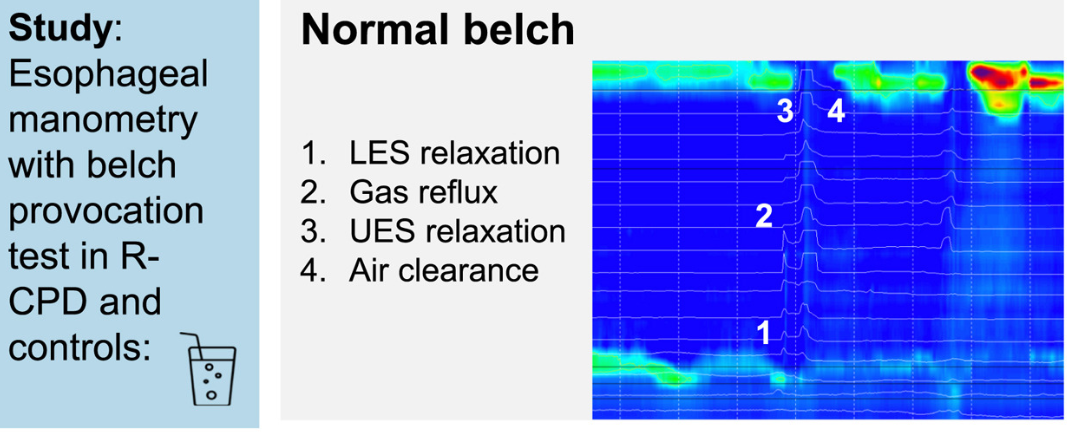
K Raymenants et al. Clin Gastroenterol Hepatol 2026; 24: 81-91. Diagnosis of Retrograde Cricopharyngeus Dysfunction Using High Resolution Impedance Manometry and Comparison With Control Subjects

Methods: Retrospective analysis of High Resolution Impedance Manometry
(HRiM) with belch provocation was performed between May 2021 and April 2024 in 55 patients with R-CPD, 30 control patients, and 15 healthy volunteers. Age of patients with R-CPD was 22-35 years.

Key findings:

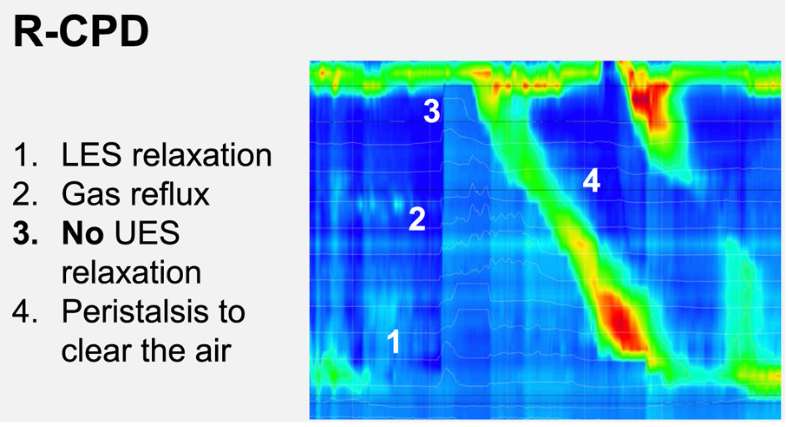
  • During belching, we saw higher UES pressures in R-CPD patients vs controls, leading to incomplete air clearance and air oscillating in the esophagus (P < .0001)
  •  After BT injection, median UES pressures during belching decreased (56 vs 3 mmHg), and air clearance improved (P < .0001)
  • A maximum UES pressure during belching >31 mmHg adequately discriminated patients from controls
  • Interestingly, the authors did not include one of the major findings in their abstract: “Symptom improvement of at least 50% was present in 57% of patients, which is lower than reported up to now”
  • R-CPD patients had inability to belch in 100%, gurgling chest noises in 100%, bloating in 92%, chest pain in 67%, nausea in 59%, and heartburn (at least weekly) in 65%

My take: Recognition of this treatable disorder is important. However, the lower improvement rate in this study is useful for counseling patients. My suspicion is that this finding likely reflects more widespread results as initial studies could have more selection or reporting bias.

Related blog posts:

Proactive Drug Monitoring for Crohn’s Disease in Pediatrics

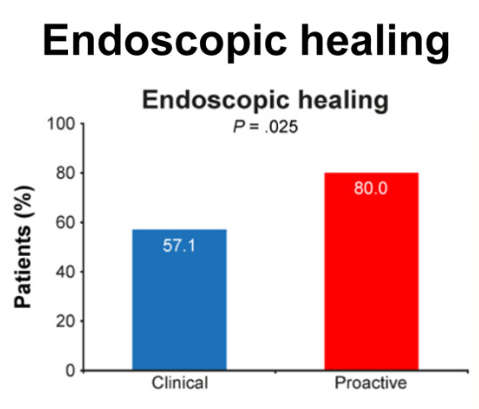
B Kang et al. Clinical Gastroenterology and Hepatology; 2026: 24: 201 – 209. Proactive Drug Monitoring Versus Clinically Based Dosing for Endoscopic Healing in Pediatric Crohn’s Disease Receiving Infliximab

Methods: This was a non-blinded, randomized controlled trial of 112 biologic-naïve children with CD who had responded to IFX induction treatment at 4 centers in South Korea between July 2017 and November 2020. Patients were randomly assigned to receive dosing based on proactive TDM (proactive arm) or clinically based dosing (clinical arm). The primary endpoint was endoscopic healing (EH) at week 54.

During the maintenance phase, patients received IFX 5 mg/kg every 8 weeks. In the proactive arm, treatment was intensified (shortening interval by 2- to 4-weeks) if trough level was less than 6 mcg/mL.

Key findings:

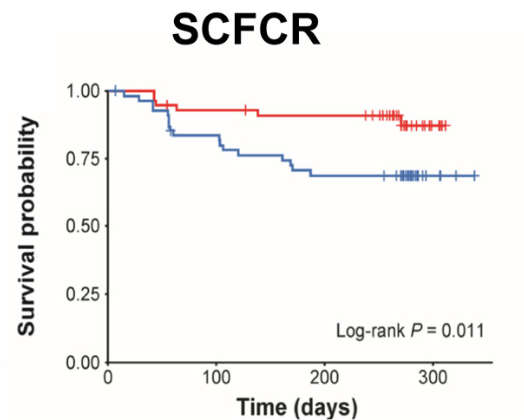
Sustained corticosteroid-free clinical remission (SCFCR) 

Discussion Points:

  • “Our findings provide evidence that the proactive strategy resulted in increased EH rates and had a positive impact on SCFCR, biochemical remission, and FC, which serve as surrogate markers of EH.”
  • “The PAILOT trial, the only prospective study on proactive TDM in pediatric patients with CD, demonstrated that proactive TDM with adalimumab resulted in higher SCFCR rates than reactive TDM (82% vs 46%; P < .001), consistent with our findings.8“
  • “In our study, IMM [immunomodulator] modulation was performed in conjunction with proactive TDM, which may explain why no difference was observed in ADA development (proactive arm, 31.4% vs clinical arm, 28.6%. Proactive TDM has been confirmed to reduce the development of ADAs, and the concept of “optimized monotherapy” based on the view that proactive TDM effectively guides IMM withdrawal in combination therapy has been well-described.30 …in our institution, IMMs are discontinued as soon as possible after 1 year of combination therapy if adequate TDM is maintained.31“

My take: This study shows that proactive TDM is superior to clinical-based dosing. The findings may have been less pronounced if higher baseline doses of IFX were used. It is well-recognized that “standard” IFX (5 mg/kg/dose every 8 weeks) is usually insufficient in pediatric patients.

Related blog posts:

Outcomes in Children with Celiac Disease Presenting with Constipation

A Almallouhi et al. J Pediatr Gastroenterol Nutr. 2025 DOI: 10.1002/jpn3.70316. Clinical outcome of constipation as the presenting symptom in children with celiac disease

Background: “It is not clear if CeD prevalence is higher in children with refractory and chronic constipation or not.11–15 The current guidelines from the American Gastroenterological Association (AGA) and the North American Society for Pediatric Gastroenterology, Hepatology, and Nutrition (NASPGHAN) do not consider constipation an indication for CeD testing in the absence of suggestive family history, growth, or developmental delay.”

Methods: This was a retrospective study (1994-2024) of children (<18 years) who presented with constipation and then diagnosed with celiac disease (CeD). There were 248 children with CeD, 177 (71%) had biopsy-confirmed CeD, and 56 (23%) were diagnosed with serology-only criteria

Key findings:

My take:

  1. It is unclear if having constipation increases the risk of celiac disease
  2. Many children with celiac disease also have functional disorders like irritable bowel and constipation that often continue despite a gluten-free diet

Related blog posts:


Also, Dr. Balistreri gives a Bowel Sounds Podcast on Hep B. Here’s the link: https://t.co/BmEUoC9YQt

Related blog posts:

GutsandGrowth: 2025 Year in Review (Part 3)

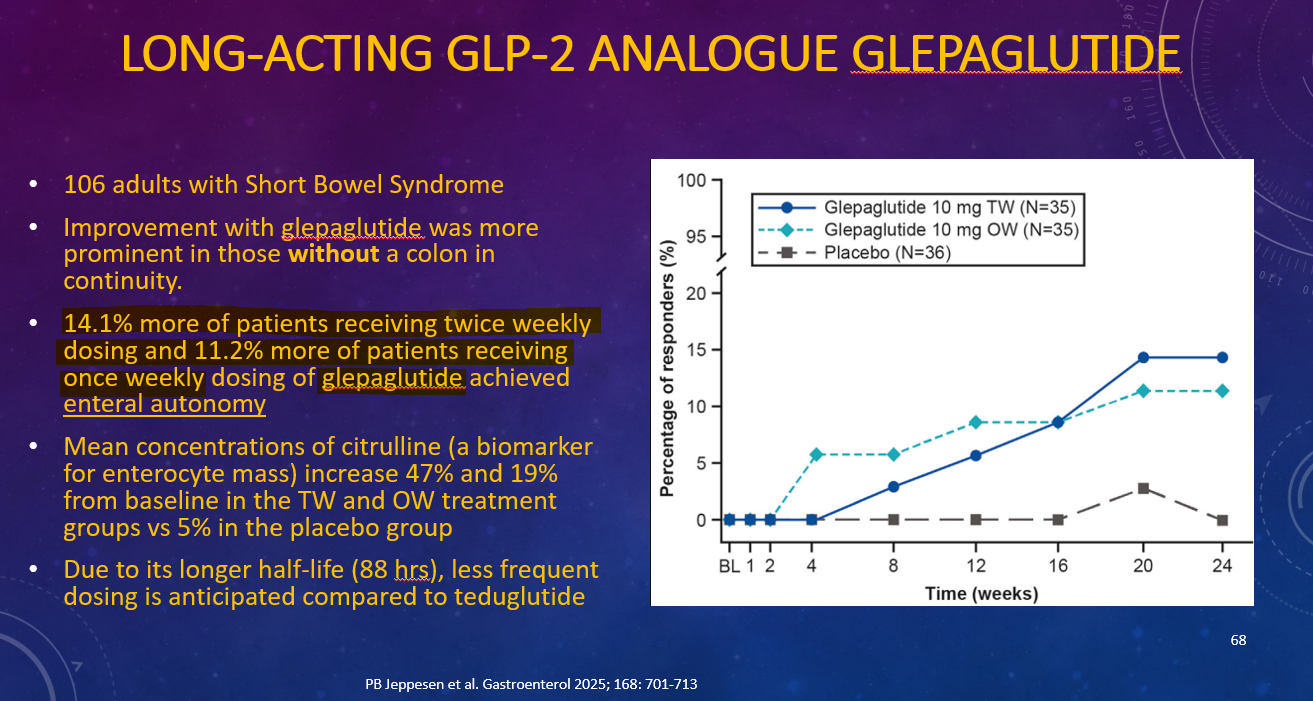
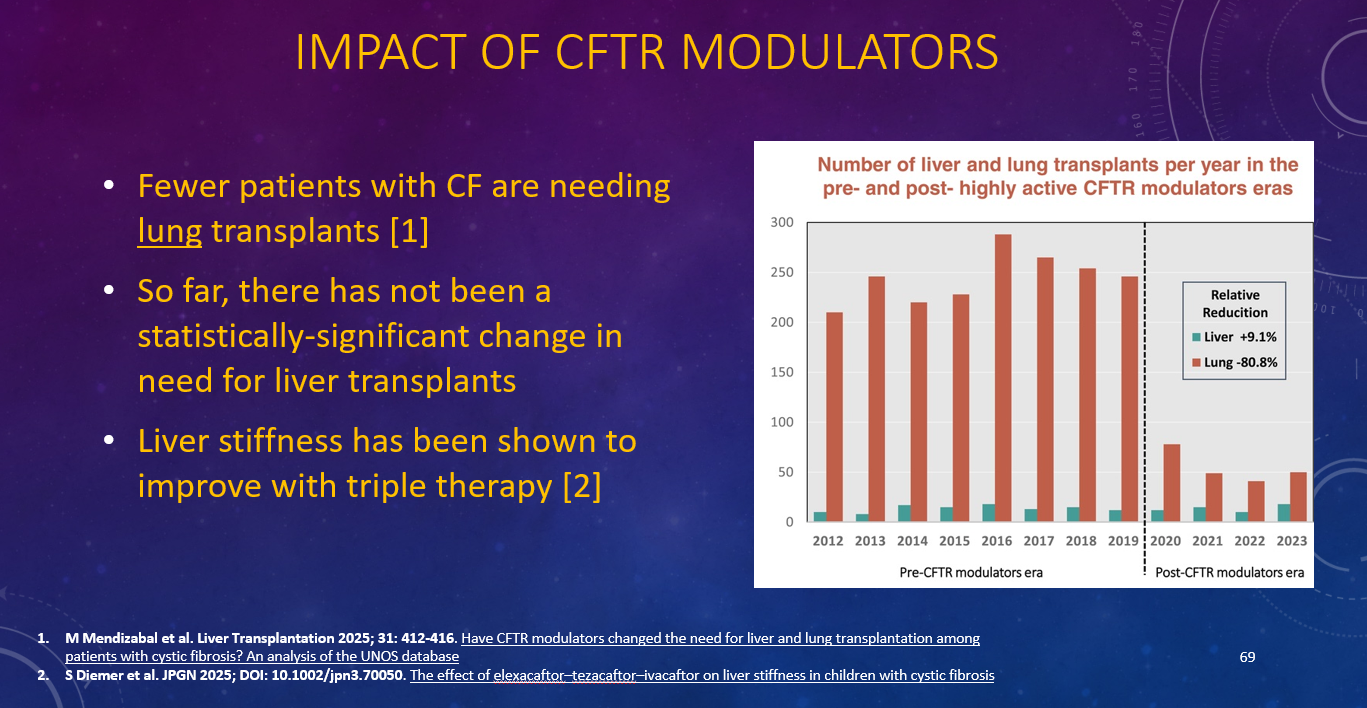
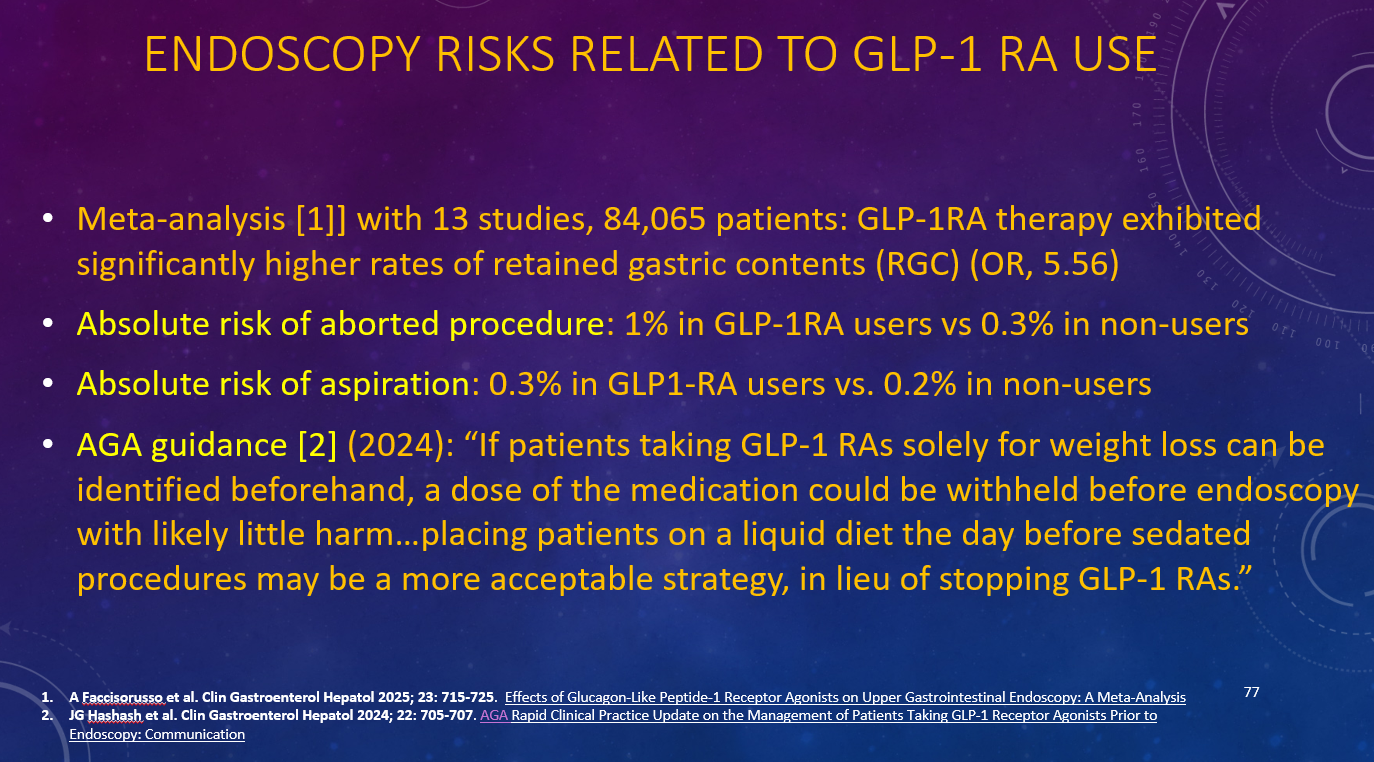
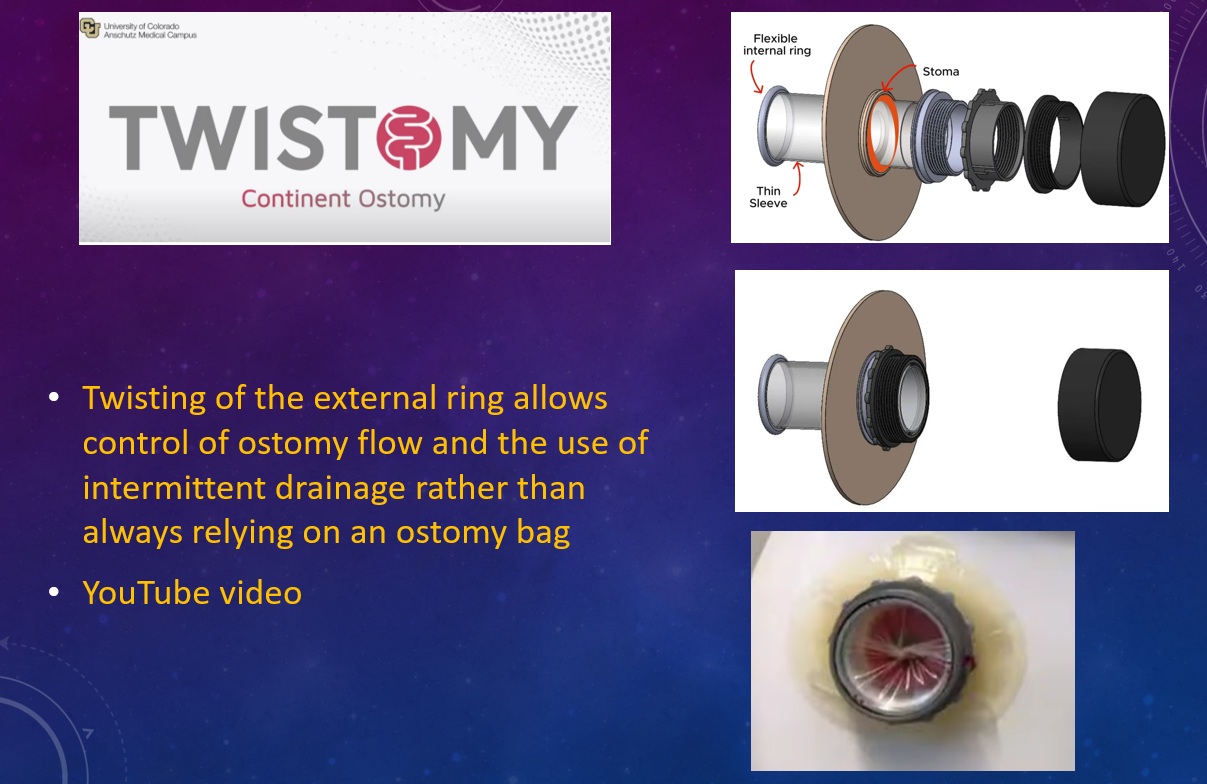
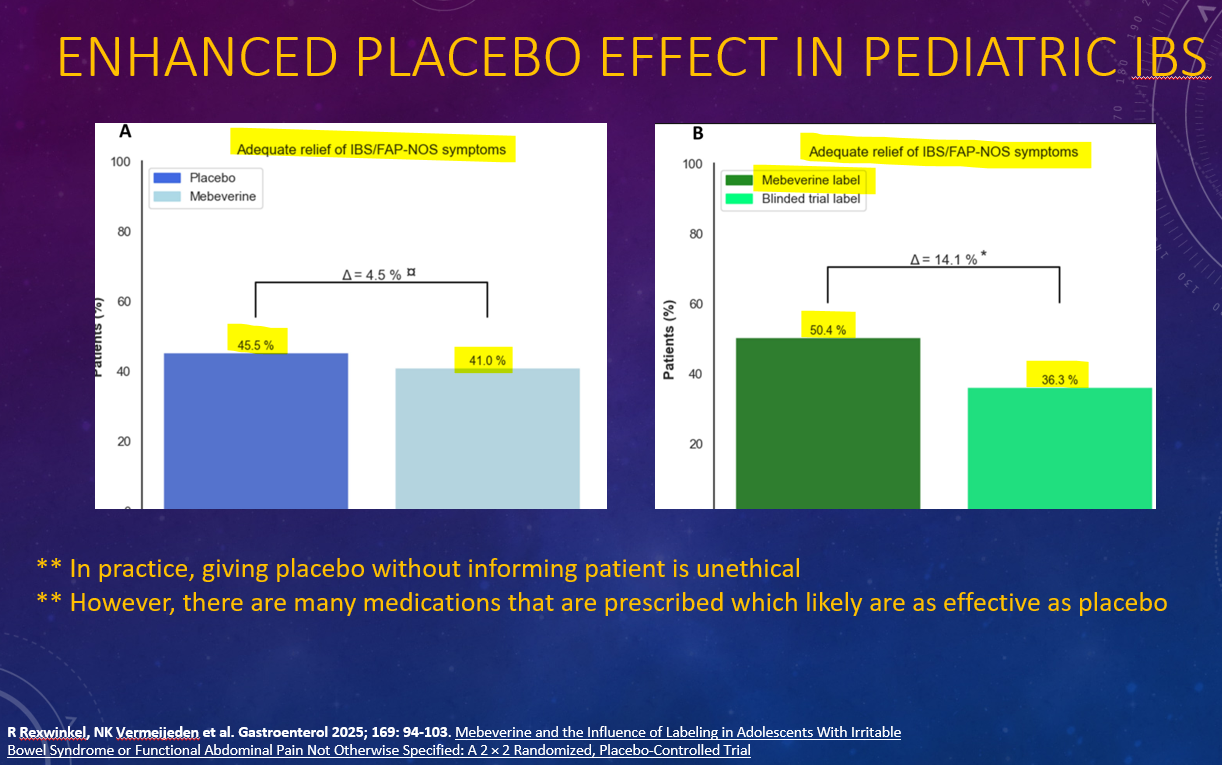
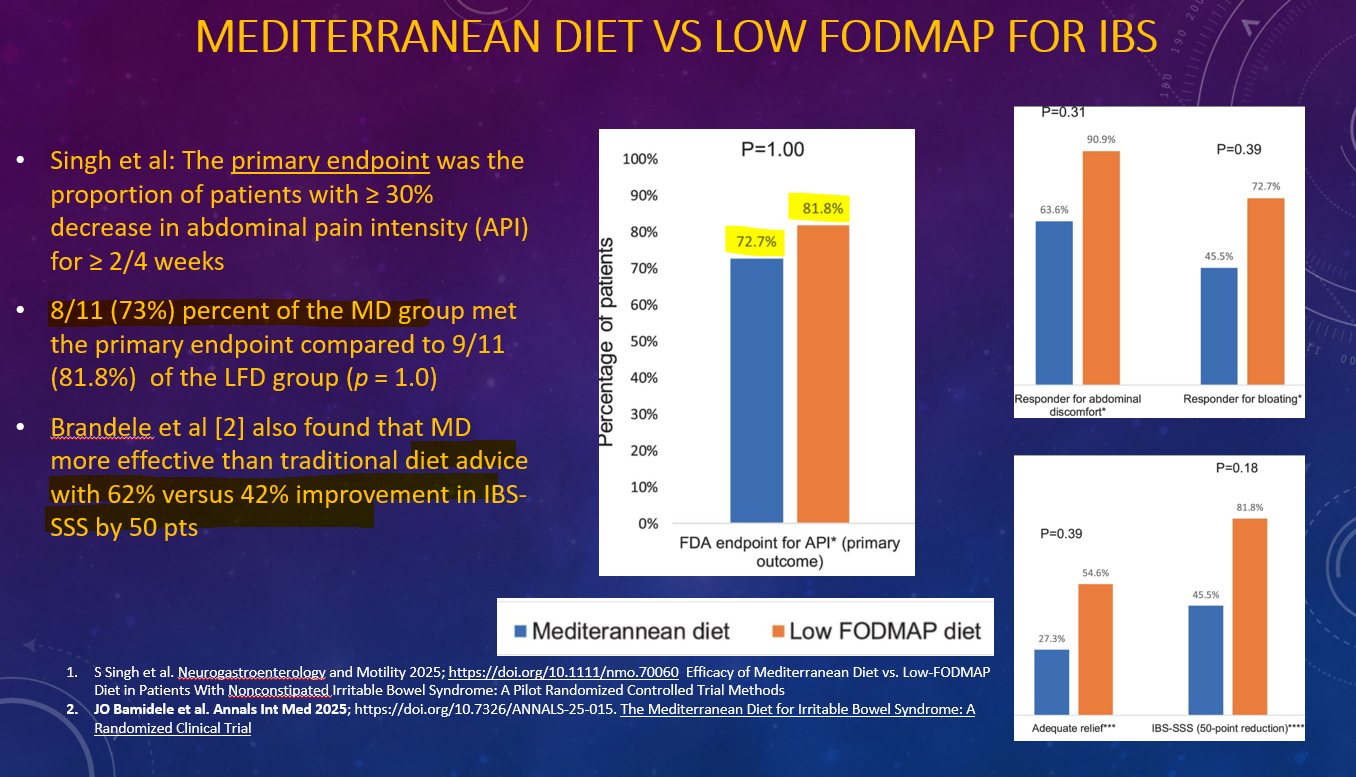
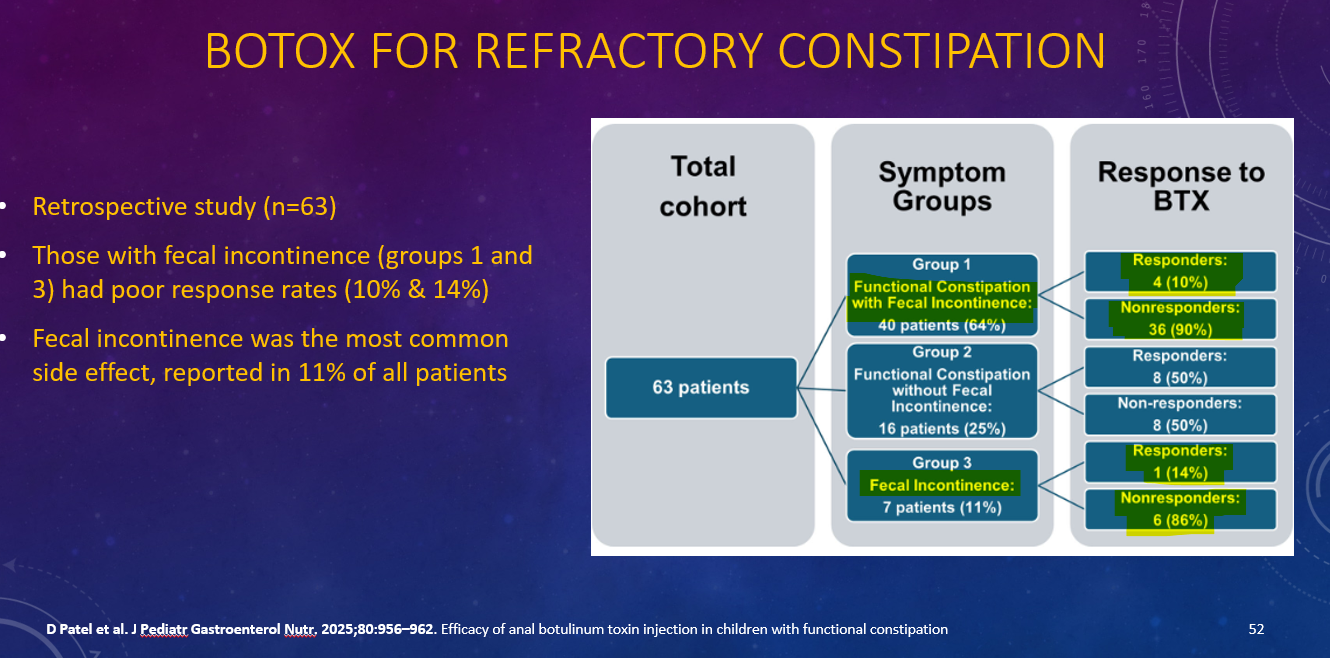
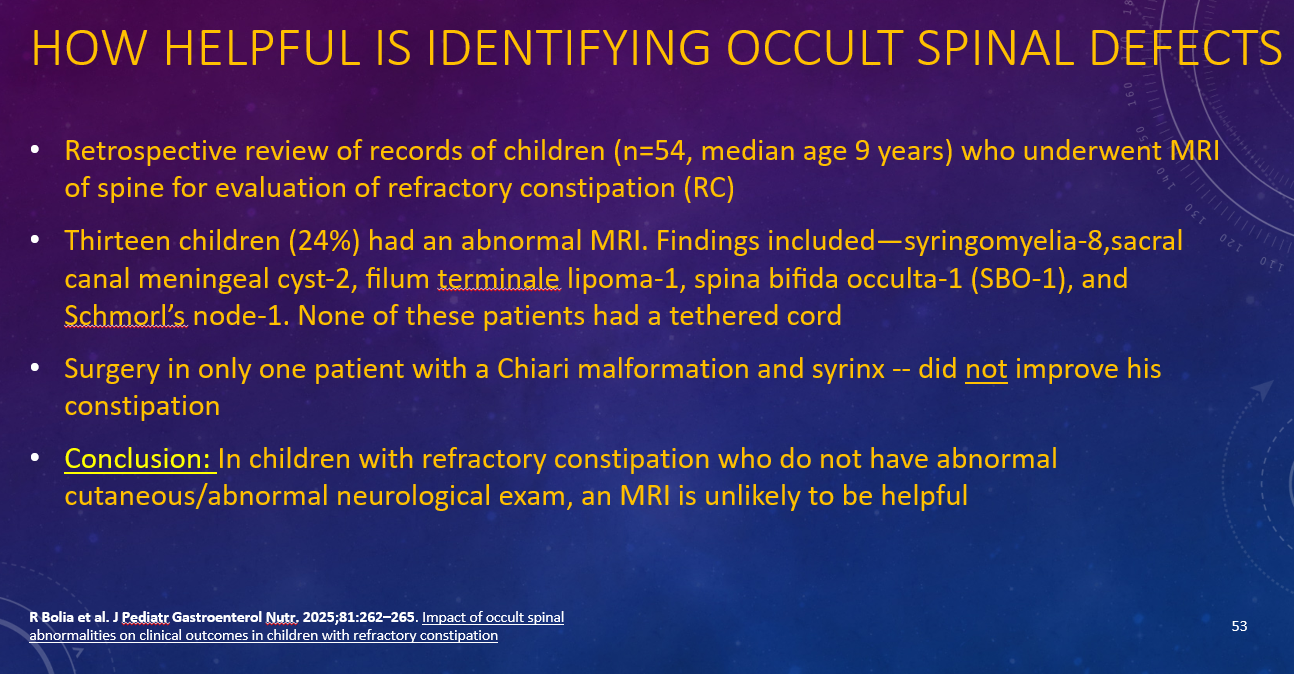
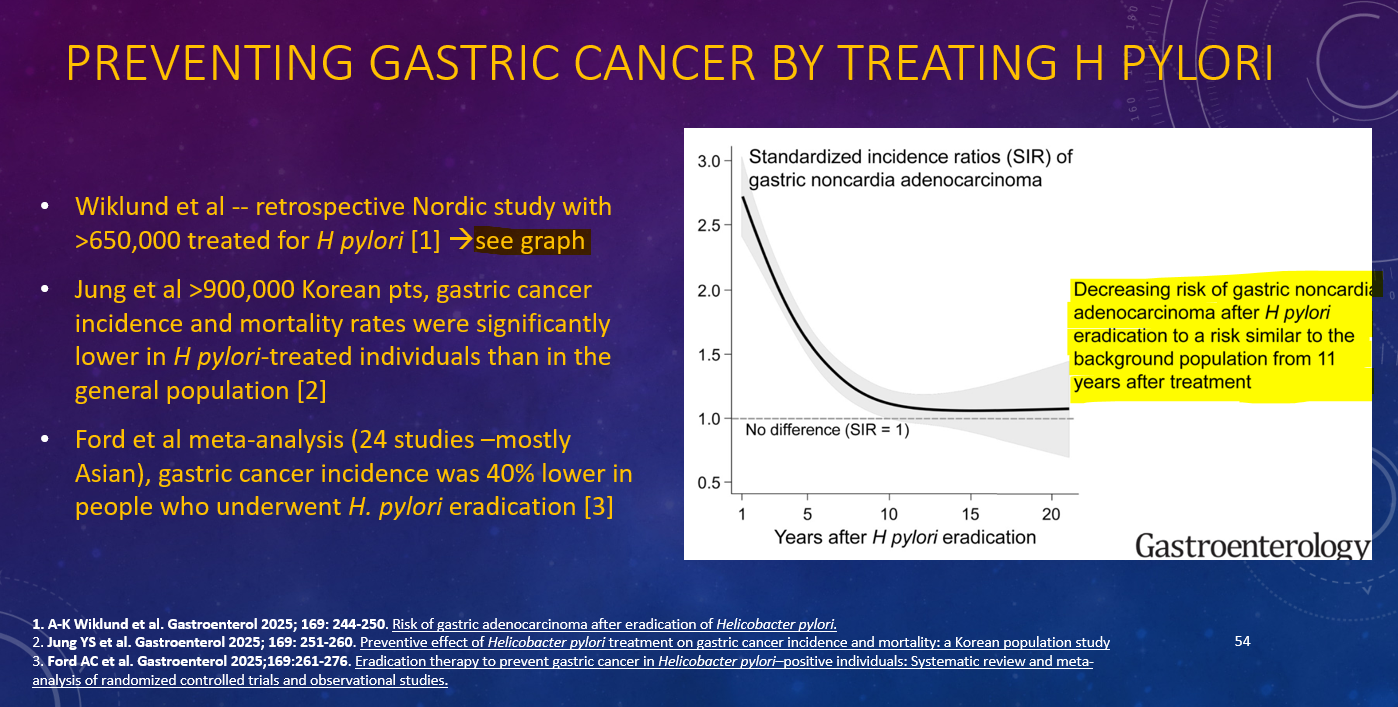
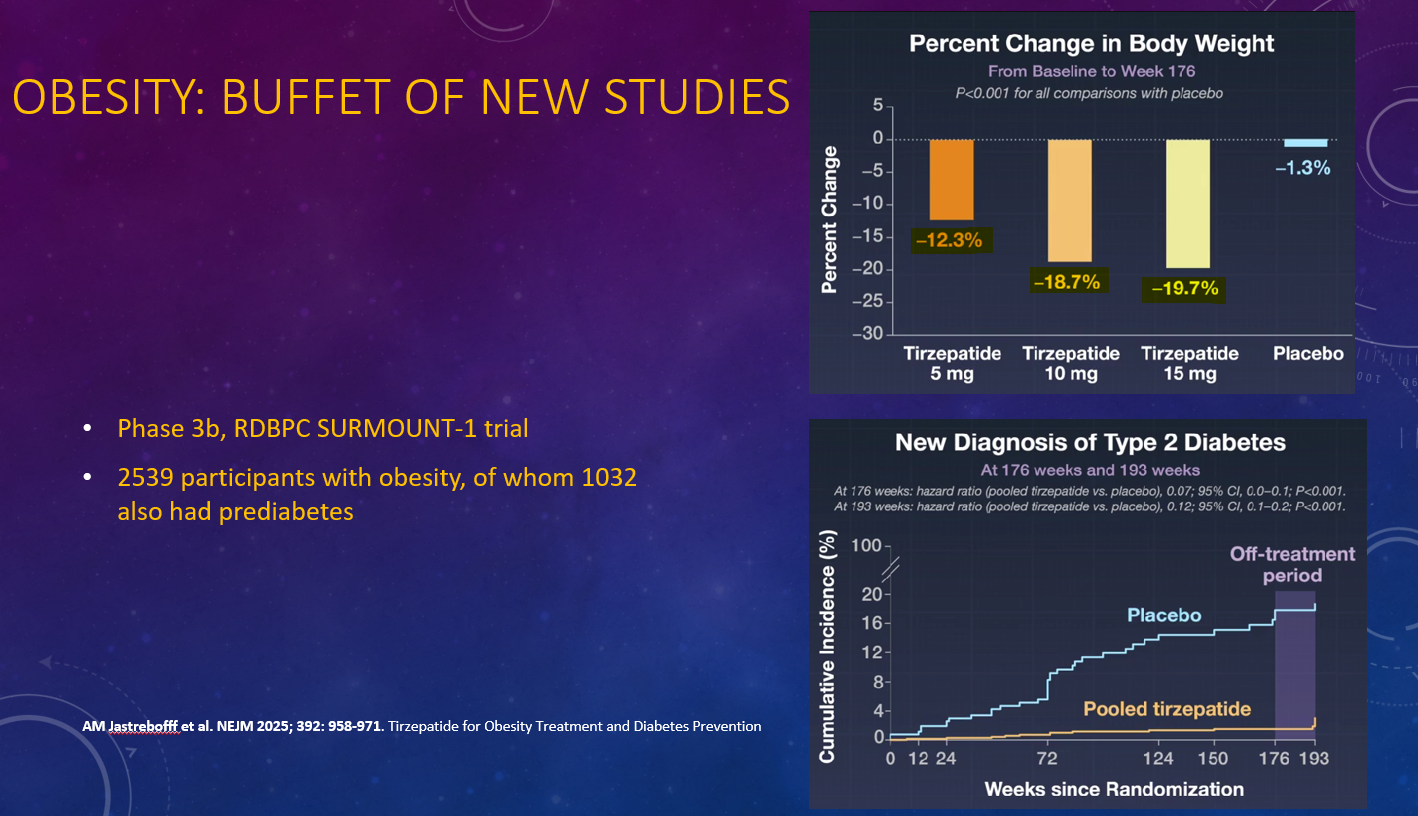
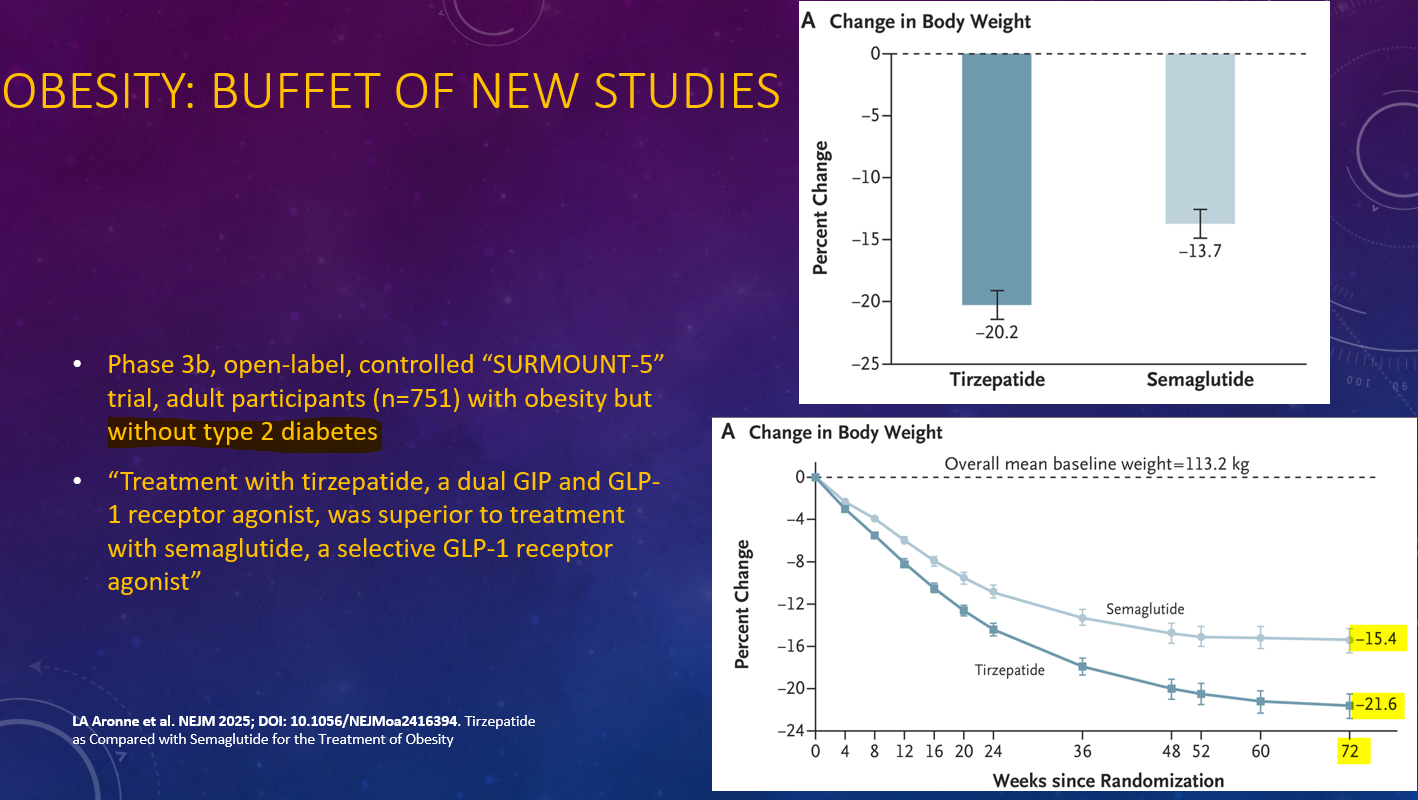
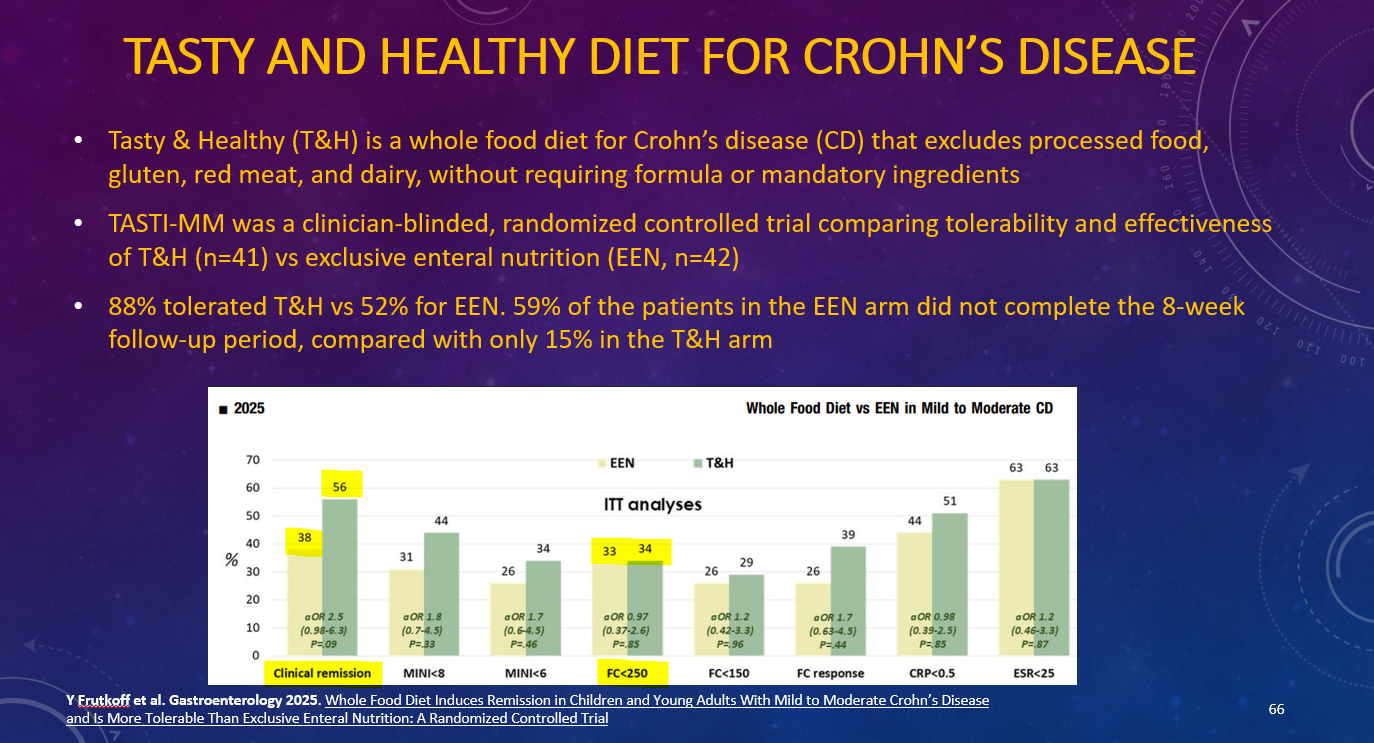
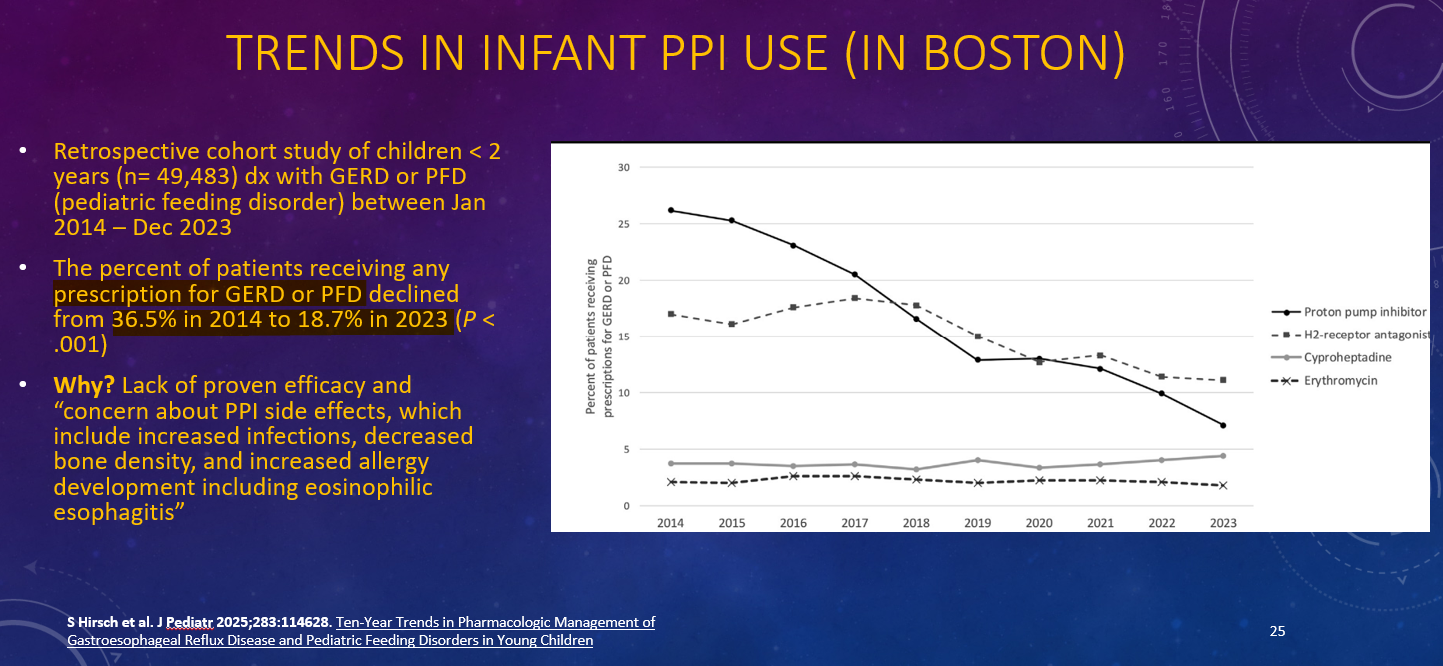
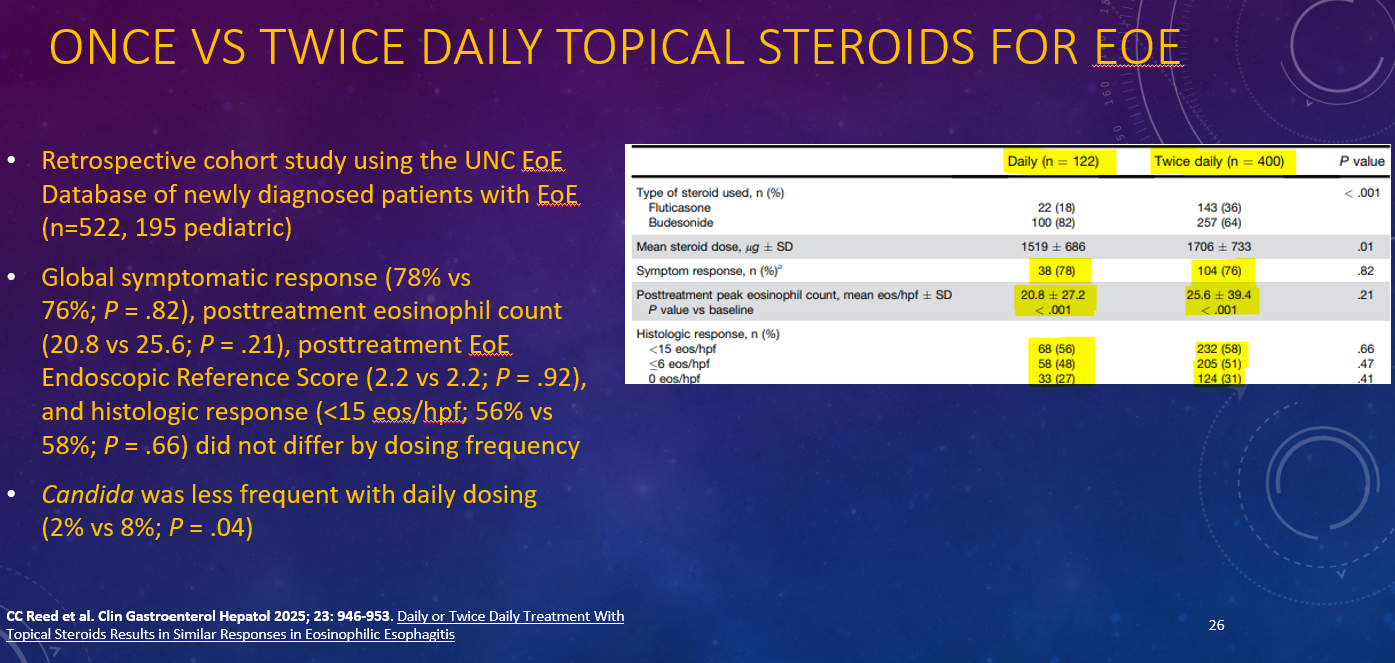
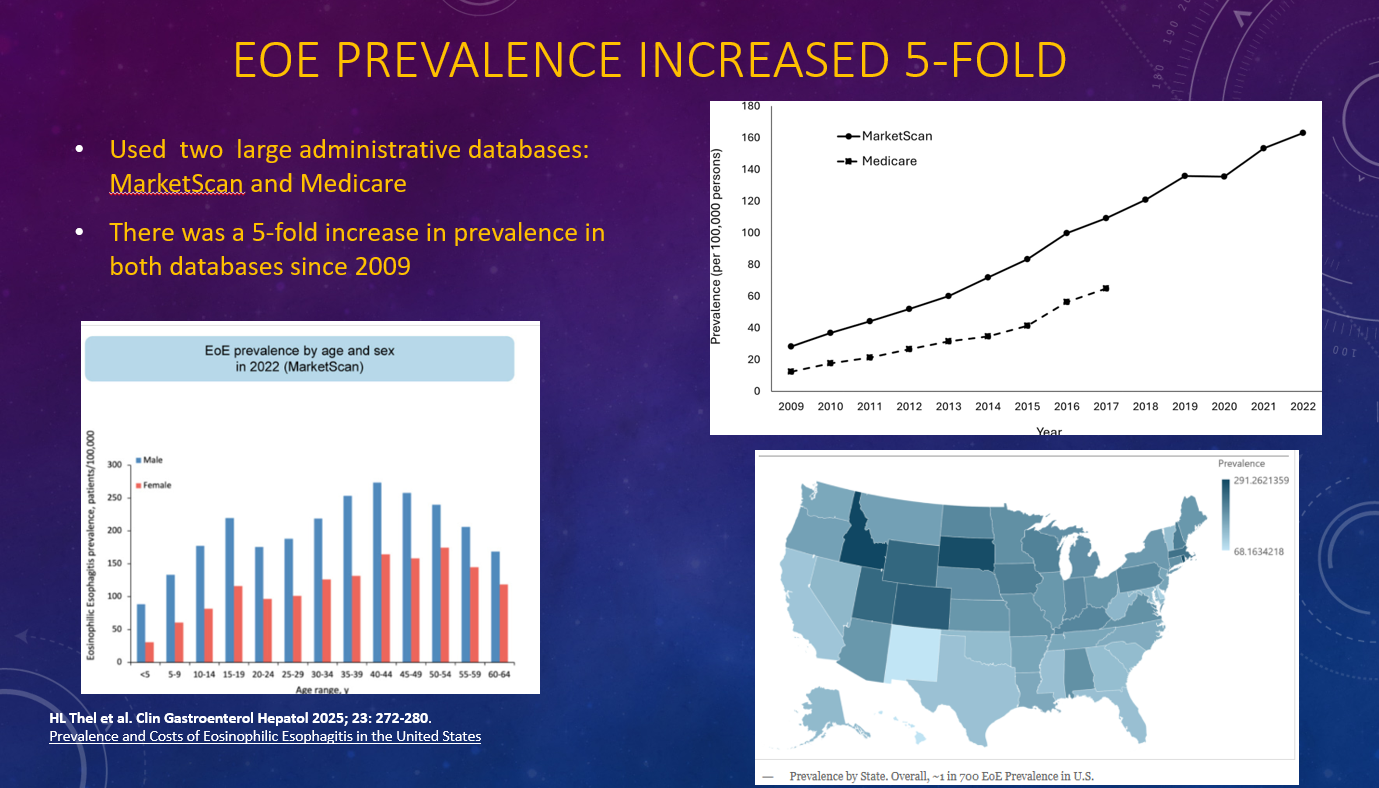
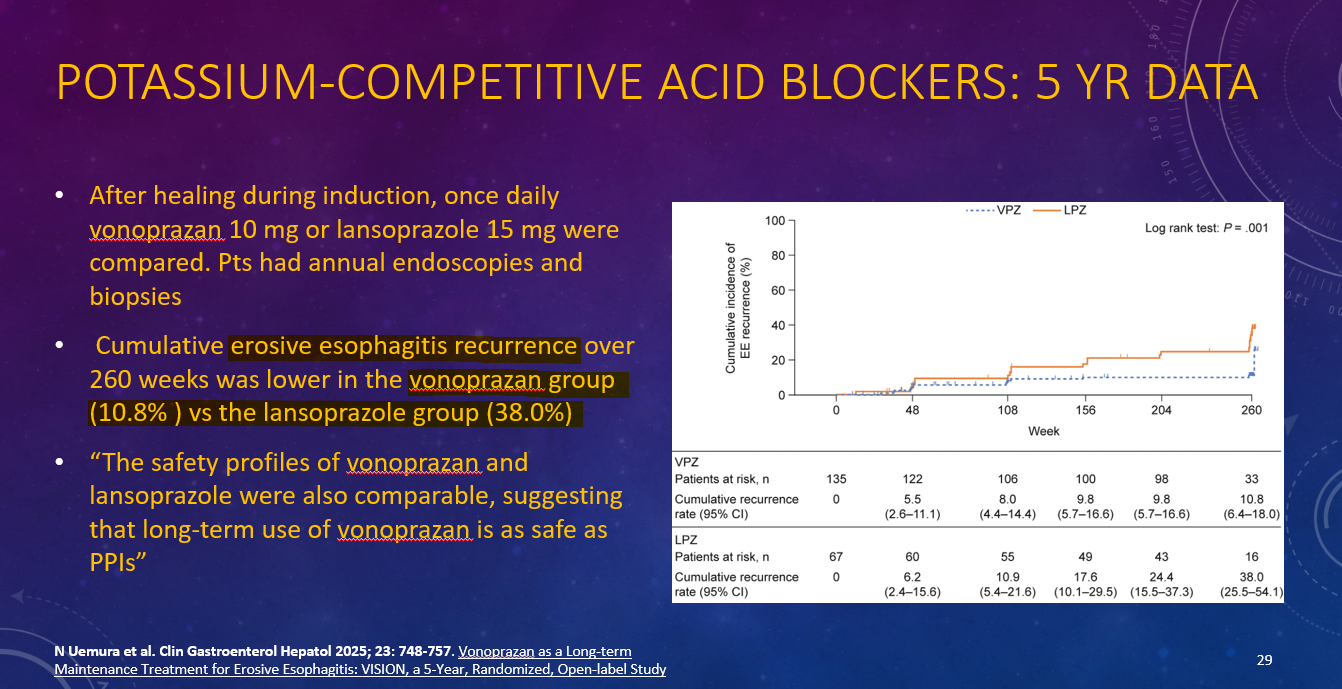
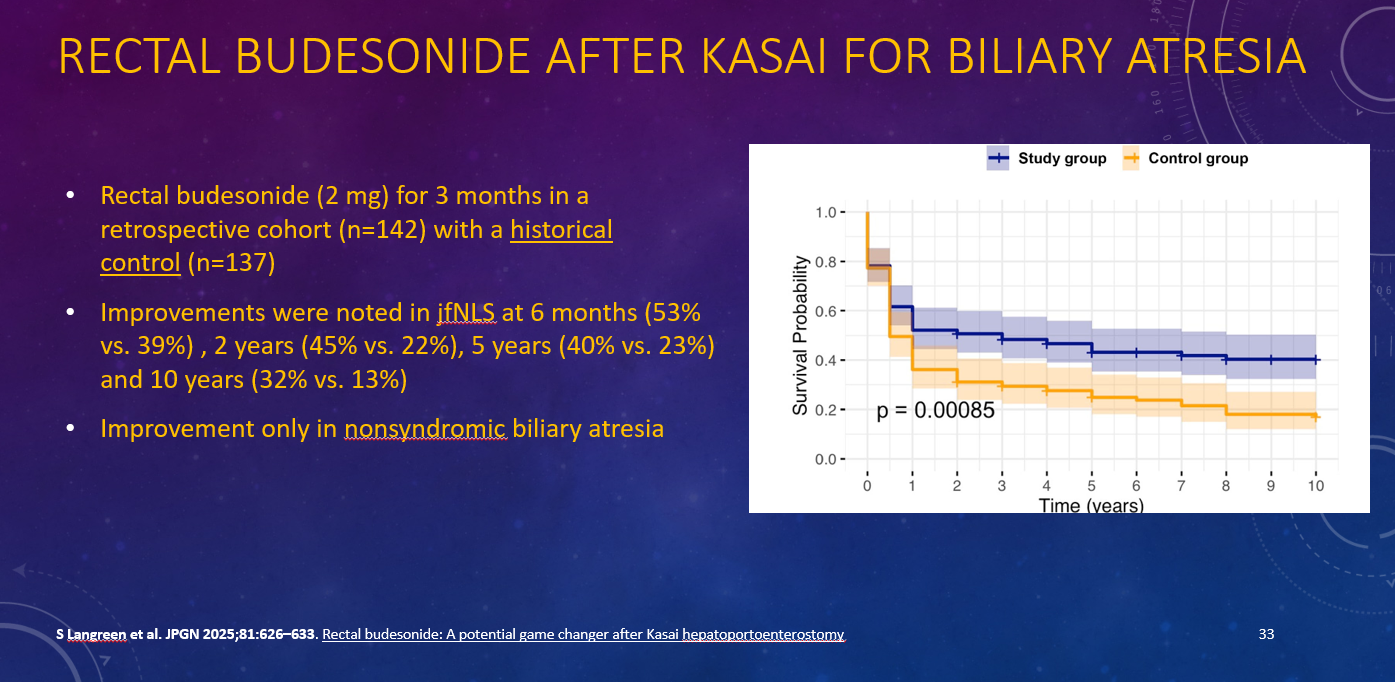
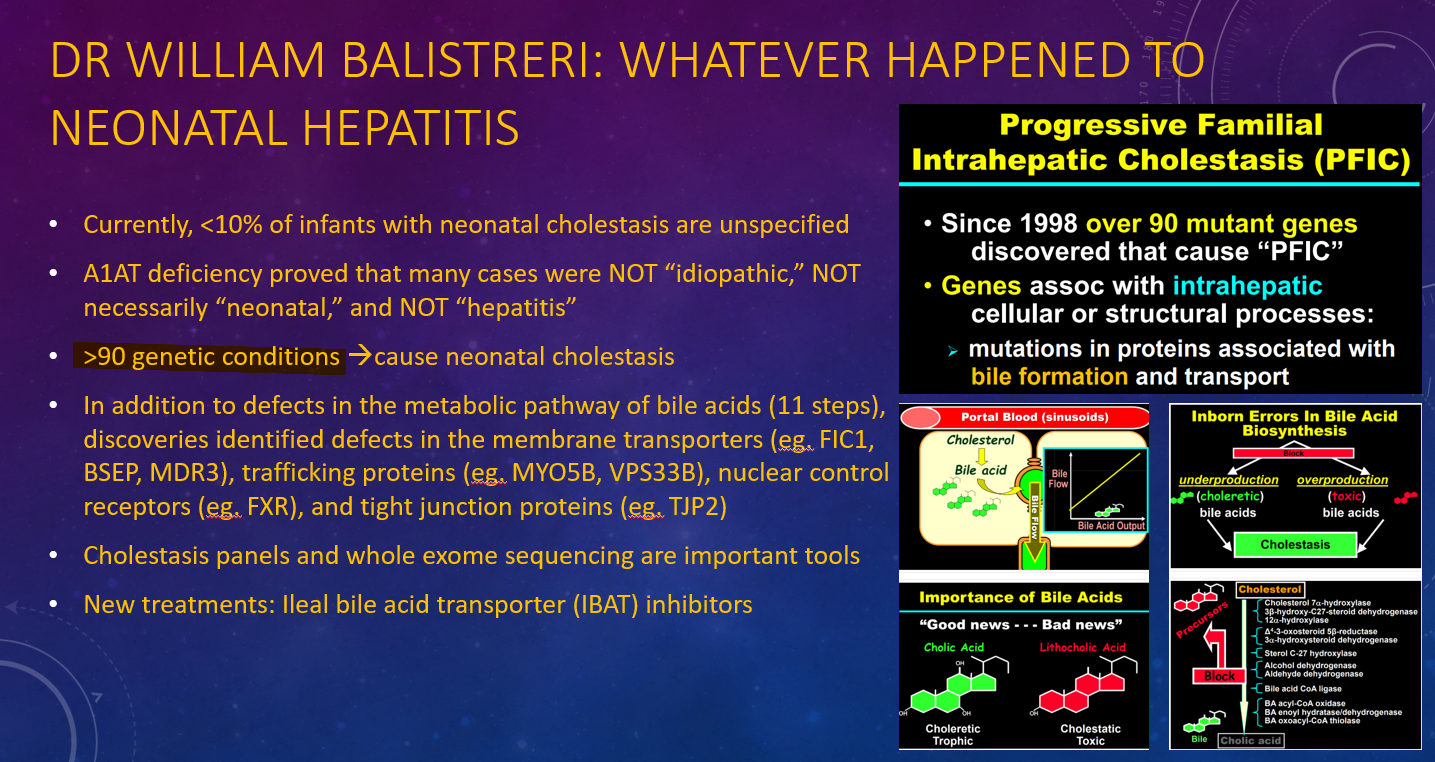
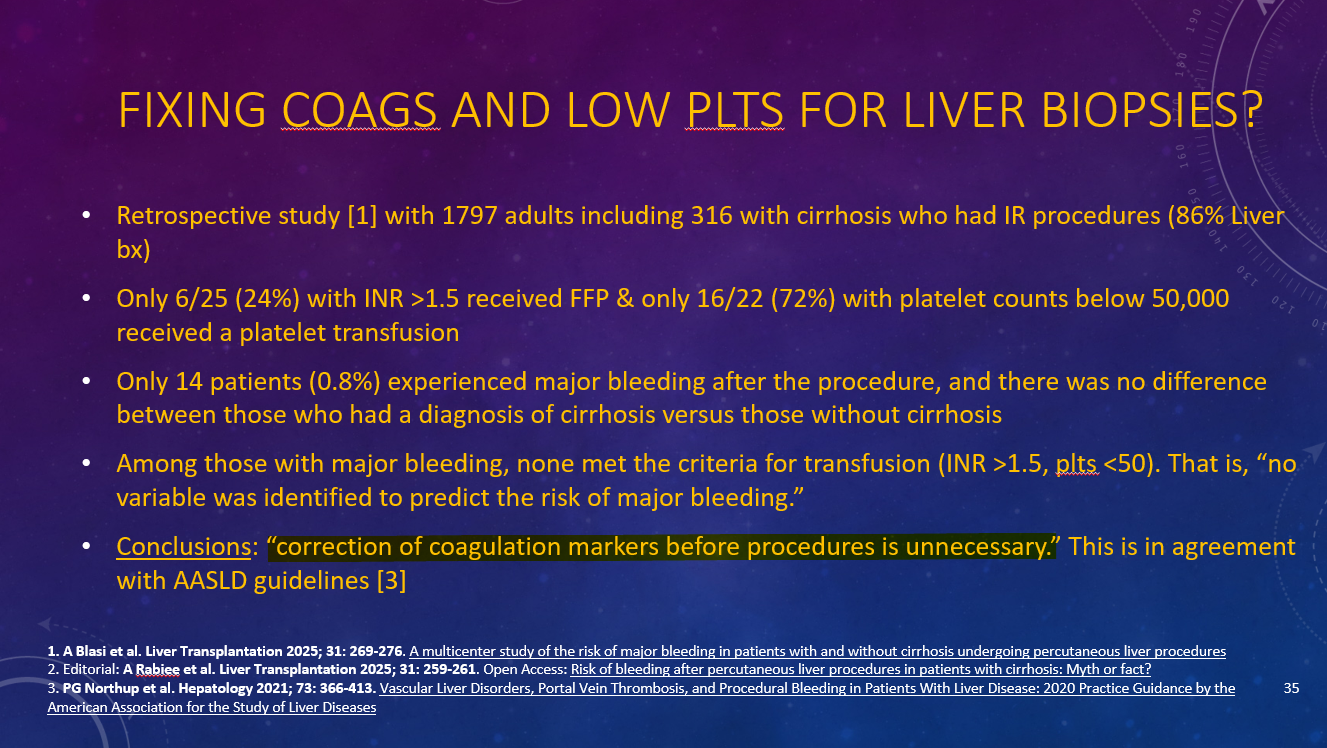
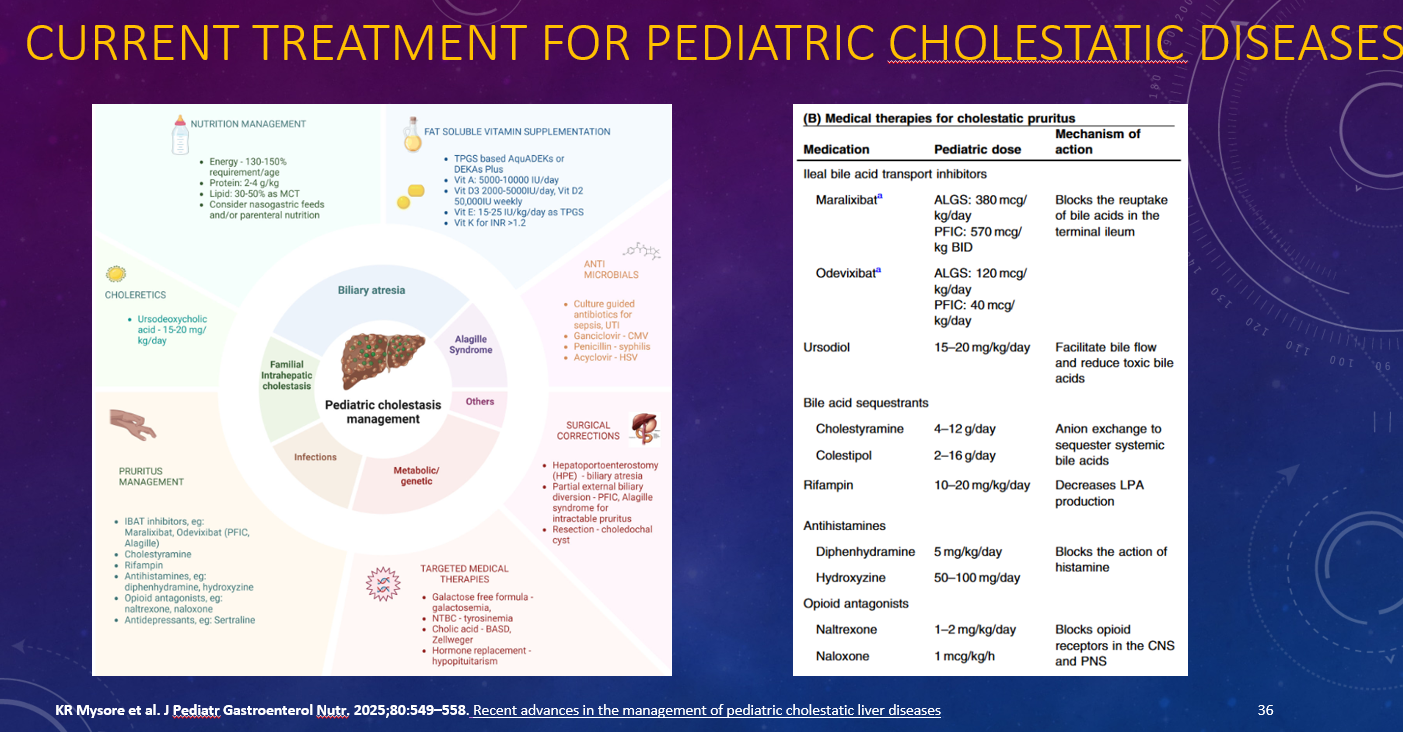
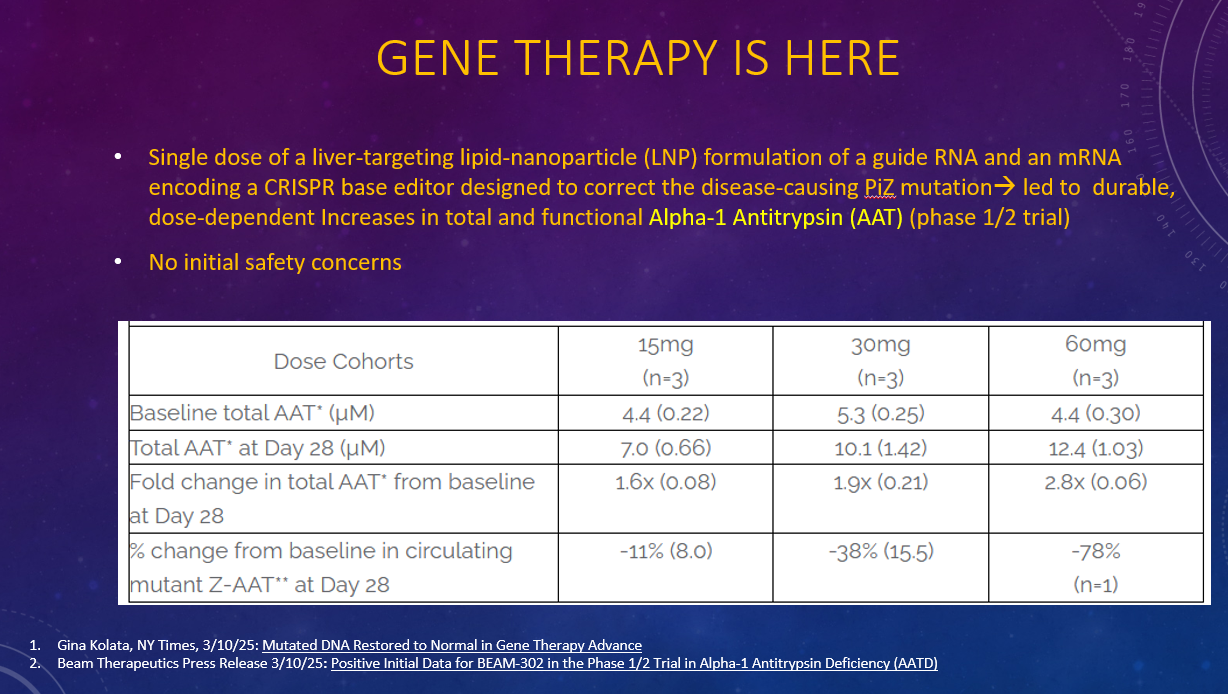
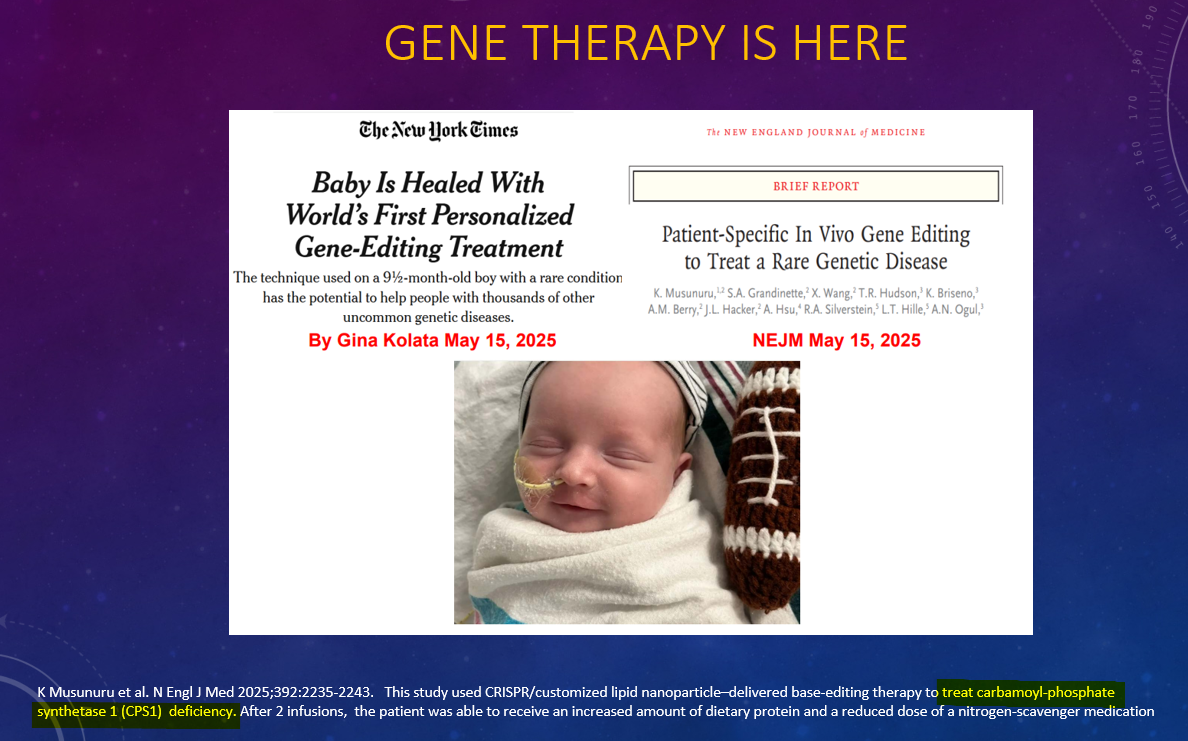
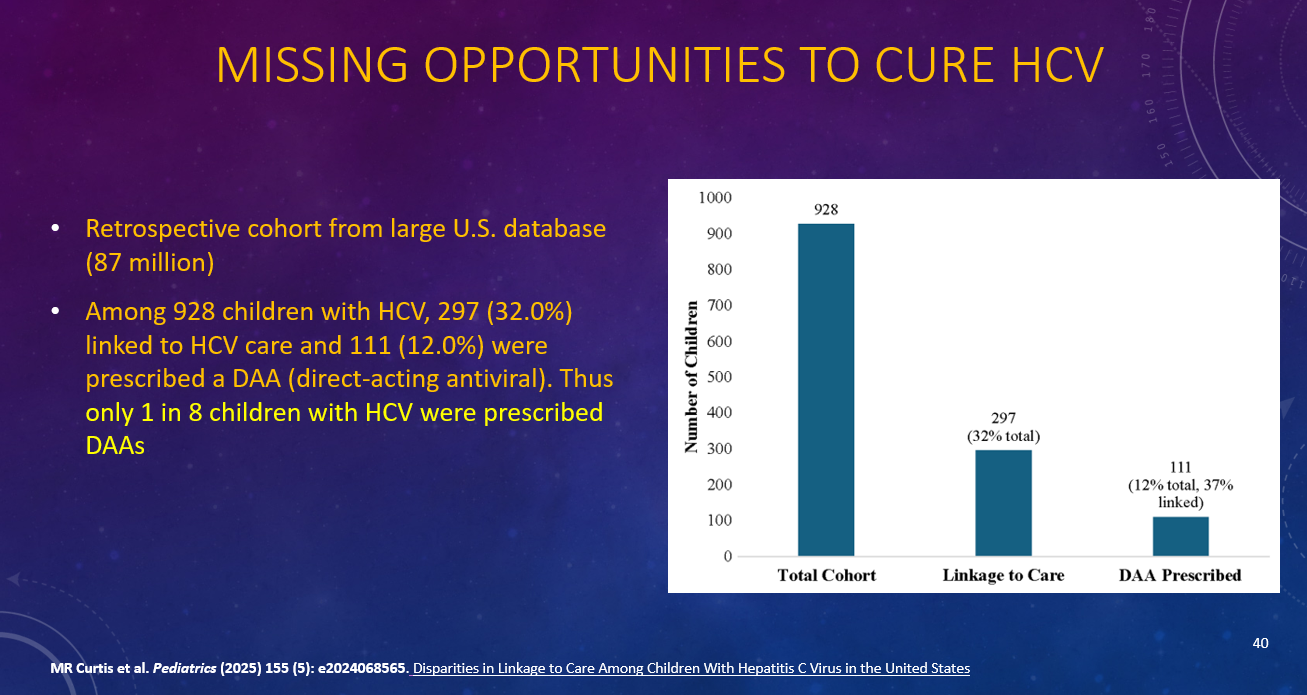
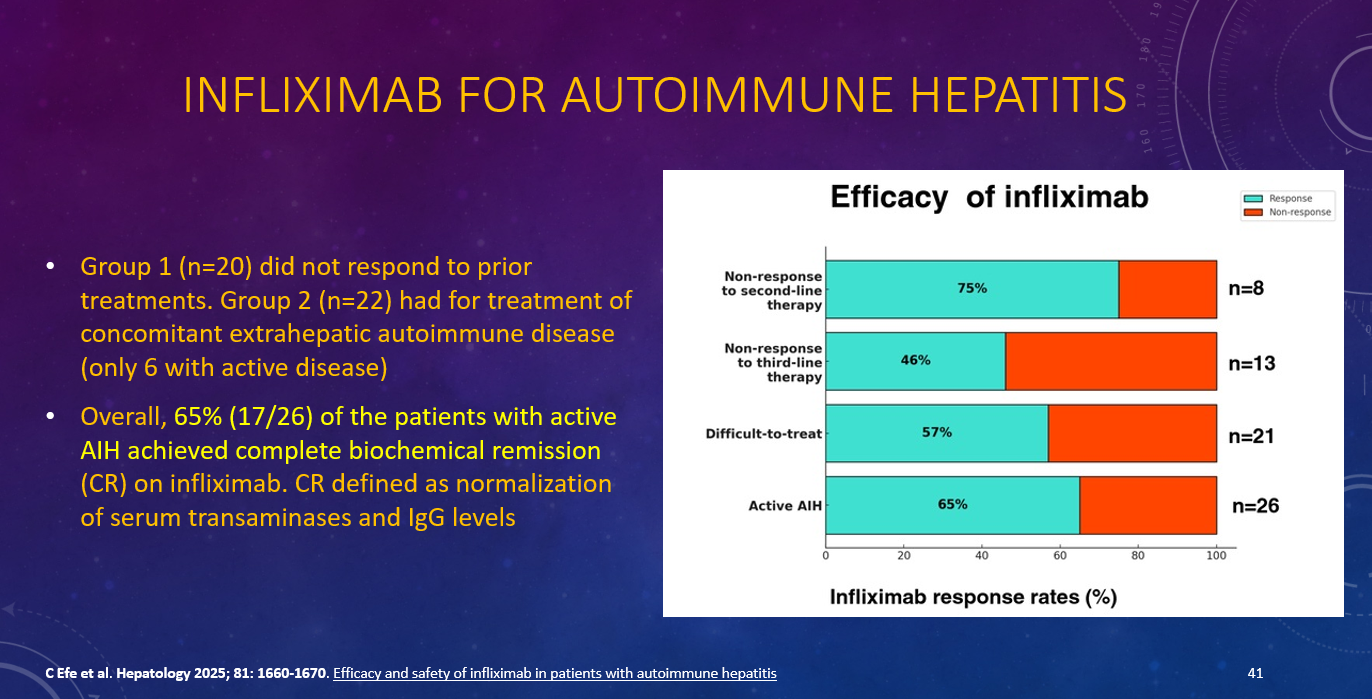
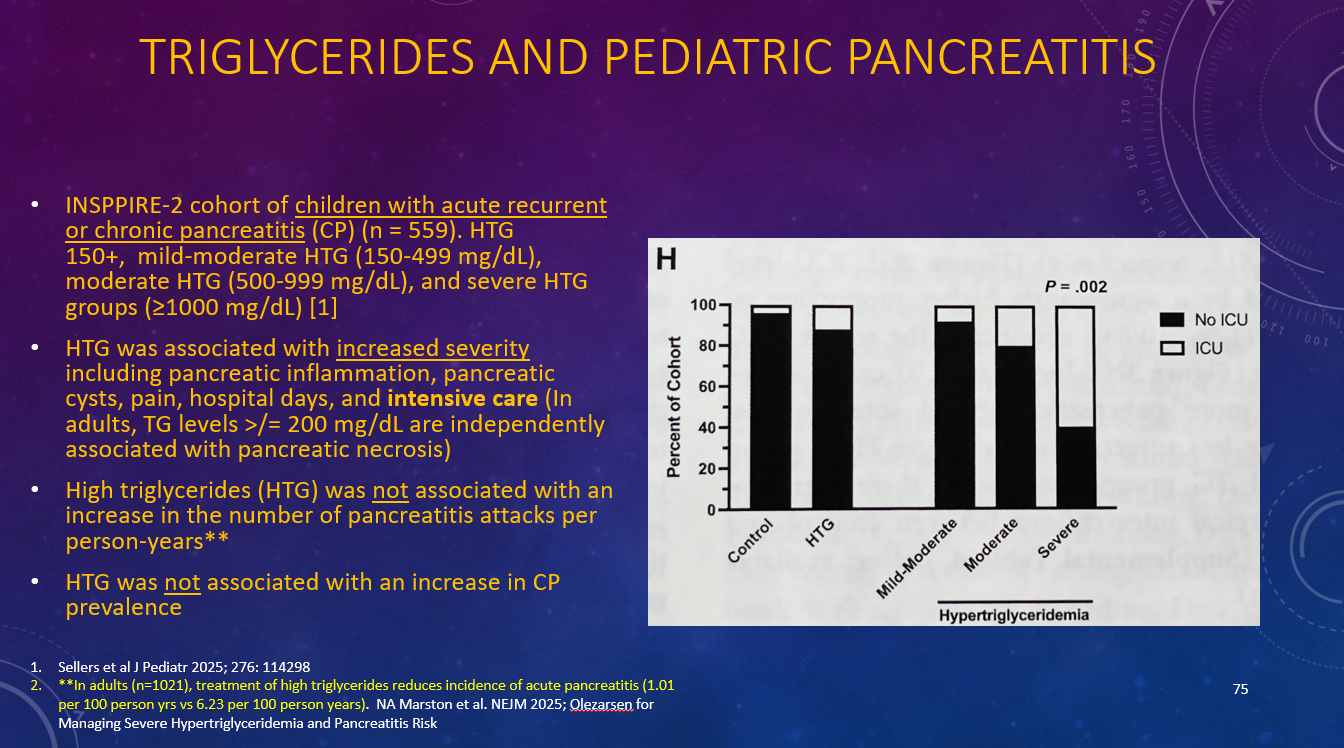
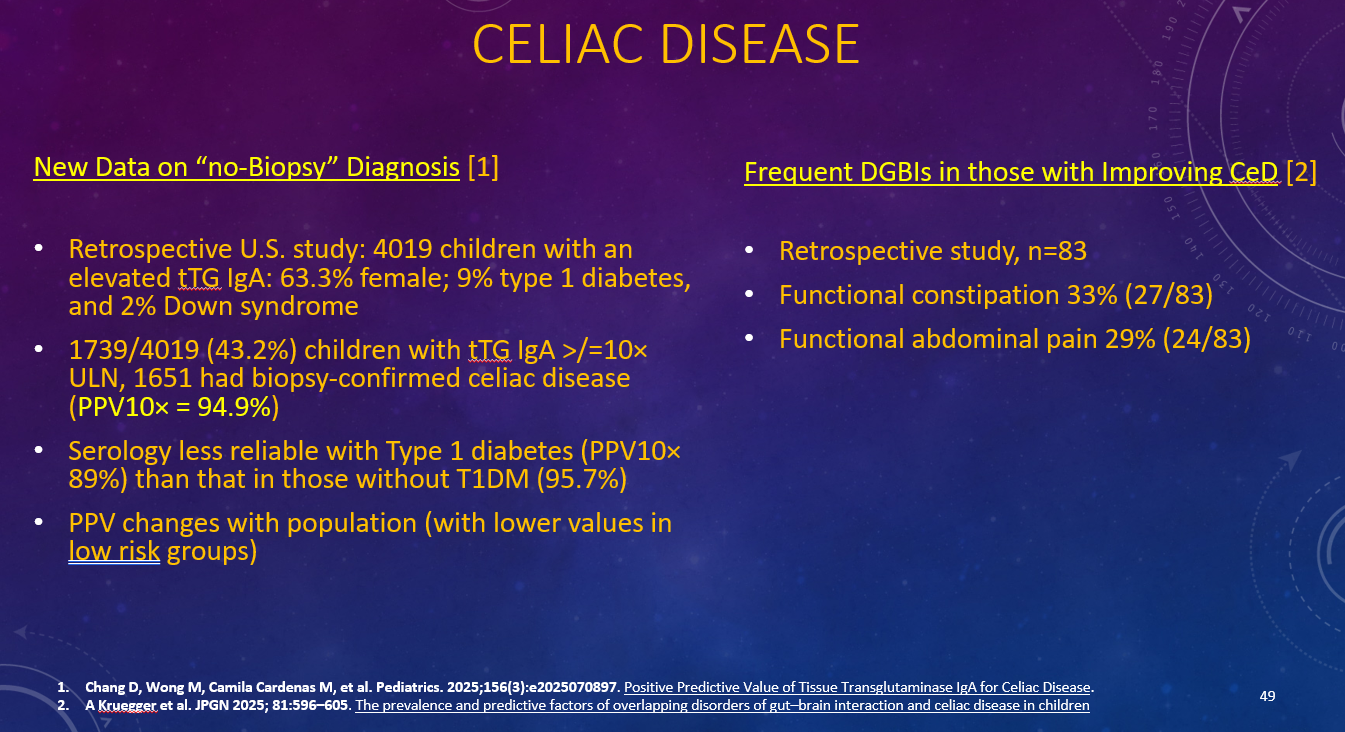
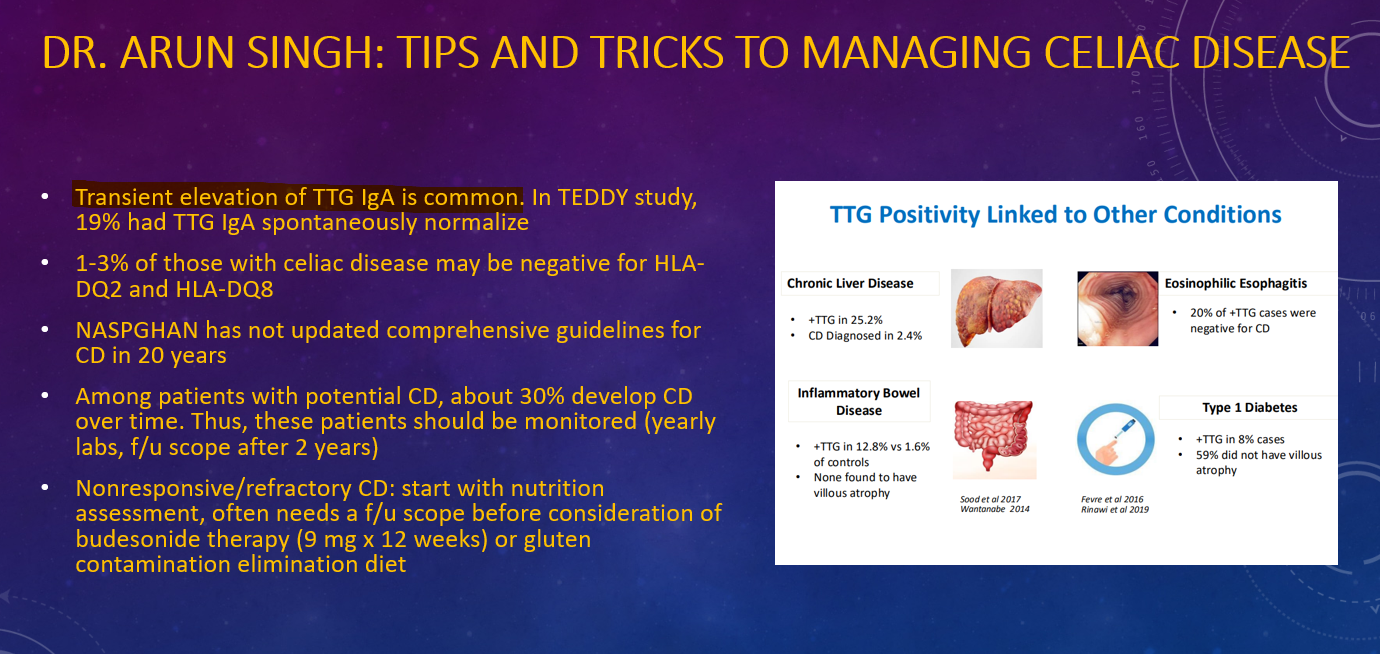
This year was the 2nd year that I had the opportunity to give a lecture to our group that reviewed much of the important advances that happened in 2025. All of the slides are based on studies or lectures that were reviewed on my blog, gutsandgrowth. Here are some of the slides:

It turns out that there has been a DBPC study for parachute use

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.

GutsandGrowth: 2025 Year in Review (Part 2)

This year was the 2nd year that I had the opportunity to give a lecture to our group that reviewed much of the important advances that happened in 2025. All of the slides are based on studies or lectures that were reviewed on my blog, gutsandgrowth. Here are some of the slides:

Disclaimer: This blog, gutsandgrowth, assumes no responsibility for any use or operation of any method, product, instruction, concept or idea contained in the material herein or for any injury or damage to persons or property (whether products liability, negligence or otherwise) resulting from such use or operation. These blog posts are for educational purposes only. Specific dosing of medications (along with potential adverse effects) should be confirmed by prescribing physician.  Because of rapid advances in the medical sciences, the gutsandgrowth blog cautions that independent verification should be made of diagnosis and drug dosages. The reader is solely responsible for the conduct of any suggested test or procedure.  This content is not a substitute for medical advice, diagnosis or treatment provided by a qualified healthcare provider. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a condition.